Your new post is loading...

|
Scooped by
Gilbert C FAURE
December 27, 2013 5:57 AM
|
Pathology, Diagnosis and Therapy
|
|
Scooped by
Gilbert C FAURE
October 8, 8:43 AM
|
|
|
Scooped by
Gilbert C FAURE
October 6, 10:25 AM
|
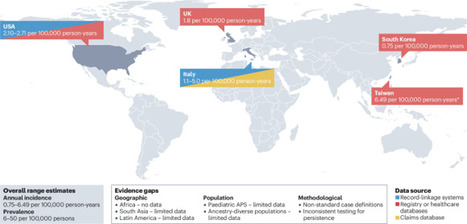
This Review provides a comprehensive overview of available evidence on the epidemiology of antiphospholipid syndrome (APS). The authors highlight the challenges associated with defining APS and its clinical heterogeneity and emphasize key areas that require further research to improve...
|
|
Scooped by
Gilbert C FAURE
August 17, 6:53 AM
|
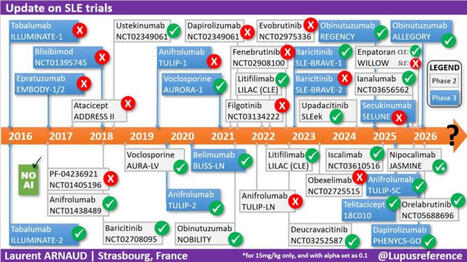
✅ 10 YEARS of RANDOMIZED TRIALS in #LUPUS ⏲️summarized on a single slide!!!! With a specific focus on phase 2(b) and 3 #RCTs, as well as whether the main endpoint was reached or not 👍 The least we can say, is that we have collectively put A LOT OF EFFORT in the development of new treatments 💊 in #SLE. As always I used only my natural intelligence (#NoAI) so please let me know if I have forgotten a trial or if something needs to be corrected.
|
|
Scooped by
Gilbert C FAURE
August 10, 7:36 AM
|
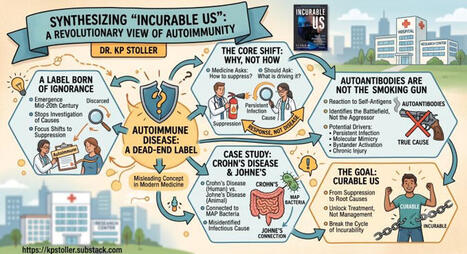
Why "Autoimmune Disease" is a Diagnostic Dead End 🔬
Here is a summary of the main points from the article written by Dr. Kenneth P. Stoller, which discusses his book Incurable Us:
The Main Idea: The author deeply questions the concept of "autoimmune disease." According to him, the idea that the immune system inexplicably turns against its own body is one of the most misleading concepts in modern medicine. The immune system is not the disease; it is merely reacting to a threat.
Key Points of His Argument:
A label born of ignorance: Historically, when medicine failed to find the cause of certain diseases, it ended up grouping them under the "autoimmune" label. The problem with this diagnosis is that it often puts an end to the search for the true cause of the disease.
The wrong medical question: Instead of looking for the root cause by asking, "What is triggering this immune response?", modern medicine has settled for asking, "How do we suppress this response?" (often using immunosuppressants).
Autoantibodies are just a symptom: The author does not deny the existence of autoantibodies or the damage they cause to healthy tissues. However, he asserts that they are proof that a battle is taking place, but do not indicate who started the war. Factors such as a persistent infection, molecular mimicry, or chronic injury can produce these autoantibodies.
The example of Crohn's disease: The article highlights a link between Crohn's disease (often considered autoimmune) and Johne's disease (a known bacterial infection in animals, caused by MAP bacteria). This illustrates his point: what is labeled "autoimmune" often hides an undiagnosed underlying infection.
In Conclusion: This reflection, which is at the heart of his book Incurable Us, calls for a medical paradigm shift: we must stop blaming the patients' immune systems and start hunting down the true external and infectious causes of these complex diseases again.
To read the article: https://lnkd.in/g2hSWvqg
Short video: https://lnkd.in/gGqWcsdV
#medicine #health #disease #autoimmune #diagnostics #IncurableUs #curable #kennethpstoller #docstoller
|
|
Scooped by
Gilbert C FAURE
August 4, 10:55 AM
|
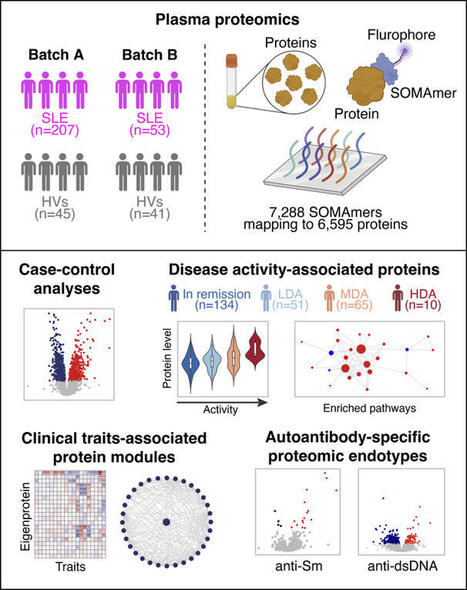
Plasma proteomic profiles of SLE. We recruited 268 patients with SLE and 86 HVs. The cohort encompassed a wide range of disease duration and disease activity (Table 1). Positivity for autoantibodies was as follows: anti-dsDNA n = 70 patients (28%), anti-Sm n = 63 (24.6%), anti-Ro60 n = 120...
|
|
Scooped by
Gilbert C FAURE
June 28, 4:46 AM
|
Wonderful news!
Five lupus patients in England are in remission after being treated with a revolutionary therapy that genetically modifies their own cells, in a medical breakthrough that could offer people a cure, doctors have said.
CAR (chimeric antigen receptor) T-cell therapy involves removing a type of white blood cell also called T lymphocytes, which are crucial for hunting out infected or damaged cells, and engineering them to spot and destroy disease. The T-cells are then fed back into the patient via an infusion to reset their immune system.
The therapy is already revolutionising cancer treatment. Now medics in London have successfully used the technique to effectively cure five NHS patients with severe lupus aged between 19 and 50.
CAR T-cell therapy, which patients only need to have once, could transform lupus treatment and remove the need for lifelong medication, doctors said.
|
|
Scooped by
Gilbert C FAURE
June 19, 1:19 PM
|
Sjögren’s Syndrome (SjS) has historically been associated with classical anti-Ro60/SSA, Ro52/SSA and La/SSB, however they are lacking in one third of the patients, which induces delays in diagnosis, and their disease-contributing role is debated. Here we have applied a SjS-tailored Systems Serology approach to a cohort of 58 SjS and 16 non-SjS sicca syndrome patients, and 40 healthy individuals, involving a multiplex assay measuring antibody isotype, subclass, Fc Receptor and complement engagement to 14 SjS-related autoantigens, an antibody-glycosylation profiling assay and a phagocytosis cell-based assay. Via a machine learning approach, we have identified unique autoantibody signatures, including classical and non-classical autoantigens-related features especially involving autoantigen-specific Fc Receptor binding, with apparent functional consequences. These findings provide interesting insights into the autoantibody responses in SjS, possibly paving the way for improved diagnostics, especially in difficult-to-diagnose patients (e.g., seronegative SjS and non-SjS sicca syndrome patients), and novel therapeutic options targeting autoantibody-specific Fc/Fc Receptor-related effector functions.
|
|
Scooped by
Gilbert C FAURE
June 8, 4:10 AM
|
🎾 Dimanche, Alexander Zverev a soulevé la Coupe des Mousquetaires 🏆.
Ce que les caméras n’ont pas filmé, c’est le deuxième match qu’il jouait en même temps. Celui contre sa propre glycémie.
Zverev est diabétique de type 1 depuis l’âge de 3 ans et demi. Une maladie auto-immune qui détruit les cellules du pancréas produisant l’insuline.
Résultat : son corps n’en fabrique plus une seule goutte. Sans injection, ce n’est pas une gêne,c’est un pronostic vital engagé.
Alors imaginez gérer cela pendant une finale de plus de 4 heures.
L’effort prolongé fait chuter la glycémie : le muscle consomme le glucose, la sensibilité à l’insuline grimpe. Mais le stress, l’adrénaline et le cortisol de la compétition la font, eux, remonter. Ajoutez la chaleur de juin sur l’ocre parisienne, qui accélère l’absorption de l’insuline et peut fausser les capteurs. La glycémie part dans les deux sens, sans prévenir.
Comment fait-il ?
Pas de pompe dernier cri. Zverev gère avec un capteur de glycémie en continu,qu’il consulte à chaque changement de côté et un simple stylo à insuline qu’il dégaine sur le court. Il a d’ailleurs dû batailler pour en obtenir le droit à Roland-Garros, qui le lui refusait au départ. « Si je ne le fais pas, ma vie est en danger », a-t-il répondu.
On lui avait pourtant dit, enfant, qu’une carrière de haut niveau serait impossible. Des médecins, « derrière leur bureau ». Ils avaient tort.
Et c’est là que la science a rattrapé le dogme. À condition de maintenir la glycémie dans la cible, une personne diabétique de type 1 peut atteindre une capacité aérobie comparable à celle d’une personne non diabétique. Le consensus international de référence (Riddell, The Lancet Diabetes & Endocrinology, 2017) en donne la recette :
- réduire l’insuline avant l’effort sans jamais la couper
- apporter 30 à 60 g de glucides par heure
- lire non pas le chiffre, mais la tendance 📈.
Team Novo Nordisk, équipe cycliste professionnelle composée exclusivement de diabétiques de type 1, le prouve chaque saison dans le peloton international.
Soyons clairs, en cardiologie/diabétologie : on ne « gagne » pas contre un diabète de type 1. La maladie est là le lendemain matin. Elle reste un facteur de risque cardiovasculaire majeur, à surveiller toute une vie.
Ce que Zverev démontre, ce n’est pas que la volonté guérit. C’est que la technologie et la discipline déplacent le plafond,celui que des décennies de prudence médicale avaient fixé bien trop bas.
Aujourd’hui, on gère le diabète de type 1. Demain, en guérira-t-on ?
Les avancées en cours méritent un post à part,j’y reviens bientôt.
À 9 ans, on lui a listé tout ce qu’il ne ferait jamais.
Dimanche, pendant que le public suivait le score, lui suivait une autre courbe,sur son capteur, entre deux jeux.
Les deux ont fini dans le vert.
Hôpital Américain de Paris
|
|
Scooped by
Gilbert C FAURE
May 13, 3:29 AM
|
Antiphospholipid antibodies (aPL) are directed against phospholipids and phospholipid-binding proteins. Laboratory assays used to detect aPL include serological tests for aPL against β2-glycoprotein 1, cardiolipin and other molecules, as well as functional assays for lupus anticoagulant. The presence of aPL can lead to endothelial dysfunction or a hypercoagulable state through prothrombotic and antifibrinolytic mechanisms. These processes, often in conjunction with a ‘second hit’, such as trauma, surgery, or other causes of hypercoagulability or stasis, can lead to venous or arterial thrombosis. The thrombotic risk associated with aPL is best recognized in thrombotic antiphospholipid syndrome, characterized by a persistently positive test for lupus anticoagulant or seropositivity for aPL associated with venous, arterial or microvascular thrombosis. However, aPL seropositivity and its clinical effect on thrombotic events have been increasingly recognized in a broader group of individuals who do not meet traditional research criteria for thrombotic antiphospholipid syndrome. In this Review, we provide an overview of the evidence related to aPL seropositivity in individuals with or without previous thrombosis and the clinical relevance of aPL seropositivity in predicting the risk of thrombotic cardiovascular events. We discuss potential management strategies and identify key knowledge gaps that warrant further research. Antiphospholipid antibodies (aPL) are associated with an elevated risk of thromboembolic events in patients with antiphospholipid syndrome and, increasingly, in those without previous thrombosis. In this Review, Bikdeli and colleagues discuss the clinical relevance of aPL seropositivity in predicting the risk of thrombotic cardiovascular events, summarize potential management strategies and identify key knowledge gaps that warrant further research.
|
|
Scooped by
Gilbert C FAURE
May 9, 5:28 AM
|
Help!! They're attacking our balls!!
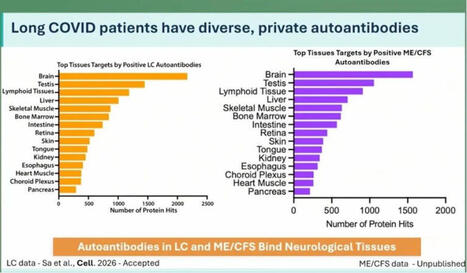
At the ME/CFS conference in Berlin today, Keyla Sá from the Akiko Iwasaki group at Yale showed that Long Covid patients have more autoantibodies targeting neurological tissue. This was apparently tested in both human and mouse tissue.
In ME there are even more autoantibodies than in Long Covid, but number 2 on the list are the cojones.
Interesting. 🍒
Maybe this helps explain why some men develop ME even though the disease is normally more common in women?
Testosterone seems to actually protect against this kind of immune misfire. We see this in research on trans men: https://lnkd.in/ewjxZsRZ
If that protection drops for any reason, the immune system can start attacking your own tissues?
Including your balls?
That’s bullocks!!
https://lnkd.in/eE-giXTv
#pwme #myalgicE #millionsmissing #severeME #MECFSConf2026
|
|
Scooped by
Gilbert C FAURE
April 10, 3:59 AM
|
L'importance du thymus de plus en plus reconnue.
On est loin d'un organe qui n'avait plus d'importance après la puberté.
|
|
Scooped by
Gilbert C FAURE
March 26, 4:13 AM
|
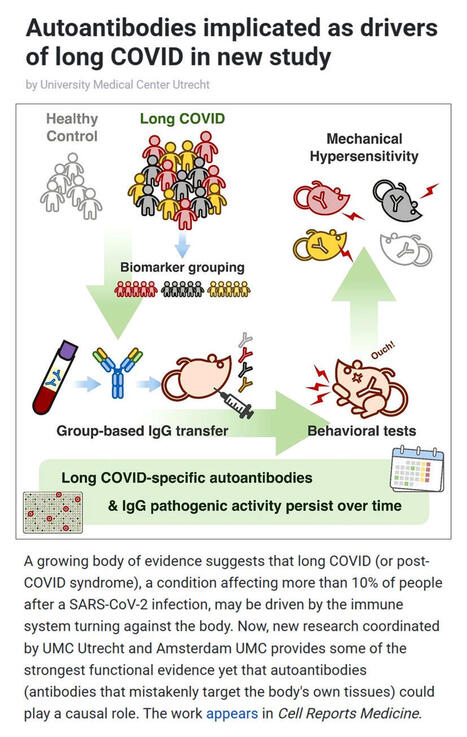
A new study coordinated by UMC Utrecht and Amsterdam UMC provides compelling evidence that #longCOVID may be driven by #autoimmunity - where the #immunesystem turns against the body.
▪️ Affecting over 10% of people after #SARSCoV2 #infection, long COVID is known for symptoms like fatigue, pain, and cognitive dysfunction. Yet its underlying #biology has remained unclear.
▪️In this study, researchers transferred IgG #antibodies from long COVID patients into mice triggering persistent pain-like symptoms that lasted weeks. Remarkably, antibodies collected from the same patients two years later produced the same effect, suggesting a long-lasting disease mechanism.
▪️Co-study leads Prof. Niels Eijkelkamp (UMC Utrecht) and Dr. Jeroen den Dunnen (Amsterdam UMC) highlight two key insights:
- Long COVID may be driven by persistent, pathogenic autoantibodies
- The condition is likely heterogeneous, with distinct biological subtypes
▪️The team also identified diverse autoantibodies targeting immune, neurological, and metabolic pathways - many persisting for years.
▪️These findings, published in Cell Reports Medicine by Cell Press, not only strengthen the case for an autoimmune basis of long COVID but also open the door to targeted treatments like immunoadsorption, plasmapheresis, and precision immunotherapy.
As research converges globally on similar findings, this marks a major step toward understanding - and treating - long COVID.
🗃️ See comments for reference.
|
|
|
Scooped by
Gilbert C FAURE
October 14, 6:49 AM
|
|
|
Scooped by
Gilbert C FAURE
October 8, 8:19 AM
|
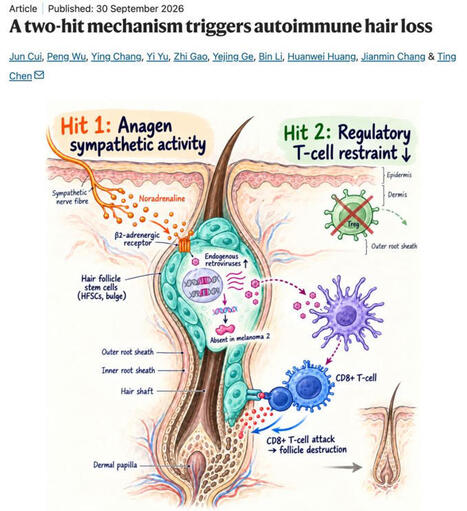
𝗦𝘁𝗿𝗲𝘀𝘀 + 𝗹𝗼𝘀𝘁 𝘁𝗼𝗹𝗲𝗿𝗮𝗻𝗰𝗲 = 𝗔𝘂𝘁𝗼𝗶𝗺𝗺𝘂𝗻𝗲 𝗵𝗮𝗶𝗿 𝗹𝗼𝘀𝘀
𝘚𝘵𝘳𝘦𝘴𝘴, 𝘦𝘯𝘥𝘰𝘨𝘦𝘯𝘰𝘶𝘴 𝘳𝘦𝘵𝘳𝘰𝘷𝘪𝘳𝘶𝘴𝘦𝘴 𝘢𝘯𝘥 𝘭𝘰𝘴𝘵 𝘛𝘳𝘦𝘨 𝘵𝘰𝘭𝘦𝘳𝘢𝘯𝘤𝘦 𝘤𝘰𝘯𝘷𝘦𝘳𝘨𝘦 𝘵𝘰 𝘵𝘳𝘪𝘨𝘨𝘦𝘳 𝘊𝘋8+ 𝘛-𝘤𝘦𝘭𝘭-𝘮𝘦𝘥𝘪𝘢𝘵𝘦𝘥 𝘢𝘶𝘵𝘰𝘪𝘮𝘮𝘶𝘯𝘦 𝘩𝘢𝘪𝘳 𝘭𝘰𝘴𝘴.
🧠 𝗔 𝗽𝗮𝗽𝗲𝗿 𝗮 𝗱𝗮𝘆 𝗸𝗲𝗲𝗽𝘀 𝗯𝗿𝗮𝗶𝗻 𝗱𝗲𝗰𝗮𝘆 𝗮𝘄𝗮𝘆 🧠
Wednesday, 7 October 2026
𝘏𝘢𝘪𝘳 𝘧𝘰𝘭𝘭𝘪𝘤𝘭𝘦 𝘴𝘵𝘦𝘮 𝘤𝘦𝘭𝘭𝘴 𝘢𝘳𝘦 𝘯𝘰𝘳𝘮𝘢𝘭𝘭𝘺 𝘱𝘳𝘰𝘵𝘦𝘤𝘵𝘦𝘥 𝘧𝘳𝘰𝘮 𝘪𝘮𝘮𝘶𝘯𝘦 𝘢𝘵𝘵𝘢𝘤𝘬. 𝘊𝘶𝘪, 𝘞𝘶 𝘦𝘵 𝘢𝘭. 𝘴𝘩𝘰𝘸 𝘪𝘯 𝘮𝘪𝘤𝘦 𝘵𝘩𝘢𝘵 𝘢𝘯𝘢𝘨𝘦𝘯-𝘭𝘪𝘯𝘬𝘦𝘥 𝘴𝘺𝘮𝘱𝘢𝘵𝘩𝘦𝘵𝘪𝘤 𝘯𝘰𝘳𝘢𝘥𝘳𝘦𝘯𝘢𝘭𝘪𝘯𝘦 𝘴𝘪𝘨𝘯𝘢𝘭𝘭𝘪𝘯𝘨 𝘵𝘩𝘳𝘰𝘶𝘨𝘩 𝘈𝘋𝘙𝘉2 𝘤𝘳𝘦𝘢𝘵𝘦𝘴 𝘢 𝘵𝘳𝘢𝘯𝘴𝘪𝘦𝘯𝘵𝘭𝘺 𝘷𝘶𝘭𝘯𝘦𝘳𝘢𝘣𝘭𝘦 𝘧𝘰𝘭𝘭𝘪𝘤𝘶𝘭𝘢𝘳 𝘴𝘵𝘢𝘵𝘦 𝘵𝘩𝘢𝘵 𝘱𝘳𝘰𝘨𝘳𝘦𝘴𝘴𝘦𝘴 𝘵𝘰 𝘢𝘶𝘵𝘰𝘪𝘮𝘮𝘶𝘯𝘦 𝘥𝘦𝘴𝘵𝘳𝘶𝘤𝘵𝘪𝘰𝘯 𝘸𝘩𝘦𝘯 𝘳𝘦𝘨𝘶𝘭𝘢𝘵𝘰𝘳𝘺 𝘛-𝘤𝘦𝘭𝘭 𝘤𝘰𝘯𝘵𝘳𝘰𝘭 𝘪𝘴 𝘭𝘰𝘴𝘵.
💡 𝗧𝗮𝗸𝗲 𝗵𝗼𝗺𝗲 𝗺𝗲𝘀𝘀𝗮𝗴𝗲
• During anagen, sympathetic noradrenaline signals through the β2-adrenergic receptor in hair follicle stem cells, physiologically reactivating endogenous retroviruses before overt inflammation.
• Loss of regulatory T-cell restraint converts this normally tolerated state into autoimmunity. Psychological stress or optogenetic sympathetic activation also renders normally resistant telogen follicles susceptible.
• Endogenous retroviral activity engages absent in melanoma 2 and type 1 conventional dendritic-cell-dependent CD8+ T-cell responses. Reverse-transcriptase inhibition or Aim2 deletion protects follicles from destruction.
🔥 𝗜𝗺𝗽𝗮𝗰𝘁
• Autoimmune hair loss emerges from the convergence of immune dysregulation with a transient physiological tissue state, nominating adrenergic signalling and endogenous retroviral activity for translational testing.
❓ 𝗢𝗽𝗲𝗻 𝗾𝘂𝗲𝘀𝘁𝗶𝗼𝗻𝘀
• Do well-staged human alopecia areata lesions reproduce the sympathetic–β2-adrenergic receptor–endogenous retrovirus axis?
• Which endogenous retroviral nucleic acids and responding cell populations drive absent in melanoma 2 activation in vivo?
• Would reverse-transcriptase inhibition or selective follicular β2-adrenergic receptor blockade prevent or reverse established human disease?
𝗔 𝘁𝘄𝗼-𝗵𝗶𝘁 𝗺𝗲𝗰𝗵𝗮𝗻𝗶𝘀𝗺 𝘁𝗿𝗶𝗴𝗴𝗲𝗿𝘀 𝗮𝘂𝘁𝗼𝗶𝗺𝗺𝘂𝗻𝗲 𝗵𝗮𝗶𝗿 𝗹𝗼𝘀𝘀
Jun Cui, Peng Wu et al.
Nature, September 2026
Corresponding author: Ting Chen
🔗 𝘓𝘪𝘯𝘬 𝘵𝘰 𝘵𝘩𝘦 𝘱𝘶𝘣𝘭𝘪𝘤𝘢𝘵𝘪𝘰𝘯 𝘪𝘯 𝘤𝘰𝘮𝘮𝘦𝘯𝘵𝘴
𝘐𝘭𝘭𝘶𝘴𝘵𝘳𝘢𝘵𝘪𝘰𝘯 𝘨𝘦𝘯𝘦𝘳𝘢𝘵𝘦𝘥 𝘸𝘪𝘵𝘩 𝘊𝘩𝘢𝘵𝘎𝘗𝘛.
𝘛𝘩𝘦 𝘰𝘱𝘪𝘯𝘪𝘰𝘯𝘴 𝘴𝘩𝘢𝘳𝘦𝘥 𝘰𝘯 𝘓𝘪𝘯𝘬𝘦𝘥𝘐𝘯 𝘢𝘳𝘦 𝘮𝘺 𝘰𝘸𝘯.
|
|
Scooped by
Gilbert C FAURE
August 25, 9:14 AM
|
We are excited to report in PNAST-Proceedings Of The National Acad... that autoantibodies neutralizing type I interferons underlie 35% of cases of Chikungunya virus (CHIKV) encephalitis or myelitis from a multiple cohort study (https://lnkd.in/gxux4e6e).
Chikungunya virus (CHIKV), an arthropod-borne virus, has caused many outbreaks. While most patients experience fever and joint pain, in rare cases, it invades the brain or spinal cord, causing fatal complications. Our new paper shows why only some develop these complications.
We studied 245 confirmed CHIKV cases from Martinique and Brazil, including 20 with severe CNS disease (encephalitis, myelitis, encephalomyelitis). In 35% of CNS cases, patients had autoantibodies that neutralize their own type I interferons, the body's frontline antiviral defense.
These autoantibodies were undetectable in all 225 patients with mild infection. However, patients who had these antibodies before infection had approximately 850 times the risk of developing severe CNS disease compared to the general population.
Our data support a mechanism where these autoantibodies block the activity of IFN-I during CHIKV infection. This disruption of the host's normal antiviral responses allows the virus to replicate unchecked and cross into the central nervous system, leading to fatal diseases.
This paper is the latest chapter of a six-year-long story that our lab has been writing. In 2020, we showed that these IFN-I autoantibodies underlie at least 10% of life-threatening COVID-19 pneumonia. This discovery was a glimpse of a larger picture (https://lnkd.in/gU3tERpW).
Since then, our studies have consistently identified the same mechanism in various viruses. Approximately 20% of COVID-19 deaths are attributed to antibodies that are already present in about 4% of individuals over the age of 70 (https://lnkd.in/gMwk9tmm)
Additionally, the Yellow fever vaccine can cause encephalitis, while the West Nile virus can cause encephalitis in about 40% of cases (https://lnkd.in/gFNU-Wzt).
Tick-borne encephalitis can cause encephalitis in about 10% of cases, and Powassan, Usutu, Ross River virus disease, and Chikungunya vaccine (VLA1553) can also cause encephalitis. (Figure: Groen & Hale Curr. Opin. Virol. 2026; https://lnkd.in/gsgXa_ME).
|
|
Scooped by
Gilbert C FAURE
August 12, 3:56 AM
|
It seems that autoimmunity and cancer have finally found common ground 🧐
|
|
Scooped by
Gilbert C FAURE
August 7, 10:04 AM
|
Access educational materials, eLearning activities, accredited Live webinar sessions with polls and chat on this fast Digital Library and Hybrid Virtual Event Platform powered by MULTILEARNING LMS.
|
|
Scooped by
Gilbert C FAURE
July 16, 10:22 AM
|
Macrophage activity is correlated with advanced fibrosis in AILD. To investigate the association between macrophage activation and fibrosis-associated transcriptional programs across AILD, we performed RNA-Seq of cryopreserved tissue samples from 64 clinically indicated liver biopsies of pediatric...
|
|
Scooped by
Gilbert C FAURE
June 22, 10:42 AM
|
Mass spectrometry reveals pneumonia type–specific protein signatures in bronchoalveolar fluid. To identify pneumonia type–specific biomarkers, we sampled BALF and plasma from individuals enrolled in the Successful Clinical Response in Pneumonia Therapy (SCRIPT) study at Northwestern Memorial...
|
|
Scooped by
Gilbert C FAURE
June 11, 1:45 PM
|
|
|
Scooped by
Gilbert C FAURE
May 26, 3:59 AM
|
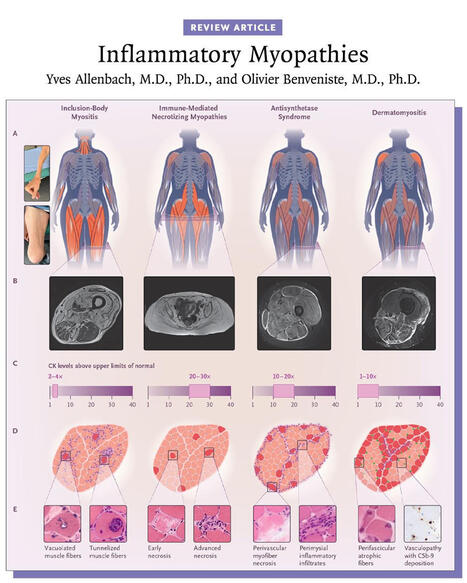
Inflammatory myopathies are typically associated with a myositis-specific autoantibody that determines the diagnosis and prognosis. Myositis subgroups have distinct pathomechanisms that now allow for targeted therapies. 👉 https://nej.md/49Iy9Oo
Inflammatory myopathies are a heterogeneous group of autoimmune diseases characterized by immune-mediated damage to skeletal muscle. They are classified into five major subtypes: inclusion-body myositis, immune-mediated necrotizing myopathies, antisynthetase syndrome, overlapping myositis, and dermatomyositis, each with distinct clinical features and outcomes.
Inclusion-body myositis and immune-mediated necrotizing myopathies primarily affect muscle, with prognosis largely determined by functional impairment, whereas antisynthetase syndrome, overlapping myositis, and dermatomyositis are systemic diseases that can involve the skin, joints, and lungs and may be life-threatening.
The majority of inflammatory myopathies are associated with myositis-specific autoantibodies, which inform diagnosis, subtype classification, and prognosis. Advances in understanding the distinct pathomechanisms underlying each subgroup now enable increasingly targeted therapeutic approaches.
Learn more in the Review Article “Inflammatory Myopathies” by Yves Allenbach, MD, PhD, and Olivier Benveniste, MD, PhD: https://nej.md/49Iy9Oo
#Neurology #Rheumatology
|
|
Scooped by
Gilbert C FAURE
May 13, 3:28 AM
|
Autoantibody flares are important drivers of pathology in systemic lupus erythematosus (SLE), highlighting the pivotal role of B cells in initiating and propagating chronic autoimmunity. Although autoreactive specificities are a normal feature of the naive B cell repertoire, these cells are normally suppressed by layered tolerance checkpoints that limit inappropriate activation. Autoimmune-prone environments can lower these tolerance thresholds, rendering naive autoreactive B cells more sensitive to aberrant cues. Cytokines and other microenvironmental signals shape tissue niches that direct autoreactive B cells towards either germinal-centre or extrafollicular differentiation pathways. Germinal centres support the entry, selection and diversification of autoreactive B cells, with T cell help sustaining these repertoires. By contrast, naive autoreactive B cells entering the extrafollicular pathway exhibit an attenuated requirement for cognate T cell help and strong dependence on complement and TLR signalling. Emerging evidence continues to refine our understanding of germinal-centre and extrafollicular responses as complementary sources of autoreactive effector cells. With this progress, investigations into the origin, development, longevity and tissue dynamics of autoreactive memory B cells as chronic sources of autoantibodies are warranted. Although broad B cell depletion therapies have yielded benefit, a key challenge now is developing precision strategies that selectively target pathogenic B cell subsets. Autoreactive B cells normally held in check by tolerance checkpoints can be driven towards germinal-centre or extrafollicular differentiation in autoimmune environments. This Review examines the cellular, molecular and contextual cues that shape these pathways and considers their implications for systemic lupus erythematosus pathogenesis and therapy.
|
|
Scooped by
Gilbert C FAURE
April 22, 9:47 AM
|
Listen to this episode from Rheumatology Notebooks on Spotify. Podcast on "2023 ACR/EULAR antiphospholipid syndromeclassification criteria".Created with NotebookLM.Intro and outro music created with Suno.Link to the paper: http:// dx.doi. org/ 10. 1136/ ard- 2023-224609
|
|
Scooped by
Gilbert C FAURE
April 10, 3:59 AM
|
New research suggests that amyotrophic lateral sclerosis, or ALS, may be partly an autoimmune disease. Scientists discovered that inflammatory immune cells called CD4+ T cells in people with ALS mistakenly attack a protein found in neurons, known as C9orf72. This self-directed immune response appears to drive rapid disease progression, explaining why ALS can destroy motor neurons quickly and lead to severe physical decline.
The study also revealed two distinct patient groups. One group had highly inflammatory CD4+ T cells and shorter predicted survival, while the second group had more anti-inflammatory CD4+ T cells alongside the harmful ones. These protective T cells appear to regulate the immune response, slowing disease progression and allowing some patients to live significantly longer. Understanding this balance between harmful and protective T cells may help explain why survival in ALS varies dramatically, from just a couple of years to several decades in rare cases.
These findings open the door to potential new treatments that boost protective T cell responses and limit harmful inflammation. Future therapies might harness the immune system to slow ALS progression. The study also has implications for other neurodegenerative diseases, such as Parkinson’s, Huntington’s, and Alzheimer’s, where immune cell involvement may similarly influence disease outcomes.
Research Paper 📄
DOI: 10.1038/s41586-025-09588-6
|
|
Scooped by
Gilbert C FAURE
February 16, 1:00 PM
|
|