Your new post is loading...

|
Scooped by
Gilbert C FAURE
December 14, 2020 5:02 AM
|
Abstract Objectives C‐type lectin receptors (CLRs) are key receptors used by DCs to orchestrate responses to pathogens. During infections, the glycan–lectin interactions shape the virus–host interp...
|
|
Scooped by
Gilbert C FAURE
December 11, 2020 6:28 AM
|
Researchers at the Crick and UCL have rebuilt a human thymus, an essential organ in the immune system, using human stem cells and a bioengineered scaffold. ...
|
|
Scooped by
Gilbert C FAURE
December 9, 2020 4:20 AM
|
|
|
Scooped by
Gilbert C FAURE
December 8, 2020 12:26 PM
|
Human T-bet is involved in the regulation of distinct leukocyte subsets, when compared
with its mouse counterpart, with its deficiency underlying severe mycobacterial disease
|
|
Scooped by
Gilbert C FAURE
December 5, 2020 1:36 PM
|
|
|
Scooped by
Gilbert C FAURE
December 3, 2020 1:01 PM
|
Home/Newsroom/Q&A Detail/Coronavirus disease (COVID-19): Herd immunity, lockdowns and COVID-19 Coronavirus disease (COVID-19): Herd immunity, lockdowns and COVID-19 15 October 2020 | Q&A What is ‘herd immunity’? ‘Herd immunity’, also known as ‘population immunity’, is a concept used for vaccination, in which a population can be protected from a certain virus if a threshold of vaccination is reached. Herd immunity is achieved by protecting people from a virus, not by exposing them to it. Vaccines train our immune systems to create proteins that fight disease, known as ‘antibodies’, just as would happen when we are exposed to a disease but – crucially – vaccines work without making us sick. Vaccinated people are protected from getting the disease in question and passing it on, breaking any chains of transmission. Visit our webpage on COVID-19 and vaccines for more detail. With herd immunity, the vast majority of a population are vaccinated, lowering the overall amount of virus able to spread in the whole population. As a result, not every single person needs to be vaccinated to be protected, which helps ensure vulnerable groups who cannot get vaccinated are kept safe. The percentage of people who need to have antibodies in order to achieve herd immunity against a particular disease varies with each disease. For example, herd immunity against measles requires about 95% of a population to be vaccinated. The remaining 5% will be protected by the fact that measles will not spread among those who are vaccinated. For polio, the threshold is about 80%. Achieving herd immunity with safe and effective vaccines makes diseases rarer and saves lives. Find out more about the science behind herd immunity by watching or reading this interview with WHO’s Chief Scientist, Dr Soumya Swaminathan. Attempts to reach ‘herd immunity’ through exposing people to a virus are scientifically problematic and unethical. Letting COVID-19 spread through populations, of any age or health status will lead to unnecessary infections, suffering and death. The vast majority of people in most countries remain susceptible to this virus. Seroprevalence surveys suggest that in most countries, less than 10% of the population have been infected with COVID-19. We are still learning about immunity to COVID-19. Most people who are infected with COVID-19 develop an immune response within the first few weeks, but we don’t know how strong or lasting that immune response is, or how it differs for different people. There have also been reports of people infected with COVID-19 for a second time. Until we better understand COVID-19 immunity, it will not be possible to know how much of a population is immune and how long that immunity last for, let alone make future predictions. These challenges should preclude any plans that try to increase immunity within a population by allowing people to get infected. Although older people and those with underlying conditions are most at risk of severe disease and death, they are not the only ones at risk. Finally, while most infected people get mild or moderate forms of COVID-19 and some experience no disease, many become seriously ill and must be admitted into hospital. We are only beginning to understand the long-term health impacts among people who have had COVID-19, including what is being described as ‘Long COVID.’ WHO is working with clinicians and patient groups to better understand the long term effects of COVID-19. Read the Director-General’s opening remarks at the 12 October COVID-19 briefing for a summary of WHO’s position. Most people who are infected with COVID-19 develop an immune response within the first few weeks after infection. Research is still ongoing into how strong that protection is and how long it lasts. WHO is also looking into whether the strength and length of immune response depends on the type of infection a person has: without symptoms (‘asymptomatic’), mild or severe. Even people without symptoms seem to develop an immune response. Globally, data from seroprevalence studies suggests that less 10% of those studied have been infected, meaning that the vast majority of the world’s population remains susceptible to this virus. For other coronaviruses – such as the common cold, SARS-CoV-1 and Middle East Respiratory Syndrome (MERS) – immunity declines over time, as is the case with other diseases. While people infected with the SARS-CoV-2 virus develop antibodies and immunity, we do not yet know how long it lasts. Watch this conversation with Dr Mike Ryan and Dr Maria Van Kerkhove for more information on immunity. Large scale physical distancing measures and movement restrictions, often referred to as ‘lockdowns’, can slow COVID‑19 transmission by limiting contact between people. However, these measures can have a profound negative impact on individuals, communities, and societies by bringing social and economic life to a near stop. Such measures disproportionately affect disadvantaged groups, including people in poverty, migrants, internally displaced people and refugees, who most often live in overcrowded and under resourced settings, and depend on daily labour for subsistence. WHO recognizes that at certain points, some countries have had no choice but to issue stay-at-home orders and other measures, to buy time. Governments must make the most of the extra time granted by ‘lockdown’ measures by doing all they can to build their capacities to detect, isolate, test and care for all cases; trace and quarantine all contacts; engage, empower and enable populations to drive the societal response and more. WHO is hopeful that countries will use targeted interventions where and when needed, based on the local situation. WHO TEAM WHO Headquarters (HQ) Related
|
|
Scooped by
Gilbert C FAURE
December 1, 2020 1:26 AM
|
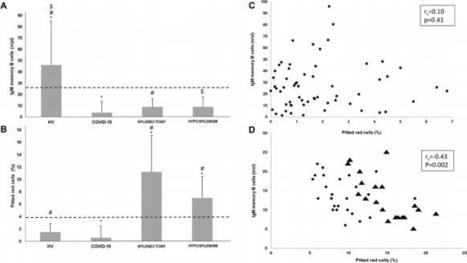
Impaired immune responses have been hypothesised to be a possible trigger of unfavourable outcomes in coronavirus disease 2019 (COVID-19). We aimed to characterise IgM memory B cells in patients with COVID-19 admitted to an internal medicine ward in Northern Italy. Overall, 66 COVID-19 patients (mean age 74 ± 16.6 years; 29 females) were enrolled. Three patients (4.5%; 1 female) had been splenectomised and were excluded from further analyses. Fifty-five patients (87.3%) had IgM memory B cell depletion, and 18 (28.6%) died during hospitalisation (cumulative incidence rate 9.26/100 person-week; 5.8–14.7 95% CI). All patients who died had IgM memory B cell depletion. A superimposed infection was found in 6 patients (9.5%), all of them having IgM memory B cell depletion (cumulative incidence rate 3.08/100 person-week; 1.3–6.8 95% CI). At bivariable analyses, older age, sex, number of comorbidities, and peripheral blood lymphocyte count < 1500/µl were not correlated with IgM memory B cell depletion. A discrete-to-marked reduction of the B-cell compartment was also noticed in autoptic spleen specimens of two COVID-19 patients. We conclude that IgM memory B cells are commonly depleted in COVID-19 patients and this correlates with increased mortality and superimposed infections.
|
|
Scooped by
Gilbert C FAURE
November 25, 2020 1:33 PM
|
Natural killer (NK) cells are innate cytotoxic lymphoid cells (ILCs) involved in the killing of infected and tumor cells. Among human and mouse NK cells from the spleen and blood, we previously identified by single-cell RNA sequencing (scRNAseq) two similar major subsets, NK1 and NK2. Using the same technology, we report here the identification, by single-cell RNA sequencing (scRNAseq), of three NK cell subpopulations in human bone marrow. Pseudotime analysis identified a subset of resident CD56bright NK cells, NK0 cells, as the precursor of both circulating CD56dim NK1-like NK cells and CD56bright NK2-like NK cells in human bone marrow and spleen under physiological conditions. Transcriptomic profiles of bone marrow NK cells from patients with acute myeloid leukemia (AML) exhibited stress-induced repression of NK cell effector functions, highlighting the profound impact of this disease on NK cell heterogeneity. Bone marrow NK cells from AML patients exhibited reduced levels of CD160, but the CD160high group had a significantly higher survival rate.
|
|
Scooped by
Gilbert C FAURE
November 24, 2020 1:03 PM
|
|
|
Scooped by
Gilbert C FAURE
November 22, 2020 10:45 AM
|
Immune dysregulation is as important as susceptibility to infection in defining primary immunodeficiencies (PIDs). Due to the variability and nonspeci…
|
|
Scooped by
Gilbert C FAURE
November 18, 2020 2:40 PM
|
Abstract Tremendous progress has been made in understanding the role of T cell immunity in acute and convalescent COVID-19 infection. Here we shed light on the “known unknowns” of pre-existing and acquired T cell responses in relation to acute and convalescent SARS-CoV-2 infection. INTRODUCTION The broad clinical spectrum of COVID-19 indicates widespread intraindividual differences in the host immune defense against severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2). The underlying cause of disease heterogeneity is probably multifactorial. However, a rapid early host response is likely critical to generate control of SARS-CoV-2 viremia before spread to the lower respiratory tract and onset of damaging hyperinflammation. In this regard, the literature is full of examples where functional T cell responses can provide early control of acute viral infections, including SARS-CoV and MERS-CoV (1, 2). Although multiple studies have indicated that T cells play a role in the early immune response to SARS-CoV-2 and can generate a functional memory pool, there are still multiple unanswered questions in the field (Box 1). Here, we summarize and speculate on a specific set of questions related to T cell immunity against respiratory viral infections, with a focus on COVID-19 severity, immunity, long-term consequences, and vaccination (Fig. 1). Box 1 Open questions about T cell immunity to SARS-CoV-2. T cells in acute SARS-CoV-2 infection • What do acute SARS-CoV-2-specific T cell responses in the blood tell us about contemporaneous T cell responses in the lung? • Which host and viral factors regulate the strength and efficacy of the early antiviral T cell response? Longevity and memory T cell formation • Do CD4+ T cell responses to the virus predominate over CD8+ responses in the lung as well as the blood? • Do poor CD4+ TFH responses to the virus correlate with reduced longevity of antibody responses? • Is severe COVID 19 linked to an impaired development of SARS-CoV-2-specific memory T cells? Cross-reactive T cells • Do pre-existing memory T cells to seasonal CoV epitopes help or hinder the host response to SARS-CoV-2? SARS-CoV-2-specific TRM • Will establishment of SARS-CoV-2-specific CD4+ and CD8+ TRM in the upper respiratory tract provide durable protection from lower pulmonary disease upon reinfection? Long COVID • Are virus-induced or bystander T cells major inducers of persistent symptoms of inflammation associated with long COVID? T cells in vaccines • What type of T cell response elicited by vaccines will be the best predictor of protection from disease following exposure to the virus? T CELLS IN ACUTE SARS-COV-2 INFECTION T cells are critical to generate early control and clearance of many viral infections of the respiratory system (3). Recent studies in transgenic mouse models provided evidence that T cells are also important for viral clearance and disease resolution after SARS-CoV-2 infection (4). As such, it is not surprising that T cell activation has emerged as a hallmark of acute COVID-19; probably as a consequence of an early SARS-CoV-2-specific cellular immune response (5–9). Although early T cell responses may play a critical role in dampening disease severity, there are also reports describing a dysregulated and unchecked T cell activation pattern in severe cases (10–12). Increased T cell activation in severe cases likely reflects increased antigen levels in the respiratory system, but whether the early T cell response reaches a state of exhaustion in subjects with severe hyperinflammation remains to be determined. Furthermore, given that COVID-19 is a disease of the respiratory tract it will be important to define if early detection of T cell activation in blood correlates with tissue-specific events. For instance, will delayed detection of SARS-CoV-2-specific T cells in blood reflect the later onset of cellular immunity in the respiratory tract or are these two compartments independent of each other in relation to disease severity? If elicitation of an early T cell response would be beneficial to dampen COVID-19 severity, what might be the underlying causes and correlates of an early versus late onset of SARS-CoV-2-specific T cell activity? Old age and male sex are both associated with increased risk of COVID-19 complications. Interestingly, females seem to mount a somewhat stronger T cell activation following SARS-CoV-2 infection (13) and disruption of T and B cell coordination has been implicated in elderly patients with severe COVID-19 (14). On the other end of the age spectrum, decreased frequencies of IFN-γ+CD4+ and CD25+CD4+ T cells have been described in hospitalized pediatric patients, who have shorter lengths of stay compared with their adult counterparts (15). In conjunction with age and sex, host and viral factors probably also play a role in the early immune defense and coordination of the early SARS-CoV-2-specific T cell response. For instance, SARS-CoV-2 has mechanisms to antagonize proinflammatory signals, particularly type I IFN (IFN-I) signaling (16, 17). IFN-I proteins are key inflammatory mediators to initiate antiviral defense, from which viral evasion might lead to a delayed clearance of SARS-CoV-2 (4). This is supported by the observation that inborn errors of immunity and autoantibodies that diminish IFN-I activity are more commonly detected in patients with severe COVID-19 (18, 19). Concordantly, the early expansion and differentiation of antiviral T cells are dependent on the direct action of IFN-I. Given that activated T cells from older individuals exhibit reduced responses to IFN-I, it is tempting to speculate that higher risk elderly persons experience delayed activation of SARS-CoV-2-specific T cells that may lead to reduced clearance of the virus and exacerbated COVID-19 severity. Collectively, more data are needed from mechanistic studies in animal models as well as large cohort studies on males and females in different age groups to identify beneficial and detrimental viral and host factors that have an impact on the early T cell response against SARS-CoV-2. LONGEVITY AND MEMORY T CELL FORMATION Generation of memory T cells can provide lifelong protection against pathogens (20). Previous studies have demonstrated that SARS-CoV- and MERS-CoV-specific T cells can be detected many years after infection (21–23). Likewise, SARS-CoV-2-specific CD4+ and CD8+ T cells are distinguished in a vast majority of convalescent donors (7, 9, 21, 24–27). Studies using peripheral blood have reported stronger SARS-CoV-2-specific CD4+ than CD8+ T cell responses in most subjects. However, it is well established that CD4+ T cells experience a higher propensity to recirculate between tissues and blood than CD8+ T cells. As such, whether SARS-CoV-2-specific CD4+ T cell responses also predominate in tissues, and particularly at barrier sites close to the epithelium, needs to be confirmed through studies on the upper and lower respiratory tract. Similar to the CD4+ T cell polarized response to many other viral infections, SARS-CoV-2-specific CD4+ T cells mainly possess a Th1 or circulating T follicular helper (TFH) cell phenotype (7–9, 14, 28). Circulating TFH differentiation seems to be impaired in certain patients with severe COVID-19 (11, 29) and recent analysis of postmortem lymph nodes and spleen samples showed an absence of germinal centers along with a defect in Bcl6+ TFH differentiation in deceased COVID-19 patients (30). Whether these consequences are due to sampling from postmortem patients remains unknown, but further studies are needed to clarify whether TFH cell formation is impaired by SARS-CoV-2 and could have an impact on declining antibody responses in specific convalescent donors. Furthermore, more mechanistic studies are needed to understand if memory T cells can generate protective immunity to lethal challenge with SARS-CoV-2, as previously demonstrated in SARS-CoV and MERS-CoV models (1, 2), in the presence or absence of high titers of neutralizing antibodies. Likewise, longitudinal human studies will also inform us of whether functional memory T cell responses are present many years after SARS-CoV-2 infection and correlate with protection from reinfection. CROSS-REACTIVE T CELLS Several studies have demonstrated the presence of CD4+ and to a lesser extent CD8+ T cells recognizing SARS-CoV-2 peptides in a significant proportion of unexposed individuals (7, 21, 24, 26, 31). Mapping of SARS-CoV-2 epitopes in unexposed blood donors revealed pre-existing T cell immunity, potentially induced by seasonal human coronaviruses (HCoVs) causing common colds (27, 32). This is supported by a relatively high amino acid similarity between recognized SARS-CoV-2 epitopes and seasonal HCoVs such as HCoV-OC43, -HKU1, -229E and -NL63. The presence of cross-reactive cellular immune responses in the population generates an obstacle to the use of T cell-based assays to track SARS-CoV-2 infection rates in blood donors. Given that antibodies do not result in the same degree of cross-reactivity as T cells and are consequently easier to use in clinical diagnostic settings, serology will likely be a better readout for tracing the infection rate in the society. Nevertheless, more thorough studies are needed to better understand the full spectrum of cross-reactive versus newly-induced SARS-CoV-2-specific CD4+ and CD8+ T cell responses. A key question in the field is whether pre-existing T cell responses influence the severity of COVID-19. Pre-existing SARS-CoV-2-specific T cells are unlikely to provide sterilizing or herd immunity but may allow the host to bypass immune evasion mechanisms, for instance evasion from IFN-I, and generate early pressure on the virus. This concept is supported by studies in mice showing that airway memory CD4+ T cells recognizing a conserved SARS-CoV epitope provided protection from related CoVs (1). Similar scenarios in which pre-existing T cells may provide earlier viral clearance and thus less severe symptoms have been proposed elsewhere (33). Here, the level of conservation between antigens may have a substantial impact on whether pre-existing T cells are beneficial or detrimental for the host. On the other hand, the concept of “original antigenic sin”, in which earlier induced antibody or T cell responses influence the response against future viral infections, needs further evaluation (34). If pre-existing T cells are less effective in clearing viral infection upon activation but contribute to systemic and permanent increase in inflammatory signals, it might lead to increased hyperinflammation and COVID-19 severity. In a first analysis, comparing T cell responses against SARS-CoV-2 and HCoV sequences did not find any evidence of “original antigenic sin” (32). Again, the level of conservation of targeted epitopes is likely to impact the outcome, and further evaluation of this concept is needed. Collectively, further animal studies and human studies done before and after SARS-CoV-2 infection are needed to define the biological relevance of pre-existing T cell responses and their role as friends or foes in host defense against SARS-CoV-2. SARS-COV-2-SPECIFIC TRM Resident memory T cells (TRM) are a distinct memory T cell lineage. These cells reside within tissues, do not recirculate to peripheral blood, and have been defined as local sentinels mediating rapid protection from reinfection (35). In fact, a vast majority of T cells in nonlymphoid tissues, such as the respiratory tract, are considered to be TRM (36). In terms of respiratory infections, there is a growing body of literature demonstrating that TRM can provide protection against severe pulmonary disease (37, 38). Likewise, airway CD4+ T cells can generate cross-reactive immunity between human and bat coronaviruses (1), emphasizing that cross-reactive T cells in the respiratory tract can provide protection from lethal challenge with pathogenic coronaviruses. Whether cross-reactive TRM, induced by seasonal coronaviruses, can block transmission of SARS-CoV-2 from the upper respiratory tract to the lung and thereby attenuate severe COVID-19 remains unanswered. This scenario, where TRM block the spread of viral disease from upper to lower respiratory tract, has been demonstrated in influenza A infection (37) and might account for partial immunity of secondary infection with heterologous strains (39, 40). Furthermore, whether SARS-CoV-2-specific TRM are induced after COVID-19 and whether these cells will provide protection in the long term also remains unknown (41). Although certain studies in mice have suggested that TRM in the lung are short-lived (42), there is evidence that their counterparts in the upper respiratory tract persist with minimal decay (37) and for more than a year in human lung (43). Altogether, there is currently no evidence supporting the provision of “sterilizing immunity” by TRM, but data presented above suggest that TRM could facilitate rapid control of upper respiratory tract SARS-CoV-2 infection, replication, and spread. In this regard, further work in animal models may provide evidence for whether local immunity mediated by TRM can achieve this type of immunity. LONG COVID A substantial number of COVID-19 patients experience heterogeneous symptoms that persist over a month and onward (44–46). This heterogeneous phenomenon is being referred to as “long COVID” and affects around 10% of all COVID-19 patients (44, 45). Many symptoms can be attributed to persistent tissue damage in severe COVID-19. Nevertheless, the fact that many individuals with milder COVID-19 symptoms also experience chronic lingering symptoms, involving the cardiovascular, nervous, and respiratory systems, indicates that persistent immune activation and/or inflammation may play a role in long COVID. Multiple mechanisms are probably involved in this condition and whether T cells play any role in long COVID is unknown. The higher incidence of long COVID in females than males, similar to autoimmune diseases (47), raises the question of whether T cells orchestrate long COVID through similar mechanisms as in autoimmune or inflammatory conditions (48, 49). One hypothetical underlying mechanism behind autoimmune-related conditions after COVID-19 could be molecular mimicry, given that HCoV-specific T cells can cross-react to myelin in multiple sclerosis patients (50). Whether SARS-CoV-2-specific T cells have the ability to react against self-antigens remains to be determined. In line with a possible effect of HLA type on COVID-19 susceptibility/severity (51, 52), we believe that larger genetic studies are needed to clarify if HLA or other immune-related genes are associated with an increased risk of developing long COVID. T CELLS IN VACCINES Based on the uncertainty of whether cross-reactive T cells or antibodies will provide protective or long-lasting immunity to COVID-19, it will become absolutely critical to administrate a safe and effective vaccine to the population to reach broad immunity and break the negative spiral of new infections. Ongoing vaccine efforts mainly target B cells to promote the induction of neutralizing antibodies (nAbs) against SARS-CoV-2 (53, 54). Although the induction of anti-spike nAbs is the key component for an effective SARS-CoV-2 vaccine, it is well-known that T cells, and in particular TFH cells, are critical to generate antibody-producing plasma cells and long-lived memory B cells. In COVID-19 patients, high nAb titers correlated with strong CD4+ T cell responses, and the lack of functional TFH cells reacting against SARS-CoV-2 was shown to be detrimental (11, 29, 30). Preliminary results from the two major mRNA vaccine trials in humans have demonstrated potent Th1 responses (55, 56). However, previous studies have reported strong TFH responses against certain mRNA vaccines (57), and future trials should therefore include other activation induced markers, such as CD40L and/or CD200, in addition to IFN-γ ELISPOT assays to understand if potent B-helper mechanisms are induced by the current vaccine regimens. Other outstanding questions are whether vaccine-induced TFH responses will be equally induced in all age groups and how long these responses will persist in blood and vaccination site-draining lymph nodes. A final issue to consider is whether high quantities of vaccine-induced CD8+ T cells at local sites need to be elicited by future vaccine candidates. If the initial group of vaccines in clinical trials that are primarily focused on generating an effective nAb response provide recipients with long-standing protection, it may not be necessary to invest in such efforts. However, if problems emerge in the vaccinated population with breakthrough infections, waning antibody levels after vaccination, and/or the emergence of new viral strains, it would be wise to reconsider vaccine approaches specifically designed to induce functional CD8+ TRM responses in the upper respiratory tract. SUMMARY Collective efforts have greatly enhanced our scientific understanding of T cell responses against SARS-CoV-2 but many unknowns remain to be resolved. Although it is clear that T cells play a central role in generating early control and clearance of many viral infections, their role in SARS-CoV-2 infection is only starting to be revealed. Specific T cells may even have a detrimental impact on the clinical outcome and contribute to long COVID symptoms. Currently, there is a need for deeper analysis using both animal models and longitudinal follow-up studies of large patient cohorts to define the beneficial versus detrimental aspects of SARS-CoV-2-specific T cells in acute, convalescent and vaccine settings of COVID-19. References and Notes ↵ J. Zhao, J. Zhao, A. K. Mangalam, R. Channappanavar, C. Fett, D. K. Meyerholz, S. Agnihothram, R. S. Baric, C. S. David, S. Perlman, Airway Memory CD4(+) T Cells Mediate Protective Immunity against Emerging Respiratory Coronaviruses. Immunity 44, 1379–1391 (2016). doi:10.1016/j.immuni.2016.05.006pmid:27287409OpenUrlCrossRefPubMed ↵ J. Zhao, J. Zhao, S. Perlman, T cell responses are required for protection from clinical disease and for virus clearance in severe acute respiratory syndrome coronavirus-infected mice. J. Virol. 84, 9318–9325 (2010). doi:10.1128/JVI.01049-10pmid:20610717 ↵ M. E. Schmidt, S. M. Varga, The CD8 T Cell Response to Respiratory Virus Infections. Front. Immunol. 9, 678 (2018). doi:10.3389/fimmu.2018.00678pmid:29686673OpenUrlCrossRefPubMed ↵ J. Sun, Z. Zhuang, J. Zheng, K. Li, R. L.-Y. Wong, D. Liu, J. Huang, J. He, A. Zhu, J. Zhao, X. Li, Y. Xi, R. Chen, A. N. Alshukairi, Z. Chen, Z. Zhang, C. Chen, X. Huang, F. Li, X. Lai, D. Chen, L. Wen, J. Zhuo, Y. Zhang, Y. Wang, S. Huang, J. Dai, Y. Shi, K. Zheng, M. R. Leidinger, J. Chen, Y. Li, N. Zhong, D. K. Meyerholz, P. B. McCray Jr.., S. Perlman, J. Zhao, Generation of a Broadly Useful Model for COVID-19 Pathogenesis, Vaccination, and Treatment. Cell 182, 734–743.e5 (2020). doi:10.1016/j.cell.2020.06.010pmid:32643603OpenUrlCrossRefPubMed ↵ I. Thevarajan, T. H. O. Nguyen, M. Koutsakos, J. Druce, L. Caly, C. E. van de Sandt, X. Jia, S. Nicholson, M. Catton, B. Cowie, S. Y. C. Tong, S. R. Lewin, K. Kedzierska, Breadth of concomitant immune responses prior to patient recovery: A case report of non-severe COVID-19. Nat. Med. 26, 453–455 (2020). doi:10.1038/s41591-020-0819-2pmid:32284614OpenUrlCrossRefPubMed A. J. Wilk, A. Rustagi, N. Q. Zhao, J. Roque, G. J. Martínez-Colón, J. L. McKechnie, G. T. Ivison, T. Ranganath, R. Vergara, T. Hollis, L. J. Simpson, P. Grant, A. Subramanian, A. J. Rogers, C. A. Blish, A single-cell atlas of the peripheral immune response in patients with severe COVID-19. Nat. Med. 26, 1070–1076 (2020). doi:10.1038/s41591-020-0944-ypmid:32514174OpenUrlCrossRefPubMed ↵ T. Sekine, A. Perez-Potti, O. Rivera-Ballesteros, K. Strålin, J.-B. Gorin, A. Olsson, S. Llewellyn-Lacey, H. Kamal, G. Bogdanovic, S. Muschiol, D. J. Wullimann, T. Kammann, J. Emgård, T. Parrot, E. Folkesson, O. Rooyackers, L. I. Eriksson, J.-I. Henter, A. Sönnerborg, T. Allander, J. Albert, M. Nielsen, J. Klingström, S. Gredmark-Russ, N. K. Björkström, J. K. Sandberg, D. A. Price, H.-G. Ljunggren, S. Aleman, M. Buggert; Karolinska COVID-19 Study Group, Robust T Cell Immunity in Convalescent Individuals with Asymptomatic or Mild COVID-19. Cell 183, 158–168.e14 (2020). doi:10.1016/j.cell.2020.08.017pmid:32979941OpenUrlCrossRefPubMed D. Weiskopf, K. S. Schmitz, M. P. Raadsen, A. Grifoni, N. M. A. Okba, H. Endeman, J. P. C. van den Akker, R. Molenkamp, M. P. G. Koopmans, E. C. M. van Gorp, B. L. Haagmans, R. L. de Swart, A. Sette, R. D. de Vries, Phenotype and kinetics of SARS-CoV-2-specific T cells in COVID-19 patients with acute respiratory distress syndrome. Sci. Immunol. 5, eabd2071 (2020). doi:10.1126/sciimmunol.abd2071pmid:32591408 ↵ Y. Peng, A. J. Mentzer, G. Liu, X. Yao, Z. Yin, D. Dong, W. Dejnirattisai, T. Rostron, P. Supasa, C. Liu, C. López-Camacho, J. Slon-Campos, Y. Zhao, D. I. Stuart, G. C. Paesen, J. M. Grimes, A. A. Antson, O. W. Bayfield, D. E. D. P. Hawkins, D.-S. Ker, B. Wang, L. Turtle, K. Subramaniam, P. Thomson, P. Zhang, C. Dold, J. Ratcliff, P. Simmonds, T. de Silva, P. Sopp, D. Wellington, U. Rajapaksa, Y.-L. Chen, M. Salio, G. Napolitani, W. Paes, P. Borrow, B. M. Kessler, J. W. Fry, N. F. Schwabe, M. G. Semple, J. K. Baillie, S. C. Moore, P. J. M. Openshaw, M. A. Ansari, S. Dunachie, E. Barnes, J. Frater, G. Kerr, P. Goulder, T. Lockett, R. Levin, Y. Zhang, R. Jing, L.-P. Ho, R. J. Cornall, C. P. Conlon, P. Klenerman, G. R. Screaton, J. Mongkolsapaya, A. McMichael, J. C. Knight, G. Ogg, T. Dong; Oxford Immunology Network Covid-19 Response T cell Consortium; ISARIC4C Investigators, Broad and strong memory CD4+ and CD8+ T cells induced by SARS-CoV-2 in UK convalescent individuals following COVID-19. Nat. Immunol. 21, 1336–1345 (2020). doi:10.1038/s41590-020-0782-6pmid:32887977OpenUrlCrossRefPubMed ↵ L. Kuri-Cervantes, M. B. Pampena, W. Meng, A. M. Rosenfeld, C. A. G. Ittner, A. R. Weisman, R. S. Agyekum, D. Mathew, A. E. Baxter, L. A. Vella, O. Kuthuru, S. A. Apostolidis, L. Bershaw, J. Dougherty, A. R. Greenplate, A. Pattekar, J. Kim, N. Han, S. Gouma, M. E. Weirick, C. P. Arevalo, M. J. Bolton, E. C. Goodwin, E. M. Anderson, S. E. Hensley, T. K. Jones, N. S. Mangalmurti, E. T. Luning Prak, E. J. Wherry, N. J. Meyer, M. R. Betts, Comprehensive mapping of immune perturbations associated with severe COVID-19. Sci. Immunol. 5, eabd7114 (2020). doi:10.1126/sciimmunol.abd7114pmid:32669287 ↵ D. Mathew, J. R. Giles, A. E. Baxter, D. A. Oldridge, A. R. Greenplate, J. E. Wu, C. Alanio, L. Kuri-Cervantes, M. B. Pampena, K. D’Andrea, S. Manne, Z. Chen, Y. J. Huang, J. P. Reilly, A. R. Weisman, C. A. G. Ittner, O. Kuthuru, J. Dougherty, K. Nzingha, N. Han, J. Kim, A. Pattekar, E. C. Goodwin, E. M. Anderson, M. E. Weirick, S. Gouma, C. P. Arevalo, M. J. Bolton, F. Chen, S. F. Lacey, H. Ramage, S. Cherry, S. E. Hensley, S. A. Apostolidis, A. C. Huang, L. A. Vella, M. R. Betts, N. J. Meyer, E. J. Wherry; UPenn COVID Processing Unit, Deep immune profiling of COVID-19 patients reveals distinct immunotypes with therapeutic implications. Science 369, eabc8511 (2020). doi:10.1126/science.abc8511pmid:32669297 ↵ A. G. Laing, A. Lorenc, I. Del Molino Del Barrio, A. Das, M. Fish, L. Monin, M. Muñoz-Ruiz, D. R. McKenzie, T. S. Hayday, I. Francos-Quijorna, S. Kamdar, M. Joseph, D. Davies, R. Davis, A. Jennings, I. Zlatareva, P. Vantourout, Y. Wu, V. Sofra, F. Cano, M. Greco, E. Theodoridis, J. Freedman, S. Gee, J. N. E. Chan, S. Ryan, E. Bugallo-Blanco, P. Peterson, K. Kisand, L. Haljasmägi, L. Chadli, P. Moingeon, L. Martinez, B. Merrick, K. Bisnauthsing, K. Brooks, M. A. A. Ibrahim, J. Mason, F. Lopez Gomez, K. Babalola, S. Abdul-Jawad, J. Cason, C. Mant, J. Seow, C. Graham, K. J. Doores, F. Di Rosa, J. Edgeworth, M. Shankar-Hari, A. C. Hayday, A dynamic COVID-19 immune signature includes associations with poor prognosis. Nat. Med. 26, 1623–1635 (2020). pmid:32807934OpenUrlCrossRefPubMed ↵ T. Takahashi, M. K. Ellingson, P. Wong, B. Israelow, C. Lucas, J. Klein, J. Silva, T. Mao, J. E. Oh, M. Tokuyama, P. Lu, A. Venkataraman, A. Park, F. Liu, A. Meir, J. Sun, E. Y. Wang, A. Casanovas-Massana, A. L. Wyllie, C. B. F. Vogels, R. Earnest, S. Lapidus, I. M. Ott, A. J. Moore, A. Shaw, J. B. Fournier, C. D. Odio, S. Farhadian, C. Dela Cruz, N. D. Grubaugh, W. L. Schulz, A. M. Ring, A. I. Ko, S. B. Omer, A. Iwasaki; Yale IMPACT Research Team, Sex differences in immune responses that underlie COVID-19 disease outcomes. Nature (2020). doi:10.1038/s41586-020-2700-3pmid:32846427OpenUrlCrossRefPubMed ↵ C. Rydyznski Moderbacher, S. I. Ramirez, J. M. Dan, A. Grifoni, K. M. Hastie, D. Weiskopf, S. Belanger, R. K. Abbott, C. Kim, J. Choi, Y. Kato, E. G. Crotty, C. Kim, S. A. Rawlings, J. Mateus, L. P. V. Tse, A. Frazier, R. Baric, B. Peters, J. Greenbaum, E. Ollmann Saphire, D. M. Smith, A. Sette, S. Crotty, Antigen-Specific Adaptive Immunity to SARS-CoV-2 in Acute COVID-19 and Associations with Age and Disease Severity. Cell 183, 996–1012.e19 (2020). doi:10.1016/j.cell.2020.09.038pmid:33010815OpenUrlCrossRefPubMed ↵ C. A. Pierce, P. Preston-Hurlburt, Y. Dai, C. B. Aschner, N. Cheshenko, B. Galen, S. J. Garforth, N. G. Herrera, R. K. Jangra, N. C. Morano, E. Orner, S. Sy, K. Chandran, J. Dziura, S. C. Almo, A. Ring, M. J. Keller, K. C. Herold, B. C. Herold, Immune responses to SARS-CoV-2 infection in hospitalized pediatric and adult patients. Sci. Transl. Med. 12, eabd5487 (2020). doi:10.1126/scitranslmed.abd5487pmid:32958614 ↵ D. Blanco-Melo, B. E. Nilsson-Payant, W.-C. Liu, S. Uhl, D. Hoagland, R. Møller, T. X. Jordan, K. Oishi, M. Panis, D. Sachs, T. T. Wang, R. E. Schwartz, J. K. Lim, R. A. Albrecht, B. R. tenOever, Imbalanced Host Response to SARS-CoV-2 Drives Development of COVID-19. Cell 181, 1036–1045.e9 (2020). doi:10.1016/j.cell.2020.04.026pmid:32416070OpenUrlCrossRefPubMed ↵ J. Hadjadj, N. Yatim, L. Barnabei, A. Corneau, J. Boussier, N. Smith, H. Péré, B. Charbit, V. Bondet, C. Chenevier-Gobeaux, P. Breillat, N. Carlier, R. Gauzit, C. Morbieu, F. Pène, N. Marin, N. Roche, T.-A. Szwebel, S. H. Merkling, J.-M. Treluyer, D. Veyer, L. Mouthon, C. Blanc, P.-L. Tharaux, F. Rozenberg, A. Fischer, D. Duffy, F. Rieux-Laucat, S. Kernéis, B. Terrier, Impaired type I interferon activity and inflammatory responses in severe COVID-19 patients. Science 369, 718–724 (2020). doi:10.1126/science.abc6027pmid:32661059 ↵ P. Bastard, L. B. Rosen, Q. Zhang, E. Michailidis, H.-H. Hoffmann, Y. Zhang, K. Dorgham, Q. Philippot, J. Rosain, V. Béziat, J. Manry, E. Shaw, L. Haljasmägi, P. Peterson, L. Lorenzo, L. Bizien, S. Trouillet-Assant, K. Dobbs, A. A. de Jesus, A. Belot, A. Kallaste, E. Catherinot, Y. Tandjaoui-Lambiotte, J. Le Pen, G. Kerner, B. Bigio, Y. Seeleuthner, R. Yang, A. Bolze, A. N. Spaan, O. M. Delmonte, M. S. Abers, A. Aiuti, G. Casari, V. Lampasona, L. Piemonti, F. Ciceri, K. Bilguvar, R. P. Lifton, M. Vasse, D. M. Smadja, M. Migaud, J. Hadjadj, B. Terrier, D. Duffy, L. Quintana-Murci, D. van de Beek, L. Roussel, D. C. Vinh, S. G. Tangye, F. Haerynck, D. Dalmau, J. Martinez-Picado, P. Brodin, M. C. Nussenzweig, S. Boisson-Dupuis, C. Rodríguez-Gallego, G. Vogt, T. H. Mogensen, A. J. Oler, J. Gu, P. D. Burbelo, J. I. Cohen, A. Biondi, L. R. Bettini, M. D’Angio, P. Bonfanti, P. Rossignol, J. Mayaux, F. Rieux-Laucat, E. S. Husebye, F. Fusco, M. V. Ursini, L. Imberti, A. Sottini, S. Paghera, E. Quiros-Roldan, C. Rossi, R. Castagnoli, D. Montagna, A. Licari, G. L. Marseglia, X. Duval, J. Ghosn, J. S. Tsang, R. Goldbach-Mansky, K. Kisand, M. S. Lionakis, A. Puel, S.-Y. Zhang, S. M. Holland, G. Gorochov, E. Jouanguy, C. M. Rice, A. Cobat, L. D. Notarangelo, L. Abel, H. C. Su, J.-L. Casanova; HGID Lab; NIAID-USUHS Immune Response to COVID Group; COVID Clinicians; COVID-STORM Clinicians; Imagine COVID Group; French COVID Cohort Study Group; Milieu Intérieur Consortium; CoV-Contact Cohort; Amsterdam UMC Covid-19 Biobank; COVID Human Genetic Effort, Autoantibodies against type I IFNs in patients with life-threatening COVID-19. Science 370, eabd4585 (2020). doi:10.1126/science.abd4585pmid:32972996 ↵ Q. Zhang, P. Bastard, Z. Liu, J. Le Pen, M. Moncada-Velez, J. Chen, M. Ogishi, I. K. D. Sabli, S. Hodeib, C. Korol, J. Rosain, K. Bilguvar, J. Ye, A. Bolze, B. Bigio, R. Yang, A. A. Arias, Q. Zhou, Y. Zhang, F. Onodi, S. Korniotis, L. Karpf, Q. Philippot, M. Chbihi, L. Bonnet-Madin, K. Dorgham, N. Smith, W. M. Schneider, B. S. Razooky, H.-H. Hoffmann, E. Michailidis, L. Moens, J. E. Han, L. Lorenzo, L. Bizien, P. Meade, A.-L. Neehus, A. C. Ugurbil, A. Corneau, G. Kerner, P. Zhang, F. Rapaport, Y. Seeleuthner, J. Manry, C. Masson, Y. Schmitt, A. Schlüter, T. Le Voyer, T. Khan, J. Li, J. Fellay, L. Roussel, M. Shahrooei, M. F. Alosaimi, D. Mansouri, H. Al-Saud, F. Al-Mulla, F. Almourfi, S. Z. Al-Muhsen, F. Alsohime, S. Al Turki, R. Hasanato, D. van de Beek, A. Biondi, L. R. Bettini, M. D’Angio’, P. Bonfanti, L. Imberti, A. Sottini, S. Paghera, E. Quiros-Roldan, C. Rossi, A. J. Oler, M. F. Tompkins, C. Alba, I. Vandernoot, J.-C. Goffard, G. Smits, I. Migeotte, F. Haerynck, P. Soler-Palacin, A. Martin-Nalda, R. Colobran, P.-E. Morange, S. Keles, F. Çölkesen, T. Ozcelik, K. K. Yasar, S. Senoglu, Ş. N. Karabela, C. Rodríguez-Gallego, G. Novelli, S. Hraiech, Y. Tandjaoui-Lambiotte, X. Duval, C. Laouénan, A. L. Snow, C. L. Dalgard, J. D. Milner, D. C. Vinh, T. H. Mogensen, N. Marr, A. N. Spaan, B. Boisson, S. Boisson-Dupuis, J. Bustamante, A. Puel, M. J. Ciancanelli, I. Meyts, T. Maniatis, V. Soumelis, A. Amara, M. Nussenzweig, A. García-Sastre, F. Krammer, A. Pujol, D. Duffy, R. P. Lifton, S.-Y. Zhang, G. Gorochov, V. Béziat, E. Jouanguy, V. Sancho-Shimizu, C. M. Rice, L. Abel, L. D. Notarangelo, A. Cobat, H. C. Su, J.-L. Casanova; COVID-STORM Clinicians; COVID Clinicians; Imagine COVID Group; French COVID Cohort Study Group; CoV-Contact Cohort; Amsterdam UMC Covid-19 Biobank; COVID Human Genetic Effort; NIAID-USUHS/TAGC COVID Immunity Group, Inborn errors of type I IFN immunity in patients with life-threatening COVID-19. Science 370, eabd4570 (2020). doi:10.1126/science.abd4570pmid:32972995 ↵ D. L. Farber, N. A. Yudanin, N. P. Restifo, Human memory T cells: Generation, compartmentalization and homeostasis. Nat. Rev. Immunol. 14, 24–35 (2014). doi:10.1038/nri3567pmid:24336101OpenUrlCrossRefPubMed ↵ N. Le Bert, A. T. Tan, K. Kunasegaran, C. Y. L. Tham, M. Hafezi, A. Chia, M. H. Y. Chng, M. Lin, N. Tan, M. Linster, W. N. Chia, M. I.-C. Chen, L.-F. Wang, E. E. Ooi, S. Kalimuddin, P. A. Tambyah, J. G.-H. Low, Y.-J. Tan, A. Bertoletti, SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls. Nature 584, 457–462 (2020). doi:10.1038/s41586-020-2550-zpmid:32668444OpenUrlCrossRefPubMed H. S. Shin, Y. Kim, G. Kim, J. Y. Lee, I. Jeong, J.-S. Joh, H. Kim, E. Chang, S. Y. Sim, J.-S. Park, D.-G. Lim, Immune Responses to Middle East Respiratory Syndrome Coronavirus During the Acute and Convalescent Phases of Human Infection. Clin. Infect. Dis. 68, 984–992 (2019). doi:10.1093/cid/ciy595pmid:30060038OpenUrlCrossRefPubMed ↵ F. Tang, Y. Quan, Z.-T. Xin, J. Wrammert, M.-J. Ma, H. Lv, T.-B. Wang, H. Yang, J. H. Richardus, W. Liu, W.-C. Cao, Lack of peripheral memory B cell responses in recovered patients with severe acute respiratory syndrome: A six-year follow-up study. J. Immunol. 186, 7264–7268 (2011). doi:10.4049/jimmunol.0903490pmid:21576510 ↵ A. Grifoni, D. Weiskopf, S. I. Ramirez, J. Mateus, J. M. Dan, C. R. Moderbacher, S. A. Rawlings, A. Sutherland, L. Premkumar, R. S. Jadi, D. Marrama, A. M. de Silva, A. Frazier, A. F. Carlin, J. A. Greenbaum, B. Peters, F. Krammer, D. M. Smith, S. Crotty, A. Sette, Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals. Cell 181, 1489–1501.e15 (2020). doi:10.1016/j.cell.2020.05.015pmid:32473127OpenUrlCrossRefPubMed L. Ni, F. Ye, M.-L. Cheng, Y. Feng, Y.-Q. Deng, H. Zhao, P. Wei, J. Ge, M. Gou, X. Li, L. Sun, T. Cao, P. Wang, C. Zhou, R. Zhang, P. Liang, H. Guo, X. Wang, C.-F. Qin, F. Chen, C. Dong, Detection of SARS-CoV-2-Specific Humoral and Cellular Immunity in COVID-19 Convalescent Individuals. Immunity 52, 971–977.e3 (2020). doi:10.1016/j.immuni.2020.04.023pmid:32413330OpenUrlCrossRefPubMed ↵ J. Braun, L. Loyal, M. Frentsch, D. Wendisch, P. Georg, F. Kurth, S. Hippenstiel, M. Dingeldey, B. Kruse, F. Fauchere, E. Baysal, M. Mangold, L. Henze, R. Lauster, M. A. Mall, K. Beyer, J. Röhmel, S. Voigt, J. Schmitz, S. Miltenyi, I. Demuth, M. A. Müller, A. Hocke, M. Witzenrath, N. Suttorp, F. Kern, U. Reimer, H. Wenschuh, C. Drosten, V. M. Corman, C. Giesecke-Thiel, L. E. Sander, A. Thiel, SARS-CoV-2-reactive T cells in healthy donors and patients with COVID-19. Nature 587, 270–274 (2020). doi:10.1038/s41586-020-2598-9pmid:32726801OpenUrlCrossRefPubMed ↵ A. Nelde, T. Bilich, J. S. Heitmann, Y. Maringer, H. R. Salih, M. Roerden, M. Lübke, J. Bauer, J. Rieth, M. Wacker, A. Peter, S. Hörber, B. Traenkle, P. D. Kaiser, U. Rothbauer, M. Becker, D. Junker, G. Krause, M. Strengert, N. Schneiderhan-Marra, M. F. Templin, T. O. Joos, D. J. Kowalewski, V. Stos-Zweifel, M. Fehr, A. Rabsteyn, V. Mirakaj, J. Karbach, E. Jäger, M. Graf, L.-C. Gruber, D. Rachfalski, B. Preuß, I. Hagelstein, M. Märklin, T. Bakchoul, C. Gouttefangeas, O. Kohlbacher, R. Klein, S. Stevanović, H.-G. Rammensee, J. S. Walz, SARS-CoV-2-derived peptides define heterologous and COVID-19-induced T cell recognition. Nat. Immunol. (2020). doi:10.1038/s41590-020-00808-xpmid:32999467OpenUrlCrossRefPubMed ↵ G. Chen, D. Wu, W. Guo, Y. Cao, D. Huang, H. Wang, T. Wang, X. Zhang, H. Chen, H. Yu, X. Zhang, M. Zhang, S. Wu, J. Song, T. Chen, M. Han, S. Li, X. Luo, J. Zhao, Q. Ning, Clinical and immunological features of severe and moderate coronavirus disease 2019. J. Clin. Invest. 130, 2620–2629 (2020). doi:10.1172/JCI137244pmid:32217835OpenUrlCrossRefPubMed ↵ J. A. Juno, H.-X. Tan, W. S. Lee, A. Reynaldi, H. G. Kelly, K. Wragg, R. Esterbauer, H. E. Kent, C. J. Batten, F. L. Mordant, N. A. Gherardin, P. Pymm, M. H. Dietrich, N. E. Scott, W.-H. Tham, D. I. Godfrey, K. Subbarao, M. P. Davenport, S. J. Kent, A. K. Wheatley, Humoral and circulating follicular helper T cell responses in recovered patients with COVID-19. Nat. Med. 26, 1428–1434 (2020). doi:10.1038/s41591-020-0995-0pmid:32661393OpenUrlCrossRefPubMed ↵ N. Kaneko, H.-H. Kuo, J. Boucau, J. R. Farmer, H. Allard-Chamard, V. S. Mahajan, A. Piechocka-Trocha, K. Lefteri, M. Osborn, J. Bals, Y. C. Bartsch, N. Bonheur, T. M. Caradonna, J. Chevalier, F. Chowdhury, T. J. Diefenbach, K. Einkauf, J. Fallon, J. Feldman, K. K. Finn, P. Garcia-Broncano, C. A. Hartana, B. M. Hauser, C. Jiang, P. Kaplonek, M. Karpell, E. C. Koscher, X. Lian, H. Liu, J. Liu, N. L. Ly, A. R. Michell, Y. Rassadkina, K. Seiger, L. Sessa, S. Shin, N. Singh, W. Sun, X. Sun, H. J. Ticheli, M. T. Waring, A. L. Zhu, G. Alter, J. Z. Li, D. Lingwood, A. G. Schmidt, M. Lichterfeld, B. D. Walker, X. G. Yu, R. F. Padera Jr.., S. Pillai; Massachusetts Consortium on Pathogen Readiness Specimen Working Group, Loss of Bcl-6-Expressing T Follicular Helper Cells and Germinal Centers in COVID-19. Cell 183, 143–157.e13 (2020). doi:10.1016/j.cell.2020.08.025pmid:32877699OpenUrlCrossRefPubMed ↵ B. J. Meckiff, C. Ramírez-Suástegui, V. Fajardo, S. J. Chee, A. Kusnadi, H. Simon, S. Eschweiler, A. Grifoni, E. Pelosi, D. Weiskopf, A. Sette, F. Ay, G. Seumois, C. H. Ottensmeier, P. Vijayanand, Imbalance of Regulatory and Cytotoxic SARS-CoV-2-Reactive CD4+ T Cells in COVID-19. Cell S0092-8674(20)31307-6 (2020). doi:10.1016/j.cell.2020.10.001pmid:33096020OpenUrlCrossRefPubMed ↵ J. Mateus, A. Grifoni, A. Tarke, J. Sidney, S. I. Ramirez, J. M. Dan, Z. C. Burger, S. A. Rawlings, D. M. Smith, E. Phillips, S. Mallal, M. Lammers, P. Rubiro, L. Quiambao, A. Sutherland, E. D. Yu, R. da Silva Antunes, J. Greenbaum, A. Frazier, A. J. Markmann, L. Premkumar, A. de Silva, B. Peters, S. Crotty, A. Sette, D. Weiskopf, Selective and cross-reactive SARS-CoV-2 T cell epitopes in unexposed humans. Science 370, 89–94 (2020). doi:10.1126/science.abd3871pmid:32753554 ↵ M. Lipsitch, Y. H. Grad, A. Sette, S. Crotty, Cross-reactive memory T cells and herd immunity to SARS-CoV-2. Nat. Rev. Immunol. 20, 709–713 (2020). doi:10.1038/s41577-020-00460-4pmid:33024281OpenUrlCrossRefPubMed ↵ P. Klenerman, R. M. Zinkernagel, Original antigenic sin impairs cytotoxic T lymphocyte responses to viruses bearing variant epitopes. Nature 394, 482–485 (1998). doi:10.1038/28860pmid:9697771OpenUrlCrossRefPubMed ↵ J. M. Schenkel, D. Masopust, Tissue-resident memory T cells. Immunity 41, 886–897 (2014). doi:10.1016/j.immuni.2014.12.007pmid:25526304OpenUrlCrossRefPubMed ↵ E. M. Steinert, J. M. Schenkel, K. A. Fraser, L. K. Beura, L. S. Manlove, B. Z. Igyártó, P. J. Southern, D. Masopust, Quantifying Memory CD8 T Cells Reveals Regionalization of Immunosurveillance. Cell 161, 737–749 (2015). doi:10.1016/j.cell.2015.03.031pmid:25957682OpenUrlCrossRefPubMed ↵ A. Pizzolla, T. H. O. Nguyen, J. M. Smith, A. G. Brooks, K. Kedzieska, W. R. Heath, P. C. Reading, L. M. Wakim, Resident memory CD8+ T cells in the upper respiratory tract prevent pulmonary influenza virus infection. Sci. Immunol. 2, eaam6970 (2017). doi:10.1126/sciimmunol.aam6970pmid:28783656 ↵ P. A. Darrah, J. J. Zeppa, P. Maiello, J. A. Hackney, M. H. Wadsworth 2nd., T. K. Hughes, S. Pokkali, P. A. Swanson 2nd., N. L. Grant, M. A. Rodgers, M. Kamath, C. M. Causgrove, D. J. Laddy, A. Bonavia, D. Casimiro, P. L. Lin, E. Klein, A. G. White, C. A. Scanga, A. K. Shalek, M. Roederer, J. L. Flynn, R. A. Seder, Prevention of tuberculosis in macaques after intravenous BCG immunization. Nature 577, 95–102 (2020). doi:10.1038/s41586-019-1817-8pmid:31894150OpenUrlCrossRefPubMed ↵ J. L. Schulman, E. D. Kilbourne, Induction of Partial Specific Heterotypic Immunity in Mice by a Single Infection with Influenza a Virus. J. Bacteriol. 89, 170–174 (1965). doi:10.1128/JB.89.1.170-174.1965pmid:14255658 ↵ R. B. Effros, P. C. Doherty, W. Gerhard, J. Bennink, Generation of both cross-reactive and virus-specific T-cell populations after immunization with serologically distinct influenza A viruses. J. Exp. Med. 145, 557–568 (1977). doi:10.1084/jem.145.3.557pmid:233901 ↵P. A. Szabo et al., Analysis of respiratory and systemic immune responses in COVID-19 reveals mechanisms of disease pathogenesis. medRxiv, (2020). DOI https://www.medrxiv.org/content/10.1101/2020.10.15.20208041v1 ↵ B. Slütter, N. Van Braeckel-Budimir, G. Abboud, S. M. Varga, S. Salek-Ardakani, J. T. Harty, Dynamics of influenza-induced lung-resident memory T cells underlie waning heterosubtypic immunity. Sci. Immunol. 2, eaag2031 (2017). doi:10.1126/sciimmunol.aag2031pmid:28783666 ↵ M. E. Snyder, M. O. Finlayson, T. J. Connors, P. Dogra, T. Senda, E. Bush, D. Carpenter, C. Marboe, L. Benvenuto, L. Shah, H. Robbins, J. L. Hook, M. Sykes, F. D’Ovidio, M. Bacchetta, J. R. Sonett, D. J. Lederer, S. Arcasoy, P. A. Sims, D. L. Farber, Generation and persistence of human tissue-resident memory T cells in lung transplantation. Sci. Immunol. 4, eaav5581 (2019). doi:10.1126/sciimmunol.aav5581pmid:30850393 ↵ E. Mahase, Long covid could be four different syndromes, review suggests. BMJ 371, m3981 (2020). doi:10.1136/bmj.m3981pmid:33055076OpenUrlFREE Full Text ↵ M. Marshall, The lasting misery of coronavirus long-haulers. Nature 585, 339–341 (2020). doi:10.1038/d41586-020-02598-6pmid:32929257OpenUrlCrossRefPubMed ↵ C. Iadecola, J. Anrather, H. Kamel, Effects of COVID-19 on the Nervous System. Cell 183, 16–27.e1 (2020). doi:10.1016/j.cell.2020.08.028pmid:32882182OpenUrlCrossRefPubMed ↵ C. C. Whitacre, Sex differences in autoimmune disease. Nat. Immunol. 2, 777–780 (2001). doi:10.1038/ni0901-777pmid:11526384 ↵ T. Icenogle, COVID-19: Infection or Autoimmunity. Front. Immunol. 11, 2055 (2020). doi:10.3389/fimmu.2020.02055pmid:33042116OpenUrlCrossRefPubMed ↵ M. Ehrenfeld, A. Tincani, L. Andreoli, M. Cattalini, A. Greenbaum, D. Kanduc, J. Alijotas-Reig, V. Zinserling, N. Semenova, H. Amital, Y. Shoenfeld, Covid-19 and autoimmunity. Autoimmun. Rev. 19, 102597 (2020). doi:10.1016/j.autrev.2020.102597pmid:32535093OpenUrlCrossRefPubMed ↵ A. Boucher, M. Desforges, P. Duquette, P. J. Talbot, Long-term human coronavirus-myelin cross-reactive T-cell clones derived from multiple sclerosis patients. Clin. Immunol. 123, 258–267 (2007). doi:10.1016/j.clim.2007.02.002pmid:17448727 ↵ P. Correale, L. Mutti, F. Pentimalli, G. Baglio, R. E. Saladino, P. Sileri, A. Giordano, HLA-B*44 and C*01 Prevalence Correlates with Covid19 Spreading across Italy. Int. J. Mol. Sci. 21, 5205 (2020). doi:10.3390/ijms21155205pmid:32717807OpenUrlCrossRefPubMed ↵ A. Nguyen, J. K. David, S. K. Maden, M. A. Wood, B. R. Weeder, A. Nellore, R. F. Thompson, Human Leukocyte Antigen Susceptibility Map for Severe Acute Respiratory Syndrome Coronavirus 2. J. Virol. 94, e00510-20 (2020). doi:10.1128/JVI.00510-20pmid:32303592 ↵ F. Krammer, SARS-CoV-2 vaccines in development. Nature 586, 516–527 (2020). doi:10.1038/s41586-020-2798-3pmid:32967006OpenUrlCrossRefPubMed ↵ M. Jeyanathan, S. Afkhami, F. Smaill, M. S. Miller, B. D. Lichty, Z. Xing, Immunological considerations for COVID-19 vaccine strategies. Nat. Rev. Immunol. 20, 615–632 (2020). doi:10.1038/s41577-020-00434-6pmid:32887954OpenUrlCrossRefPubMed ↵ U. Sahin, A. Muik, E. Derhovanessian, I. Vogler, L. M. Kranz, M. Vormehr, A. Baum, K. Pascal, J. Quandt, D. Maurus, S. Brachtendorf, V. Lörks, J. Sikorski, R. Hilker, D. Becker, A.-K. Eller, J. Grützner, C. Boesler, C. Rosenbaum, M.-C. Kühnle, U. Luxemburger, A. Kemmer-Brück, D. Langer, M. Bexon, S. Bolte, K. Karikó, T. Palanche, B. Fischer, A. Schultz, P.-Y. Shi, C. Fontes-Garfias, J. L. Perez, K. A. Swanson, J. Loschko, I. L. Scully, M. Cutler, W. Kalina, C. A. Kyratsous, D. Cooper, P. R. Dormitzer, K. U. Jansen, Ö. Türeci, COVID-19 vaccine BNT162b1 elicits human antibody and TH1 T cell responses. Nature 586, 594–599 (2020). doi:10.1038/s41586-020-2814-7pmid:32998157OpenUrlCrossRefPubMed ↵ L. A. Jackson, E. J. Anderson, N. G. Rouphael, P. C. Roberts, M. Makhene, R. N. Coler, M. P. McCullough, J. D. Chappell, M. R. Denison, L. J. Stevens, A. J. Pruijssers, A. McDermott, B. Flach, N. A. Doria-Rose, K. S. Corbett, K. M. Morabito, S. O’Dell, S. D. Schmidt, P. A. Swanson 2nd., M. Padilla, J. R. Mascola, K. M. Neuzil, H. Bennett, W. Sun, E. Peters, M. Makowski, J. Albert, K. Cross, W. Buchanan, R. Pikaart-Tautges, J. E. Ledgerwood, B. S. Graham, J. H. Beigel; mRNA-1273 Study Group, An mRNA Vaccine against SARS-CoV-2 - Preliminary Report. N. Engl. J. Med. 383, 1920–1931 (2020). doi:10.1056/NEJMoa2022483pmid:32663912OpenUrlCrossRefPubMed ↵ N. Pardi, M. J. Hogan, M. S. Naradikian, K. Parkhouse, D. W. Cain, L. Jones, M. A. Moody, H. P. Verkerke, A. Myles, E. Willis, C. C. LaBranche, D. C. Montefiori, J. L. Lobby, K. O. Saunders, H.-X. Liao, B. T. Korber, L. L. Sutherland, R. M. Scearce, P. T. Hraber, I. Tombácz, H. Muramatsu, H. Ni, D. A. Balikov, C. Li, B. L. Mui, Y. K. Tam, F. Krammer, K. Karikó, P. Polacino, L. C. Eisenlohr, T. D. Madden, M. J. Hope, M. G. Lewis, K. K. Lee, S.-L. Hu, S. E. Hensley, M. P. Cancro, B. F. Haynes, D. Weissman, Nucleoside-modified mRNA vaccines induce potent T follicular helper and germinal center B cell responses. J. Exp. Med. 215, 1571–1588 (2018). doi:10.1084/jem.20171450pmid:29739835 Acknowledgments: Funding. A.C.K. was supported by the Swedish Research Council, the Karolinska Institutet, and The Center for Innovative Medicine. M.B. was supported by the Swedish Research Council, the Karolinska Institutet, the Jeansson Stiftelse, the Åke Wibergs Stiftelse, the Swedish Society of Medicine, the Swedish Cancer Society, the Magnus Bergvalls Stiftelse, the Lars Hiertas Stiftelse, the Swedish Physician against AIDS Foundation, the Jonas Söderquist Stiftelse, and the Clas Groschinskys Minnesfond. Author contributions: A.C.K., M.H. and M.B. contributed to writing and drafting the illustration. A.C.K. and M.B. edited the manuscript. Competing Interests. The authors declare that they have no competing interests. Copyright © 2020, American Association for the Advancement of Science
|
|
Scooped by
Gilbert C FAURE
November 16, 2020 4:23 AM
|
Click on the article title to read more.
|
|
Scooped by
Gilbert C FAURE
November 13, 2020 1:31 PM
|
Another host factor for SARS-CoV-2 Virus-host interactions determine cellular entry and spreading in tissues. Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) and the earlier SARS-CoV use angiotensin-converting enzyme 2 (ACE2) as a receptor; however, their tissue tropism differs, raising the possibility that additional host factors are involved. The spike protein of SARS-CoV-2 contains a cleavage site for the protease furin that is absent from SARS-CoV (see the Perspective by Kielian). Cantuti-Castelvetri et al. now show that neuropilin-1 (NRP1), which is known to bind furin-cleaved substrates, potentiates SARS-CoV-2 infectivity. NRP1 is abundantly expressed in the respiratory and olfactory epithelium, with highest expression in endothelial and epithelial cells. Daly et al. found that the furin-cleaved S1 fragment of the spike protein binds directly to cell surface NRP1 and blocking this interaction with a small-molecule inhibitor or monoclonal antibodies reduced viral infection in cell culture. Understanding the role of NRP1 in SARS-CoV-2 infection may suggest potential targets for future antiviral therapeutics. Science, this issue p. 856, p. 861; see also p. 765 Abstract Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), the causative agent of coronavirus disease 2019 (COVID-19), uses the viral spike (S) protein for host cell attachment and entry. The host protease furin cleaves the full-length precursor S glycoprotein into two associated polypeptides: S1 and S2. Cleavage of S generates a polybasic Arg-Arg-Ala-Arg carboxyl-terminal sequence on S1, which conforms to a C-end rule (CendR) motif that binds to cell surface neuropilin-1 (NRP1) and NRP2 receptors. We used x-ray crystallography and biochemical approaches to show that the S1 CendR motif directly bound NRP1. Blocking this interaction by RNA interference or selective inhibitors reduced SARS-CoV-2 entry and infectivity in cell culture. NRP1 thus serves as a host factor for SARS-CoV-2 infection and may potentially provide a therapeutic target for COVID-19. Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) is the coronavirus responsible for the current coronavirus disease 2019 (COVID-19) pandemic (1, 2). A marked difference between the spike (S) protein of SARS-CoV-2 and SARS-CoV is the presence, in the former, of a polybasic sequence motif, Arg-Arg-Ala-Arg (RRAR), at the S1/S2 boundary. It provides a cleavage site for a host proprotein convertase, furin (3–5) (fig. S1A). The resulting two proteins, S1 and S2, remain noncovalently associated, with the serine protease TMPRSS2 further priming S2 (6). Furin-mediated processing increases infectivity and affects the tropism of SARS-CoV-2, whereas furin inhibition diminishes SARS-CoV-2 entry, and deletion of the polybasic site in the S protein reduces syncytia formation in cell culture (3–5, 7). The C terminus of the S1 protein generated by furin cleavage has an amino acid sequence (682RRAR685) that conforms to a [R/K]XX[R/K] motif, termed the “C-end rule” (CendR) (fig. S1B) (8). CendR peptides bind to neuropilin-1 (NRP1) and NRP2, transmembrane receptors that regulate pleiotropic biological processes, including axon guidance, angiogenesis, and vascular permeability (8–10). To explore the possibility that the SARS-CoV-2 S1 protein may associate with neuropilins, we generated a green fluorescent protein (GFP)–tagged S1 construct (GFP-S1) (fig. S1C). When expressed in human embryonic kidney 293T (HEK293T) cells engineered to express the SARS-CoV-2 receptor angiotensin-converting enzyme 2 (ACE2), GFP-S1 immunoprecipitated endogenous NRP1 and ACE2 (Fig. 1A). We transiently coexpressed NRP1-mCherry and either GFP-S1 or GFP-S1 ΔRRAR (a deletion of the terminal 682RRAR685 residues) in HEK293T cells. NRP1 immunoprecipitated the S1 protein, and deletion of the CendR motif reduced this association (Fig. 1B). Comparable binding was also observed with mCherry-NRP2, a receptor with high homology to NRP1 (fig. S1, D and E). In both cases, residual binding was observed with the ΔRRAR mutant, indicating an additional CendR-independent association between neuropilins and the S1 protein. To probe the functional relevance of this interaction, we generated HeLa wild-type and NRP1 knockout (KO) cell lines stably expressing ACE2, designated as HeLawt+ACE2 and HeLaNRP1KO+ACE2, respectively (the level of ACE2 expression was comparable between these lines) (fig. S1F). Using a clinical isolate SARS-CoV-2 (SARS-CoV-2/human/Liverpool/REMRQ001/2020), we performed viral infection assays and fixed the cells at 6 and 16 hours postinfection (hpi). SARS-CoV-2 infection was reduced in HeLaNRP1KO+ACE2 relative to HeLawt+ACE2 (Fig. 1C). HeLa cells lacking ACE2 expression were not infected (fig. S1G). In Caco-2 cells, a human colon adenocarcinoma cell line endogenously expressing ACE2 and widely used in COVID-19 studies, the suppression of NRP1 expression by short hairpin RNA (shRNA) greatly reduced SARS-CoV-2 infection at both 7 and 16 hpi, respectively, whereas that of vesicular stomatitis virus (VSV) pseudotyped with VSV-G was unaffected (Fig. 1D and figs. S1H and S2A). To determine if NRP1 was required for early virus infection, we established a sequential staining procedure using antibodies against SARS-CoV-2 S and N proteins to distinguish extracellular and intracellular viral particles (fig. S2B). Although NRP1 depletion did not affect SARS-CoV-2 binding to the Caco-2 cell surface (Fig. 1E), virus uptake was halved in NRP1-depleted cells compared to control cells after 30 min of internalization (Fig. 1F). Thus, NRP1 enhances SARS-CoV-2 entry and infection. We also observed that SARS-CoV-2–infected HeLawt+ACE2 cells displayed a multinucleated syncytia cell pattern, as reported by others (Fig. 1C) (5). Using an image analysis algorithm and supervised machine learning (fig. S2, C to F) (11), we quantified syncytia of infected HeLawt+ACE2 and HeLaNRP1KO+ACE2 cells. At 16 hpi, the majority of HeLawt+ACE2 cells formed syncytia, whereas in HeLaNRP1KO+ACE2 cells, this phenotype was reduced (fig. S2G). When infected with a SARS-CoV-2 isolate lacking the furin cleavage site (SARS-CoV-2 ΔS1/S2) (fig. S1A), the differences in infection and syncytia formation were less pronounced (fig. S2, H and I). However, a significant decrease in infection of HeLaNRP1KO+ACE2 was still observed at 16 hpi, indicating that NRP1 may additionally influence infection through a CendR-independent mechanism (fig. S2H). The extracellular regions of NRP1 and NRP2 are composed of two CUB domains (a1 and a2), two coagulation factor domains (b1 and b2), and a MAM domain (9). Of these, the b1 domain contains the specific binding site for CendR peptides (fig. S3A) (12). Accordingly, the mCherry-b1 domain of NRP1 immunoprecipitated GFP-S1, and a shortened GFP-S1 construct spanning residues 493 to 685 (figs. S1C and S3B). Isothermal titration calorimetry (ITC) established that the b1 domain of NRP1 directly bound a synthetic S1 CendR peptide (679NSPRRAR685) with an affinity of 20.3 μM at pH 7.5, which was enhanced to 13.0 μM at pH 5.5 (Fig. 2A). Binding was not observed to an S1 CendR peptide in which the C-terminal arginine was mutated to alanine (679NSPRRAA685) (Fig. 2A). We cocrystallized the NRP1 b1 domain in complex with the S1 CendR peptide (Fig. 2B). The resolved 2.35-Å structure revealed four molecules of b1 with electron density of the S1 CendR peptide clearly visible in the asymmetric unit (fig. S3C). S1 CendR peptide binding displayed strong similarity to the previously solved structure of NRP1 b1 domain in complex with its endogenous ligand VEGF-A164 (Fig. 2B and fig. S3D) (12). The key residues responsible for contacting the C-terminal R685 of the CendR peptide —Y297, W301, T316, D320, S346, T349 and Y353—are almost identical between the two structures (Fig. 2B and fig. S3D). The R682 and R685 side chains together engage NRP1 via stacked cation-π interactions with NRP1 side chains of Y297 and Y353. By projecting these findings onto the structure of the NRP1 ectodomain, the b1 CendR binding pocket appears to be freely accessible to the S1 CendR peptide (fig. S3E) (13). Site-directed mutagenesis of the S1 R685 residue to aspartic acid drastically reduced GFP-S1493-685 immunoprecipitation by mCherry-b1, confirming the critical role of the C-terminal arginine (Fig. 2C). Mutagenesis of the T316 residue within the mCherry-b1 domain of NRP1 to arginine also reduced association with GFP-S1493-685, consistent with its inhibitory impact on VEGF-A164 binding (12) (Fig. 2D). Accordingly, incubation of mCherry-b1 with VSV particles pseudotyped with trimeric S resulted in immunoprecipitation of processed forms of S1, which was dependent on the T316 residue (fig. S3F). Next, we transiently expressed either GFP, full-length NRP1 wt-GFP, or full length NRP1-GFP harboring the T316R mutation in HeLaNRP1KO+ACE2 cells. GFP expression and ACE2 expression levels were comparable and both constructs retained similar cell surface localization (fig. S3, G and H). SARS-CoV-2 infection was significantly enhanced in cells expressing NRP1 wt-GFP compared to GFP control, whereas it was not enhanced in cells expressing the T316R mutant (Fig. 2E). Thus, the SARS-CoV-2 S1 CendR and NRP1 interaction promotes infection. To establish the functional relevance of the S1 CendR-NRP1 interaction, we screened monoclonal antibodies (mAb#1, mAb#2, mAb#3) raised against the NRP1 b1b2 ectodomain. All three bound to the NRP1 b1b2 domain, displayed staining by immunofluorescence in NRP1-expressing PPC-1 (human primary prostate cancer) cells but not in M21 (human melanoma) cells that do not express NRP1 (fig. S4A) (8), and stained the extracellular domain of NRP1-GFP expressed in cells (fig. S4B). Of these antibodies, mAb#3, and to a lesser extent mAb#1, bound to the CendR-binding pocket with high specificity, as defined by reduced ability to bind to a b1b2 mutant that targets residues (S346, E348, T349) at the opening of the binding pocket (Fig. 3A) (12). Incubation of Caco-2 cells with mAbs#1 and 3 reduced SARS-CoV-2 infection compared to a control mAb targeting avian influenza A virus (H11N3) hemagglutinin (Fig. 3B). Consistent with this, mAb#3 inhibited binding of GFP-S1493-685 and mCherry-b1 (Fig. 3C). As a comparison, Caco-2 and Calu-3 cells were incubated with soluble ACE2, which inhibited SARS-CoV-2 infection in both cases (fig. S4C). Next, we turned to the small molecule EG00229, a selective NRP1 antagonist that binds the b1 CendR binding pocket and inhibits VEGF-A binding (Fig. 3D) (14). ITC established that EG00229 bound to the NRP1 b1 domain with a dissociation constant (Kd) of 5.1 and 11.0 μM at pH 7.5 and 5.5, respectively (Fig. 3E). EG00229 inhibited the direct binding between b1 and the S1 CendR peptide, and the immunoprecipitation of GFP-S1493-685 by mCherry-b1 (Fig. 3E and fig. S4D). Finally, incubation of Caco-2 cells with EG00229 reduced the efficiency of SARS-CoV-2 infection at 7 and 16 hpi (Fig. 3F). Thus, the SARS-CoV-2 interaction with NRP1 can be targeted to reduce viral infectivity in relevant human cell lines (fig. S5). Cell entry of SARS-CoV-2 depends on priming by host cell proteases (5, 6, 15). Our data indicate that a component of SARS-CoV-2 S protein binding to cell surface neuropilins occurs via the S1 CendR motif generated by the furin cleavage of S1/S2. Though not affecting cell surface attachment, this interaction promotes entry and infection by SARS-CoV-2 in physiologically relevant cell lines widely used in the study of COVID-19. The molecular basis for the effect is unclear, but neuropilins are known to mediate the internalization of CendR ligands through an endocytic process resembling macropinocytosis, (8, 16, 17). Notably, gene expression analysis has revealed an up-regulation of NRP1 and NRP2 in lung tissue from COVID-19 patients (18). A SARS-CoV-2 virus with a natural deletion of the S1/S2 furin cleavage site demonstrated attenuated pathogenicity in hamster models (19). NRP1 binding to the CendR peptide in S1 is thus likely to play a role in the increased infectivity of SARS-CoV-2 compared with SARS-CoV. The ability to target this specific interaction may provide a route for COVID-19 therapies. Supplementary Materials science.sciencemag.org/content/370/6518/861/suppl/DC1 Materials and Methods Figs. S1 to S5 Tables S1 to S3 References (20–33) MDAR Reproducibility Checklist https://creativecommons.org/licenses/by/4.0/ This is an open-access article distributed under the terms of the Creative Commons Attribution license, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. References and Notes ↵WHO Coronavirus disease, 2019 (COVID-19) Weekly Epidemiological Update – 31 August 2020. https://www.who.int/docs/default-source/coronaviruse/situation-reports/20200831-weekly-epi-update-3.pdf?sfvrsn=d7032a2a_4 ↵ E. Dong, H. Du, L. Gardner, An interactive web-based dashboard to track COVID-19 in real time. Lancet Infect. Dis. 20, 533–534 (2020). doi:10.1016/S1473-3099(20)30120-1pmid:32087114OpenUrlCrossRefPubMed ↵ D. Wrapp, N. Wang, K. S. Corbett, J. A. Goldsmith, C.-L. Hsieh, O. Abiona, B. S. Graham, J. S. McLellan, Cryo-EM structure of the 2019-nCoV spike in the prefusion conformation. Science 367, 1260–1263 (2020). doi:10.1126/science.abb2507pmid:32075877 A. C. Walls, Y.-J. Park, M. A. Tortorici, A. Wall, A. T. McGuire, D. Veesler, Structure, Function, and Antigenicity of the SARS-CoV-2 Spike Glycoprotein. Cell 181, 281–292.e6 (2020). doi:10.1016/j.cell.2020.02.058pmid:32155444OpenUrlCrossRefPubMed ↵ M. Hoffmann, H. Kleine-Weber, S. Pöhlmann, A multibasic cleavage site in the spike protein of SARS-CoV-2 is essential for infection of human lung cells. Mol. Cell 78, 779–784.e5 (2020). doi:10.1016/j.molcel.2020.04.022pmid:32362314OpenUrlCrossRefPubMed ↵ M. Hoffmann, H. Kleine-Weber, S. Schroeder, N. Krüger, T. Herrler, S. Erichsen, T. S. Schiergens, G. Herrler, N.-H. Wu, A. Nitsche, M. A. Müller, C. Drosten, S. Pöhlmann, SARS-CoV-2 cell entry depends on ACE2 and TMPRSS2 and is blocked by a clinically proven protease inhibitor. Cell 181, 271–280.e8 (2020). doi:10.1016/j.cell.2020.02.052pmid:32142651OpenUrlCrossRefPubMed ↵ J. Shang, Y. Wan, C. Luo, G. Ye, Q. Geng, A. Auerbach, F. Li, Cell entry mechanisms of SARS-CoV-2. Proc. Natl. Acad. Sci. U.S.A. 117, 11727–11734 (2020). doi:10.1073/pnas.2003138117pmid:32376634 ↵ T. Teesalu, K. N. Sugahara, V. R. Kotamraju, E. Ruoslahti, C-end rule peptides mediate neuropilin-1-dependent cell, vascular, and tissue penetration. Proc. Natl. Acad. Sci. U.S.A. 106, 16157–16162 (2009). doi:10.1073/pnas.0908201106pmid:19805273 ↵ H. F. Guo, C. W. Vander Kooi, Neuropilin functions as an essential cell surface receptor. J. Biol. Chem. 290, 29120–29126 (2015). doi:10.1074/jbc.R115.687327pmid:26451046 ↵ A. Plein, A. Fantin, C. Ruhrberg, Neuropilin regulation of angiogenesis, arteriogenesis, and vascular permeability. Microcirculation 21, 315–323 (2014). doi:10.1111/micc.12124pmid:24521511 ↵ R. Hollandi, A. Szkalisity, T. Toth, E. Tasnadi, C. Molnar, B. Mathe, I. Grexa, J. Molnar, A. Balind, M. Gorbe, M. Kovacs, E. Migh, A. Goodman, T. Balassa, K. Koos, W. Wang, J. C. Caicedo, N. Bara, F. Kovacs, L. Paavolainen, T. Danka, A. Kriston, A. E. Carpenter, K. Smith, P. Horvath, nucleAIzer: A parameter-free deep learning framework for nucleus segmentation using image style transfer. Cell Syst. 10, 453–458.e6 (2020). doi:10.1016/j.cels.2020.04.003OpenUrlCrossRef ↵ M. W. Parker, P. Xu, X. Li, C. W. Vander Kooi, Structural basis for selective vascular endothelial growth factor-A (VEGF-A) binding to neuropilin-1. J. Biol. Chem. 287, 11082–11089 (2012). doi:10.1074/jbc.M111.331140pmid:22318724 ↵ B. J. Janssen, T. Malinauskas, G. A. Weir, M. Z. Cader, C. Siebold, E. Y. Jones, Neuropilins lock secreted semaphorins onto plexins in a ternary signaling complex. Nat. Struct. Mol. Biol. 19, 1293–1299 (2012). doi:10.1038/nsmb.2416pmid:23104057OpenUrlCrossRefPubMed ↵ A. Jarvis, C. K. Allerston, H. Jia, B. Herzog, A. Garza-Garcia, N. Winfield, K. Ellard, R. Aqil, R. Lynch, C. Chapman, B. Hartzoulakis, J. Nally, M. Stewart, L. Cheng, M. Menon, M. Tickner, S. Djordjevic, P. C. Driscoll, I. Zachary, D. L. Selwood, Small molecule inhibitors of the neuropilin-1 vascular endothelial growth factor A (VEGF-A) interaction. J. Med. Chem. 53, 2215–2226 (2010). doi:10.1021/jm901755gpmid:20151671OpenUrlCrossRefPubMed ↵ J. K. Millet, G. R. Whittaker, Physiological and molecular triggers for SARS-CoV membrane fusion and entry into host cells. Virology 517, 3–8 (2018). doi:10.1016/j.virol.2017.12.015pmid:29275820OpenUrlCrossRefPubMed ↵ M. Simons, E. Gordon, L. Claesson-Welsh, Mechanisms and regulation of endothelial VEGF receptor signalling. Nat. Rev. Mol. Cell Biol. 17, 611–625 (2016). doi:10.1038/nrm.2016.87pmid:27461391OpenUrlCrossRefPubMed ↵ H. B. Pang, G. B. Braun, T. Friman, P. Aza-Blanc, M. E. Ruidiaz, K. N. Sugahara, T. Teesalu, E. Ruoslahti, An endocytosis pathway initiated through neuropilin-1 and regulated by nutrient availability. Nat. Commun. 5, 4904 (2014). doi:10.1038/ncomms5904pmid:25277522OpenUrlCrossRefPubMed ↵ M. Ackermann, S. E. Verleden, M. Kuehnel, A. Haverich, T. Welte, F. Laenger, A. Vanstapel, C. Werlein, H. Stark, A. Tzankov, W. W. Li, V. W. Li, S. J. Mentzer, D. Jonigk, Pulmonary vascular endothelialitis, thrombosis, and angiogenesis in Covid-19. N. Engl. J. Med. 383, 120–128 (2020). doi:10.1056/NEJMoa2015432pmid:32437596OpenUrlCrossRefPubMed ↵ S.-Y. Lau, P. Wang, B. W.-Y. Mok, A. J. Zhang, H. Chu, A. C.-Y. Lee, S. Deng, P. Chen, K.-H. Chan, W. Song, Z. Chen, K. K.-W. To, J. F.-W. Chan, K.-Y. Yuen, H. Chen, Attenuated SARS-CoV-2 variants with deletions at the S1/S2 junction. Emerg. Microbes Infect. 9, 837–842 (2020). doi:10.1080/22221751.2020.1756700pmid:32301390OpenUrlCrossRefPubMed ↵ A. D. Davidson, M. K. Williamson, S. Lewis, D. Shoemark, M. W. Carroll, K. J. Heesom, M. Zambon, J. Ellis, P. A. Lewis, J. A. Hiscox, D. A. Matthews, Characterisation of the transcriptome and proteome of SARS-CoV-2 reveals a cell passage induced in-frame deletion of the furin-like cleavage site from the spike glycoprotein. Genome Med. 12, 68 (2020). doi:10.1186/s13073-020-00763-0pmid:32723359OpenUrlCrossRefPubMed M. Berger Rentsch, G. Zimmer, A vesicular stomatitis virus replicon-based bioassay for the rapid and sensitive determination of multi-species type I interferon. PLOS ONE 6, e25858 (2011). doi:10.1371/journal.pone.0025858pmid:21998709OpenUrlCrossRefPubMed K. Smith, Y. Li, F. Piccinini, G. Csucs, C. Balazs, A. Bevilacqua, P. Horvath, CIDRE: An illumination-correction method for optical microscopy. Nat. Methods 12, 404–406 (2015). doi:10.1038/nmeth.3323pmid:25775044OpenUrlCrossRefPubMed O. Ronneberger, P. Fischer, T. Brox, U-net: Convolutional networks for biomedical image segmentation, in Medical Image Computing and Computer-Assisted Intervention –MICCAI 2015, N. Navab, J. Hornegger, W. Wells, A. Frangi, Eds., Lecture Notes in Computer Science (Springer International Publishing, 2015), vol. 9351, pp. 234–241. F. Piccinini, T. Balassa, A. Szkalisity, C. Molnar, L. Paavolainen, K. Kujala, K. Buzas, M. Sarazova, V. Pietiainen, U. Kutay, K. Smith, P. Horvath, Advanced cell classifier: User-friendly machine-learning-based software for discovering phenotypes in high-content imaging data. Cell Syst. 4, 651–655.e5 (2017). doi:10.1016/j.cels.2017.05.012pmid:28647475OpenUrlCrossRefPubMed B. A. Appleton, P. Wu, J. Maloney, J. Yin, W.-C. Liang, S. Stawicki, K. Mortara, K. K. Bowman, J. M. Elliott, W. Desmarais, J. F. Bazan, A. Bagri, M. Tessier-Lavigne, A. W. Koch, Y. Wu, R. J. Watts, C. Wiesmann, Structural studies of neuropilin/antibody complexes provide insights into semaphorin and VEGF binding. EMBO J. 26, 4902–4912 (2007). doi:10.1038/sj.emboj.7601906pmid:17989695 C. W. Vander Kooi, M. A. Jusino, B. Perman, D. B. Neau, H. D. Bellamy, D. J. Leahy, Structural basis for ligand and heparin binding to neuropilin B domains. Proc. Natl. Acad. Sci. U.S.A. 104, 6152–6157 (2007). doi:10.1073/pnas.0700043104pmid:17405859 B. G. Dorner, S. Steinbach, M. B. Hüser, R. A. Kroczek, A. Scheffold, Single-cell analysis of the murine chemokines MIP-1α, MIP-1β, RANTES and ATAC/lymphotactin by flow cytometry. J. Immunol. Methods 274, 83–91 (2003). doi:10.1016/S0022-1759(02)00498-2pmid:12609535 W. Kabsch, XDS. Acta Crystallogr. D Biol. Crystallogr. 66, 125–132 (2010). doi:10.1107/S0907444909047337pmid:20124692 P. R. Evans, G. N. Murshudov, How good are my data and what is the resolution? Acta Crystallogr. D Biol. Crystallogr. 69, 1204–1214 (2013). doi:10.1107/S0907444913000061pmid:23793146 A. J. McCoy, R. W. Grosse-Kunstleve, P. D. Adams, M. D. Winn, L. C. Storoni, R. J. Read, Phaser crystallographic software. J. Appl. Crystallogr. 40, 658–674 (2007). doi:10.1107/S0021889807021206pmid:19461840 P. D. Adams, P. V. Afonine, G. Bunkóczi, V. B. Chen, I. W. Davis, N. Echols, J. J. Headd, L.-W. Hung, G. J. Kapral, R. W. Grosse-Kunstleve, A. J. McCoy, N. W. Moriarty, R. Oeffner, R. J. Read, D. C. Richardson, J. S. Richardson, T. C. Terwilliger, P. H. Zwart, PHENIX: A comprehensive Python-based system for macromolecular structure solution. Acta Crystallogr. D Biol. Crystallogr. 66, 213–221 (2010). doi:10.1107/S0907444909052925pmid:20124702 V. B. Chen, W. B. Arendall 3rd, J. J. Headd, D. A. Keedy, R. M. Immormino, G. J. Kapral, L. W. Murray, J. S. Richardson, D. C. Richardson, MolProbity: All-atom structure validation for macromolecular crystallography. Acta Crystallogr. D Biol. Crystallogr. 66, 12–21 (2010). doi:10.1107/S0907444909042073pmid:20057044 ↵ L. Holm, P. Rosenström, Dali server: Conservation mapping in 3D. Nucleic Acids Res. 38, W545-9 (2010). doi:10.1093/nar/gkq366pmid:20457744 Acknowledgments: We thank the Bristol Synthetic Biology Centre and the Advanced Computing Research Centre for provision of HPC (Bluegem), and the University of Bristol Wolfson Bioimaging Facility. We thank the University of Queensland Remote Operation Crystallisation and X-ray facility (UQ-ROCX) and the staff for their support with the crystallization experiments, and the staff of the Australian Synchrotron for assistance with x-ray diffraction data collection. Funding: J.L.D. was supported by a Wellcome Trust studentship from the Dynamic Molecular Cell Biology Ph.D. program (203959/Z/16/Z), C.A.P. was supported by Beca Fundación Ramón Areces Estudios Postdoctorales en el Extranjero, and M.K.W. was supported by an MRC grant (MR/R020566/1) awarded to A.D.D. This project has received funding from the MRC (MR/P018807/1), Wellcome Trust (104568/Z/14/2), Lister Institute of Preventive Medicine, and Elizabeth Blackwell Institute for Health Research Rapid Response Call (COVID-19) awarded to P.J.C, the European Research Council under the European Union’s Horizon 2020 research and innovation program (No 856581 - CHUbVi), and from MRC-AMED (MR/T028769/1) awarded to Y.Y., the Swiss National Science Foundation and Kanton Zurich awarded to U.F.G. B.M.C. is supported by an Australian National Health and Medical Research Council (NHMRC) Senior Research Fellowship (APP1136021) and Project Grant (APP1156493), and the United States Food and Drug Administration grant no. HHSF223201510104C “Ebola Virus Disease: correlates of protection, determinants of outcome and clinical management” amended to incorporate urgent COVID-19 studies awarded to J.A.H., A.D.D., and D.A.M. R.H. and P.H. acknowledge support from the LENDULET-BIOMAG Grant (2018-342), from H2020-discovAIR (874656), and from Chan Zuckerberg Initiative, Seed Networks for the HCA-DVP. T.T. was supported by the European Regional Development Fund (Project no. 2014-2020.4.01.15-0012), by European Research Council grant GLIOGUIDE and Estonian Research Council (grants PRG230 and EAG79, to T.T.). Author contributions: J.L.D., B.S., A.H., P.J.C., and Y.Y. conceived the study. J.L.D., B.S., K.K, and Y.Y. performed most of the experiments. K.K., M.K.W., D.A.M., and A.D.D. performed all work with infectious SARS-CoV-2 supervised by A.D.D. M.K.W. and A.D.D. isolated SARS-CoV-2 strains used for the work. K.C., C.A.P., M.B., L.S.G., U.F.G., K.K., R.B.S., D.K.S., J.A.H., and T.T. did experimental work and/or provided essential reagents. R.H. and P.H. performed image analysis. B.S., A.D.D., B.M.C., P.J.C., and Y.Y. supervised the research. J.L.D., B.S., A.D.D., P.J.C., and Y.Y. wrote the manuscript and made the figures. All authors read and approved the final manuscript. Competing interests: T.T. is an inventor of patents on CendR peptides and a shareholder of Cend Therapeutics Inc., a company that holds a license for the CendR peptides and is developing the peptides for cancer therapy. J.A.H. is a member of the Department of Health, New and Emerging Respiratory Virus Threats Advisory Group (NERVTAG) and the Department of Health, Testing Advisory Group. U.F.G. is a consultant to F. Hoffmann–La Roche Ltd, Switzerland. All other authors declare no competing interests. Data and materials availability: Coordinates and structure factors for the NRP1 b1-S1 CendR peptide complex have been deposited at the Protein Data Bank (PDB) with accession code 7JJC. All other data are available in the manuscript or the supplementary materials. This work is licensed under a Creative Commons Attribution 4.0 International (CC BY 4.0) license, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. To view a copy of this license, visit https://creativecommons.org/licenses/by/4.0/. This license does not apply to figures/photos/artwork or other content included in the article that is credited to a third party; obtain authorization from the rights holder before using such material.
|
Cytokine Storm Cytokine storm, a life-threatening disorder involving cytokine elevations and immune-cell hyperactivation, has various causes and is characterized by constitutional symptoms
Via Krishan Maggon
|
|
Scooped by
Gilbert C FAURE
December 9, 2020 6:14 AM
|
|
|
Scooped by
Gilbert C FAURE
December 9, 2020 3:56 AM
|
DNA and RNA stimulate the mammalian innate immune system through activation of Toll-like
receptors (TLRs). DNA containing methylated CpG motifs, however, is not stimulatory.
Selected nucleosides in naturally occurring RNA are also methylated or otherwise modified,
but the immunomodulatory effects of these alterations remain untested. We show that
RNA signals through human TLR3, TLR7, and TLR8, but incorporation of modified nucleosides
m5C, m6A, m5U, s2U, or pseudouridine ablates activity. Dendritic cells (DCs) exposed
to such modified RNA express significantly less cytokines and activation markers than
those treated with unmodified RNA.
|
|
Scooped by
Gilbert C FAURE
December 6, 2020 2:37 PM
|
|
|
Scooped by
Gilbert C FAURE
December 3, 2020 1:33 PM
|
RESEARCH ARTICLE Preferential infection of CD4+ memory T cells by human immunodeficiency virus type 1: evidence for a role in the selective T-cell functional defects observed in infected individuals. S M Schnittman, H C Lane, J Greenhouse, J S Justement, M Baseler, and A S Fauci PNAS August 1, 1990 87 (16) 6058-6062; https://doi.org/10.1073/pnas.87.16.6058 Article Info & Metrics PDF Abstract CD4+ T cells of patients with AIDS exhibit a qualitative defect in their ability to respond to soluble antigen while their responses to mitogens remain normal. CD4+ T cells can be broadly divided phenotypically into "naive" [CD45RA+ (2H4+)] and "memory" [CD29+ (4B4+) or CD45RO+ (UCHL1+)] cell subpopulations, which represent distinct maturation stages. To determine the human immunodeficiency virus type 1 (HIV-1) infectability of memory and naive CD4+ T-cell subsets in vitro and to determine the in vivo preference of HIV-1 in these subpopulations, we obtained highly purified CD4+ T-cell subsets from normal and HIV-1-infected individuals and studied them by viral cultivation, quantitative polymerase chain reaction, and functional assays. Polymerase chain reaction studies demonstrated that the memory cell subset of CD4+ T cells is preferentially infected (4- to 10-fold more than naive T cells) by HIV-1 in vitro, and these memory cells are the principal reservoir for HIV-1 within CD4+ T cells obtained from infected individuals. Functional abnormalities attributable to CD4+ T cells in HIV-infected individuals (failure to respond in vitro to soluble antigen or to anti-CD3 monoclonal antibodies) were shown to reside primarily within these memory cells. Thus, the present study suggests that the selective functional defects present in the memory CD4+ T-cell subset of HIV-infected individuals may be a direct result of the preferential infection and consequently greater viral burden within these cells. Previous Next Share Table of Contents Submit Sign up for the PNAS Highlights newsletter—the top stories in science, free to your inbox twice a month: Sign up for Article Alerts Sign up JUMP TO SECTION YOU MAY ALSO BE INTERESTED IN Changing environmental conditions and genetic adaptations may explain how penguins radiated and expanded their geographic ranges to encompass diverse environments. Image credit: Aurora Fernández Durán (photographer). In the United States, mortality rates and life expectancy were worse for Blacks during nonpandemic years than for Whites during the COVID-19 pandemic, a study finds. Image credit: Pixabay/PIRO4D. Genetic insights could help shore up populations of a rare dog species thought to be nearly extinct in the wild. Image credit: Anang Dianto (photographer). Featured QnAs QnAs with Enquye Negash, Zeresenay Alemseged, and Jonathan Wynn Top Left: Image credit: Dikka Research Project. Top Right: Image credit: Alem Abreha (photographer). Bottom: Image credit: Dikka Research Project. Researchers reveal key details of how the heat shock protein mechanism disassembles the α-synuclein amyloids linked to Parkinson’s disease. Image credit: Rosenzweig lab, Weizmann Institute of Science. Similar Articles
|
|
Scooped by
Gilbert C FAURE
December 3, 2020 12:57 PM
|
We report the updated classification of Inborn Errors of Immunity/Primary Immunodeficiencies, compiled by the International Union of Immunological Societies Expert Committee. This report documents the key clinical and laboratory features of 430 inborn errors of immunity, including 64 gene defects that have either been discovered in the past 2 years since the previous update (published January 2018) or were characterized earlier but have since been confirmed or expanded upon in subsequent studies. The application of next-generation sequencing continues to expedite the rapid identification of novel gene defects, rare or common; broaden the immunological and clinical phenotypes of conditions arising from known gene defects and even known variants; and implement gene-specific therapies. These advances are contributing to greater understanding of the molecular, cellular, and immunological mechanisms of disease, thereby enhancing immunological knowledge while improving the management of patients and their families. This report serves as a valuable resource for the molecular diagnosis of individuals with heritable immunological disorders and also for the scientific dissection of cellular and molecular mechanisms underlying inborn errors of immunity and related human diseases.
|
|
Scooped by
Gilbert C FAURE
November 27, 2020 3:53 AM
|
Shomuradova et al. assessed the immune response to SARS-CoV-2 in convalescent patients
and healthy donors. Antigen-specific T cells were increased in convalescents and in
donors sampled during the pandemic. The work identified two public epitopes from S-glycoprotein.
T cell receptor repertoire profiling of S-glycoprotein specific lymphocytes revealed
public CDR3 motifs.
|
|
Scooped by
Gilbert C FAURE
November 25, 2020 1:29 PM
|
|
|
Scooped by
Gilbert C FAURE
November 23, 2020 6:00 AM
|
Our data shows that distinct subtypes of PAD display unique infection patterns. We also show that patients with agammaglobulinemia suffer more invasive infections and differ most significantly from all other forms of PAD studied. Our analysis has broad implications about infection surveillance, prog …

|
Suggested by
Société Francaise d'Immunologie
November 19, 2020 12:51 PM
|
Immunotherapies have transformed the treatment of several types of cancer over the last decade. Yet they focus on reactivating one arm of the immune system: cytotoxic T cells, which sniff out and kill tumor cells.
|
|
Scooped by
Gilbert C FAURE
November 17, 2020 1:35 PM
|
|
|
Scooped by
Gilbert C FAURE
November 13, 2020 1:40 PM
|
|


 Scoop.it!