Rheumatology-Rhumatologie
14.2K views | +3 today
 
Scooped by Gilbert C FAURE
onto Rheumatology-Rhumatologie
October 23, 2019 4:46 AM
Scoop.it!

Detection of Cell Surface Ligands for Human Synovial γδ T Cells | The Journal of Immunology

Detection of Cell Surface Ligands for Human Synovial γδ T Cells | The Journal of Immunology | Rheumatology-Rhumatologie | Scoop.it
KEY POINTS TCR-γδ tetramer identified ligand expression by flow cytometry. TCR-γδ ligands were induced on activated monocytes or T cells. Bioinformatics combined with mass spectrometry produced an overlapping list of 16 candidate ligands. Visual Abstract Abstract Lack of understanding of the nature and physiological regulation of γδ T cell ligands has considerably hampered full understanding of the function of these cells. We developed an unbiased approach to identify human γδ T cells ligands by the production of a soluble TCR-γδ (sTCR-γδ) tetramer from a synovial Vδ1 γδ T cell clone from a Lyme arthritis patient. The sTCR-γδ was used in flow cytometry to initially define the spectrum of ligand expression by both human tumor cell lines and certain human primary cells. Analysis of diverse tumor cell lines revealed high ligand expression on several of epithelial or fibroblast origin, whereas those of hematopoietic origin were largely devoid of ligand. This allowed a bioinformatics-based identification of candidate ligands using RNAseq data from each tumor line. We further observed that whereas fresh monocytes and T cells expressed low to negligible levels of TCR-γδ ligands, activation of these cells resulted in upregulation of surface ligand expression. Ligand upregulation on monocytes was partly dependent upon IL-1β. The sTCR-γδ tetramer was then used to bind candidate ligands from lysates of activated monocytes and analyzed by mass spectrometry. Surface TCR-γδ ligand was eliminated by treatment with trypsin or removal of glycosaminoglycans, and also suppressed by inhibition of endoplasmic reticulum–Golgi transport. Of particular interest was that inhibition of glycolysis also blocked TCR-γδ ligand expression. These findings demonstrate the spectrum of ligand(s) expression for human synovial Vδ1 γδ T cells as well as the physiology that regulates their expression. This article is featured in In This Issue, p.2353 Introduction Full understanding of γδ T cell biology has been handicapped by ignorance of the ligands for most TCR-γδ. γδ T cells reside at mucosal and epithelial barriers and often accumulate at sites of inflammation with autoimmunity, infections, or tumors (1). Evidence suggests that γδ T cells provide protection against infections with bacteria, viruses, and protozoans and are generally beneficial in autoimmunity (1–17). In addition, a role for γδ T cells in the immune response against tumors in humans is evident from a seminal study reporting that intratumoral γδ T cells are the most favorable prognostic immune population across 39 cancer types in humans (18). γδ T cells are often highly lytic against transformed proliferative cells, infected cells, and infiltrating CD4+ T cells in inflammatory arthritis (9, 17, 19). They can produce a variety of cytokines including IFN-γ, TNF-α, and IL-17 (20), as well as insulin-like growth factor-1 (IGF1) and keratinocyte growth factor (KGF) that promote epithelial wound repair (21). These collective studies indicate that a principal function of γδ T cells is in response to tissue injury of various causes. It is, thus, not surprising that γδ T cells are often suggested to react to host components that are upregulated or exposed during proliferation or cell injury (22). As such, γδ T cells may function in tissue homeostasis and immunoregulation as much as in protection from infection. Yet in the vast majority of cases, little if anything is known regarding the nature of these self-components or whether they actually engage the TCR-γδ. Whereas αβ T cells recognize proteins that are processed into peptides and presented on MHC molecules, the few proposed ligands for γδ T cells suggest that they recognize mostly intact proteins directly, without MHC restriction. This makes them highly attractive for immunotherapy. Despite the elaborate mechanisms that αβ T cells and B cells use to prevent autoreactivity, γδ T cells have been frequently reported to respond to autologous proteins. Furthermore, in contrast to other lymphocytes that maximize the potential diversity of their receptors, γδ T cells frequently show limitations in their diversity. Thus, human γδ T cells comprise a subset of Vδ2 T cells, the predominant γδ in peripheral blood that respond to prenyl phosphates and certain alkyl amines (23–25), and Vδ1 T cells, which do not respond to these compounds and often accumulate at epithelial barriers and sites of inflammation (1). A similar limited repertoire occurs in the mouse in which Vγ5Vδ1 cells colonize the epidermis, and a Vγ6Vδ1 subset colonizes the tongue, lung, and female reproductive tract (21, 26). This restricted repertoire implies that TCR-γδ ligands may also be limited. This may provide for a more rapid response and perhaps explain why, in contrast to αβ T cells and B cells, it is difficult to generate Ag-specific γδ T cells by immunization with a defined Ag. Various ligands for γδ T cells have been proposed, although only a few have been confirmed to bind to TCR-γδ, and these lack any obvious similarity in structure. γδ T cells for which ligands have been identified include the murine γδ T cell clone G8, which recognizes the MHC class I–like molecules T10 and T22 (27), γδ T cells from mice infected with HSV that recognize herpes glycoprotein gl (28), a subset of murine and human γδ T cells that bind the algae protein PE (20), a human γδ T cell clone G115 that recognizes ATP synthase complexed with ApoA-1 (28), a human γδ T cell clone (Vγ4Vδ5) from a CMV-infected transplant patient that recognizes endothelial protein C receptor (EPCR) (29), and some human Vδ1 T cells that recognize CD1d-sulfatide Ags (30). However, to date no systematic process has been reported for determining the spectrum of human TCR-γδ ligands. To provide an unbiased approach for the identification of candidate ligands for human γδ T cells, we produced a biotinylatable form of a soluble TCR-γδ (sTCR-γδ) from a synovial Vδ1 γδ T cell clone of a Lyme arthritis patient. The tetramerized sTCR-γδ was used in flow cytometry to identify various cell types that expressed candidate ligands. Initial analysis of 24 tumor cell lines identified a set of nine ligand-positive tumors, enriched for those of epithelial and fibroblast origin, and 15 ligand-negative tumors, largely of hematopoietic origin. In addition, ligand was not expressed by primary monocytes or T cells, although each could be induced to express ligand following their activation. Ligand expression was sensitive to trypsin digestion, revealing the protein nature of the ligands, and was also reduced by inhibition of glycolysis. These findings provide a framework and strategy for the identification of individual ligands for human synovial γδ T cells. Materials and Methods Production of a sTCR-γδ Human synovial γδ T cell clones from a Lyme arthritis patient were produced as previously described (9, 31). One of these clones, Bb15, was chosen for production of the sTCR-γδ using modification of a previously reported procedure (32, 33). Both TCR chains were produced as a single transcript in a baculovirus vector. The pBACp10pH vector used contains two back-to-back promoters, p10 and polyhedrin (Fig. 1A). The p10 promoter is followed by multiple cloning sites for the γ-chain, and the polyhedrin promoter is followed by multiple cloning sites for the δ-chain. Downstream of the γ-chain, we placed a hexa-His tag for nickel column purification, followed by a biotinylation sequence for tetramerization. The γ-chain and δ-chain were PCR amplified using high fidelity polymerase (Deep Vent Polymerase; New England Biolabs). Both TCR chain sequences were verified following the initial PCR amplification as well as after insertion into the pBACp10pH vector. Virus encoding the sTCR-γδ was generated by cotransfection of Sf21 moth cells using the Sapphire baculovirus DNA and Transfection kit (Orbigen) with the sTCR pBACp10pH construct. Virus was harvested 6 d later and used as primary stocks (P1 stock). Two additional rounds of viral amplification, P2 and P3, were completed using midlog phase Sf21 cells (∼1.6 × 10⁶ cells/ml) allowed to adhere for 1 h before infecting at a multiplicity of infection of 0.01 or 0.1 with P1 and P2 stock, respectively. After 72 h of infection, culture medium was clarified by centrifugation (1000 × g for 10 min) and filtration (VacuCap 90PF 0.8/0.2 μm Supor membrane filter units; Pall, Westborough, MA) before storing in the dark at 4°C until use. Protein production occurred in 12-l batches of midlog phase (∼1.6 × 10⁶ cells/ml) Hi5 cells growing in suspension (0.5 l of culture in 1 l spinner flasks) and infected with P3 stock at a 1:50 dilution. Following 72 h of infection, cells were removed by centrifugation and filtration as described above. The filtered supernatant (∼12 l) containing secreted sTCR-γδ was concentrated to ∼100 ml before dialyzing against 1 l of nickel column loading buffer (20 mM NaPhosphate buffer, pH 7.4, 20 mM imidazole, 0.5 M NaCl) using a Pellicon diafiltration system with two 10K MWCO membranes (MilliporeSigma, Burlington, MA) back down to ∼100 ml. After system flushing, the final sample volume was ∼200 ml. It was then loaded onto loading buffer–equilibrated His-Trap HP columns (GE Healthcare, Little Chalfont, U.K.) at 100 ml per 2 × 5 ml columns. Columns were washed with at least 10 column volumes of loading buffer until baseline absorption was achieved. Bound proteins were eluted using a gradient from 20 to 500 mM imidiazole over 20 column volumes. Elution was monitored by absorbance at 280 nM, and 1 ml fractions were collected. Fractions containing the target protein were identified using SDS-PAGE gel analysis using Coomassie Blue. High purity (>95%) sTCR-γδ fractions were pooled, dialyzed against PBS (pH 7.4), and frozen at −80°C until used in future studies. Yields were typically ∼1.0–2.5 mg/l of culture. Purified sTCR-γδ was then biotinylated using a biotin-protein ligase system (Avidity) and tetramerized with streptavidin-PE (BioLegend) for FACS staining. Verification of TCR-γδ protein was confirmed by SDS-PAGE gel analysis using Coomassie Blue as well as immunoblot using Abs to Vδ1 or Cγ (Endogen). Flow cytometry Cells were stained with either sTCR-γδ-PE (10 μg/ml) or negative controls that included streptavidin-PE (10 μg/ml), IgG-PE (10 μg/ml) (BioLegend), or a sTCRαβ-PE (a kind gift of Dr. M. Davis). Additional surface staining of T cells consisted of CD4, CD8, CD19, and CD25 (BioLegend). Live–Dead staining (BD Bioscience) was used to eliminate dead cells from analysis. Samples were run on an LSRII flow cytometer (Becton Dickinson). Purification and activation of human monocytes and T cells and cell lines Human monocytes were purified from human PBMC using CD14-labeled magnetic beads, followed by column purification (Miltenyi Biotec) and then cultured in RPMI complete medium with 10% FCS in the absence or presence of either a Borrelia burgdorferi sonicate (10 μg/ml) or LPS (1 μg/ml; Sigma-Aldrich) for 18 h. To some cultures were added TNF-α (10 ng/ml) (BioLegend), anti-TNF-α (10 μg/ml) (BioLegend), IL-1β (10 pg/ml) (Invitrogen), or anti–IL-1β (5 μg/ml) (R&D Systems). Cells were then stained with the sTCR-γδ tetramer. T cells from PBMC were either used fresh or were activated with anti-CD3/anti-CD28 (each 10 μg/ml; BioLegend) + IL-2 (50 U/ml; Cetus) and propagated for 3 d. Cells were then stained with the sTCR-γδ tetramer. Human PBMC were obtained using an approved protocol from The University of Vermont Human Studies Committee. Verified cell lines were obtained from American Type Culture Collection. CHO cells deficient for glycosaminoglycans (GAGs) were derived as previously described (34). Bioinformatics analysis Expression profiling (35) based on Illumina RNAseq technology (36) was used to characterize the transcriptomes of 22 of the 24 tumor cell lines examined (excluding bronchoepithelial cell line and 2fTGH). Expression data for all known genes (37) were generated, and those genes whose representation in tetramer-positive cell lines was significantly higher than in negative cell lines were considered as candidate ligands. Mass spectrometry analysis Biotinylated sTCR-γδ was bound to avidin magnetic beads and then incubated with cell lysates from monocytes activated with B. burgdorferi sonicate. Magnetic beads alone, without TCR-γδ tetramer, with monocyte lysates served as a negative control. After 4 h, beads were washed five times, and bound proteins were then separated on polyacrylamide gels. Gel lanes for each sample type were cut into 12 identical regions and diced into 1-mm cubes. In-gel tryptic digestion was conducted on each region as previously described (38). Extracted peptides were subjected to liquid chromatography tandem mass spectrometry (38), except that the analysis was performed using an LTQ linear ion trap mass spectrometer (Thermo Fisher Scientific, Waltham, MA). Tandem mass spectra were searched against the forward and reverse concatenated human IPI database using SEQUEST, requiring fully tryptic peptides, allowing a mass tolerance of 2 Da and mass additions of 16 Da for the oxidation of methionine and 71 Da for the addition of acrylamide to cysteine. SEQUEST matches in the first position were then filtered by XCorr scores of 1.8, 2, and 2.7 for singly, doubly, and triply charged ions, respectively. Protein matches made with more than two unique peptides were further considered. This list had a peptide false discovery rate of <0.01%. Inhibition of glycolysis, transcription, translation, and endoplasmic reticulum–Golgi transport or trypsin or heparinases I–III treatment Inhibition of glycolysis was performed using the 2-deoxyglucose (2-DG, 5 mM; Sigma-Aldrich) for 48 h. Transcription and translation were inhibited using, respectively, actinomycin D (5 μg/ml; ICN Biomedicals) or cycloheximide (1 μg/ml; MilliporeSigma) for 18 h. Endoplasmic reticulum (ER)–Golgi transport was blocked using brefeldin A (1:1000) or monensin (1:1400) (BD Bioscience) for 18 h. Cell surface protein digestion was performed using trypsin (Invitrogen) (1×; 5–10 min, 37°C.). GAGs were removed from cells by treatment with heparinases I–III (2 μU/ml) for 30 min in RPMI 1640 with no serum. The reaction was then stopped by the addition of PBS–BSA. Statistical analysis The following statistical tests were used: unpaired Student t test when comparing two conditions, and one-way ANOVA with Sidak test for correction for multiple comparisons when comparing multiple variables across multiple conditions. Results Production of a human synovial sTCR-γδ We previously produced a panel of synovial Vδ1 γδ T cells from Lyme arthritis patients (9, 31). A representative clone, Bb15 (Vδ1Vγ9), was selected from which to clone its TCR-γδ. The pBACp10pH vector has been used previously to produce murine sTCR-γδ tetramers (33). It contains two back-to-back promoters, p10 and polyhedrin, in which the p10 promoter is followed by multiple cloning sites for inserting the γ-chain, and the polyhedrin promoter is followed by multiple cloning sites for inserting the δ-chain (Fig. 1A). Downstream of the γ-chain we placed a hexa-His tag for purification, followed by a biotinylation BRP sequence for tetramerization with streptavidin-PE. Protein production was undertaken in Hi5 cells followed by purification using His-Trap HP columns. Fractions were analyzed by SDS-PAGE, and those with protein of the correct size were pooled, with yields typically of 1–2 mg/l of culture. A sample sTCR-γδ preparation is shown in Fig. 1B, stained with Coomassie Blue, showing bands of the expected size for the heterodimer under nonreducing (59 kDa) and reducing conditions (30/28 kDa for the γ- and δ-chains, respectively). The protein was stained by immunoblot with Abs to either Vδ1 or Cγ (Fig. 1C) and also blocked anti-γδ Ab staining of the synovial γδ T cell clones (Fig. 1D). The purified sTCR-γδ was then biotinylated and tetramerized with streptavidin-PE for use by flow cytometry. As an additional measure of specificity, sTCR-γδ tetramer staining of a fibrosarcoma tumor cell line (2fTGH) could be inhibited by anti-γδ Ab but not control IgG (Fig. 1E). Finally, staining of 2fTGH cells with the sTCR-γδ tetramer was dose dependent but did not increase with increasing dose on a negative tumor line, Daudi (Fig. 1F). FIGURE 1. Production of human synovial sTCR-γδ. (A) pBACp10pH vector containing the δ-chain driven by the polyhedrin promoter and the γ-chain with hexa-His and biotinylation BRP sequences driven by the p10 promoter from γδ T cell clone Bb15 (Vγ9Vδ1). (B) Sample of nickel NTA column-purified sTCR-γδ analyzed by SDS-PAGE under reducing and nonreducing conditions, and stained with Coomassie Blue. (C) Immunoblot of sTCR-γδ stained with anti-Vδ1 or anti-Cγ. (D) γδ T cell clone Bb15 was stained with anti–TCR-γδ Ab in the absence or presence of competing sTCR-γδ. (E) The fibrosarcoma cell line 2fTGH was stained with the sTCR-γδ in the absence or presence of the indicated concentrations of anti-γδ Ab or control IgG. (F) Titration of sTCR-γδ staining of the positively staining tumor line 2fTGH or negatively staining line Daudi. Number inserts indicate percent positively staining cells. Findings are representative of three experiments. Expression of sTCR-γδ candidate ligand(s) varies among cell lines We initially used the sTCR-γδ tetramer to screen a panel of 24 cell lines from a variety of cell types. None of the cell lines stained with the negative controls (IgG-PE, avidin-PE, or sTCR-αβ tetramer-PE), but the sTCR-γδ tetramer gave a spectrum of staining in which nine cell lines were strongly positive and the other cell lines manifested low to undetectable surface staining (Fig. 2). Of interest was that the positive group was enriched for cell lines of epithelial and fibroblast origin, cell types known to exist where γδ T cells are often found, such as skin, intestines, and synovium. With this information, expression profiling (35) using available RNAseq was used to characterize the transcriptomes of 22 of the 24 tumor cell lines (RNAseq on the bronchoepithelial and 2fTGH were not available). Expression data for all known genes (37) were generated, and those genes whose representation in tetramer-positive cell lines was significantly higher than in negative cell lines were considered to be candidate ligands. This produced an initial list of candidate ligands for sTCR-γδ (Supplemental Table I). FIGURE 2. sTCR-γδ tetramer staining of a cell line panel. A panel of 24 diverse cell lines was stained with either sTCR-αβ or sTCR-γδ, gated on live cells, and examined by flow cytometry. Shown are examples of tumors representing either (A) positive staining or (B) negative staining with sTCR-γδ, with the complete list summarized below each example. Number inserts indicate mean fluorescence intensity of entire histogram. Findings are representative of four experiments. Candidate sTCR-γδ ligands are sensitive to trypsin and reduced by inhibition of transcription, translation, ER–Golgi transport, or removal of GAGs We treated the positively staining cell lines with trypsin and noted a complete disappearance of surface staining, as exemplified for bronchoepithelial cells in Fig. 3A. Similar results were observed with two additional tumor lines. This supports the view that the TCR-γδ ligand contains a protein component essential for recognition by the receptor. We also observed no increase in sTCR-γδ tetramer staining of cells (C1R or HeLa) expressing CD1a, b, c, or d, nor with MICA/B (data not shown). Thus, at present there is no evidence that the synovial Vδ1 TCR-γδ ligand is one of these MHC class I–like molecules, at least bound to endogenous molecules from these particular cell lines. FIGURE 3. sTCR-γδ ligand is sensitive to protease, blockers of ER–Golgi transport, translation, or transcription and contains GAGs. The human bronchoepithelial cell line was either untreated or treated with (A) trypsin for 15 min, (B) untreated or treated for 18 h with cycloheximide or actinomycin D, or (C) untreated or treated for 18 h with brefeldin A or monensin. Cells were then stained with sTCR-γδ tetramer. (D) The 2fTGH fibrosarcoma cell line, wild-type CHO cells, or GAG-deficient CHO cells were either untreated or treated with a combination of heparinases I–III for 30 min and then stained with sTCR-γδ tetramer. Number inserts indicate mean fluorescence intensity of entire histogram. Findings are representative of three experiments. We further determined that surface TCR-γδ ligand expression was reduced by inhibition of protein translation or transcription with, respectively, cycloheximide or actinomycin D (Fig. 3B). Surface ligand was also considerably reduced by inhibition of transport from the ER to Golgi using either brefeldin A or monensin (Fig. 3C). This further demonstrated the protein nature of candidate TCR-γδ ligands. Finally, we examined the extent to which GAGs contribute to ligand binding by TCR-γδ. This was tested in two ways. Initially, the ligand-positive fibrosarcoma cell line 2fTGH was either treated or not with heparinases I–III, which removes most GAGs. This considerably reduced sTCR-γδ tetramer staining (Fig. 3D). This was further supported by the observation that sTCR-γδ stained wild-type but not GAG-deficient CHO cells (Fig. 3D). sTCR-γδ ligands are expressed by activated monocytes In considering what primary cells might express ligand(s) for the sTCR-γδ, we first examined fresh monocytes, as we had observed previously that following their activation with B. burgdorferi or LPS, monocytes could activate the synovial γδ T cell clones (31). Consistent with these earlier findings, we observed that the sTCR-γδ tetramer did not stain freshly isolated human monocytes, but following 24 h activation with a sonicate of B. burgdorferi or LPS, there was a robust upregulation of sTCR-γδ tetramer staining (Fig. 4). The same cells did not stain with negative controls that included avidin-PE, IgG-PE, or a human sTCR-αβ tetramer-PE. Because activated monocytes are known to produce certain cytokines, particularly TNF-α and IL-1β, we examined the possible influence of these cytokines on ligand expression. Curiously, the low level of sTCR-γδ tetramer staining of fresh monocytes was reduced further with TNF-α, whereas ligand expression by Borrelia-activated monocytes was not affected by the further addition of TNF-α or blocking anti–TNF-α Ab (Fig. 4B). By contrast, IL-1β increased ligand expression by fresh but not activated monocytes, and blocking anti–IL-1β Ab partially inhibited ligand expression by activated monocytes (Fig. 4C). Thus, sTCR-γδ ligand expression appears to be partly regulated by certain monocyte-derived cytokines. FIGURE 4. TCR-γδ ligand is induced on human monocytes following activation. (A) Freshly isolated monocytes were either unstimulated or activated with B. burgdorferi or LPS for 18 h and then stained with the indicated reagents and analyzed by flow cytometry. (B and C) Fresh monocytes or monocytes activated with Borrelia were incubated in the presence of medium alone or TNF-α or blocking anti-TNF-α (B) or IL-1β or blocking anti–IL-1β (C). Number inserts indicate percent positively staining cells. Error bars represent SEM. Findings are representative of four experiments. Given the induction of sTCR-γδ ligand expression by activated monocytes, we prepared lysates from Borrelia-activated monocytes and then used the biotinylated sTCR-γδ complexed with avidin magnetic beads as a bait. Following incubation with the monocyte lysates, the sTCR-γδ was isolated by magnetic purification and washed five times; bound proteins were separated on polyacrylamide gels, and gel slices were subjected to trypsin digestion and analyzed by mass spectrometry. Avidin magnetic beads alone incubated with monocyte lysates served as a negative control. This analysis yielded 291 unique proteins (Supplemental Table II). When compared with the list produced by the RNAseq bioinformatics approach of the tumor lines, 16 proteins were found in common (Supplemental Table III). Of interest is that two of these, Annexin A2 and heat shock protein 70, have previously been proposed as γδ ligands (39–41). sTCR-γδ ligands are expressed by activated T cells We further analyzed freshly isolated PBL from three individuals of various ages (28–66). This consistently revealed that fresh CD8+ T cells exhibited negligible sTCR-γδ staining, whereas a subset of fresh CD4+ T cells manifested modest levels of sTCR-γδ staining (Fig. 5A). In contrast to the freshly isolated T cells, following 3 d activation with anti-CD3/CD28 + IL-2, we observed that a subset of both CD4+ and CD8+ T cells now displayed high levels of sTCR-γδ staining (Fig. 5B). Both the proportion of cells expressing ligand and the density was higher on activated CD4+ T cells compared with CD8+ T cells. Given that in vitro–activated proliferating T cells express sTCR-γδ ligand, we considered that the subset of fresh CD4+ T cells expressing ligand might also represent a proliferative subset. One of the most rapidly proliferative T cell subsets in vivo is T regulatory cells (Treg) (42). Treg can be identified as a subset of fresh CD4+ T cells expressing CD25. Indeed, when we subset fresh human CD4+ T cells based on CD25 expression, sTCR-γδ tetramer staining was again observed preferentially by the CD25+ subset (Fig. 5C). FIGURE 5. sTCR-γδ tetramer stains a subset of activated human T cells and Treg. PBL were stained with Abs to CD4 and CD8 as well as with sTCR-αβ tetramer-PE or sTCR-γδ tetramer-PE either (A) freshly isolated or (B) 3 d after activation with anti-CD3/CD28 + IL-2. Number inserts indicate the percentages of T cells staining negatively or positively with sTCR-γδ tetramer, as a portion of the total CD4+ or CD8+ subsets, as well as mean fluorescence intensity (MFI) in some cases. Findings are representative of six experiments. (C) Freshly isolated PBL were stained with anti-CD4, anti-CD25 or isotype control, and streptavidin-PE (SA-PE) or sTCR-γδ-PE. Shown are cells gated on CD4 expression. Number inserts indicate MFI of sTCR-γδ-PE staining for CD25+ and CD25− subsets. Findings are representative of two experiments. TCR-γδ ligand expression is partly dependent upon glycolysis The finding that fresh monocytes and T lymphocytes expressed low to negligible levels of sTCR-γδ ligand(s), but upregulated expression following activation, raised the possibility that this might reflect the known induction of glycolysis following activation of T cells, monocytes, or dendritic cells (43, 44) and the resultant synthetic capacity promoted by glycolysis (45). This notion is supported by the fact that ligand-expressing Treg are also highly glycolytic (42). We thus examined this question in two ways. First, we exposed activated T cells to 2-DG, an inhibitor of glycolysis. This reduced expression of both CD25 and sTCR-γδ ligand (Fig. 6A). Second, we distinguished between activated T cells on day 3 based on their expression of CD25, as this identifies cells responsive to IL-2 and are hence most glycolytic (45). As shown in Fig. 6B, CD25+ T cells expressed sTCR-γδ ligand whereas the CD25− subset was devoid of ligand expression. Of further note is that within the CD25+ subset, CD4+ T cells again expressed more ligand than CD8+ T cells (Fig. 6B). We extended this analysis to the ligand-positive tumor 2fTGH and observed that 2-DG also resulted in reduced ligand expression in these cells (Fig. 6C). FIGURE 6. TCR-γδ ligand expression parallels glycolysis. (A and B) PBL were activated with anti-CD3/CD28 + IL-2 in the absence or presence of 2-DG (5 mM). On day 3, cells were stained with Abs to CD4, CD8, CD25, and sTCR-γδ tetramer-PE. Shown in (A) are the levels of CD25 and TCR-γδ ligand without or with 2-DG. Shown in (B) is the expression of TCR-γδ ligand in CD4+ or CD8+ subsets based on surface CD25. (C) 2fTGH cells were cultured for 48 h in either regular medium or medium plus 2-DG (5 mM). Cells were then stained with TCR-αβ or TCR-γδ. Number inserts indicate mean fluorescence intensity (MFI) of sTCR-γδ-PE staining. Findings are representative of three experiments. Discussion To our knowledge, the current findings provide the first unbiased characterization of the spectrum of ligand expression for human synovial Vδ1 γδ T cells. The range of ligand expression may reflect the various locations and seemingly diverse functions attributed to γδ T cells. For example, ligand induction by B. burgdorferi– or LPS-activated monocytes parallels their known ability to activate synovial γδ T cell clones (9, 31). In addition, ligand expression by fresh CD4+ but not CD8+ T cells also correlates with our previous observations that Lyme arthritis synovial γδ T cells suppress by cytolysis the expansion of synovial CD4+ but not CD8+ T cells in response to B. burgdorferi (9). Finally, defining the spectrum of tumor cell types that express TCR-Vδ1 ligands may help explain which tumors contain Vδ1 γδ T cells and impact their effectiveness as immunotherapy. The collective findings are also most consistent with the view that γδ T cells respond to self-proteins as much as or possibly more than foreign proteins. Although these results were obtained using a sTCR-γδ tetramer from a single synovial γδ T cell clone, the fact that it shares a common Vδ1 chain found on most synovial γδ T cells (9), as well as γδ T cells found in intestinal epithelium (1, 10, 21), several tumors (18), and cells expanded in PBL following certain infections such as HIV (46, 47) and CMV (29), suggests the possibility that Vδ1 γδ T cells from these other sources may share a common physiology of ligand expression. Previous studies of ligands for murine and human γδ T cells have come largely from the identification of individual molecules that activate a specific γδ T cell clone (27–30). Although this has been successful in some instances, the current study applied a broader approach of using a sTCR-γδ tetramer in an unbiased fashion to identify the spectrum of ligand expression and how they are regulated. This approach also provided two independent methods by which to identify candidate ligands. One method used RNAseq transcriptome analysis from 22 tumor cell lines to match genes increased in positively staining tumors and decreased in negatively staining tumors. The second approach used the sTCR-γδ tetramer as a bait to bind ligands from lysates of activated monocytes and then identify the bound proteins by mass spectrometry. It is of considerable intertest that among these two sets of candidate ligands were 16 in common, two of which, Annexin A2 and heat shock protein 70, have been previously proposed as ligands for γδ T cells (39–41). By contrast, surface sTCR-γδ tetramer binding was eliminated by treatment with trypsin or removal of GAGs, and also suppressed by inhibition of ER–Golgi transport, suggesting the involvement of a combination of protein and GAGs in tetramer binding. Future studies will explore through knockdown and transfection methods whether any of the candidate ligands we have identified activate the original γδ T cell clone and the extent to which GAG/glycoprotein binding may or may not be a confounder. Although the findings thus far have not determined whether there is one or several synovial Vδ1 TCR-γδ ligands, they do provide a framework for understanding the distribution and regulation of ligand expression, which is critical for better understanding of γδ T cell biology. For example, γδ T cells have been implicated in the defense against a variety of infections (2–7), which is consistent with our finding that different TLR agonists induce TCR-γδ ligand expression on monocytes. Similar studies using a murine sTCR-γδ also found ligands induced with bacterial infection (21). In addition, γδ T cells have been found to generally alleviate various autoimmune models (12–15), which may be consistent with the expression of ligand by a subset of activated CD4+ T cells. The induction of TCR-γδ ligand expression by activation of primary monocytes or T cells, as well as ligand expression by a variety of highly proliferative tumor cell lines, suggested that the metabolic state of cells may influence their ability to express TCR-γδ ligands. Activation of monocytes and T cells is known to induce a metabolic switch to glycolysis to provide the synthetic capacity for proliferation (43, 44). In addition, Treg, which are known to be glycolytic in vivo (42), spontaneously expressed ligand. Moreover, most tumors are highly glycolytic, and the inhibition of glycolysis in these cells also reduced ligand expression. Collectively, these findings suggest that some γδ T cells may function to survey and regulate highly proliferative cells. It is of some interest that the cell lines bearing high levels of TCR-γδ ligand expression were enriched for those of epithelial and fibroblast origin, because Vδ1 γδ T cells are typically found at epithelial barriers, such as skin or intestinal epithelium, as well as in inflamed synovium, which is rich in fibroblasts (48). By contrast, sTCR-γδ ligand expression was noticeably absent from most cell lines of hematopoietic origin. The spectrum of cell line staining with the human synovial sTCR-γδ also bears considerable similarity to previous results using a murine sTCR-γδ, which strongly stained epithelial and fibroblast tumors, and less well tumors of hematopoietic origin (33). These same murine sTCR-γδ also stained macrophages activated by TLR2 or TLR4 stimuli, similar to our findings with monocytes activated by Borrelia or LPS (49). Furthermore, staining of macrophages by the murine sTCR-γδ was also not affected by the absence of β2-microgloublin, suggesting little or no contribution of ligand by classical or nonclassical MHC class I molecules. This agrees with our findings that the human synovial sTCR-γδ tetramer staining was not affected by the presence or absence of CD1 or MICA/B molecules. The findings in this study were made using primary cells and tumor cell lines. Future studies will attempt to extend these results to analyses of sTCR-γδ tetramer histologic staining of primary tissues as well as tumors and inflamed synovium to determine the spectrum of TCR-γδ ligand expression at these sites. Screening primary tumors for binding of sTCR-γδ tetramer may also help identify tumors that may benefit from immunotherapy with Vδ1 γδ T cells. In addition, identifying the ligands in inflamed synovium or intestinal epithelium will provide therapeutic strategies for manipulating the function of infiltrating γδ T cells. Disclosures The authors have no financial conflicts of interest. Acknowledgments We thank Dr. Roxana del Rio-Guerra for technical assistance with flow cytometry, as well as the Harry Hood Bassett Flow Cytometry and Cell Sorting Facility at The University of Vermont Larner College of Medicine. We thank Drs. Mark Davis and Naresha Saligrama for providing the human soluble TCR-αβ. We also thank the Vermont Genetics Network National Institutes of Health IDeA Networks of Biomedical Research Excellence program and the Vermont Center for Immunology and Infectious Diseases National Institutes of Health Centers of Biomedical Research Excellence program for support of the mass spectrometry facility. Footnotes This work was supported by National Institutes of Health Grants AI107298, GM118228, and AI119979 (to R.C.B.), 8P20GM103449 (to B.A.B.), HL107152 (to K.B.), and by Wellcome Trust Grants 098274/Z/12/Z (to S.D.) and 206194 (to G.J.W.). The online version of this article contains supplemental material. Abbreviations used in this article: 2-DG 2-deoxyglucose ER endoplasmic reticulum GAG glycosaminoglycan sTCR-γδ soluble TCR-γδ Treg T regulatory cell. Received April 17, 2019. Accepted August 26, 2019. Copyright © 2019 The Authors This article is distributed under the terms of the CC BY 4.0 Unported license. References ↵Born, W., C. Cady, J. Jones-Carson, A. Mukasa, M. Lahn, R. O’Brien. 1999. Immunoregulatory functions of gamma delta T cells. Adv. Immunol. 71: 77–144.OpenUrlPubMed ↵Shi, C., B. Sahay, J. Q. Russell, K. A. Fortner, N. Hardin, T. J. Sellati, R. C. Budd. 2011. Reduced immune response to Borrelia burgdorferi in the absence of γδ T cells. Infect. Immun. 79: 3940–3946. Hiromatsu, K., Y. Yoshikai, G. Matsuzaki, S. Ohga, K. Muramori, K. Matsumoto, J. A. Bluestone, K. Nomoto. 1992. A protective role of gamma/delta T cells in primary infection with Listeria monocytogenes in mice. J. Exp. Med. 175: 49–56. Rosat, J. P., H. R. MacDonald, J. A. Louis. 1993. A role for gamma delta + T cells during experimental infection of mice with Leishmania major. J. Immunol. 150: 550–555.OpenUrlAbstract Kaufmann, S. H., C. H. Ladel. 1994. Role of T cell subsets in immunity against intracellular bacteria: experimental infections of knock-out mice with Listeria monocytogenes and Mycobacterium bovis BCG. Immunobiology 191: 509–519.OpenUrlCrossRefPubMed Tsuji, M., P. Mombaerts, L. Lefrancois, R. S. Nussenzweig, F. Zavala, S. Tonegawa. 1994. Gamma delta T cells contribute to immunity against the liver stages of malaria in alpha beta T-cell-deficient mice. Proc. Natl. Acad. Sci. USA 91: 345–349. ↵Mixter, P. F., V. Camerini, B. J. Stone, V. L. Miller, M. Kronenberg. 1994. Mouse T lymphocytes that express a gamma delta T-cell antigen receptor contribute to resistance to Salmonella infection in vivo. Infect. Immun. 62: 4618–4621. Brennan, F. M., M. Londei, A. M. Jackson, T. Hercend, M. B. Brenner, R. N. Maini, M. Feldmann. 1988. T cells expressing gamma delta chain receptors in rheumatoid arthritis. J. Autoimmun. 1: 319–326.OpenUrlCrossRefPubMed ↵Vincent, M. S., K. Roessner, D. Lynch, D. Wilson, S. M. Cooper, J. Tschopp, L. H. Sigal, R. C. Budd. 1996. Apoptosis of fashigh CD4+ synovial T cells by Borrelia-reactive fas-ligand(high) gamma delta T cells in lyme arthritis. J. Exp. Med. 184: 2109–2117. ↵Rust, C., Y. Kooy, S. Pena, M. L. Mearin, P. Kluin, F. Koning. 1992. Phenotypical and functional characterization of small intestinal TcR gamma delta + T cells in coeliac disease. Scand. J. Immunol. 35: 459–468.OpenUrlCrossRefPubMed Balbi, B., D. R. Moller, M. Kirby, K. J. Holroyd, R. G. Crystal. 1990. Increased numbers of T lymphocytes with gamma delta-positive antigen receptors in a subgroup of individuals with pulmonary sarcoidosis. J. Clin. Invest. 85: 1353–1361.OpenUrlCrossRefPubMed ↵Peterman, G. M., C. Spencer, A. I. Sperling, J. A. Bluestone. 1993. Role of gamma delta T cells in murine collagen-induced arthritis. J. Immunol. 151: 6546–6558.OpenUrlAbstract Pelegrí, C., P. Kühnlein, E. Buchner, C. B. Schmidt, A. Franch, M. Castell, T. Hünig, F. Emmrich, R. W. Kinne. 1996. Depletion of gamma/delta T cells does not prevent or ameliorate, but rather aggravates, rat adjuvant arthritis. Arthritis Rheum. 39: 204–215.OpenUrlCrossRefPubMed Peng, S. L., M. P. Madaio, A. C. Hayday, J. Craft. 1996. Propagation and regulation of systemic autoimmunity by gamma delta T cells. J. Immunol. 157: 5689–5698.OpenUrlAbstract ↵Mukasa, A., K. Hiromatsu, G. Matsuzaki, R. O’Brien, W. Born, K. Nomoto. 1995. Bacterial infection of the testis leading to autoaggressive immunity triggers apparently opposed responses of alpha beta and gamma delta T cells. J. Immunol. 155: 2047–2056.OpenUrlAbstract Girardi, M., D. E. Oppenheim, C. R. Steele, J. M. Lewis, E. Glusac, R. Filler, P. Hobby, B. Sutton, R. E. Tigelaar, A. C. Hayday. 2001. Regulation of cutaneous malignancy by gammadelta T cells. Science 294: 605–609. ↵Costa, G., S. Loizon, M. Guenot, I. Mocan, F. Halary, G. de Saint-Basile, V. Pitard, J. Déchanet-Merville, J. F. Moreau, M. Troye-Blomberg, et al. 2011. Control of Plasmodium falciparum erythrocytic cycle: γδ T cells target the red blood cell-invasive merozoites. Blood 118: 6952–6962. ↵Gentles, A. J., A. M. Newman, C. L. Liu, S. V. Bratman, W. Feng, D. Kim, V. S. Nair, Y. Xu, A. Khuong, C. D. Hoang, et al. 2015. The prognostic landscape of genes and infiltrating immune cells across human cancers. Nat. Med. 21: 938–945.OpenUrlCrossRefPubMed ↵Wilhelm, M., V. Kunzmann, S. Eckstein, P. Reimer, F. Weissinger, T. Ruediger, H. P. Tony. 2003. Gammadelta T cells for immune therapy of patients with lymphoid malignancies. Blood 102: 200–206. ↵Zeng, X., Y.-L. Wei, J. Huang, E. W. Newell, H. Yu, B. A. Kidd, M. S. Kuhns, R. W. Waters, M. M. Davis, C. T. Weaver, Y. Chien. 2012. Gamma delta T cells recognize a microbial encoded B cell antigen to initiate a rapid antigen-specific interleukin-17 response. Immunity 37: 524–534.OpenUrlCrossRefPubMed ↵Nielsen, M. M., D. A. Witherden, W. L. Havran. 2017. γδ T cells in homeostasis and host defence of epithelial barrier tissues. Nat. Rev. Immunol. 17: 733–745.OpenUrlCrossRef ↵Hirsh, M. I., W. G. Junger. 2008. Roles of heat shock proteins and gamma delta T cells in inflammation. Am. J. Respir. Cell Mol. Biol. 39: 509–513.OpenUrlCrossRefPubMed ↵Morita, C. T., E. M. Beckman, J. F. Bukowski, Y. Tanaka, H. Band, B. R. Bloom, D. E. Golan, M. B. Brenner. 1995. Direct presentation of nonpeptide prenyl pyrophosphate antigens to human gamma delta T cells. Immunity 3: 495–507.OpenUrlCrossRefPubMed Tanaka, Y., C. T. Morita, E. Nieves, M. B. Brenner, B. R. Bloom. 1995. Natural and synthetic non-peptide antigens recognized by human gamma delta T cells. Nature 375: 155–158.OpenUrlCrossRefPubMed ↵Bukowski, J. F., C. T. Morita, M. B. Brenner. 1999. Human gamma delta T cells recognize alkylamines derived from microbes, edible plants, and tea: implications for innate immunity. Immunity 11: 57–65.OpenUrlCrossRefPubMed ↵Witherden, D. A., K. Ramirez, W. L. Havran. 2014. Multiple receptor-ligand interactions direct tissue-resident γδ T cell activation. Front. Immunol. 5: 602.OpenUrlCrossRefPubMed ↵Adams, E. J., Y. H. Chien, K. C. Garcia. 2005. Structure of a gammadelta T cell receptor in complex with the nonclassical MHC T22. Science 308: 227–231. ↵Chien, Y. H., Y. Konigshofer. 2007. Antigen recognition by gammadelta T cells. Immunol. Rev. 215: 46–58.OpenUrlCrossRefPubMed ↵Willcox, C. R., V. Pitard, S. Netzer, L. Couzi, M. Salim, T. Silberzahn, J.-F. Moreau, A. C. Hayday, B. E. Willcox, J. Déchanet-Merville. 2012. Cytomegalovirus and tumor stress surveillance by binding of a human γδ T cell antigen receptor to endothelial protein C receptor. Nat. Immunol. 13: 872–879.OpenUrlCrossRefPubMed ↵Luoma, A. M., C. D. Castro, T. Mayassi, L. A. Bembinster, L. Bai, D. Picard, B. Anderson, L. Scharf, J. E. Kung, L. V. Sibener, et al. 2013. Crystal structure of V1 T cell receptor in complex with CD1d-sulfatide shows MHC-like recognition of a self-lipid by human T cells. Immunity 39: 1032–1042.OpenUrlCrossRefPubMed ↵Vincent, M. S., K. Roessner, T. Sellati, C. D. Huston, L. H. Sigal, S. M. Behar, J. D. Radolf, R. C. Budd. 1998. Lyme arthritis synovial gamma delta T cells respond to Borrelia burgdorferi lipoproteins and lipidated hexapeptides. J. Immunol. 161: 5762–5771. ↵Kappler, J., J. White, H. Kozono, J. Clements, P. Marrack. 1994. Binding of a soluble alpha beta T-cell receptor to superantigen/major histocompatibility complex ligands. Proc. Natl. Acad. Sci. USA 91: 8462–8466. ↵Aydintug, M. K., C. L. Roark, X. Yin, J. M. Wands, W. K. Born, R. L. O’Brien. 2004. Detection of cell surface ligands for the gamma delta TCR using soluble TCRs. J. Immunol. 172: 4167–4175. ↵Esko, J. D., T. E. Stewart, W. H. Taylor. 1985. Animal cell mutants defective in glycosaminoglycan biosynthesis. Proc. Natl. Acad. Sci. USA 82: 3197–3201. ↵‘t Hoen, P. A., Y. Ariyurek, H. H. Thygesen, E. Vreugdenhil, R. H. Vossen, R. X. de Menezes, J. M. Boer, G. J. van Ommen, J. T. den Dunnen. 2008. Deep sequencing-based expression analysis shows major advances in robustness, resolution and inter-lab portability over five microarray platforms. Nucleic Acids Res. 36: e141.OpenUrlCrossRefPubMed ↵Bentley, D. R., S. Balasubramanian, H. P. Swerdlow, G. P. Smith, J. Milton, C. G. Brown, K. P. Hall, D. J. Evers, C. L. Barnes, H. R. Bignell, et al. 2008. Accurate whole human genome sequencing using reversible terminator chemistry. Nature 456: 53–59.OpenUrlCrossRefPubMed ↵Hubbard, T. J., B. L. Aken, S. Ayling, B. Ballester, K. Beal, E. Bragin, S. Brent, Y. Chen, P. Clapham, L. Clarke, et al. 2009. Ensembl 2009. Nucleic Acids Res. 37: D690–D697.OpenUrlCrossRefPubMed ↵Ballif, B. A., Z. Cao, D. Schwartz, K. L. Carraway III., S. P. Gygi. 2006. Identification of 14-3-3epsilon substrates from embryonic murine brain. J. Proteome Res. 5: 2372–2379.OpenUrlCrossRefPubMed ↵Marlin, R., A. Pappalardo, H. Kaminski, C. R. Willcox, V. Pitard, S. Netzer, C. Khairallah, A. M. Lomenech, C. Harly, M. Bonneville, et al. 2017. Sensing of cell stress by human gammadelta TCR-dependent recognition of annexin A2. Proc. Natl. Acad. Sci. USA 114: 3163–3168. Born, W., L. Hall, A. Dallas, J. Boymel, T. Shinnick, D. Young, P. Brennan, R. O’Brien. 1990. Recognition of a peptide antigen by heat shock–reactive gamma delta T lymphocytes. Science 249: 67–69. ↵Chen, H., X. He, Z. Wang, D. Wu, H. Zhang, C. Xu, H. He, L. Cui, D. Ba, W. He. 2008. Identification of human T cell receptor gammadelta-recognized epitopes/proteins via CDR3delta peptide-based immunobiochemical strategy. J. Biol. Chem. 283: 12528–12537. ↵Galgani, M., V. De Rosa, A. La Cava, G. Matarese. 2016. Role of metabolism in the immunobiology of regulatory T cells. J. Immunol. 197: 2567–2575. ↵Kamiński, M. M., S. W. Sauer, M. Kamiński, S. Opp, T. Ruppert, P. Grigaravičius, P. Grudnik, H. J. Gröne, P. H. Krammer, K. Gülow. 2012. T cell activation is driven by an ADP-dependent glucokinase linking enhanced glycolysis with mitochondrial reactive oxygen species generation. Cell Rep. 2: 1300–1315.OpenUrlCrossRefPubMed ↵Everts, B., E. Amiel, S. C. Huang, A. M. Smith, C. H. Chang, W. Y. Lam, V. Redmann, T. C. Freitas, J. Blagih, G. J. van der Windt, et al. 2014. TLR-driven early glycolytic reprogramming via the kinases TBK1-IKKɛ supports the anabolic demands of dendritic cell activation. Nat. Immunol. 15: 323–332.OpenUrlCrossRefPubMed ↵Vander Heiden, M. G., L. C. Cantley, C. B. Thompson. 2009. Understanding the Warburg effect: the metabolic requirements of cell proliferation. Science 324: 1029–1033. ↵Li, Z., Y. Jiao, Y. Hu, L. Cui, D. Chen, H. Wu, J. Zhang, W. He. 2015. Distortion of memory Vδ2 γδ T cells contributes to immune dysfunction in chronic HIV infection. Cell. Mol. Immunol. 12: 604–614.OpenUrl ↵Li, Z., W. Li, N. Li, Y. Jiao, D. Chen, L. Cui, Y. Hu, H. Wu, W. He. 2014. γδ T cells are involved in acute HIV infection and associated with AIDS progression. PLoS One 9: e106064. ↵Firestein, G. S. 2005. Immunologic mechanisms in the pathogenesis of rheumatoid arthritis. J. Clin. Rheumatol. 11(3 Suppl.): S39–S44.OpenUrlCrossRefPubMed ↵Aydintug, M. K., C. L. Roark, J. L. Chain, W. K. Born, R. L. O’Brien. 2008. Macrophages express multiple ligands for gammadelta TCRs. Mol. Immunol. 45: 3253–3263.OpenUrlCrossRefPubMed
No comment yet.
Your new post is loading...
Scooped by Gilbert C FAURE
December 15, 2013 11:27 AM
Scoop.it!

RHUMATOLOGIE - RHEUMATOLOGY

Obviously a topic of interest for so many people::


for patients, it includes aching muscles, tendons, bones and joints..

for MDs and researchers, it covers degenerative diseases as well as arthritis, often associated with various autoimmune diseases (see autoimmunity http://www.scoop.it/t/autoimmunity).


Fortunately, new diagnostic tools are available

https://www.scoop.it/t/rheumatology-rhumatologie?q=diagnosis

and new biotherapies 

https://www.scoop.it/t/rheumatology-rhumatologie?q=therapy

allowed to improve the prognosis and the quality of life of patients


Guess why some topics are much covered than others?

Simply because, they were personal topics of research before, for instance

Synovial membrane

https://www.scoop.it/topic/rheumatology-rhumatologie?q=synovial


Crystal Deposition Diseases

https://www.scoop.it/topic/rheumatology-rhumatologie?q=crystal


Rheumatoid arthritis

https://www.scoop.it/topic/rheumatology-rhumatologie?q=rheumatoid


with various methods

Scanning Electron Microscopy, Immunohistology


Gilbert C FAURE's insight:

September 2026:  > 2300 scoops, >13.9 K views, > 5300 visitors

No comment yet.
Scooped by Gilbert C FAURE
September 24, 4:18 AM
Scoop.it!

Temporal evolution of synovial histopathology in rheumatoid arthritis across treatment periods: a large-scale analysis of 1770 surgical specimens using the Rooney score

Objectives To evaluate temporal changes in rheumatoid arthritis (RA) synovial histopathology across treatment periods using the Rooney score in a surgical cohort. Methods This retrospective study included 1770 synovial specimens from 1150 patients who underwent orthopaedic surgery between 2011 and 2025. Specimens were classified into early biological disease-modifying antirheumatic drug (bDMARD) (2011–2013), established bDMARD (2014–2018) and contemporary targeted therapy (2019–2025) periods. Mixed-effects models included patient-level random intercepts. Sensitivity analyses used calendar year, 3-year intervals, specimen-count-based tertiles and operated-joint power Doppler (PD) grade. Results The median total Rooney scores were 29 (IQR 20–36), 24 (19.25–34) and 23 (20–32) across the periods (p for trend <0.001), driven by lower lymphocytic infiltration. The combined lymphocytic infiltration score decreased from 11 (0–20; early period) to 2 (0–11; contemporary period). After full adjustment, the contemporary period remained associated with a lower Rooney score than the early period (β –1.61, 95% CI –2.74 to –0.48; p=0.005). Tertile analyses were consistent, whereas adding operated-joint PD grade attenuated period estimates. Janus kinase (JAK) inhibitor-treated specimens did not have lower scores than bDMARD-treated specimens without JAK inhibitor exposure. Residual lymphocytic infiltration remained detectable despite clinical or imaging remission. Conclusions RA synovial histopathology evolved across treatment periods, with lower Rooney scores and marked reductions in lymphocytic infiltration. These changes appear to reflect broader contemporary RA management rather than a JAK inhibitor-specific effect, although tissue-level inflammation may persist despite clinical or imaging remission.
No comment yet.
Scooped by Gilbert C FAURE
August 23, 5:43 AM
Scoop.it!

TLR7 in systemic lupus erythematosus: genetics and emerging therapies | Nature Reviews Rheumatology

TLR7 in systemic lupus erythematosus: genetics and emerging therapies | Nature Reviews Rheumatology | Rheumatology-Rhumatologie | Scoop.it
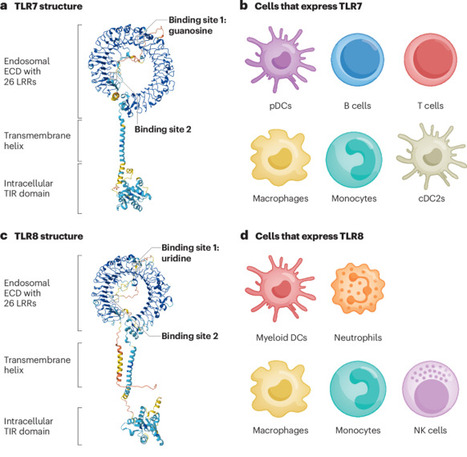
Systemic lupus erythematosus (SLE) is a disease with considerable unmet treatment needs. Endosomal nucleic acid sensing by Toll-like receptor 7 (TLR7) is emerging as a key pathogenic pathway. Gain-of-function mutations in the genes encoding TLR7 and its chaperone UNC93B1 can cause monogenic childhood-onset SLE; rare variants in proteins that regulate ligand availability or downstream signalling proteins also contribute to disease. TLR7 variants can increase the affinity of this receptor for its ligands and can alter binding to endogenous antagonists. Both self RNA–protein complexes and viruses have been implicated in TLR7 activation. Key pathogenic mechanisms include breakdown in B cell tolerance and autoantibody production and type I interferon secretion. Although current therapies such as B cell-depleting chimeric antigen receptor (CAR) T cells and anifrolumab (anti-type I interferon receptor) offer benefit, they are limited by high costs and lack of oral options. In this context, TLR7 has emerged as a promising therapeutic target. Phase II trials of an oral dual TLR7–TLR8 antagonist show durable suppression of the interferon signature in all patients, indicating that TLR7 and TLR8 drive this signature in SLE. This treatment has shown clinical benefit for SLE and cutaneous lupus erythematosus, although the primary endpoint (a dose–response effect) was only met in cutaneous lupus erythematosus. Thus, TLR7–TLR8 antagonists might reshape SLE treatment, alone or in combination with other drugs. Targeting Toll-like receptor 7 (TLR7) represents a promising therapeutic strategy for the treatment of systemic lupus erythematosus (SLE). This Review provides mechanistic insights into the roles of TLR7 and its associated agonistic and antagonistic ligands in SLE and highlights emerging clinical data on therapeutics that target TLR7 for the treatment of SLE.
No comment yet.
Scooped by Gilbert C FAURE
July 15, 8:36 AM
Scoop.it!

Knee Pain? Ragged Cartilage? Research Suggests Surgery’s Not the Best Answer - KFF Health News | George Niles Mekeel

Knee Pain? Ragged Cartilage? Research Suggests Surgery’s Not the Best Answer - KFF Health News | George Niles Mekeel | Rheumatology-Rhumatologie | Scoop.it
"A Finnish study followed patients for 10 years after they had a popular knee surgery. For many, the pain continued or even worsened."
Elisabeth Rosenthal
No comment yet.
Scooped by Gilbert C FAURE
June 28, 7:55 AM
Scoop.it!

Treatment strategies in giant cell arteritis and polymyalgia rheumatica: beyond glucocorticoids | Nature Reviews Rheumatology

Treatment strategies in giant cell arteritis and polymyalgia rheumatica: beyond glucocorticoids | Nature Reviews Rheumatology | Rheumatology-Rhumatologie | Scoop.it
Giant cell arteritis (GCA) and polymyalgia rheumatica (PMR) are closely related chronic inflammatory conditions. Glucocorticoids remain the cornerstone of treatment for both conditions, as they rapidly control inflammation and also reduce the risk of ischaemic complications in GCA. However, glucocorticoid therapy is often prolonged and associated with substantial treatment-related morbidity. In addition, many patients experience relapses during glucocorticoid maintenance therapy and can accrue vascular damage. Advances in understanding the immunopathology of GCA and PMR have led to the development of targeted therapies, particularly agents inhibiting the IL-6 pathway and, more recently, Janus kinase (JAK) signalling. IL-6 receptor inhibitors reduce the risk of disease relapse and allow for reduction in glucocorticoid use in both GCA and PMR, and JAK inhibition enables glucocorticoid sparing and lowers the risk of relapse in GCA. Optimal management of GCA and PMR requires close monitoring, careful assessment of disease activity and treatment-related toxicity, as well as individualized therapeutic strategies. Ongoing research continues to refine treatment algorithms and could help to define therapeutic targets across GCA and PMR. Emerging therapeutic options and evolving treatment algorithms reflect the dynamic and patient-centred nature of advancements in GCA and PMR management. In this Review, the authors provide an overview of current and emerging therapeutic strategies for giant cell arteritis and polymyalgia rheumatica, including glucocorticoids and glucocorticoid-sparing approaches, and also discuss challenges including monitoring disease activity, defining treatment targets and managing relapse.
No comment yet.
Scooped by Gilbert C FAURE
June 21, 2:21 AM
Scoop.it!

Low Back Pain: Epidemiology and Treatment Options | JAMA posted on the topic

Low Back Pain: Epidemiology and Treatment Options | JAMA posted on the topic | Rheumatology-Rhumatologie | Scoop.it
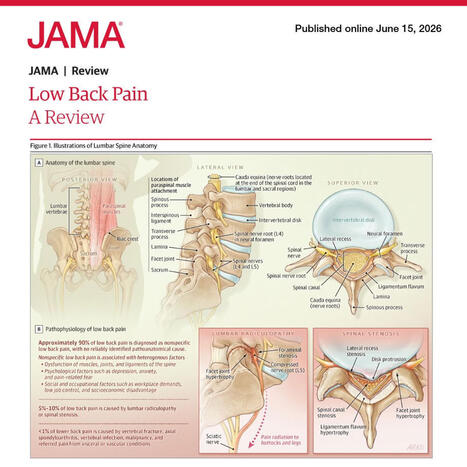
Low back pain is defined as pain located below the costal margin and above the inferior gluteal folds, with or without leg pain and is the leading cause of years lived with #disability worldwide, affecting people of all ages.

Approximately 1 in 4 US workers report low back pain, with mean lifetime prevalence of approximately 40% in adults. Approximately 90% of cases presenting in clinical settings are classified as nonspecific low back pain, with no identified pathoanatomical cause. Initial management emphasizes advice, education, and continued activity.

For acute nonspecific low back pain, first-line therapies include nonpharmacological treatments such as heat application, spinal manipulation, massage, and acupuncture, along with nonsteroidal anti-inflammatory drugs (NSAIDs) and skeletal muscle relaxants.

Chronic nonspecific low back pain is less likely to resolve but is managed with exercise, psychological therapies (such as cognitive behavioral therapy), and multidisciplinary approaches, with NSAIDs considered as second-line therapy.

📝This JAMA Review summarizes the epidemiology, pathophysiology, clinical evaluation, prognosis, and treatment of nonspecific low back pain in the outpatient setting.

https://ja.ma/4oC1znS | 11 comments on LinkedIn
No comment yet.
Scooped by Gilbert C FAURE
April 7, 11:40 AM
Scoop.it!

Fertility, pregnancy and lactation in women with systemic lupus erythematosus | Nature Reviews Rheumatology

This Review examines fertility, pregnancy and lactation in SLE, highlighting the bidirectional effects of pregnancy and disease and summarizing evidence-based approaches to counselling, risk stratification, monitoring and medication safety throughout the reproductive journey.
No comment yet.
Scooped by Gilbert C FAURE
March 29, 3:59 AM
Scoop.it!

For colleagues fond of crystals | Frédéric Lioté

For colleagues fond of crystals | Frédéric Lioté | Rheumatology-Rhumatologie | Scoop.it
For colleagues fond of crystals
No comment yet.
Scooped by Gilbert C FAURE
March 14, 2:14 PM
Scoop.it!

Targeting synovial inflammation in knee osteoarthritis: translational insights for diagnosis and therapy - ScienceDirect

Targeting synovial inflammation in knee osteoarthritis: translational insights for diagnosis and therapy - ScienceDirect | Rheumatology-Rhumatologie | Scoop.it
Synovial inflammation is a central feature of knee osteoarthritis (OA), linking systemic and local pathogenic pathways with clinical outcomes. This re…
No comment yet.
Scooped by Gilbert C FAURE
February 27, 4:06 AM
Scoop.it!

Researchers at Stanford University School of Medicine have made an exciting discovery that could change how we treat joint pain. - WHAT is the drug called ?? They found that by blocking a specific...

Researchers at Stanford University School of Medicine have made an exciting discovery that could change how we treat joint pain. - WHAT is the drug called ?? They found that by blocking a specific... | Rheumatology-Rhumatologie | Scoop.it
Researchers at Stanford University School of Medicine have made an exciting discovery that could change how we treat joint pain. - WHAT is the drug called ??

They found that by blocking a specific protein related to aging, called 15-PGDH, they can actually regrow knee cartilage and prevent osteoarthritis.

What makes this treatment special is that it does not use stem cells. Instead, it works by "reprogramming" the cartilage cells already in your body to act young again.

This is a major breakthrough because it treats the actual cause of the disease rather than just dulling the pain.

The best news is that this medicine might come in the form of a simple pill.

A version of this drug has already passed early safety tests in humans for treating muscle weakness.

Scientists hope that this new approach will eventually mean people no longer need to have difficult joint replacement surgeries.

This could help millions of people stay active and move without pain as they get older.

ANYONE got more on this …..? | 25 comments on LinkedIn
No comment yet.
Scooped by Gilbert C FAURE
February 10, 4:14 AM
Scoop.it!

Intervertebral disc degeneration | Nature Reviews Disease Primers

Intervertebral disc degeneration | Nature Reviews Disease Primers | Rheumatology-Rhumatologie | Scoop.it
Intervertebral disc (IVD) degeneration is a naturally occurring process that is a consequence of biological ageing and exposure to normal physiological loading over a lifetime and is characterized by loss of IVD tissue structural integrity. The nucleus pulposus changes with loss of pressurization, decreased collagen concentration and loss of distinction from annulus fibrosus. The annulus fibrosus and cartilaginous endplate suffer delamination, tears, fractures and clefts of their respective extracellular matrix at both microscopic and macroscopic scales. This loss of structural integrity generally follows a predictable pattern of degeneration, and it predisposes the IVD to pathological states. As the disc degenerates, the likelihood of functional failure to protect the neural elements and/or to provide stable spine motion and support increases. Functional failure takes the degenerated IVD to a state of disc pathology that has various phenotypes: the most common forms are disc herniation, mechanical instability, spinal stenosis, degenerative spondylolisthesis and degenerative scoliosis. IVD pathology is commonly self-limited and non-operative treatment remains the mainstay of treatment in most patients. For patients with refractory disease, surgical intervention focuses on neural decompression and, when indicated, motion segment stabilization. Future therapies for prevention of disc degeneration, targeted disc regeneration and biological modification of the degenerative cascade might prevent or reverse pathological changes across all spinal regions. Intervertebral disc degeneration is a natural consequence of ageing and involves a loss of tissue structural integrity, which can lead to various pathological states. In this Primer, Hammoor et al. review the epidemiology, pathophysiology, diagnosis and treatment of the various pathologies. They also discuss the effects of disc pathology on patient quality of life and highlight emerging and future therapies to improve outcomes.
No comment yet.
Scooped by Gilbert C FAURE
January 4, 3:53 AM
Scoop.it!

Mechanisms of osteoclast activation in inflammatory bone loss in rheumatoid arthritis | Nature Reviews Rheumatology

Mechanisms of osteoclast activation in inflammatory bone loss in rheumatoid arthritis | Nature Reviews Rheumatology | Rheumatology-Rhumatologie | Scoop.it
Rheumatoid arthritis is an autoimmune disease that affects ~1% of the global population and leads to joint inflammation, local bone erosions and systemic bone loss. The disability and immobility caused by inflammatory bone loss, joint destruction and fractures in rheumatoid arthritis present a clinical challenge and impose a considerable socioeconomical burden. Osteoclasts have the unique ability to resorb bone and cause bone loss. A comprehensive understanding of the regulatory mechanisms of osteoclasts and their crosstalk with stromal cells, such as osteoblasts, or immune cells during inflammation is essential for the development of targeted therapies to prevent and treat bone loss. The objective of this Review is to present a comprehensive overview of the current knowledge of osteoclast regulation at different levels: from systemic pathways to changes in the bone microenvironment, including the involvement of local cells, to osteoclast-intrinsic regulation such as metabolic adaptations. We also discuss some of the current and emerging therapies that can counteract inflammatory bone loss. The factors and mechanisms that regulate osteoclast-induced inflammatory bone loss are complex. The authors of this Review provide an overview of osteoclast regulation in the context of inflammatory bone loss and rheumatoid arthritis and provide insights into potential treatment strategies.
No comment yet.
Scooped by Gilbert C FAURE
December 9, 2025 6:18 AM
Scoop.it!

Emerging and underrecognized viral triggers of autoimmune inflammatory rheumatic disease flares | Nature Reviews Rheumatology

Emerging and underrecognized viral triggers of autoimmune inflammatory rheumatic disease flares | Nature Reviews Rheumatology | Rheumatology-Rhumatologie | Scoop.it
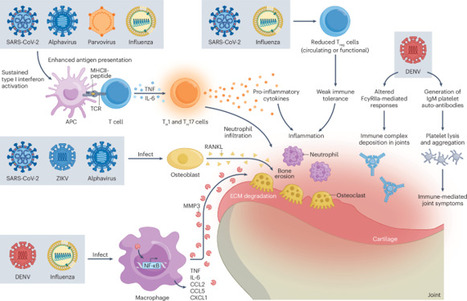
In this Review, the authors summarize the potential role of emerging viruses in autoimmune rheumatic diseases (AIRDs). They describe the association between viruses and AIRD flare ups, the putative mechanisms linking AIRD to viral infections and hormone modulation of viral pathogenesis and...
No comment yet.
Scooped by Gilbert C FAURE
September 27, 4:59 AM
Scoop.it!

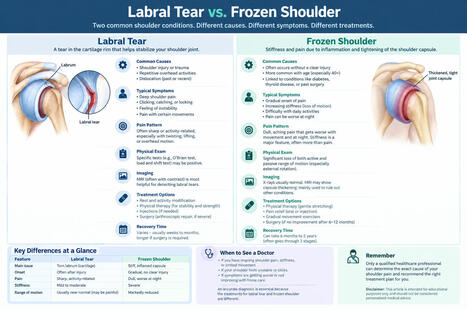
Labral Tear vs Frozen Shoulder: Key Differences, Symptoms, Causes & Treatment

Labral Tear vs Frozen Shoulder: Key Differences, Symptoms, Causes & Treatment | Rheumatology-Rhumatologie | Scoop.it
A labral tear and frozen shoulder can both cause shoulder pain, stiffness, and difficulty using the arm, but they are different problems.For example, you may...
No comment yet.
Scooped by Gilbert C FAURE
August 25, 8:11 AM
Scoop.it!

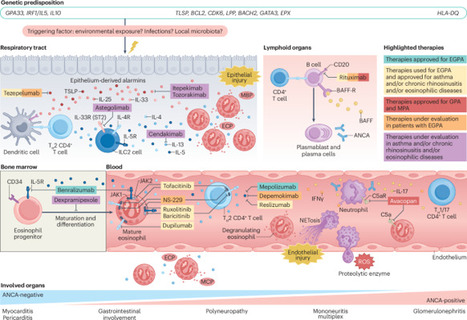
Advances in the treatment of eosinophilic granulomatosis with polyangiitis - Nature Reviews Rheumatology | Benjamin Terrier

Advances in the treatment of eosinophilic granulomatosis with polyangiitis - Nature Reviews Rheumatology | Benjamin Terrier | Rheumatology-Rhumatologie | Scoop.it
New review on advances in the treatment of EGPA in Nature Reviews Rhematology
Congratulations to Adrien Cottu and all the international colleagues
No comment yet.
Scooped by Gilbert C FAURE
August 9, 3:23 AM
Scoop.it!

Diagnostic, prognostic and therapeutic biomarkers in rheumatoid arthritis | Nature Reviews Rheumatology

Diagnostic, prognostic and therapeutic biomarkers in rheumatoid arthritis | Nature Reviews Rheumatology | Rheumatology-Rhumatologie | Scoop.it
Outcomes in rheumatoid arthritis (RA) have improved considerably with the advent of new therapeutic modalities, improved therapeutic strategies and greater recognition of the need to manage comorbidities. Nevertheless, unmet needs remain. Sustained remission is achieved by only a minority of patients, in part owing to delays in diagnosis, imprecise risk stratification and suboptimal treatment selection. A pressing need therefore exists for robust diagnostic and prognostic tools to support clinical decision making. Advances in genetic, protein, imaging and multi-omics biomarkers offer opportunities to refine RA diagnosis, predict disease course and guide therapeutic choices. Parallel progress in biomarker discovery is also shaping understanding of major RA-associated comorbidities, including cardiovascular disease, interstitial lung disease, osteoporosis and malignancy. Together, clinical introduction of such biomarkers could enable earlier intervention, more precise therapy and improved outcomes for patients with RA. This Review examines emerging laboratory, imaging and multi-omics biomarkers in rheumatoid arthritis, highlighting roles in diagnosis, prognosis, treatment selection and comorbidity management, and emphasizing challenges and opportunities for translating biomarker advances into routine clinical practice and improved patient outcomes.
No comment yet.
Scooped by Gilbert C FAURE
July 1, 7:23 AM
Scoop.it!

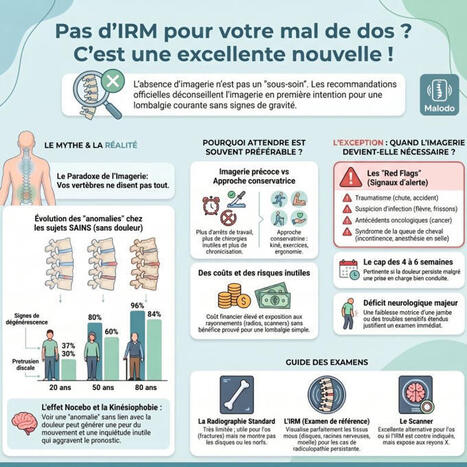
« Mon médecin n'a pas voulu me prescrire d'IRM. C'est normal ? » Phrase entendue régulièrement, et qui révèle un décalage massif entre la croyance populaire (« plus on en sait, mieux c'est ») et…...

« Mon médecin n'a pas voulu me prescrire d'IRM. C'est normal ? » Phrase entendue régulièrement, et qui révèle un décalage massif entre la croyance populaire (« plus on en sait, mieux c'est ») et…... | Rheumatology-Rhumatologie | Scoop.it
« Mon médecin n'a pas voulu me prescrire d'IRM. C'est normal ? »


Phrase entendue régulièrement, et qui révèle un décalage massif entre la croyance populaire (« plus on en sait, mieux c'est ») et les recommandations cliniques actuelles sur l'imagerie en lombalgie.

Position des sociétés savantes (HAS, NICE, Choosing Wisely) : ne pas prescrire d'imagerie en première intention pour une lombalgie commune sans red flags.

Pourquoi cette position contre-intuitive ?
➡️ Les anomalies dégénératives sont fréquentes chez les sujets asymptomatiques (Brinjikji et al. 2015 : 30% de protrusions discales chez les 30 ans asymptomatiques, 84% chez les 80 ans, hernies, arthrose facettaire, etc.)
🛫 Voir des « anomalies » sur une imagerie ne signifie pas qu'elles expliquent les symptômes
🤡 L'imagerie précoce est associée paradoxalement à plus de chronicisation, plus d'arrêts de travail prolongés, plus de chirurgies, sans bénéfice clinique
😱 Les patients informés d'« anomalies » développent plus facilement la kinésiophobie et le catastrophisme
💲 Coût et exposition aux rayonnements (pour les radio/scanner) sans bénéfice prouvé en première intention

Indications validées de l'imagerie en lombalgie :
📛 Présence de red flags (suspicion d'urgence, pathologie spécifique)
📛 Lombalgie persistante au-delà de 4-6 semaines malgré prise en charge bien conduite
❌ Suspicion clinique précise (radiculopathie avec déficit, suspicion inflammatoire, antécédents oncologiques)
❌ Échec de la prise en charge conservatrice avec discussion d'une intervention

*️⃣ Hiérarchie des examens :
✔️ Radio standard : très limitée en lombalgie (montre os mais peu utile dans la plupart des situations)
✔️ IRM : examen de référence pour évaluation des structures (disque, racines, moelle, ligaments)
✔️ Scanner : utile pour la pathologie osseuse précise, examen radiculaire si IRM contre-indiquée
✔️ Scintigraphie, EMG : indications très spécifiques

L'éducation du patient sur ce sujet est cruciale. 🧠
Beaucoup arrivent en consultation persuadés qu'« il faut bien voir ».

Expliquer que l'absence d'imagerie n'est pas un sous-soin mais conforme aux recommandations, c'est un travail pédagogique récurrent. 🖖

Les délais sont tellement rallongés pour les prises de rdv bilan initial chez le kiné parce qu'il faut "attendre d'avoir l'IRM" sans raison particulière... que de temps perdu chez vous aussi? 😐
No comment yet.
Scooped by Gilbert C FAURE
June 21, 9:46 AM
Scoop.it!

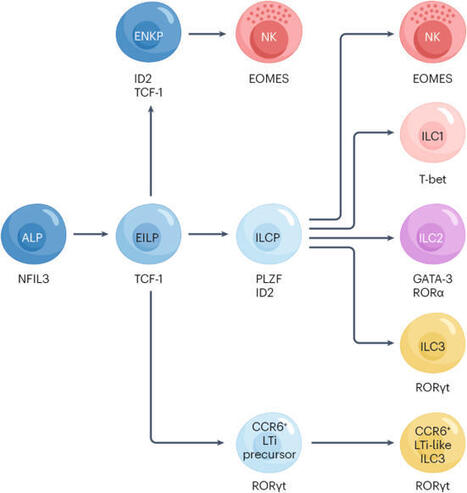
Innate lymphoid cells in rheumatoid arthritis as mediators of pathology and resolution | Nature Reviews Rheumatology

Innate lymphoid cells in rheumatoid arthritis as mediators of pathology and resolution | Nature Reviews Rheumatology | Rheumatology-Rhumatologie | Scoop.it
Innate lymphoid cells (ILCs) are emerging as critical modulators of inflammation in rheumatoid arthritis, contributing to both disease pathology and resolution. Group 3 ILCs (ILC3s) mirror TH17 cells in their production of IL-17A and IL-22, promoting fibroblast activation, neutrophil recruitment and synovial inflammatory cascades. By contrast, group 2 ILCs (ILC2s) engage reparative and immunoregulatory pathways via secretion of IL-9, IL-13 and IL-10. Lymphoid tissue inducer (LTi) ILCs contribute to ectopic lymphoid tissue neogenesis and stromal remodelling in early disease. Clinically, alterations in ILC subset composition correlate with disease activity, therapeutic responsiveness and inflammatory burden. Advances in high-dimensional immunophenotyping, spatial transcriptomics and single-cell multi-omics now enable precise mapping of ILC subsets and their effector programmes across peripheral blood and synovial tissue, supporting their use in biomarker discovery and treatment pipelines. Furthermore, modulation of ILCs by targeting upstream cytokines, signalling pathways or the use of microbiota-derived metabolites is a potential therapeutic strategy. Finally, cell-based avenues include IL-10-producing ILC2s (ILC210) and engineered chimeric antigen receptor (CAR)-ILC2s for targeted, tissue-resident immune modulation. Although still in the preclinical stages, these approaches highlight the translational potential of ILCs as biomarkers and therapeutic targets in rheumatoid arthritis. Innate lymphoid cells (ILCs) influence rheumatoid arthritis by amplifying inflammatory circuits through ILC3 activity and promoting immune regulation via ILC2 responses. These context-dependent functions position ILC subsets as emerging biomarkers and targets for innovative therapies.
No comment yet.
Scooped by Gilbert C FAURE
June 11, 9:58 AM
Scoop.it!

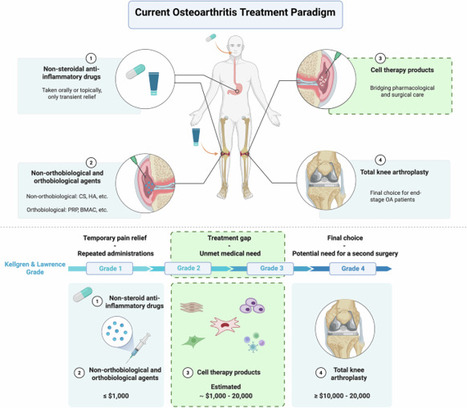
Next-generation therapies for osteoarthritis: the evolving role of cell therapy products | Experimental & Molecular Medicine

Next-generation therapies for osteoarthritis: the evolving role of cell therapy products | Experimental & Molecular Medicine | Rheumatology-Rhumatologie | Scoop.it
Osteoarthritis (OA) remains a major cause of disability worldwide; however, current non-surgical treatments offer transient symptom relief without altering disease course. This leaves a therapeutic gap for patients with early-to-moderate disease who are not candidates for surgery but continue to experience pain and functional limitation. Intra-articular interventions such as non-steroidal anti-inflammatory drugs, hyaluronic acid, and platelet-rich plasma may ease symptoms, but do not modify disease progression. By contrast, cell therapy products hold promise as regenerative approaches that may both alleviate pain and influence disease trajectory. Cell therapy products for knee OA exert multimodal effects through paracrine and immunomodulatory mechanisms, including modulation of synovial inflammation, attenuation of senescence-associated pathways, and support of extracellular matrix production. Despite encouraging preclinical and clinical signals, only a few cell therapy products have been approved globally, and most remain in development. However, substantial translational challenges remain, including variability in cell source and potency, limited persistence in joint environment, small clinical trial sizes, and regulatory and manufacturing hurdles. To achieve broader adoption, it will be essential to demonstrate superiority to minimally manipulated orthobiologics, clarify redosing strategies, and generate robust long-term evidence. This Review discusses recent clinical trial data, mechanistic insights, regulatory considerations, and operational challenges shaping the evolving role of cell therapy products for OA as next-generation candidates to bridge the gap between pharmacological and surgical interventions. In addition, this Review is written to support regulatory agencies as well as academics and clinicians involved in the development and evaluation of cell therapy products. Osteoarthritis is a leading cause of pain and disability, affecting more than 600 million adults globally, with its prevalence rising due to aging and obesity. This Review explores the potential of cell-based orthobiological regenerative therapies, particularly mesenchymal stem cells (MSCs), which may provide durable benefits by modulating inflammation and supporting endogenous tissue repair. MSCs, despite rapid clearance from the knee joint, exhibit multifactorial mechanisms, including immunomodulation and chondroprotection, which could offer broader therapeutic effects than currently available treatments. However, clinical evidence for their superiority remains limited, highlighting the need for further mechanistic studies and stratified clinical trials. This Review emphasizes the importance of developing standardized manufacturing processes and regulatory frameworks to advance these therapies. Future directions include exploring cell-free approaches and enhancing MSC durability in the osteoarthritis environment, aiming for long-term clinical benefits and potential disease modification. This summary was initially drafted using artificial intelligence, then revised and fact-checked by the author.
No comment yet.
Scooped by Gilbert C FAURE
April 6, 11:34 AM
Scoop.it!

#drugoftheweek #pharmacology #nsaids #drugsafety #toxicology | Abu Medinat

#drugoftheweek #pharmacology #nsaids #drugsafety #toxicology | Abu Medinat | Rheumatology-Rhumatologie | Scoop.it
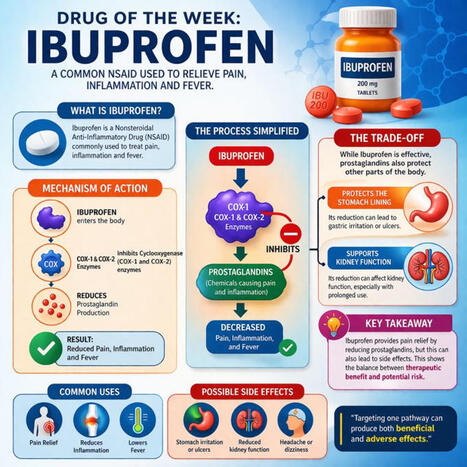
💊 Drug of the Week: Ibuprofen

Ibuprofen is one of the most widely used nonsteroidal anti-inflammatory drugs (NSAIDs) — commonly taken for pain, inflammation, and fever.

But what makes it effective?

🔬 Mechanism of action:
Ibuprofen inhibits cyclooxygenase (COX-1 and COX-2) enzymes → reducing the production of prostaglandins

🧠 Why this matters:
Prostaglandins are responsible for pain, inflammation, and fever
So reducing them leads to symptom relief

⚠️ The trade-off:
Prostaglandins also play protective roles in the body

📌 Their inhibition can lead to:

- Gastric irritation or ulcers (reduced stomach protection)
- Altered kidney function (especially with prolonged use)

This highlights a key concept in Pharmacology and Toxicology:
👉 Targeting one pathway can produce both beneficial and adverse effects

It’s a reminder that even commonly used drugs require careful consideration of dose and duration.

#DrugOfTheWeek #Pharmacology #NSAIDs #DrugSafety #Toxicology
No comment yet.
Scooped by Gilbert C FAURE
March 18, 5:07 AM
Scoop.it!

DOULEUR et gêne pour MARCHER, notre rhumatologue nous dit quand opérer (+ce qui fonctionne vraiment) | Sergyl Lafont

DOULEUR et gêne pour MARCHER, notre rhumatologue nous dit quand opérer (+ce qui fonctionne vraiment) | Sergyl Lafont | Rheumatology-Rhumatologie | Scoop.it
🤔 DOULEUR et gêne pour MARCHER, notre rhumatologue nous dit quand opérer (+ce qui fonctionne vraiment)
interview par le Professeur Boris Hansel
https://lnkd.in/dur6JWFp
14 mars 2026
👉 RETROUVER UNE VIE NORMALE malgré l'arthrose de la hanche, c'est l'objectif de la prothèse totale de hanche, l'une des interventions les plus réussies de la chirurgie moderne. Des alternatives existent, selon ce qu'on peut lire un peu partout sur les réseaux sociaux.
Dans cette émission PUMS, on décrypte les contradictions que l'on trouve sur Internet concernant l'opération de la hanche. Pourquoi certains sont-ils ravis et d'autres déçus ? Quand le cartilage disparaît et que le "pincement" articulaire devient insupportable, quelles sont les étapes avant d'envisager le bloc opératoire ?
Avec le Pr francis berenbaum, #rhumatologue et expert mondial de l'arthrose, on explique les mécanismes de la douleur, du pli de l'aine jusqu'à la cuisse. On fait le point sur les traitements médicaux : comment utiliser intelligemment les anti-inflammatoires ? Les infiltrations sont-elles vraiment dangereuses pour le cartilage ou est-ce une idée reçue ?
Découvrez l'indice de Lequesne, cet outil pratique qui permet d'évaluer votre #handicap réel et de savoir si c'est le bon moment pour sauter le pas. Nous abordons aussi la question de la "prothèse oubliée", de la rééducation (souvent plus simple qu'on ne le pense) et de la reprise du sport. Peut-on encore skier ou courir avec une hanche artificielle ?
🎥 Pour découvrir toutes nos vidéos, abonnez-vous : @PUMS
https://lnkd.in/dEqqr5_P
Une vidéo indispensable pour tous ceux qui souffrent de la hanche, pour comprendre le rapport bénéfice/risque de la chirurgie et reprendre le contrôle sur sa mobilité.
PUMS (Pour une meilleure santé)

#arthrose #hanche #prothesedehanche
No comment yet.
Scooped by Gilbert C FAURE
March 11, 9:07 AM
Scoop.it!

Un grand merci maxime dougados pour ce très bel hommage au Pr Bernard Amor. Un grand Monsieur effectivement qui a été à mes côtés dans mes débuts professionnels et un ami de 30 ans avec Magali, son...

Un grand merci maxime dougados pour ce très bel hommage au Pr Bernard Amor. Un grand Monsieur effectivement qui a été à mes côtés dans mes débuts professionnels et un ami de 30 ans avec Magali, son... | Rheumatology-Rhumatologie | Scoop.it
Un grand merci maxime dougados pour ce très bel hommage au Pr Bernard Amor.
Un grand Monsieur effectivement qui a été à mes côtés dans mes débuts professionnels et un ami de 30 ans avec Magali, son épouse.
Qu'il était beau notre premier voyage tous les trois à Montréal en 1995 ! Que de bons souvenirs.
Aujourd'hui, tu dois avoir aménager un box de consultation au paradis pour soigner les anges...
Bernard, tu me manques, tu nous manques.
No comment yet.
Scooped by Gilbert C FAURE
February 22, 4:10 AM
Scoop.it!

Soigner naturellement l'arthrose ? + le "jus des cartilages"

🌱 14 Février 2024 : Découvrez la nouvelle plateforme RGNR.TV (https://www.rgnr.tv/ ) où vous retrouverez les nouvelles vidéos de Thierry sans aucune censure mais aussi de nombreuses autres contributions sur les sujets de la santé, l'autonomie, la liberté.

🌱 Inscrivez vous aux formules d'abonnement RGNR + ou RGNR Premium pour découvrir un potentiel nouveau pour votre santé: https://www.rgnr.tv/compte-dadherent/niveaux-dadhesion/

🌱 FIL TELEGRAM
Écoutez les podcasts gratuits de Thierry et les actualités non-censurées
https://t.me/rgnr_fr

🌱 X (Twitter): actualités, coups de gueule et polémiques
https://twitter.com/thierrycas

🌱 FACEBOOK
La page officielle Facebook avec les actualités
https://www.facebook.com/thierry.rgnr

🌱 INSTAGRAM
Le compte Instagram officiel en cours d’élaboration
https://www.instagram.com/rgnr_regeneration/


_________

LES CODES PROMO DES PARTENAIRES

▶ 10 % de réduction sur toute la boutique WARMCOOK (Kuvings) :
Rendez-vous sur : http://rgnr.li/warmcook avec le code : REGENERE10

▶ 10 % de réduction sur une sélection de produits de la boutique VIDYA :
Rendez-vous sur : http://rgnr.li/vidya avec le code : REGENERE10

▶ 10 % de réduction sur les extracteurs de la marque SANA :
Rendez-vous sur http://rgnr.li/lechoubrave avec le code : REGENERE10

▶ 30 jours gratuit sur l’application de méditation et de bien-être ENVOL :
Rendez-vous sur https://www.envol.app/code avec le code : REGENERE
Gilbert C FAURE's insight:

acide

No comment yet.
Scooped by Gilbert C FAURE
January 28, 5:52 AM
Scoop.it!

Livre-Blanc-Rhumatologie-2025.pdf | Frédéric Lioté

Livre-Blanc-Rhumatologie-2025.pdf | Frédéric Lioté | Rheumatology-Rhumatologie | Scoop.it
Le Livre blanc de la rhumatologue en France est disponible ! Important pour les tutelles et autres décideurs.
Notre Ministre de la santé et rhumatologue, la Dre Stephanie RIST saura apprécier.
No comment yet.
Scooped by Gilbert C FAURE
December 15, 2025 6:14 AM
Scoop.it!

Advances in the pathophysiology, diagnosis and treatment of Takayasu arteritis | Nature Reviews Rheumatology

Takayasu arteritis (TAK) is a rare, chronic, large-vessel vasculitis that primarily targets the aorta and its major branches, leading to vascular stenosis, occlusion and aneurysm formation. TAK, which is characterized by granulomatous inflammation of the arterial wall, predominantly affects women, with peak onset typically occurring between 20 and 40 years of age. The disease exhibits substantial geographic variability in prevalence, with emerging evidence suggesting that these differences are partly owing to variations in genetic susceptibility loci, particularly within immune-related genes; however, the role of environmental factors in the disease aetiology remains poorly understood. Non-invasive imaging techniques have become central to both diagnosis and disease monitoring. Furthermore, the development of biomarkers holds promise for more accurate assessment of disease activity. The management of TAK is evolving, driven by an improved understanding of disease pathogenesis. The growing use of biologic agents is providing new treatment options, particularly for patients with refractory or relapsing disease. By integrating these developments, this Review is aimed at serving as a comprehensive resource for clinicians and researchers dedicated to improving the understanding and management of TAK. This Review article provides an update on the pathophysiology, diagnosis and treatment of Takayasu arteritis. The authors emphasize the need for a multidisciplinary approach to the diagnosis and management of this complex disease.
No comment yet.
Scooped by Gilbert C FAURE
December 9, 2025 4:01 AM
Scoop.it!

Emerging AI- and Biomarker-Driven Precision Medicine in Autoimmune Rheumatic Diseases: From Diagnostics to Therapeutic Decision-Making | Rheumato MDPI

Emerging AI- and Biomarker-Driven Precision Medicine in Autoimmune Rheumatic Diseases: From Diagnostics to Therapeutic Decision-Making | Rheumato MDPI | Rheumatology-Rhumatologie | Scoop.it
🔥Don't miss this #FeaturePaper by Moawiah Naffaa, PhD and Ola A. Al-Ewaidat.

Emerging AI- and Biomarker-Driven Precision Medicine in Autoimmune Rheumatic Diseases: From Diagnostics to Therapeutic Decision-Making


🔗More details: https://brnw.ch/21wY2dx


#OpenAccess #AutoimmuneRheumaticDiseases #ArtificialIntelligence #Biomarkers #DigitalHealth
No comment yet.