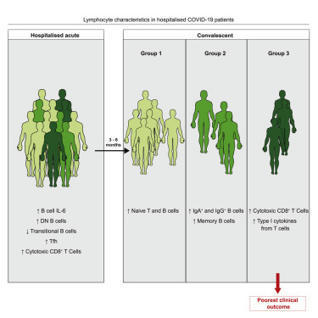

Emerging studies indicate that some coronavirus disease 2019 (COVID-19) patients suffer from persistent symptoms, including breathlessness and chronic…

 Your new post is loading...
 Scoop.it! Emerging studies indicate that some coronavirus disease 2019 (COVID-19) patients suffer from persistent symptoms, including breathlessness and chronic… 
No comment yet.
Sign up to comment
Scoop.it!

Since the initial reports of a cluster of pneumonia cases of unidentified origin in Wuhan, China, in December 2019, the novel coronavirus that causes this disease — severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) — has spread throughout the world, igniting the twenty-first century’s deadliest pandemic. Over the past 12 months, a dizzying array of information has emerged from numerous laboratories, covering everything from the putative origin of SARS-CoV-2 to the development of numerous candidate vaccines. Many immunologists quickly pivoted from their existing research to focus on coronavirus disease 2019 (COVID-19) and, owing to this unprecedented convergence of efforts on one viral infection, a remarkable body of work has been produced and disseminated, through both preprint servers and peer-reviewed journals. Here, we take readers through the timeline of key discoveries during the first year of the pandemic, which showcases the extraordinary leaps in our understanding of the immune response to SARS-CoV-2 and highlights gaps in our knowledge as well as areas for future investigations. A timeline of the major scientific discoveries during the first year of the COVID-19 pandemic showcases the collaborative efforts that enabled the key aspects of the immune response to SARS-CoV-2 to be reported at unprecedented speed.
Scoop.it!
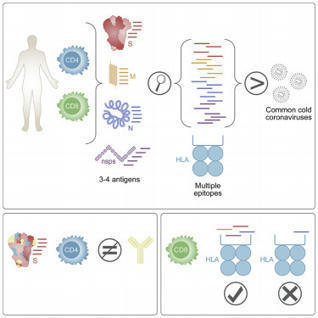
Tarke et al. shows a broad T cell repertoire suggesting that viral escape of T-cell
Scoop.it!
In an exciting, state-of-the-art study currently available on the medRxiv* preprint server, US researchers created a multi-coronavirus protein microarray containing full-length proteins, peptide libraries, and overlapping protein fragments from the severe acute respiratory syndrome coronavirus 2...
Scoop.it!
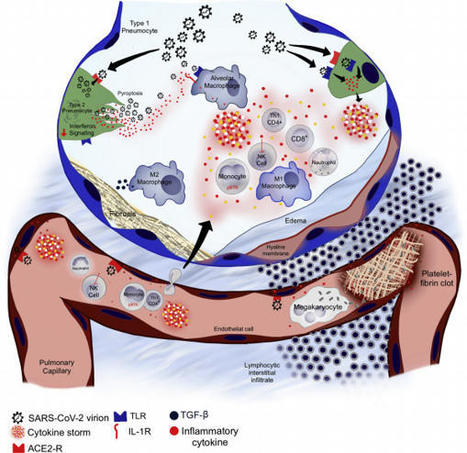
The rapid spread of coronavirus disease 2019 (COVID-19), caused by severe acute respiratory
Scoop.it!
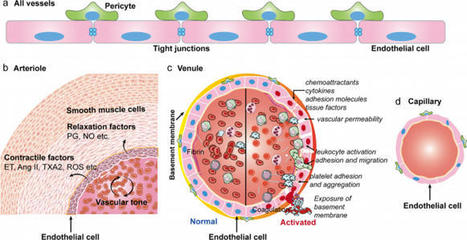
On 12 March 2020, the outbreak of coronavirus disease 2019 (COVID-19) was declared a pandemic by the World Health Organization. As of 4 August 2020, more than 18 million confirmed infections had been reported globally. Most patients have mild symptoms, but some patients develop respiratory failure which is the leading cause of death among COVID-19 patients. Endothelial cells with high levels of angiotensin-converting enzyme 2 expression are major participants and regulators of inflammatory reactions and coagulation. Accumulating evidence suggests that endothelial activation and dysfunction participate in COVID-19 pathogenesis by altering the integrity of vessel barrier, promoting pro-coagulative state, inducing endothelial inflammation, and even mediating leukocyte infiltration. This review describes the proposed cellular and molecular mechanisms of endothelial activation and dysfunction during COVID-19 emphasizing the principal mediators and therapeutic implications.
Scoop.it!
Home/Newsroom/Q&A Detail/Coronavirus disease (COVID-19): Herd immunity, lockdowns and COVID-19 Coronavirus disease (COVID-19): Herd immunity, lockdowns and COVID-19 15 October 2020 | Q&A What is ‘herd immunity’? ‘Herd immunity’, also known as ‘population immunity’, is a concept used for vaccination, in which a population can be protected from a certain virus if a threshold of vaccination is reached. Herd immunity is achieved by protecting people from a virus, not by exposing them to it. Vaccines train our immune systems to create proteins that fight disease, known as ‘antibodies’, just as would happen when we are exposed to a disease but – crucially – vaccines work without making us sick. Vaccinated people are protected from getting the disease in question and passing it on, breaking any chains of transmission. Visit our webpage on COVID-19 and vaccines for more detail. With herd immunity, the vast majority of a population are vaccinated, lowering the overall amount of virus able to spread in the whole population. As a result, not every single person needs to be vaccinated to be protected, which helps ensure vulnerable groups who cannot get vaccinated are kept safe. The percentage of people who need to have antibodies in order to achieve herd immunity against a particular disease varies with each disease. For example, herd immunity against measles requires about 95% of a population to be vaccinated. The remaining 5% will be protected by the fact that measles will not spread among those who are vaccinated. For polio, the threshold is about 80%. Achieving herd immunity with safe and effective vaccines makes diseases rarer and saves lives. Find out more about the science behind herd immunity by watching or reading this interview with WHO’s Chief Scientist, Dr Soumya Swaminathan. Attempts to reach ‘herd immunity’ through exposing people to a virus are scientifically problematic and unethical. Letting COVID-19 spread through populations, of any age or health status will lead to unnecessary infections, suffering and death. The vast majority of people in most countries remain susceptible to this virus. Seroprevalence surveys suggest that in most countries, less than 10% of the population have been infected with COVID-19. We are still learning about immunity to COVID-19. Most people who are infected with COVID-19 develop an immune response within the first few weeks, but we don’t know how strong or lasting that immune response is, or how it differs for different people. There have also been reports of people infected with COVID-19 for a second time. Until we better understand COVID-19 immunity, it will not be possible to know how much of a population is immune and how long that immunity last for, let alone make future predictions. These challenges should preclude any plans that try to increase immunity within a population by allowing people to get infected. Although older people and those with underlying conditions are most at risk of severe disease and death, they are not the only ones at risk. Finally, while most infected people get mild or moderate forms of COVID-19 and some experience no disease, many become seriously ill and must be admitted into hospital. We are only beginning to understand the long-term health impacts among people who have had COVID-19, including what is being described as ‘Long COVID.’ WHO is working with clinicians and patient groups to better understand the long term effects of COVID-19. Read the Director-General’s opening remarks at the 12 October COVID-19 briefing for a summary of WHO’s position. Most people who are infected with COVID-19 develop an immune response within the first few weeks after infection. Research is still ongoing into how strong that protection is and how long it lasts. WHO is also looking into whether the strength and length of immune response depends on the type of infection a person has: without symptoms (‘asymptomatic’), mild or severe. Even people without symptoms seem to develop an immune response. Globally, data from seroprevalence studies suggests that less 10% of those studied have been infected, meaning that the vast majority of the world’s population remains susceptible to this virus. For other coronaviruses – such as the common cold, SARS-CoV-1 and Middle East Respiratory Syndrome (MERS) – immunity declines over time, as is the case with other diseases. While people infected with the SARS-CoV-2 virus develop antibodies and immunity, we do not yet know how long it lasts. Watch this conversation with Dr Mike Ryan and Dr Maria Van Kerkhove for more information on immunity. Large scale physical distancing measures and movement restrictions, often referred to as ‘lockdowns’, can slow COVID‑19 transmission by limiting contact between people. However, these measures can have a profound negative impact on individuals, communities, and societies by bringing social and economic life to a near stop. Such measures disproportionately affect disadvantaged groups, including people in poverty, migrants, internally displaced people and refugees, who most often live in overcrowded and under resourced settings, and depend on daily labour for subsistence. WHO recognizes that at certain points, some countries have had no choice but to issue stay-at-home orders and other measures, to buy time. Governments must make the most of the extra time granted by ‘lockdown’ measures by doing all they can to build their capacities to detect, isolate, test and care for all cases; trace and quarantine all contacts; engage, empower and enable populations to drive the societal response and more. WHO is hopeful that countries will use targeted interventions where and when needed, based on the local situation. WHO TEAM WHO Headquarters (HQ) Related
Scoop.it!

Abstract Tremendous progress has been made in understanding the role of T cell immunity in acute and convalescent COVID-19 infection. Here we shed light on the “known unknowns” of pre-existing and acquired T cell responses in relation to acute and convalescent SARS-CoV-2 infection. INTRODUCTION The broad clinical spectrum of COVID-19 indicates widespread intraindividual differences in the host immune defense against severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2). The underlying cause of disease heterogeneity is probably multifactorial. However, a rapid early host response is likely critical to generate control of SARS-CoV-2 viremia before spread to the lower respiratory tract and onset of damaging hyperinflammation. In this regard, the literature is full of examples where functional T cell responses can provide early control of acute viral infections, including SARS-CoV and MERS-CoV (1, 2). Although multiple studies have indicated that T cells play a role in the early immune response to SARS-CoV-2 and can generate a functional memory pool, there are still multiple unanswered questions in the field (Box 1). Here, we summarize and speculate on a specific set of questions related to T cell immunity against respiratory viral infections, with a focus on COVID-19 severity, immunity, long-term consequences, and vaccination (Fig. 1). Box 1 Open questions about T cell immunity to SARS-CoV-2. T cells in acute SARS-CoV-2 infection • What do acute SARS-CoV-2-specific T cell responses in the blood tell us about contemporaneous T cell responses in the lung? • Which host and viral factors regulate the strength and efficacy of the early antiviral T cell response? Longevity and memory T cell formation • Do CD4+ T cell responses to the virus predominate over CD8+ responses in the lung as well as the blood? • Do poor CD4+ TFH responses to the virus correlate with reduced longevity of antibody responses? • Is severe COVID 19 linked to an impaired development of SARS-CoV-2-specific memory T cells? Cross-reactive T cells • Do pre-existing memory T cells to seasonal CoV epitopes help or hinder the host response to SARS-CoV-2? SARS-CoV-2-specific TRM • Will establishment of SARS-CoV-2-specific CD4+ and CD8+ TRM in the upper respiratory tract provide durable protection from lower pulmonary disease upon reinfection? Long COVID • Are virus-induced or bystander T cells major inducers of persistent symptoms of inflammation associated with long COVID? T cells in vaccines • What type of T cell response elicited by vaccines will be the best predictor of protection from disease following exposure to the virus? T CELLS IN ACUTE SARS-COV-2 INFECTION T cells are critical to generate early control and clearance of many viral infections of the respiratory system (3). Recent studies in transgenic mouse models provided evidence that T cells are also important for viral clearance and disease resolution after SARS-CoV-2 infection (4). As such, it is not surprising that T cell activation has emerged as a hallmark of acute COVID-19; probably as a consequence of an early SARS-CoV-2-specific cellular immune response (5–9). Although early T cell responses may play a critical role in dampening disease severity, there are also reports describing a dysregulated and unchecked T cell activation pattern in severe cases (10–12). Increased T cell activation in severe cases likely reflects increased antigen levels in the respiratory system, but whether the early T cell response reaches a state of exhaustion in subjects with severe hyperinflammation remains to be determined. Furthermore, given that COVID-19 is a disease of the respiratory tract it will be important to define if early detection of T cell activation in blood correlates with tissue-specific events. For instance, will delayed detection of SARS-CoV-2-specific T cells in blood reflect the later onset of cellular immunity in the respiratory tract or are these two compartments independent of each other in relation to disease severity? If elicitation of an early T cell response would be beneficial to dampen COVID-19 severity, what might be the underlying causes and correlates of an early versus late onset of SARS-CoV-2-specific T cell activity? Old age and male sex are both associated with increased risk of COVID-19 complications. Interestingly, females seem to mount a somewhat stronger T cell activation following SARS-CoV-2 infection (13) and disruption of T and B cell coordination has been implicated in elderly patients with severe COVID-19 (14). On the other end of the age spectrum, decreased frequencies of IFN-γ+CD4+ and CD25+CD4+ T cells have been described in hospitalized pediatric patients, who have shorter lengths of stay compared with their adult counterparts (15). In conjunction with age and sex, host and viral factors probably also play a role in the early immune defense and coordination of the early SARS-CoV-2-specific T cell response. For instance, SARS-CoV-2 has mechanisms to antagonize proinflammatory signals, particularly type I IFN (IFN-I) signaling (16, 17). IFN-I proteins are key inflammatory mediators to initiate antiviral defense, from which viral evasion might lead to a delayed clearance of SARS-CoV-2 (4). This is supported by the observation that inborn errors of immunity and autoantibodies that diminish IFN-I activity are more commonly detected in patients with severe COVID-19 (18, 19). Concordantly, the early expansion and differentiation of antiviral T cells are dependent on the direct action of IFN-I. Given that activated T cells from older individuals exhibit reduced responses to IFN-I, it is tempting to speculate that higher risk elderly persons experience delayed activation of SARS-CoV-2-specific T cells that may lead to reduced clearance of the virus and exacerbated COVID-19 severity. Collectively, more data are needed from mechanistic studies in animal models as well as large cohort studies on males and females in different age groups to identify beneficial and detrimental viral and host factors that have an impact on the early T cell response against SARS-CoV-2. LONGEVITY AND MEMORY T CELL FORMATION Generation of memory T cells can provide lifelong protection against pathogens (20). Previous studies have demonstrated that SARS-CoV- and MERS-CoV-specific T cells can be detected many years after infection (21–23). Likewise, SARS-CoV-2-specific CD4+ and CD8+ T cells are distinguished in a vast majority of convalescent donors (7, 9, 21, 24–27). Studies using peripheral blood have reported stronger SARS-CoV-2-specific CD4+ than CD8+ T cell responses in most subjects. However, it is well established that CD4+ T cells experience a higher propensity to recirculate between tissues and blood than CD8+ T cells. As such, whether SARS-CoV-2-specific CD4+ T cell responses also predominate in tissues, and particularly at barrier sites close to the epithelium, needs to be confirmed through studies on the upper and lower respiratory tract. Similar to the CD4+ T cell polarized response to many other viral infections, SARS-CoV-2-specific CD4+ T cells mainly possess a Th1 or circulating T follicular helper (TFH) cell phenotype (7–9, 14, 28). Circulating TFH differentiation seems to be impaired in certain patients with severe COVID-19 (11, 29) and recent analysis of postmortem lymph nodes and spleen samples showed an absence of germinal centers along with a defect in Bcl6+ TFH differentiation in deceased COVID-19 patients (30). Whether these consequences are due to sampling from postmortem patients remains unknown, but further studies are needed to clarify whether TFH cell formation is impaired by SARS-CoV-2 and could have an impact on declining antibody responses in specific convalescent donors. Furthermore, more mechanistic studies are needed to understand if memory T cells can generate protective immunity to lethal challenge with SARS-CoV-2, as previously demonstrated in SARS-CoV and MERS-CoV models (1, 2), in the presence or absence of high titers of neutralizing antibodies. Likewise, longitudinal human studies will also inform us of whether functional memory T cell responses are present many years after SARS-CoV-2 infection and correlate with protection from reinfection. CROSS-REACTIVE T CELLS Several studies have demonstrated the presence of CD4+ and to a lesser extent CD8+ T cells recognizing SARS-CoV-2 peptides in a significant proportion of unexposed individuals (7, 21, 24, 26, 31). Mapping of SARS-CoV-2 epitopes in unexposed blood donors revealed pre-existing T cell immunity, potentially induced by seasonal human coronaviruses (HCoVs) causing common colds (27, 32). This is supported by a relatively high amino acid similarity between recognized SARS-CoV-2 epitopes and seasonal HCoVs such as HCoV-OC43, -HKU1, -229E and -NL63. The presence of cross-reactive cellular immune responses in the population generates an obstacle to the use of T cell-based assays to track SARS-CoV-2 infection rates in blood donors. Given that antibodies do not result in the same degree of cross-reactivity as T cells and are consequently easier to use in clinical diagnostic settings, serology will likely be a better readout for tracing the infection rate in the society. Nevertheless, more thorough studies are needed to better understand the full spectrum of cross-reactive versus newly-induced SARS-CoV-2-specific CD4+ and CD8+ T cell responses. A key question in the field is whether pre-existing T cell responses influence the severity of COVID-19. Pre-existing SARS-CoV-2-specific T cells are unlikely to provide sterilizing or herd immunity but may allow the host to bypass immune evasion mechanisms, for instance evasion from IFN-I, and generate early pressure on the virus. This concept is supported by studies in mice showing that airway memory CD4+ T cells recognizing a conserved SARS-CoV epitope provided protection from related CoVs (1). Similar scenarios in which pre-existing T cells may provide earlier viral clearance and thus less severe symptoms have been proposed elsewhere (33). Here, the level of conservation between antigens may have a substantial impact on whether pre-existing T cells are beneficial or detrimental for the host. On the other hand, the concept of “original antigenic sin”, in which earlier induced antibody or T cell responses influence the response against future viral infections, needs further evaluation (34). If pre-existing T cells are less effective in clearing viral infection upon activation but contribute to systemic and permanent increase in inflammatory signals, it might lead to increased hyperinflammation and COVID-19 severity. In a first analysis, comparing T cell responses against SARS-CoV-2 and HCoV sequences did not find any evidence of “original antigenic sin” (32). Again, the level of conservation of targeted epitopes is likely to impact the outcome, and further evaluation of this concept is needed. Collectively, further animal studies and human studies done before and after SARS-CoV-2 infection are needed to define the biological relevance of pre-existing T cell responses and their role as friends or foes in host defense against SARS-CoV-2. SARS-COV-2-SPECIFIC TRM Resident memory T cells (TRM) are a distinct memory T cell lineage. These cells reside within tissues, do not recirculate to peripheral blood, and have been defined as local sentinels mediating rapid protection from reinfection (35). In fact, a vast majority of T cells in nonlymphoid tissues, such as the respiratory tract, are considered to be TRM (36). In terms of respiratory infections, there is a growing body of literature demonstrating that TRM can provide protection against severe pulmonary disease (37, 38). Likewise, airway CD4+ T cells can generate cross-reactive immunity between human and bat coronaviruses (1), emphasizing that cross-reactive T cells in the respiratory tract can provide protection from lethal challenge with pathogenic coronaviruses. Whether cross-reactive TRM, induced by seasonal coronaviruses, can block transmission of SARS-CoV-2 from the upper respiratory tract to the lung and thereby attenuate severe COVID-19 remains unanswered. This scenario, where TRM block the spread of viral disease from upper to lower respiratory tract, has been demonstrated in influenza A infection (37) and might account for partial immunity of secondary infection with heterologous strains (39, 40). Furthermore, whether SARS-CoV-2-specific TRM are induced after COVID-19 and whether these cells will provide protection in the long term also remains unknown (41). Although certain studies in mice have suggested that TRM in the lung are short-lived (42), there is evidence that their counterparts in the upper respiratory tract persist with minimal decay (37) and for more than a year in human lung (43). Altogether, there is currently no evidence supporting the provision of “sterilizing immunity” by TRM, but data presented above suggest that TRM could facilitate rapid control of upper respiratory tract SARS-CoV-2 infection, replication, and spread. In this regard, further work in animal models may provide evidence for whether local immunity mediated by TRM can achieve this type of immunity. LONG COVID A substantial number of COVID-19 patients experience heterogeneous symptoms that persist over a month and onward (44–46). This heterogeneous phenomenon is being referred to as “long COVID” and affects around 10% of all COVID-19 patients (44, 45). Many symptoms can be attributed to persistent tissue damage in severe COVID-19. Nevertheless, the fact that many individuals with milder COVID-19 symptoms also experience chronic lingering symptoms, involving the cardiovascular, nervous, and respiratory systems, indicates that persistent immune activation and/or inflammation may play a role in long COVID. Multiple mechanisms are probably involved in this condition and whether T cells play any role in long COVID is unknown. The higher incidence of long COVID in females than males, similar to autoimmune diseases (47), raises the question of whether T cells orchestrate long COVID through similar mechanisms as in autoimmune or inflammatory conditions (48, 49). One hypothetical underlying mechanism behind autoimmune-related conditions after COVID-19 could be molecular mimicry, given that HCoV-specific T cells can cross-react to myelin in multiple sclerosis patients (50). Whether SARS-CoV-2-specific T cells have the ability to react against self-antigens remains to be determined. In line with a possible effect of HLA type on COVID-19 susceptibility/severity (51, 52), we believe that larger genetic studies are needed to clarify if HLA or other immune-related genes are associated with an increased risk of developing long COVID. T CELLS IN VACCINES Based on the uncertainty of whether cross-reactive T cells or antibodies will provide protective or long-lasting immunity to COVID-19, it will become absolutely critical to administrate a safe and effective vaccine to the population to reach broad immunity and break the negative spiral of new infections. Ongoing vaccine efforts mainly target B cells to promote the induction of neutralizing antibodies (nAbs) against SARS-CoV-2 (53, 54). Although the induction of anti-spike nAbs is the key component for an effective SARS-CoV-2 vaccine, it is well-known that T cells, and in particular TFH cells, are critical to generate antibody-producing plasma cells and long-lived memory B cells. In COVID-19 patients, high nAb titers correlated with strong CD4+ T cell responses, and the lack of functional TFH cells reacting against SARS-CoV-2 was shown to be detrimental (11, 29, 30). Preliminary results from the two major mRNA vaccine trials in humans have demonstrated potent Th1 responses (55, 56). However, previous studies have reported strong TFH responses against certain mRNA vaccines (57), and future trials should therefore include other activation induced markers, such as CD40L and/or CD200, in addition to IFN-γ ELISPOT assays to understand if potent B-helper mechanisms are induced by the current vaccine regimens. Other outstanding questions are whether vaccine-induced TFH responses will be equally induced in all age groups and how long these responses will persist in blood and vaccination site-draining lymph nodes. A final issue to consider is whether high quantities of vaccine-induced CD8+ T cells at local sites need to be elicited by future vaccine candidates. If the initial group of vaccines in clinical trials that are primarily focused on generating an effective nAb response provide recipients with long-standing protection, it may not be necessary to invest in such efforts. However, if problems emerge in the vaccinated population with breakthrough infections, waning antibody levels after vaccination, and/or the emergence of new viral strains, it would be wise to reconsider vaccine approaches specifically designed to induce functional CD8+ TRM responses in the upper respiratory tract. SUMMARY Collective efforts have greatly enhanced our scientific understanding of T cell responses against SARS-CoV-2 but many unknowns remain to be resolved. Although it is clear that T cells play a central role in generating early control and clearance of many viral infections, their role in SARS-CoV-2 infection is only starting to be revealed. Specific T cells may even have a detrimental impact on the clinical outcome and contribute to long COVID symptoms. Currently, there is a need for deeper analysis using both animal models and longitudinal follow-up studies of large patient cohorts to define the beneficial versus detrimental aspects of SARS-CoV-2-specific T cells in acute, convalescent and vaccine settings of COVID-19. References and Notes ↵ J. Zhao, J. Zhao, A. K. Mangalam, R. Channappanavar, C. Fett, D. K. Meyerholz, S. Agnihothram, R. S. Baric, C. S. David, S. Perlman, Airway Memory CD4(+) T Cells Mediate Protective Immunity against Emerging Respiratory Coronaviruses. Immunity 44, 1379–1391 (2016). doi:10.1016/j.immuni.2016.05.006pmid:27287409OpenUrlCrossRefPubMed ↵ J. Zhao, J. Zhao, S. Perlman, T cell responses are required for protection from clinical disease and for virus clearance in severe acute respiratory syndrome coronavirus-infected mice. J. Virol. 84, 9318–9325 (2010). doi:10.1128/JVI.01049-10pmid:20610717 ↵ M. E. Schmidt, S. M. Varga, The CD8 T Cell Response to Respiratory Virus Infections. Front. Immunol. 9, 678 (2018). doi:10.3389/fimmu.2018.00678pmid:29686673OpenUrlCrossRefPubMed ↵ J. Sun, Z. Zhuang, J. Zheng, K. Li, R. L.-Y. Wong, D. Liu, J. Huang, J. He, A. Zhu, J. Zhao, X. Li, Y. Xi, R. Chen, A. N. Alshukairi, Z. Chen, Z. Zhang, C. Chen, X. Huang, F. Li, X. Lai, D. Chen, L. Wen, J. Zhuo, Y. Zhang, Y. Wang, S. Huang, J. Dai, Y. Shi, K. Zheng, M. R. Leidinger, J. Chen, Y. Li, N. Zhong, D. K. Meyerholz, P. B. McCray Jr.., S. Perlman, J. Zhao, Generation of a Broadly Useful Model for COVID-19 Pathogenesis, Vaccination, and Treatment. Cell 182, 734–743.e5 (2020). doi:10.1016/j.cell.2020.06.010pmid:32643603OpenUrlCrossRefPubMed ↵ I. Thevarajan, T. H. O. Nguyen, M. Koutsakos, J. Druce, L. Caly, C. E. van de Sandt, X. Jia, S. Nicholson, M. Catton, B. Cowie, S. Y. C. Tong, S. R. Lewin, K. Kedzierska, Breadth of concomitant immune responses prior to patient recovery: A case report of non-severe COVID-19. Nat. Med. 26, 453–455 (2020). doi:10.1038/s41591-020-0819-2pmid:32284614OpenUrlCrossRefPubMed A. J. Wilk, A. Rustagi, N. Q. Zhao, J. Roque, G. J. Martínez-Colón, J. L. McKechnie, G. T. Ivison, T. Ranganath, R. Vergara, T. Hollis, L. J. Simpson, P. Grant, A. Subramanian, A. J. Rogers, C. A. Blish, A single-cell atlas of the peripheral immune response in patients with severe COVID-19. Nat. Med. 26, 1070–1076 (2020). doi:10.1038/s41591-020-0944-ypmid:32514174OpenUrlCrossRefPubMed ↵ T. Sekine, A. Perez-Potti, O. Rivera-Ballesteros, K. Strålin, J.-B. Gorin, A. Olsson, S. Llewellyn-Lacey, H. Kamal, G. Bogdanovic, S. Muschiol, D. J. Wullimann, T. Kammann, J. Emgård, T. Parrot, E. Folkesson, O. Rooyackers, L. I. Eriksson, J.-I. Henter, A. Sönnerborg, T. Allander, J. Albert, M. Nielsen, J. Klingström, S. Gredmark-Russ, N. K. Björkström, J. K. Sandberg, D. A. Price, H.-G. Ljunggren, S. Aleman, M. Buggert; Karolinska COVID-19 Study Group, Robust T Cell Immunity in Convalescent Individuals with Asymptomatic or Mild COVID-19. Cell 183, 158–168.e14 (2020). doi:10.1016/j.cell.2020.08.017pmid:32979941OpenUrlCrossRefPubMed D. Weiskopf, K. S. Schmitz, M. P. Raadsen, A. Grifoni, N. M. A. Okba, H. Endeman, J. P. C. van den Akker, R. Molenkamp, M. P. G. Koopmans, E. C. M. van Gorp, B. L. Haagmans, R. L. de Swart, A. Sette, R. D. de Vries, Phenotype and kinetics of SARS-CoV-2-specific T cells in COVID-19 patients with acute respiratory distress syndrome. Sci. Immunol. 5, eabd2071 (2020). doi:10.1126/sciimmunol.abd2071pmid:32591408 ↵ Y. Peng, A. J. Mentzer, G. Liu, X. Yao, Z. Yin, D. Dong, W. Dejnirattisai, T. Rostron, P. Supasa, C. Liu, C. López-Camacho, J. Slon-Campos, Y. Zhao, D. I. Stuart, G. C. Paesen, J. M. Grimes, A. A. Antson, O. W. Bayfield, D. E. D. P. Hawkins, D.-S. Ker, B. Wang, L. Turtle, K. Subramaniam, P. Thomson, P. Zhang, C. Dold, J. Ratcliff, P. Simmonds, T. de Silva, P. Sopp, D. Wellington, U. Rajapaksa, Y.-L. Chen, M. Salio, G. Napolitani, W. Paes, P. Borrow, B. M. Kessler, J. W. Fry, N. F. Schwabe, M. G. Semple, J. K. Baillie, S. C. Moore, P. J. M. Openshaw, M. A. Ansari, S. Dunachie, E. Barnes, J. Frater, G. Kerr, P. Goulder, T. Lockett, R. Levin, Y. Zhang, R. Jing, L.-P. Ho, R. J. Cornall, C. P. Conlon, P. Klenerman, G. R. Screaton, J. Mongkolsapaya, A. McMichael, J. C. Knight, G. Ogg, T. Dong; Oxford Immunology Network Covid-19 Response T cell Consortium; ISARIC4C Investigators, Broad and strong memory CD4+ and CD8+ T cells induced by SARS-CoV-2 in UK convalescent individuals following COVID-19. Nat. Immunol. 21, 1336–1345 (2020). doi:10.1038/s41590-020-0782-6pmid:32887977OpenUrlCrossRefPubMed ↵ L. Kuri-Cervantes, M. B. Pampena, W. Meng, A. M. Rosenfeld, C. A. G. Ittner, A. R. Weisman, R. S. Agyekum, D. Mathew, A. E. Baxter, L. A. Vella, O. Kuthuru, S. A. Apostolidis, L. Bershaw, J. Dougherty, A. R. Greenplate, A. Pattekar, J. Kim, N. Han, S. Gouma, M. E. Weirick, C. P. Arevalo, M. J. Bolton, E. C. Goodwin, E. M. Anderson, S. E. Hensley, T. K. Jones, N. S. Mangalmurti, E. T. Luning Prak, E. J. Wherry, N. J. Meyer, M. R. Betts, Comprehensive mapping of immune perturbations associated with severe COVID-19. Sci. Immunol. 5, eabd7114 (2020). doi:10.1126/sciimmunol.abd7114pmid:32669287 ↵ D. Mathew, J. R. Giles, A. E. Baxter, D. A. Oldridge, A. R. Greenplate, J. E. Wu, C. Alanio, L. Kuri-Cervantes, M. B. Pampena, K. D’Andrea, S. Manne, Z. Chen, Y. J. Huang, J. P. Reilly, A. R. Weisman, C. A. G. Ittner, O. Kuthuru, J. Dougherty, K. Nzingha, N. Han, J. Kim, A. Pattekar, E. C. Goodwin, E. M. Anderson, M. E. Weirick, S. Gouma, C. P. Arevalo, M. J. Bolton, F. Chen, S. F. Lacey, H. Ramage, S. Cherry, S. E. Hensley, S. A. Apostolidis, A. C. Huang, L. A. Vella, M. R. Betts, N. J. Meyer, E. J. Wherry; UPenn COVID Processing Unit, Deep immune profiling of COVID-19 patients reveals distinct immunotypes with therapeutic implications. Science 369, eabc8511 (2020). doi:10.1126/science.abc8511pmid:32669297 ↵ A. G. Laing, A. Lorenc, I. Del Molino Del Barrio, A. Das, M. Fish, L. Monin, M. Muñoz-Ruiz, D. R. McKenzie, T. S. Hayday, I. Francos-Quijorna, S. Kamdar, M. Joseph, D. Davies, R. Davis, A. Jennings, I. Zlatareva, P. Vantourout, Y. Wu, V. Sofra, F. Cano, M. Greco, E. Theodoridis, J. Freedman, S. Gee, J. N. E. Chan, S. Ryan, E. Bugallo-Blanco, P. Peterson, K. Kisand, L. Haljasmägi, L. Chadli, P. Moingeon, L. Martinez, B. Merrick, K. Bisnauthsing, K. Brooks, M. A. A. Ibrahim, J. Mason, F. Lopez Gomez, K. Babalola, S. Abdul-Jawad, J. Cason, C. Mant, J. Seow, C. Graham, K. J. Doores, F. Di Rosa, J. Edgeworth, M. Shankar-Hari, A. C. Hayday, A dynamic COVID-19 immune signature includes associations with poor prognosis. Nat. Med. 26, 1623–1635 (2020). pmid:32807934OpenUrlCrossRefPubMed ↵ T. Takahashi, M. K. Ellingson, P. Wong, B. Israelow, C. Lucas, J. Klein, J. Silva, T. Mao, J. E. Oh, M. Tokuyama, P. Lu, A. Venkataraman, A. Park, F. Liu, A. Meir, J. Sun, E. Y. Wang, A. Casanovas-Massana, A. L. Wyllie, C. B. F. Vogels, R. Earnest, S. Lapidus, I. M. Ott, A. J. Moore, A. Shaw, J. B. Fournier, C. D. Odio, S. Farhadian, C. Dela Cruz, N. D. Grubaugh, W. L. Schulz, A. M. Ring, A. I. Ko, S. B. Omer, A. Iwasaki; Yale IMPACT Research Team, Sex differences in immune responses that underlie COVID-19 disease outcomes. Nature (2020). doi:10.1038/s41586-020-2700-3pmid:32846427OpenUrlCrossRefPubMed ↵ C. Rydyznski Moderbacher, S. I. Ramirez, J. M. Dan, A. Grifoni, K. M. Hastie, D. Weiskopf, S. Belanger, R. K. Abbott, C. Kim, J. Choi, Y. Kato, E. G. Crotty, C. Kim, S. A. Rawlings, J. Mateus, L. P. V. Tse, A. Frazier, R. Baric, B. Peters, J. Greenbaum, E. Ollmann Saphire, D. M. Smith, A. Sette, S. Crotty, Antigen-Specific Adaptive Immunity to SARS-CoV-2 in Acute COVID-19 and Associations with Age and Disease Severity. Cell 183, 996–1012.e19 (2020). doi:10.1016/j.cell.2020.09.038pmid:33010815OpenUrlCrossRefPubMed ↵ C. A. Pierce, P. Preston-Hurlburt, Y. Dai, C. B. Aschner, N. Cheshenko, B. Galen, S. J. Garforth, N. G. Herrera, R. K. Jangra, N. C. Morano, E. Orner, S. Sy, K. Chandran, J. Dziura, S. C. Almo, A. Ring, M. J. Keller, K. C. Herold, B. C. Herold, Immune responses to SARS-CoV-2 infection in hospitalized pediatric and adult patients. Sci. Transl. Med. 12, eabd5487 (2020). doi:10.1126/scitranslmed.abd5487pmid:32958614 ↵ D. Blanco-Melo, B. E. Nilsson-Payant, W.-C. Liu, S. Uhl, D. Hoagland, R. Møller, T. X. Jordan, K. Oishi, M. Panis, D. Sachs, T. T. Wang, R. E. Schwartz, J. K. Lim, R. A. Albrecht, B. R. tenOever, Imbalanced Host Response to SARS-CoV-2 Drives Development of COVID-19. Cell 181, 1036–1045.e9 (2020). doi:10.1016/j.cell.2020.04.026pmid:32416070OpenUrlCrossRefPubMed ↵ J. Hadjadj, N. Yatim, L. Barnabei, A. Corneau, J. Boussier, N. Smith, H. Péré, B. Charbit, V. Bondet, C. Chenevier-Gobeaux, P. Breillat, N. Carlier, R. Gauzit, C. Morbieu, F. Pène, N. Marin, N. Roche, T.-A. Szwebel, S. H. Merkling, J.-M. Treluyer, D. Veyer, L. Mouthon, C. Blanc, P.-L. Tharaux, F. Rozenberg, A. Fischer, D. Duffy, F. Rieux-Laucat, S. Kernéis, B. Terrier, Impaired type I interferon activity and inflammatory responses in severe COVID-19 patients. Science 369, 718–724 (2020). doi:10.1126/science.abc6027pmid:32661059 ↵ P. Bastard, L. B. Rosen, Q. Zhang, E. Michailidis, H.-H. Hoffmann, Y. Zhang, K. Dorgham, Q. Philippot, J. Rosain, V. Béziat, J. Manry, E. Shaw, L. Haljasmägi, P. Peterson, L. Lorenzo, L. Bizien, S. Trouillet-Assant, K. Dobbs, A. A. de Jesus, A. Belot, A. Kallaste, E. Catherinot, Y. Tandjaoui-Lambiotte, J. Le Pen, G. Kerner, B. Bigio, Y. Seeleuthner, R. Yang, A. Bolze, A. N. Spaan, O. M. Delmonte, M. S. Abers, A. Aiuti, G. Casari, V. Lampasona, L. Piemonti, F. Ciceri, K. Bilguvar, R. P. Lifton, M. Vasse, D. M. Smadja, M. Migaud, J. Hadjadj, B. Terrier, D. Duffy, L. Quintana-Murci, D. van de Beek, L. Roussel, D. C. Vinh, S. G. Tangye, F. Haerynck, D. Dalmau, J. Martinez-Picado, P. Brodin, M. C. Nussenzweig, S. Boisson-Dupuis, C. Rodríguez-Gallego, G. Vogt, T. H. Mogensen, A. J. Oler, J. Gu, P. D. Burbelo, J. I. Cohen, A. Biondi, L. R. Bettini, M. D’Angio, P. Bonfanti, P. Rossignol, J. Mayaux, F. Rieux-Laucat, E. S. Husebye, F. Fusco, M. V. Ursini, L. Imberti, A. Sottini, S. Paghera, E. Quiros-Roldan, C. Rossi, R. Castagnoli, D. Montagna, A. Licari, G. L. Marseglia, X. Duval, J. Ghosn, J. S. Tsang, R. Goldbach-Mansky, K. Kisand, M. S. Lionakis, A. Puel, S.-Y. Zhang, S. M. Holland, G. Gorochov, E. Jouanguy, C. M. Rice, A. Cobat, L. D. Notarangelo, L. Abel, H. C. Su, J.-L. Casanova; HGID Lab; NIAID-USUHS Immune Response to COVID Group; COVID Clinicians; COVID-STORM Clinicians; Imagine COVID Group; French COVID Cohort Study Group; Milieu Intérieur Consortium; CoV-Contact Cohort; Amsterdam UMC Covid-19 Biobank; COVID Human Genetic Effort, Autoantibodies against type I IFNs in patients with life-threatening COVID-19. Science 370, eabd4585 (2020). doi:10.1126/science.abd4585pmid:32972996 ↵ Q. Zhang, P. Bastard, Z. Liu, J. Le Pen, M. Moncada-Velez, J. Chen, M. Ogishi, I. K. D. Sabli, S. Hodeib, C. Korol, J. Rosain, K. Bilguvar, J. Ye, A. Bolze, B. Bigio, R. Yang, A. A. Arias, Q. Zhou, Y. Zhang, F. Onodi, S. Korniotis, L. Karpf, Q. Philippot, M. Chbihi, L. Bonnet-Madin, K. Dorgham, N. Smith, W. M. Schneider, B. S. Razooky, H.-H. Hoffmann, E. Michailidis, L. Moens, J. E. Han, L. Lorenzo, L. Bizien, P. Meade, A.-L. Neehus, A. C. Ugurbil, A. Corneau, G. Kerner, P. Zhang, F. Rapaport, Y. Seeleuthner, J. Manry, C. Masson, Y. Schmitt, A. Schlüter, T. Le Voyer, T. Khan, J. Li, J. Fellay, L. Roussel, M. Shahrooei, M. F. Alosaimi, D. Mansouri, H. Al-Saud, F. Al-Mulla, F. Almourfi, S. Z. Al-Muhsen, F. Alsohime, S. Al Turki, R. Hasanato, D. van de Beek, A. Biondi, L. R. Bettini, M. D’Angio’, P. Bonfanti, L. Imberti, A. Sottini, S. Paghera, E. Quiros-Roldan, C. Rossi, A. J. Oler, M. F. Tompkins, C. Alba, I. Vandernoot, J.-C. Goffard, G. Smits, I. Migeotte, F. Haerynck, P. Soler-Palacin, A. Martin-Nalda, R. Colobran, P.-E. Morange, S. Keles, F. Çölkesen, T. Ozcelik, K. K. Yasar, S. Senoglu, Ş. N. Karabela, C. Rodríguez-Gallego, G. Novelli, S. Hraiech, Y. Tandjaoui-Lambiotte, X. Duval, C. Laouénan, A. L. Snow, C. L. Dalgard, J. D. Milner, D. C. Vinh, T. H. Mogensen, N. Marr, A. N. Spaan, B. Boisson, S. Boisson-Dupuis, J. Bustamante, A. Puel, M. J. Ciancanelli, I. Meyts, T. Maniatis, V. Soumelis, A. Amara, M. Nussenzweig, A. García-Sastre, F. Krammer, A. Pujol, D. Duffy, R. P. Lifton, S.-Y. Zhang, G. Gorochov, V. Béziat, E. Jouanguy, V. Sancho-Shimizu, C. M. Rice, L. Abel, L. D. Notarangelo, A. Cobat, H. C. Su, J.-L. Casanova; COVID-STORM Clinicians; COVID Clinicians; Imagine COVID Group; French COVID Cohort Study Group; CoV-Contact Cohort; Amsterdam UMC Covid-19 Biobank; COVID Human Genetic Effort; NIAID-USUHS/TAGC COVID Immunity Group, Inborn errors of type I IFN immunity in patients with life-threatening COVID-19. Science 370, eabd4570 (2020). doi:10.1126/science.abd4570pmid:32972995 ↵ D. L. Farber, N. A. Yudanin, N. P. Restifo, Human memory T cells: Generation, compartmentalization and homeostasis. Nat. Rev. Immunol. 14, 24–35 (2014). doi:10.1038/nri3567pmid:24336101OpenUrlCrossRefPubMed ↵ N. Le Bert, A. T. Tan, K. Kunasegaran, C. Y. L. Tham, M. Hafezi, A. Chia, M. H. Y. Chng, M. Lin, N. Tan, M. Linster, W. N. Chia, M. I.-C. Chen, L.-F. Wang, E. E. Ooi, S. Kalimuddin, P. A. Tambyah, J. G.-H. Low, Y.-J. Tan, A. Bertoletti, SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls. Nature 584, 457–462 (2020). doi:10.1038/s41586-020-2550-zpmid:32668444OpenUrlCrossRefPubMed H. S. Shin, Y. Kim, G. Kim, J. Y. Lee, I. Jeong, J.-S. Joh, H. Kim, E. Chang, S. Y. Sim, J.-S. Park, D.-G. Lim, Immune Responses to Middle East Respiratory Syndrome Coronavirus During the Acute and Convalescent Phases of Human Infection. Clin. Infect. Dis. 68, 984–992 (2019). doi:10.1093/cid/ciy595pmid:30060038OpenUrlCrossRefPubMed ↵ F. Tang, Y. Quan, Z.-T. Xin, J. Wrammert, M.-J. Ma, H. Lv, T.-B. Wang, H. Yang, J. H. Richardus, W. Liu, W.-C. Cao, Lack of peripheral memory B cell responses in recovered patients with severe acute respiratory syndrome: A six-year follow-up study. J. Immunol. 186, 7264–7268 (2011). doi:10.4049/jimmunol.0903490pmid:21576510 ↵ A. Grifoni, D. Weiskopf, S. I. Ramirez, J. Mateus, J. M. Dan, C. R. Moderbacher, S. A. Rawlings, A. Sutherland, L. Premkumar, R. S. Jadi, D. Marrama, A. M. de Silva, A. Frazier, A. F. Carlin, J. A. Greenbaum, B. Peters, F. Krammer, D. M. Smith, S. Crotty, A. Sette, Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals. Cell 181, 1489–1501.e15 (2020). doi:10.1016/j.cell.2020.05.015pmid:32473127OpenUrlCrossRefPubMed L. Ni, F. Ye, M.-L. Cheng, Y. Feng, Y.-Q. Deng, H. Zhao, P. Wei, J. Ge, M. Gou, X. Li, L. Sun, T. Cao, P. Wang, C. Zhou, R. Zhang, P. Liang, H. Guo, X. Wang, C.-F. Qin, F. Chen, C. Dong, Detection of SARS-CoV-2-Specific Humoral and Cellular Immunity in COVID-19 Convalescent Individuals. Immunity 52, 971–977.e3 (2020). doi:10.1016/j.immuni.2020.04.023pmid:32413330OpenUrlCrossRefPubMed ↵ J. Braun, L. Loyal, M. Frentsch, D. Wendisch, P. Georg, F. Kurth, S. Hippenstiel, M. Dingeldey, B. Kruse, F. Fauchere, E. Baysal, M. Mangold, L. Henze, R. Lauster, M. A. Mall, K. Beyer, J. Röhmel, S. Voigt, J. Schmitz, S. Miltenyi, I. Demuth, M. A. Müller, A. Hocke, M. Witzenrath, N. Suttorp, F. Kern, U. Reimer, H. Wenschuh, C. Drosten, V. M. Corman, C. Giesecke-Thiel, L. E. Sander, A. Thiel, SARS-CoV-2-reactive T cells in healthy donors and patients with COVID-19. Nature 587, 270–274 (2020). doi:10.1038/s41586-020-2598-9pmid:32726801OpenUrlCrossRefPubMed ↵ A. Nelde, T. Bilich, J. S. Heitmann, Y. Maringer, H. R. Salih, M. Roerden, M. Lübke, J. Bauer, J. Rieth, M. Wacker, A. Peter, S. Hörber, B. Traenkle, P. D. Kaiser, U. Rothbauer, M. Becker, D. Junker, G. Krause, M. Strengert, N. Schneiderhan-Marra, M. F. Templin, T. O. Joos, D. J. Kowalewski, V. Stos-Zweifel, M. Fehr, A. Rabsteyn, V. Mirakaj, J. Karbach, E. Jäger, M. Graf, L.-C. Gruber, D. Rachfalski, B. Preuß, I. Hagelstein, M. Märklin, T. Bakchoul, C. Gouttefangeas, O. Kohlbacher, R. Klein, S. Stevanović, H.-G. Rammensee, J. S. Walz, SARS-CoV-2-derived peptides define heterologous and COVID-19-induced T cell recognition. Nat. Immunol. (2020). doi:10.1038/s41590-020-00808-xpmid:32999467OpenUrlCrossRefPubMed ↵ G. Chen, D. Wu, W. Guo, Y. Cao, D. Huang, H. Wang, T. Wang, X. Zhang, H. Chen, H. Yu, X. Zhang, M. Zhang, S. Wu, J. Song, T. Chen, M. Han, S. Li, X. Luo, J. Zhao, Q. Ning, Clinical and immunological features of severe and moderate coronavirus disease 2019. J. Clin. Invest. 130, 2620–2629 (2020). doi:10.1172/JCI137244pmid:32217835OpenUrlCrossRefPubMed ↵ J. A. Juno, H.-X. Tan, W. S. Lee, A. Reynaldi, H. G. Kelly, K. Wragg, R. Esterbauer, H. E. Kent, C. J. Batten, F. L. Mordant, N. A. Gherardin, P. Pymm, M. H. Dietrich, N. E. Scott, W.-H. Tham, D. I. Godfrey, K. Subbarao, M. P. Davenport, S. J. Kent, A. K. Wheatley, Humoral and circulating follicular helper T cell responses in recovered patients with COVID-19. Nat. Med. 26, 1428–1434 (2020). doi:10.1038/s41591-020-0995-0pmid:32661393OpenUrlCrossRefPubMed ↵ N. Kaneko, H.-H. Kuo, J. Boucau, J. R. Farmer, H. Allard-Chamard, V. S. Mahajan, A. Piechocka-Trocha, K. Lefteri, M. Osborn, J. Bals, Y. C. Bartsch, N. Bonheur, T. M. Caradonna, J. Chevalier, F. Chowdhury, T. J. Diefenbach, K. Einkauf, J. Fallon, J. Feldman, K. K. Finn, P. Garcia-Broncano, C. A. Hartana, B. M. Hauser, C. Jiang, P. Kaplonek, M. Karpell, E. C. Koscher, X. Lian, H. Liu, J. Liu, N. L. Ly, A. R. Michell, Y. Rassadkina, K. Seiger, L. Sessa, S. Shin, N. Singh, W. Sun, X. Sun, H. J. Ticheli, M. T. Waring, A. L. Zhu, G. Alter, J. Z. Li, D. Lingwood, A. G. Schmidt, M. Lichterfeld, B. D. Walker, X. G. Yu, R. F. Padera Jr.., S. Pillai; Massachusetts Consortium on Pathogen Readiness Specimen Working Group, Loss of Bcl-6-Expressing T Follicular Helper Cells and Germinal Centers in COVID-19. Cell 183, 143–157.e13 (2020). doi:10.1016/j.cell.2020.08.025pmid:32877699OpenUrlCrossRefPubMed ↵ B. J. Meckiff, C. Ramírez-Suástegui, V. Fajardo, S. J. Chee, A. Kusnadi, H. Simon, S. Eschweiler, A. Grifoni, E. Pelosi, D. Weiskopf, A. Sette, F. Ay, G. Seumois, C. H. Ottensmeier, P. Vijayanand, Imbalance of Regulatory and Cytotoxic SARS-CoV-2-Reactive CD4+ T Cells in COVID-19. Cell S0092-8674(20)31307-6 (2020). doi:10.1016/j.cell.2020.10.001pmid:33096020OpenUrlCrossRefPubMed ↵ J. Mateus, A. Grifoni, A. Tarke, J. Sidney, S. I. Ramirez, J. M. Dan, Z. C. Burger, S. A. Rawlings, D. M. Smith, E. Phillips, S. Mallal, M. Lammers, P. Rubiro, L. Quiambao, A. Sutherland, E. D. Yu, R. da Silva Antunes, J. Greenbaum, A. Frazier, A. J. Markmann, L. Premkumar, A. de Silva, B. Peters, S. Crotty, A. Sette, D. Weiskopf, Selective and cross-reactive SARS-CoV-2 T cell epitopes in unexposed humans. Science 370, 89–94 (2020). doi:10.1126/science.abd3871pmid:32753554 ↵ M. Lipsitch, Y. H. Grad, A. Sette, S. Crotty, Cross-reactive memory T cells and herd immunity to SARS-CoV-2. Nat. Rev. Immunol. 20, 709–713 (2020). doi:10.1038/s41577-020-00460-4pmid:33024281OpenUrlCrossRefPubMed ↵ P. Klenerman, R. M. Zinkernagel, Original antigenic sin impairs cytotoxic T lymphocyte responses to viruses bearing variant epitopes. Nature 394, 482–485 (1998). doi:10.1038/28860pmid:9697771OpenUrlCrossRefPubMed ↵ J. M. Schenkel, D. Masopust, Tissue-resident memory T cells. Immunity 41, 886–897 (2014). doi:10.1016/j.immuni.2014.12.007pmid:25526304OpenUrlCrossRefPubMed ↵ E. M. Steinert, J. M. Schenkel, K. A. Fraser, L. K. Beura, L. S. Manlove, B. Z. Igyártó, P. J. Southern, D. Masopust, Quantifying Memory CD8 T Cells Reveals Regionalization of Immunosurveillance. Cell 161, 737–749 (2015). doi:10.1016/j.cell.2015.03.031pmid:25957682OpenUrlCrossRefPubMed ↵ A. Pizzolla, T. H. O. Nguyen, J. M. Smith, A. G. Brooks, K. Kedzieska, W. R. Heath, P. C. Reading, L. M. Wakim, Resident memory CD8+ T cells in the upper respiratory tract prevent pulmonary influenza virus infection. Sci. Immunol. 2, eaam6970 (2017). doi:10.1126/sciimmunol.aam6970pmid:28783656 ↵ P. A. Darrah, J. J. Zeppa, P. Maiello, J. A. Hackney, M. H. Wadsworth 2nd., T. K. Hughes, S. Pokkali, P. A. Swanson 2nd., N. L. Grant, M. A. Rodgers, M. Kamath, C. M. Causgrove, D. J. Laddy, A. Bonavia, D. Casimiro, P. L. Lin, E. Klein, A. G. White, C. A. Scanga, A. K. Shalek, M. Roederer, J. L. Flynn, R. A. Seder, Prevention of tuberculosis in macaques after intravenous BCG immunization. Nature 577, 95–102 (2020). doi:10.1038/s41586-019-1817-8pmid:31894150OpenUrlCrossRefPubMed ↵ J. L. Schulman, E. D. Kilbourne, Induction of Partial Specific Heterotypic Immunity in Mice by a Single Infection with Influenza a Virus. J. Bacteriol. 89, 170–174 (1965). doi:10.1128/JB.89.1.170-174.1965pmid:14255658 ↵ R. B. Effros, P. C. Doherty, W. Gerhard, J. Bennink, Generation of both cross-reactive and virus-specific T-cell populations after immunization with serologically distinct influenza A viruses. J. Exp. Med. 145, 557–568 (1977). doi:10.1084/jem.145.3.557pmid:233901 ↵P. A. Szabo et al., Analysis of respiratory and systemic immune responses in COVID-19 reveals mechanisms of disease pathogenesis. medRxiv, (2020). DOI https://www.medrxiv.org/content/10.1101/2020.10.15.20208041v1 ↵ B. Slütter, N. Van Braeckel-Budimir, G. Abboud, S. M. Varga, S. Salek-Ardakani, J. T. Harty, Dynamics of influenza-induced lung-resident memory T cells underlie waning heterosubtypic immunity. Sci. Immunol. 2, eaag2031 (2017). doi:10.1126/sciimmunol.aag2031pmid:28783666 ↵ M. E. Snyder, M. O. Finlayson, T. J. Connors, P. Dogra, T. Senda, E. Bush, D. Carpenter, C. Marboe, L. Benvenuto, L. Shah, H. Robbins, J. L. Hook, M. Sykes, F. D’Ovidio, M. Bacchetta, J. R. Sonett, D. J. Lederer, S. Arcasoy, P. A. Sims, D. L. Farber, Generation and persistence of human tissue-resident memory T cells in lung transplantation. Sci. Immunol. 4, eaav5581 (2019). doi:10.1126/sciimmunol.aav5581pmid:30850393 ↵ E. Mahase, Long covid could be four different syndromes, review suggests. BMJ 371, m3981 (2020). doi:10.1136/bmj.m3981pmid:33055076OpenUrlFREE Full Text ↵ M. Marshall, The lasting misery of coronavirus long-haulers. Nature 585, 339–341 (2020). doi:10.1038/d41586-020-02598-6pmid:32929257OpenUrlCrossRefPubMed ↵ C. Iadecola, J. Anrather, H. Kamel, Effects of COVID-19 on the Nervous System. Cell 183, 16–27.e1 (2020). doi:10.1016/j.cell.2020.08.028pmid:32882182OpenUrlCrossRefPubMed ↵ C. C. Whitacre, Sex differences in autoimmune disease. Nat. Immunol. 2, 777–780 (2001). doi:10.1038/ni0901-777pmid:11526384 ↵ T. Icenogle, COVID-19: Infection or Autoimmunity. Front. Immunol. 11, 2055 (2020). doi:10.3389/fimmu.2020.02055pmid:33042116OpenUrlCrossRefPubMed ↵ M. Ehrenfeld, A. Tincani, L. Andreoli, M. Cattalini, A. Greenbaum, D. Kanduc, J. Alijotas-Reig, V. Zinserling, N. Semenova, H. Amital, Y. Shoenfeld, Covid-19 and autoimmunity. Autoimmun. Rev. 19, 102597 (2020). doi:10.1016/j.autrev.2020.102597pmid:32535093OpenUrlCrossRefPubMed ↵ A. Boucher, M. Desforges, P. Duquette, P. J. Talbot, Long-term human coronavirus-myelin cross-reactive T-cell clones derived from multiple sclerosis patients. Clin. Immunol. 123, 258–267 (2007). doi:10.1016/j.clim.2007.02.002pmid:17448727 ↵ P. Correale, L. Mutti, F. Pentimalli, G. Baglio, R. E. Saladino, P. Sileri, A. Giordano, HLA-B*44 and C*01 Prevalence Correlates with Covid19 Spreading across Italy. Int. J. Mol. Sci. 21, 5205 (2020). doi:10.3390/ijms21155205pmid:32717807OpenUrlCrossRefPubMed ↵ A. Nguyen, J. K. David, S. K. Maden, M. A. Wood, B. R. Weeder, A. Nellore, R. F. Thompson, Human Leukocyte Antigen Susceptibility Map for Severe Acute Respiratory Syndrome Coronavirus 2. J. Virol. 94, e00510-20 (2020). doi:10.1128/JVI.00510-20pmid:32303592 ↵ F. Krammer, SARS-CoV-2 vaccines in development. Nature 586, 516–527 (2020). doi:10.1038/s41586-020-2798-3pmid:32967006OpenUrlCrossRefPubMed ↵ M. Jeyanathan, S. Afkhami, F. Smaill, M. S. Miller, B. D. Lichty, Z. Xing, Immunological considerations for COVID-19 vaccine strategies. Nat. Rev. Immunol. 20, 615–632 (2020). doi:10.1038/s41577-020-00434-6pmid:32887954OpenUrlCrossRefPubMed ↵ U. Sahin, A. Muik, E. Derhovanessian, I. Vogler, L. M. Kranz, M. Vormehr, A. Baum, K. Pascal, J. Quandt, D. Maurus, S. Brachtendorf, V. Lörks, J. Sikorski, R. Hilker, D. Becker, A.-K. Eller, J. Grützner, C. Boesler, C. Rosenbaum, M.-C. Kühnle, U. Luxemburger, A. Kemmer-Brück, D. Langer, M. Bexon, S. Bolte, K. Karikó, T. Palanche, B. Fischer, A. Schultz, P.-Y. Shi, C. Fontes-Garfias, J. L. Perez, K. A. Swanson, J. Loschko, I. L. Scully, M. Cutler, W. Kalina, C. A. Kyratsous, D. Cooper, P. R. Dormitzer, K. U. Jansen, Ö. Türeci, COVID-19 vaccine BNT162b1 elicits human antibody and TH1 T cell responses. Nature 586, 594–599 (2020). doi:10.1038/s41586-020-2814-7pmid:32998157OpenUrlCrossRefPubMed ↵ L. A. Jackson, E. J. Anderson, N. G. Rouphael, P. C. Roberts, M. Makhene, R. N. Coler, M. P. McCullough, J. D. Chappell, M. R. Denison, L. J. Stevens, A. J. Pruijssers, A. McDermott, B. Flach, N. A. Doria-Rose, K. S. Corbett, K. M. Morabito, S. O’Dell, S. D. Schmidt, P. A. Swanson 2nd., M. Padilla, J. R. Mascola, K. M. Neuzil, H. Bennett, W. Sun, E. Peters, M. Makowski, J. Albert, K. Cross, W. Buchanan, R. Pikaart-Tautges, J. E. Ledgerwood, B. S. Graham, J. H. Beigel; mRNA-1273 Study Group, An mRNA Vaccine against SARS-CoV-2 - Preliminary Report. N. Engl. J. Med. 383, 1920–1931 (2020). doi:10.1056/NEJMoa2022483pmid:32663912OpenUrlCrossRefPubMed ↵ N. Pardi, M. J. Hogan, M. S. Naradikian, K. Parkhouse, D. W. Cain, L. Jones, M. A. Moody, H. P. Verkerke, A. Myles, E. Willis, C. C. LaBranche, D. C. Montefiori, J. L. Lobby, K. O. Saunders, H.-X. Liao, B. T. Korber, L. L. Sutherland, R. M. Scearce, P. T. Hraber, I. Tombácz, H. Muramatsu, H. Ni, D. A. Balikov, C. Li, B. L. Mui, Y. K. Tam, F. Krammer, K. Karikó, P. Polacino, L. C. Eisenlohr, T. D. Madden, M. J. Hope, M. G. Lewis, K. K. Lee, S.-L. Hu, S. E. Hensley, M. P. Cancro, B. F. Haynes, D. Weissman, Nucleoside-modified mRNA vaccines induce potent T follicular helper and germinal center B cell responses. J. Exp. Med. 215, 1571–1588 (2018). doi:10.1084/jem.20171450pmid:29739835 Acknowledgments: Funding. A.C.K. was supported by the Swedish Research Council, the Karolinska Institutet, and The Center for Innovative Medicine. M.B. was supported by the Swedish Research Council, the Karolinska Institutet, the Jeansson Stiftelse, the Åke Wibergs Stiftelse, the Swedish Society of Medicine, the Swedish Cancer Society, the Magnus Bergvalls Stiftelse, the Lars Hiertas Stiftelse, the Swedish Physician against AIDS Foundation, the Jonas Söderquist Stiftelse, and the Clas Groschinskys Minnesfond. Author contributions: A.C.K., M.H. and M.B. contributed to writing and drafting the illustration. A.C.K. and M.B. edited the manuscript. Competing Interests. The authors declare that they have no competing interests. Copyright © 2020, American Association for the Advancement of Science
Scoop.it!

A provocative study suggests that certain colds may leave antibodies against the new coronavirus, perhaps explaining why children are more protected than adults. It’s been a big puzzle of the pandemic: Why are children so much less likely than adults to become infected with the new coronavirus and, if infected, less likely to become ill? A possible reason may be that many children already have antibodies to other coronaviruses, according to researchers at the Francis Crick Institute in London. About one in five of the colds that plague children are caused by viruses in this family. Antibodies to those viruses may also block SARS-CoV-2, the new coronavirus causing the pandemic. In a study published Friday in Science, the group, led by George Kassiotis, who heads the Retroviral Immunology Laboratory at the institute, reports that on average only 5 percent of adults had these antibodies, but 43 percent of children did.
Researchers who did not participate in the study were intrigued by the finding. H. Benjamin Larman, an immunologist at Johns Hopkins School of Medicine, called it a “well-done study that puts forward a compelling theory which is supported by their data.” Stephen J. Elledge, a genetics professor at Harvard Medical School and Brigham and Women’s Hospital, had a similar response. He and others have found many people have antibodies to common colds caused by other coronaviruses; in laboratory studies, these antibodies also block the new coronavirus. In March, as the pandemic was just beginning, Dr. Kassiotis and his colleagues decided to develop a highly sensitive antibody test. To assess it, they examined blood samples taken before the pandemic from over 300 adults and 48 children and adolescents, comparing them with samples from more than 170 people who had been infected with the new coronavirus. The scientists expected samples taken before the pandemic to have no antibodies that attacked the new coronavirus. Those were to be the controls for the test the scientists were developing. Instead, they found that many children, and some adults, carried one antibody in particular that can prevent coronaviruses, including the new one, from entering cells. This antibody attaches itself to a spike that pokes out of coronaviruses. While the tip of the spike is unique to the new coronavirus, the base is found in all coronaviruses, Dr. Kassiotis said. In lab tests, antibodies to the base of the spike prevented the new coronavirus from entering cells in order to reproduce.
Now the researchers are planning to expand their study to monitor thousands of children and adults. Some have antibodies that can block the new coronavirus in lab tests. Others do not. “If they have the pandemic strain, are they protected?” Dr. Kassiotis asked. Will they get sick, he wondered, or will the infection be all but undetectable? Dr. Elledge and his colleagues at Harvard developed their own highly specific, sensitive and exhaustive antibody test, VirScan. It is able to detect a diverse collection of antibodies with that are directed at any of more than 800 places on the new coronavirus, including the antibody that Dr. Kassiotis and his colleagues studied. After examining blood taken from 190 people before the pandemic emerged, Dr. Elledge and his colleagues concluded that many already had antibodies, including the one targeting the base of the spike — presumably from infections with related coronaviruses that cause colds...
Cited study published in Science (Nov. 6, 2020): Via Juan Lama

Dennis Zelaya's curator insight,
November 18, 2020 1:51 PM
Kids are less likely to develop Covid than adults. Kids are naturally fighting against more colds a year than adults, who may only get a cold once or twice a year. This leaves more antibodies in kids than it does adults. Which helps prevent contracting Covid and fighting off the infection itself. I've also noticed that when parents would get infected with Covid, their kids would test negative even after being in contact with them. Kids may play a big part in finding the cure for Covid.
Scoop.it!

The development of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) vaccines and therapeutics will depend on understanding viral immunity.We studied T cell memory in 42 patients following recovery from COVID-19 (28 with mild disease and 14 with severe disease) and 16 unexposed donors,...
Scoop.it!
Clinical MedicineCOVID-19 Open Access | 10.1172/jci.insight.142167 High levels of SARS-CoV-2–specific T cells with restricted functionality in severe courses of COVID-19 David Schub,1 Verena Klemis,1 Sophie Schneitler,2 Janine Mihm,3 Philipp M. Lepper,4 Heinrike Wilkens,4 Robert Bals,4 Hermann Eichler,5 Barbara C. Gärtner,2 Sören L. Becker,2 Urban Sester,3 Martina Sester,1 and Tina Schmidt1 First published September 16, 2020 - More info Abstract BACKGROUND. Patients infected with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) differ in the severity of disease. We hypothesized that characteristics of SARS-CoV-2–specific immunity correlate with disease severity. METHODS. In this study, SARS-CoV-2–specific T cells and antibodies were characterized in uninfected controls and patients with different coronavirus disease 2019 (COVID-19) disease severity. SARS-CoV-2–specific T cells were flow cytometrically quantified after stimulation with SARS-CoV-2 peptide pools and analyzed for expression of cytokines (IFN-γ, IL-2, and TNF-α) and markers for activation, proliferation, and functional anergy. SARS-CoV-2–specific IgG and IgA antibodies were quantified using ELISA. Moreover, global characteristics of lymphocyte subpopulations were compared between patient groups and uninfected controls. RESULTS. Despite severe lymphopenia affecting all major lymphocyte subpopulations, patients with severe disease mounted significantly higher levels of SARS-CoV-2–specific T cells as compared with convalescent individuals. SARS-CoV-2–specific CD4+ T cells dominated over CD8+ T cells and closely correlated with the number of plasmablasts and SARS-CoV-2–specific IgA and IgG levels. Unlike in convalescent patients, SARS-CoV-2–specific T cells in patients with severe disease showed marked alterations in phenotypical and functional properties, which also extended to CD4+ and CD8+ T cells in general. CONCLUSION. Given the strong induction of specific immunity to control viral replication in patients with severe disease, the functionally altered characteristics may result from the need for contraction of specific and general immunity to counteract excessive immunopathology in the lung. FUNDING. The study was supported by institutional funds to MS and in part by grants of Saarland University, the State of Saarland, and the Rolf M. Schwiete Stiftung. Introduction Coronavirus disease 2019 (COVID-19), the disease caused by severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), can be asymptomatic or mild but also includes severe disease manifestations, such as acute respiratory distress syndrome, which can lead to multi-organ failure and death despite intensive medical treatment. The mortality rate is particularly high in older individuals and in patients with preexisting lung, heart, or immunodeficiency diseases (1, 2). Studies have shown that SARS-CoV-2 infection causes global changes in cellular immunity, mainly characterized by lymphopenia, skewed distribution of T cell subpopulations, and high plasma concentrations of proinflammatory cytokines (2, 3). In addition, T cell functionality appears to be altered as shown by impaired expression of IFN-γ (4–6). So far, mainly nonspecific general changes in the number and functionality of blood cells have been described, whereas specific T cell immunity directed against SARS-CoV-2 has as yet not been studied as extensively (7–11), especially in patients with different disease severity. It seems reasonable to suggest that the individual course of a SARS-CoV-2 infection depends on the induction and functionality of the adaptive immunity including both antibodies and T cells. Seroconversion in patients with COVID-19 does not seem to be delayed, because SARS-CoV-2–specific IgM and IgA antibodies are induced early after the onset of symptoms after a median of 5 days, while the median time for IgG seroconversion is 14 days (12–14). Thus far, it remains to be elucidated whether patients with different disease manifestations differ in the levels and functionality of SARS-CoV-2–specific T cells or antibodies. We have previously shown that symptomatic infections with persistent pathogens are associated with alterations in pathogen-specific T cell levels and impaired functionality as compared with individuals with successful immune control (15–20). Based on these observations, we hypothesized that T cells induced against SARS-CoV-2 may differ in quantity and functionality depending on the severity of symptoms of COVID-19. Moreover, we hypothesized that antigen-specific T cell characteristics may affect B cell subpopulations and SARS-CoV-2–specific antibodies. We therefore recruited 2 groups of patients who were similar in the time elapsed since onset of clinical symptoms. One group included hospitalized patients with a severe course of disease, whereas a second group comprised convalescent individuals who had mild disease manifestations and who completely recovered from SARS-CoV-2–related symptoms mainly in an outpatient setting. Results Study population. In this study, 50 patients with COVID-19 were included at a median of 42.5 (IQR 16.5) days after onset of symptoms. Among those, 14 were critically ill patients (64.3 ± 8.2 years) hospitalized in the intensive care unit (“ICU patients”), whereas 36 individuals (42.2 ± 13.6 years) had recovered from COVID-19 in an outpatient setting (“convalescent patients”) with no or mild remaining symptoms at the time of analysis: cough (n = 3), rhinitis (n = 2), myalgia (n = 2), and anosmia (n = 7). Both groups did not differ in the median time after onset of symptoms at the time of analysis (ICU patients: 40.0 [IQR 15.0] days; convalescent patients: 43.5 [IQR 16.5]) days; P = 0.37). Ten individuals without evidence for SARS-CoV-2 infection were recruited as negative controls (48.1 ± 11.4 years). The demographic and clinical characteristics of patients and controls are shown in Table 1. As expected, ICU patients were significantly older as compared with the other groups (P < 0.0001). Cardiovascular disease (10/14 ICU patients) and metabolic diseases (7/14 ICU patients, especially obesity) were the most common comorbidities in ICU patients. Median time from symptom onset to hospital admission was 5 (IQR 5.5) days and 7 (IQR 6) days to ICU admission. Eleven patients were mechanically ventilated, of which 7 were additionally treated with extracorporeal membrane oxygenation, and 7 received renal replacement therapy. Therapeutic drug regimens included hydroxychloroquine and azithromycin in 11 cases, 1 patient received tocilizumab, 1 patient received icatibant, and 2 patients underwent a 3-day course of high-dose steroid treatment. Viral load determinations were not performed for all patients on a regular schedule. Information on the duration of viral encounter was given in 8 patients, where at least 2 subsequent test results documented a median of up to 19.5 days (range 6–34 days) of continuous PCR positivity. Three patients died 8, 15, and 16 days after analysis, of which 1 still was SARS-CoV-2 PCR positive. Twelve out of 14 ICU patients became SARS-CoV-2 PCR negative during the hospital stay, with 11 patients known to have a first negative test result at least 8 days before the blood sampling (median 9 days; range 8–28 days). PCR results on follow-up were not available for 1 patient who was readmitted to the primary care hospital after the end of mechanical ventilation and clinical stabilization. SARS-CoV-2 PCR was performed in 33/36 convalescent patients after quarantine, and all tests were negative. Table 1 Demographic and clinical characteristics of the study population Altered counts of leukocytes and lymphocyte subpopulations in patients with severe COVID-19. Leukocyte numbers and differential white blood cell counts showed substantial differences between ICU patients and convalescent individuals, with increased levels of neutrophils and severe lymphopenia as the most prominent findings (Table 1). In contrast, convalescent individuals had similar levels as controls (Table 1). A more detailed analysis of lymphocytes and their subpopulations was performed from whole blood using flow cytometry. Absolute cell counts were calculated based on differential blood counts. As shown in Figure 1, lymphopenia affected all major lymphocyte subpopulations, such as NK cells, B cells, and T cells, including CD4+ and CD8+ T cells and Tregs. Figure 1 Reduced counts of lymphocytes and lymphocyte subpopulations in patients with severe COVID-19. Absolute cell numbers per microliter whole blood of lymphocytes and lymphocyte subpopulations were calculated in SARS-CoV-2–negative individuals (n = 10), patients with severe COVID-19 (n = 14), and convalescent patients (n = 21) based on flow cytometry and differential blood counts. Flow cytometry data were obtained from all convalescent patients, but 15/36 had to be excluded because no differential blood count was available. Natural killer (NK) cells were defined as CD3−CD16+/CD56+, B cells as CD19+, T cells as CD3+, CD4+ and CD8+ T cells as CD4+CD8− and CD8+CD4− T cells, and regulatory T cells (Tregs) as CD4+CD25hiCD127lo within lymphocytes, respectively. Bars represent medians with IQRs. Differences between the groups were calculated using Kruskal-Wallis test and Dunn’s posttest. **P < 0.01, ***P < 0.001, ****P < 0.0001. Significantly higher percentages of SARS-CoV-2–specific T cells in patients with severe COVID-19. To identify specific immunity against SARS-CoV-2, whole-blood samples were stimulated with overlapping peptide pools covering the major SARS-CoV-2 structural spike protein (spike N and C-terminal peptide sets, respectively), the nucleocapsid (NCAP) protein, the membrane protein VME1, and the envelope small membrane protein VEMP. Stimulation was carried out for 6 hours, and antigen-specific T cells were identified by intracellular staining of cytokines (IFN-γ, IL-2, and TNF-α) among activated CD69+ CD4+ and CD8+ T cells. Stimulation with Staphylococcus aureus enterotoxin B (SEB) allowed assessment of polyclonal T cell responses. DMSO was used to control for background reactivity, which was subtracted from specific stimulations. To characterize response patterns of stimulation-induced CD4+ and CD8+ T cells toward the various peptide pools, we first focused on IFN-γ+ T cells because IFN-γ is the most specific and readily induced in T cells toward a variety of clinically relevant pathogens (16, 17, 21). A typical set of contour plots from a hospitalized patient illustrating induction of SARS-CoV-2–specific T cell reactivity among CD4+ and CD8+ T cells is shown in Figure 2A. When analyzing all individuals, CD4+ T cell frequencies were highest after stimulation with spike N and VME1, followed by spike C and NCAP, whereas reactivity toward the smallest protein, VEMP, was largely absent. Antigen-specific CD8+ T cell levels were generally lower, with the most pronounced reactivity after stimulation with spike N and NCAP. In contrast, spike C, VME1, or VEMP elicited only modest or no reactivity with no difference between infected and noninfected groups (Figure 2B). When comparing antigen reactivity in the 3 groups, significantly higher levels of SARS-CoV-2–specific CD4+ T cells were found in both infected patient groups as compared with negative controls, who were largely nonresponsive (Figure 2B). A difference between infected and noninfected individuals was also observed for CD8+ T cells reacting toward spike N or NCAP, whereas CD8+ T cell reactivity toward the remaining peptide pools was equally low in both infected and noninfected groups (Figure 2B). Interestingly, among convalescent patients, individuals with lower respiratory symptoms, such as cough or dyspnea (n = 19), had significantly higher median levels of SARS-CoV-2–specific CD4+ T cells (0.16%, IQR 0.17%) than individuals without these symptoms (n = 17; 0.08%, IQR 0.127%; P = 0.015; data not shown). Figure 2 Increased percentages of SARS-CoV-2–specific T cells in patients with severe COVID-19. Whole-blood samples were stimulated with overlapping peptide pools spanning the SARS-CoV-2 spike protein (spike N, N-terminal; spike C, C-terminal), the NCAP protein, the membrane protein VME1, and the envelope small membrane protein VEMP. Stimulations with DMSO and SEB served as negative controls and polyclonal stimulus, respectively. (A) Contour plots illustrating specific immunity from a 56-year-old hospitalized patient are shown. Numbers indicate percentage of reactive (CD69+IFN-γ+) cells within total CD4+ and CD8+ T cells. (B) Percentages of CD4+ and CD8+ T cells specific for the different SARS-CoV-2 antigens were compared between SARS-CoV-2–negative individuals (negative, n = 10), patients with severe COVID-19 (ICU, n = 14), and convalescent patients (n = 36). (C) Total percentages of SARS-CoV-2–specific (CD69+IFN-γ+) T cells, determined by the sum of frequencies toward the individual peptide pools for each individual, and SEB-reactive T cell frequencies are compared between the 3 groups. Bars represent medians with IQRs. Differences between the groups were calculated using Kruskal-Wallis test and Dunn’s posttest. *P < 0.05, **P < 0.01, ***P < 0.001, ****P < 0.0001. To obtain an estimate of the total levels of SARS-CoV-2–specific T cells in each group, SARS-CoV-2–specific T cell frequencies toward the individual peptide pools were added up for each individual (Figure 2C). This showed that patients with a severe course had the highest levels of SARS-CoV-2–specific CD4+ T cells (0.48%, IQR 0.37%), which not only differed from negative controls (0.01%, IQR 0.01%) but also differed from convalescent individuals (0.13%, IQR 0.18%; P < 0.0001). This contrasts with polyclonal SEB-reactive CD4+ T cell frequencies, which were significantly lower in ICU patients (1.77%, IQR 1.76%) as compared with controls (3.97%, IQR 2.15%) or convalescent patients (5.06%, IQR 5.07%, P = 0.0001, Figure 2C). Likewise, total levels of SARS-CoV-2–specific CD8+ T cells were significantly higher in patients than in noninfected controls (P = 0.023), whereas the difference between ICU patients and convalescent patients did not reach statistical significance. Unlike in CD4+ T cells, SEB-reactive CD8+ T cell levels were similar among the 3 groups (P = 0.244). SARS-CoV-2–specific CD8+ T cell levels inversely correlated with time since onset of clinical symptoms (r = –0.37, P = 0.01), whereas this was not significant for specific CD4+ T cells (P = 0.1; Supplemental Figure 1; supplemental material available online with this article; https://doi.org/10.1172/jci.insight.142167DS1). Taken together, despite strong lymphopenia affecting both CD4+ and CD8+ T cells, and lower levels of polyclonal SEB-reactive CD4+ T cells, patients with severe COVID-19 were capable of mounting high levels of SARS-CoV-2–specific T cells. Restricted functionality of SARS-CoV-2–specific CD4+ T cells in patients with a severe course of COVID-19. To characterize the functionality of SARS-CoV-2–specific T cells in more detail, their cytokine expression profile regarding IFN-γ, IL-2, and TNF-α was analyzed using flow cytometry. Representative contour plots showing cytokine expression profiles after stimulation with the antigens are shown in Supplemental Figure 2. Boolean gating of activated CD69+ T cells resulted in assessment of 7 subpopulations of cells producing all 3 cytokines, 2 cytokines, or 1 cytokine only. As with results shown from IFN-γ+ subpopulations (Figure 2C), the total percentage of SARS-CoV-2–specific CD4+ T cells producing any of the 3 cytokines was also highest among ICU patients (P < 0.0001), with a trend also observed for specific CD8+ T cells (P = 0.055, Supplemental Figure 3). We then further characterized SARS-CoV-2–reactive CD4+ T cells for their cytokine expression profiles. All cytokine-positive cells were set to 100% in each individual and assessed for distribution of the 7 subpopulations. As shown in Figure 3A, the percentage of multifunctional, SARS-CoV-2–specific CD4+ T cells with the ability to simultaneously produce all 3 cytokines was significantly lower in patients with severe courses as compared with convalescent individuals. This was associated with a concomitant higher expression of cells simultaneously producing IL-2 and TNF-α. The same analysis was performed for cytokine-positive SEB-reactive CD4+ T cells. Both their magnitude (Supplemental Figure 3) and their cytokine profile were different from those of SARS-CoV-2–specific cells. Nevertheless, the SEB-reactive and SARS-CoV-2–specific cytokine profiles exhibited similar differences between patients with severe disease and convalescent individuals (Figure 3A). In addition, the cytokine expression profile of SEB-reactive CD4+ T cells in convalescent individuals did not differ from SARS-CoV-2–noninfected controls (data not shown). This indicates that patients with severe disease have a restricted cytokine expression profile with lower percentages of multifunctional cells simultaneously producing all 3 cytokines. Unlike in convalescent patients, this restricted expression profile also extends to polyclonal T cells in general. Figure 3 Altered cytokine profiles and characteristics of SARS-CoV-2–specific T cells in patients with a severe course of COVID-19. Expression patterns of SARS-CoV-2–specific T cells were determined from combined T cells reacting to the individual peptide pools for each individual. (A) SARS-CoV-2–specific and SEB-reactive CD4+ T cells were divided into 7 subpopulations according to their expression of the cytokines IFN-γ, IL-2, and TNF-α. Distribution of these subgroups was compared between ICU patients and convalescent patients. To ensure robust statistical analysis, cytokine profiling was restricted to CD4+ T cells and to all samples with at least 35 measurable CD69+IFN-γ+ cells (all ICU patients and 20 convalescent patients). (B) CTLA-4 expression of SARS-CoV-2–specific and SEB-reactive CD4+ and CD8+ T cells was compared between ICU patients and convalescent patients. Analysis was restricted to individuals with sufficient SARS-CoV-2–specific immunity, i.e., where the total number of measurable CD69+IFN-γ+ cells reached at least 20 cells (n = 13 and 3 ICU patients and 17 and 18 convalescent patients for CD4+ and CD8+ T cells, respectively). (C) In a subgroup of 10 patient samples (5 ICU patients and 5 convalescent patients), where a larger sample volume for in vitro stimulations was available, expression of PD-1, Ki67, and granzyme B of SARS-CoV-2–specific and SEB-reactive CD4+ and CD8+ T cells was analyzed. Overlaid contour plots (built using BD FACSDiva 8) of samples from a 31-year-old convalescent patient stimulated with SARS-CoV-2 antigens are shown in the upper panel. PD-1 MFI was analyzed from all stimulatory reactions with at least 20 CD69+IFN-γ+ cells (n = 8 and 4 for CD4+ and CD8+ T cells, respectively). Analysis of intranuclear presence of Ki67 (%Ki67+) and expression of granzyme B (%granzyme B+) was restricted to samples with at least 20 specific CD4+ (n = 8 for SARS-CoV-2 and n = 7 for SEB) or CD8+ T cells (n = 4), respectively. ICU patients are depicted by dark symbols and convalescent patients by light symbols. Bar charts in A represent mean and SD, and differences between the 2 groups were assessed using unpaired 2-tailed t test. Bars in B and C represent medians with IQRs. Differences between the groups were calculated using Mann-Whitney U test. *P < 0.05, **P < 0.01, ***P < 0.001, ****P < 0.0001. MFI, median fluorescence intensity. We also analyzed expression of cytotoxic T lymphocyte antigen 4 (CTLA-4) on SARS-CoV-2–specific and SEB-reactive T cells as phenotypical correlates of altered functionality commonly observed during active infections. This showed that SARS-CoV-2–specific CD4+ T cells from ICU patients had significantly higher expression levels of CTLA-4 than from convalescent patients (P = 0.035), which also held true for SEB-reactive CD4+ T cells (P < 0.0001, Figure 3B). Although the total number of patients with measurable SARS-CoV-2–reactive CD8+ T cells was lower, a similar trend was found for SARS-CoV-2–reactive or SEB-reactive CD8+ T cells (Figure 3B). Finally, a subset of 10 SARS-CoV-2–infected patients (5 hospitalized, 5 convalescent patients) was studied to further characterize SARS-CoV-2–specific CD4+ and CD8+ T cells for expression of programmed cell death 1 (PD-1), Ki67, and granzyme B, with contour plots shown in Figure 3C. This analysis was restricted to samples with sufficient amounts of detectable SARS-CoV-2–specific T cells. PD-1 expression levels and the percentage of Ki67+ cells were higher on SARS-CoV-2–specific CD4+ T cells than on polyclonal SEB-reactive CD4+ T cells. Likewise, although the number of individuals with sufficient numbers of SARS-CoV-2–specific CD8+ T cells was lower, some individuals had Ki67-expressing CD8+ T cells; a large fraction of SARS-CoV-2–specific CD8+ T cells expressed granzyme B, which was lower among SEB-reactive T cells (Figure 3C). Altered characteristics of global CD4+ and CD8+ T cells in patients with severe COVID-19. Because cytokine expression patterns and CTLA-4 expression in patients with severe courses were altered in both SARS-CoV-2–specific and SEB-reactive T cells, these alterations may also extend to T cells in general. To analyze bulk T cells in more detail, expression of CTLA-4 and PD-1, as well as Ki67+ cells, were analyzed directly from whole blood without prior stimulation, with representative contour plots shown in Figure 4A. As shown from MFIs in Figure 4B, both CD4+ and CD8+ T cells from ICU patients showed markedly increased expression of CTLA-4 and PD-1 as compared with controls, whereas respective expression in convalescent individuals was lower and similar to in controls. The same conclusion was reached if the percentage of CTLA-4– or PD-1–expressing cells was analyzed (Supplemental Figure 4). Interestingly, the percentage of recently proliferated Ki67+ CD4+ and CD8+ T cells was significantly higher in patients with a severe course as compared with controls and convalescent individuals. Figure 4 Altered characteristics of global CD4+ and CD8+ T cells in patients with severe COVID-19. (A) Representative contour plots showing expression of CTLA-4 and PD-1 and intranuclear Ki67 expression of unstimulated total CD4+ and CD8+ T cells from an ICU patient and a convalescent individual. Because cells showed a continuum in the expression of CTLA-4 and PD-1, cell surface expression levels of CTLA-4 and PD-1 were expressed as MFI. Numbers indicate expression levels (MFI) of CTLA-4 and PD-1 and percentage of Ki67+ cells among total CD4+ and CD8+ T cells. (B) Results were compared among SARS-CoV-2–negative individuals (negative, n = 10), patients with severe COVID-19 (ICU, n = 14), and convalescent patients (n = 36). Bars represent medians with IQRs. Differences between the groups were calculated using Kruskal-Wallis test and Dunn’s posttest. *P < 0.05, **P < 0.01, ***P < 0.001, ****P < 0.0001. Strong correlation of SARS-CoV-2–specific CD4+ T cell levels with specific IgG and IgA antibodies and plasmablasts. To comparatively analyze cellular and humoral immunity against SARS-CoV-2, specific IgA and IgG antibodies were determined using ELISA. As shown in Figure 5A, all individuals with severe courses were positive for SARS-CoV-2–specific IgG and IgA. Interestingly, their levels were significantly higher than those of convalescent individuals, among whom only 83% (30/36 patients) had positive IgG and 69% (25/36 patients) had IgA above the detection limit. Intermediate IgA and IgG titers were found in 2 individuals each. SARS-CoV-2–negative controls did not show any specific IgG or IgA. In line with the role of CD4+ T cells in providing help for induction of humoral immunity, the percentage of SARS-CoV-2–specific CD4+ T cells showed a significant correlation with both specific IgG (r = 0.77, P < 0.0001) and IgA antibodies (r = 0.67, P < 0.0001), whereas no correlation was observed with specific CD8+ T cells (P = 0.78 for IgG; P = 0.52 for IgA, Figure 5B). To elucidate whether the observed differences in specific antibody levels were related to differences in B cells among the groups, we analyzed CD19+ B cell subpopulations by their expression of IgD and CD27, with contour plots of a 64-year-old hospitalized patient shown in Figure 5C. As with B cell lymphopenia in general (Figure 1), the numbers of naive (IgD+CD27–), non-switched memory (IgD+CD27+), and switched memory B cells (IgD–CD27+) were significantly lower in patients with a severe course (Figure 5C). Interestingly, however, the number of plasmablasts, which were identified as CD38+ switched memory B cells, was significantly higher than in controls or convalescent patients. In line with the central role of plasmablasts in initiating antibody production, their numbers showed a strong correlation with both IgG (r = 0.53, P = 0.0014) and IgA antibody levels (r = 0.54, P = 0.0013, Figure 5D). Figure 5 Strong correlation of SARS-CoV-2–specific CD4+ T cell levels with specific IgG and IgA antibodies and plasmablasts. (A) Levels of SARS-CoV-2–specific IgG and IgA were compared among SARS-CoV-2–negative individuals (negative, n = 10), patients with severe COVID-19 (ICU, n = 14), and convalescent patients (n = 36). (B) Correlation between levels of SARS-CoV-2–specific IgG or IgA with frequencies of SARS-CoV-2–specific CD69+IFN-γ+ CD4+ or CD8+ T cells expressed in patients with SARS-CoV-2. (C) Representative contour plots of a 64-year-old hospitalized patient showing the differentiation status of B cells characterized by surface expression of IgD and CD27, with plasmablasts identified among switched memory B cells by additional staining of CD38. Numbers of B cell subpopulations and plasmablasts were compared between groups, and (D) plasmablasts were correlated with levels of SARS-CoV-2–specific IgG and IgA. Antibody levels were determined semiquantitatively by dividing the optical density of an individual sample by that of a positive control serum. Bars in A and C represent medians with IQRs. Differences between the groups were calculated using Kruskal-Wallis test and Dunn’s posttest. *P < 0.05, **P < 0.01, ***P < 0.001, ****P < 0.0001. Correlations in B and D were analyzed according to Spearman. Dotted lines indicate detection limits for IgG and IgA, indicating negative, intermediate, and positive levels, respectively, as per manufacturer’s instructions. Discussion Manifestation of SARS-CoV-2 infections may range from asymptomatic infections or mild symptoms to severe courses of disease with a high risk of fatal outcome (2). In this study, we show that SARS-CoV-2–specific immunological characteristics in patients with a severe course are clearly distinct from infected individuals who recovered from mild disease that could be managed in an outpatient setting. Both groups were analyzed at the same time after onset of COVID-19 symptoms. As main findings, we show that patients with severe disease had high levels of SARS-CoV-2–specific CD4+ and CD8+ T cells as well as high titers of specific IgG and IgA antibodies as compared with convalescent individuals, where levels were significantly lower. However, SARS-CoV-2–specific T cells in severe cases had a restricted cytokine expression profile with fewer multifunctional cells and strongly expressed CTLA-4 as a hallmark of T cells in the contraction phase of an immune response after active encounter with the virus. In contrast, convalescent individuals who had recovered from mild or moderate disease had lower levels of SARS-CoV-2–specific humoral and cellular immunity, and antigen-specific T cells showed fewer signs of functional alterations. Finally, differences between the infected patient groups were also found for major lymphocyte subpopulations, such as B cells, NK cells, Tregs, and CD4+ and CD8+ T cells. Apart from severe lymphopenia, CD4+ and CD8+ T cells from patients with severe COVID-19 exhibited increased expression of CTLA-4 and PD-1 and a high expression of Ki67 as a marker for recent proliferation. In addition, the percentage of cells responding after polyclonal stimulation was lower and restricted in functionality. In contrast, lymphocyte characteristics from convalescent individuals were similar as in noninfected controls. Taken together, this indicates that the severity of clinical disease in patients with COVID-19 is not only associated with prominent changes in the innate immune system but also characterized by a marked alteration of adaptive humoral and cellular immunity that includes both SARS-CoV-2–specific and global T cell function. Up to now, only few studies have described SARS-CoV-2–specific T cells in patients with COVID-19 (7–11, 22). With results from our study, key characteristics of SARS-CoV-2–specific T cells emerge. SARS-CoV-2–reactive T cells exhibit immediate effector function with proliferative potential, and expression of IFN-γ, IL-2, and TNF-α, which suggests a Th1 phenotype. This is supported by results from supernatants of stimulated peripheral blood mononuclear cells showing detectable IFN-γ, IL-2, and TNF-α and low levels of IL-5, IL-13, IL-9, IL-10, and IL-22 (7, 11). Reactive T cells exist among both CD4+ and CD8+ T cells, and CD8+ T cells were able to produce effector molecules such as granzyme B, and evidence of perforin and CD107a expression was recently found (10). In line with other reports (8, 10, 11), SARS-CoV-2–specific CD4+ T cell levels were higher than those of CD8+ T cells. Unlike CD4+ T cells, specific CD8+ T cell levels inversely correlated with time after onset of symptoms, which may reflect higher stability of CD4+ T cells. Alternatively, antigen-specific CD8+ T cells might have been recruited to the lungs as the site of massive SARS-CoV-2 replication because signatures for clonally expanded CD8+ T cells were found in bronchoalveolar lavage samples of patients with SARS-CoV-2–associated lung disease (23). Previous studies show that SARS-CoV-2–specific T cell levels differ in infected and noninfected individuals (7–11, 22). Our results suggest that SARS-CoV-2–specific CD4+ T cells allowed for a better distinction not only of noninfected and infected individuals but also of patients with different severity of disease. This distinction may further be improved using immunodominant peptides for stimulation. So far, a relative immunodominance of the spike protein has been described (8, 11, 22). This was also observed in our study, but the 4 viral structural proteins differed in their ability to induce specific immunity among CD4+ and CD8+ T cells. The VEMP protein elicited hardly any reactivity, which may be related to its small size and its relatively low abundance in the virus particle (24). Reactive CD4+ T cells were found toward all other proteins with a dominance of the spike and the VME1 proteins. Interestingly, apart from the N-terminal portion of the spike protein, CD8+ T cells showed pronounced reactivity toward the NCAP protein. NCAP may be more readily processed to be presented in MHC class I molecules because of its predominant localization in the cytoplasm, whereas all other membrane proteins are directly assembled in the ER membrane (25). It was striking that patients with severe courses of disease had significantly higher levels of both SARS-CoV-2–specific antibodies and T cells as compared with convalescent patients, which is in line with recent observations (10). Because all analyses were performed in a short time frame after onset of symptoms, we consider it unlikely that antibody and T cell levels in convalescent individuals had been similarly high during active viral replication and had decreased after successful control of infection. Instead, the levels of specific humoral and cellular immunity needed to control viral replication may be directly related to the viral load during primary infection. Thus, patients with a severe course may have required induction of higher levels of specific immunity. Whether this may be due to potentially higher viral load or prolonged periods of active viral replication needs further study with regular sampling. So far it is known that infection efficiency is high in nasal epithelial cells of the upper airways and decreases in epithelial cells of the lower respiratory tract along an angiotensin converting enzyme 2 receptor gradient (26). Therefore, viral replication may remain restricted to the upper airway in the majority of infected individuals with mild symptoms. Further seeding of virus to the lung may be favored by high viral load in the upper airways with subsequent microaspiration events that are more frequent in patients at risk for severe courses of COVID-19, such as elderly people or individuals with diabetes or obesity. Thus, lower viral load with local restriction to the upper airways may require less pronounced specific immunity as compared with higher viral load and/or further dissemination of the virus to the lower respiratory tract. This may be supported by our observation that SARS-CoV-2–specific CD4+ T cell levels showed significant differences among convalescent individuals with or without symptoms of the lower respiratory tract (cough and dyspnea) (P = 0.015). The induction of specific immunity may further be modulated by preexisting cross-reactive immunity against common cold coronaviruses. This is illustrated by influenza vaccine studies, where preexisting immunity against influenza is associated with a less pronounced induction of vaccine-specific immunity as compared with influenza-naive subjects (27, 28). Evidence for cross-reactive immunity also exists among coronaviruses. In our study, very low levels of SARS-CoV-2–reactive T cells were in part detectable among control subjects without SARS-CoV-2 infection. However, as shown in recent studies using longer stimulation times, evidence for cross-reactive T cells is found in 20% to up to 50% of noninfected controls (8–11). Based on a variety of clinically relevant pathogens, the quantity and the characteristics of antigen-specific T cells have been shown to differ in relation to the pathogen activity in the context of primary infections or reactivations. As exemplified for immunity against cytomegalovirus, varicella zoster virus, HIV, or mycobacteria, T cells induced by primary infection or reactivation during active encounter with the pathogen show a low percentage of multifunctional cells and increased expression of inhibitory surface receptors such as CTLA-4 or PD-1, whereas the expression of these molecules decreases with successful control of the pathogen (15–18, 21, 29). In this respect, the lower CTLA-4 expression levels on SARS-CoV-2–specific T cells of convalescent individuals are compatible with successful viral control, whereas the increased expression of CTLA-4 on SARS-CoV-2–specific T cells in patients with severe disease may result from a prolonged and more intense encounter with the virus. Consistent with primary induction, specific T cells had a restricted cytokine pattern with a low percentage of multifunctional cells and a relative dominance of single or dual cytokine-producing cells expressing IL-2, which is different from reactivations, where the loss in multifunctional cells is associated with a shift toward cells exclusively expressing IFN-γ (18, 30). Although this functional profile of SARS-CoV-2–specific T cells in patients with severe disease has several characteristics of an exhausted phenotype found in patients with symptomatic disease in the context of chronic infections and/or reactivations, exhaustion is frequently associated with a quantitative decrease in specific T cells (15, 17). In contrast, our patients were able to mount a strong adaptive T cell response with proliferative potential, and the majority of patients achieved control of viral replication. Therefore, the high expression levels of CTLA-4 and the restricted functionality may reflect a physiological contraction mechanism to downregulate immune hyperactivation and specific immunity after its strong induction and to compensate for excessive immunopathology in the lung. This process appears to have notable effects on lymphocyte subpopulations and their functional characteristics in general, which show the same pattern of inhibitory surface receptors and functional restriction and thereby may account for an increased susceptibility for other opportunistic infections in patients with severe COVID-19 (31, 32). As with SARS-CoV-2–specific T cells, specific antibody responses were also highest in patients with severe disease. Interestingly, despite severe B cell lymphopenia that affected all major subpopulations, the increased antibody levels showed a direct correlation with the number of circulating plasmablasts, which were significantly higher than in convalescent patients and noninfected controls. Because high antibody responses were shown to correlate with neutralization capacity, this may directly contribute to viral clearance (13, 14, 33). However, given the association with disease severity, further studies should address whether antibodies may also contribute antibody-dependent enhancement of viral entry into Fc receptor–expressing cells, such as macrophages, thereby leading to increased inflammation and lung injury (34). Our study is limited by a low sample size, especially regarding some parameters that were analyzed in a subset of patients only. Nevertheless, differences in general as well as antigen-specific immunity between the 2 patient groups are very pronounced and correlate well with the severity of the disease. Moreover, we did not perform any longitudinal analyses of specific T cells and antibodies to evaluate whether the levels of specific immunity during primary infection determined stability and protection in the long term. Data on SARS-CoV-1–specific immunity indicated that both antibodies and T cells were detectable for several years, with highest stability in patients with more severe disease (35, 36). Similar studies with larger sample sizes are needed to evaluate whether the more pronounced immunity in patients with severe COVID-19 may result in higher stability after recovery and better protection from reinfection with SARS-CoV-2 in the long term. Knowledge gained from this study may have implications for vaccine design and therapeutic management. Our study revealed an immunodominance of specific T cells toward the spike protein as the main vaccine target. In addition, other viral proteins may represent promising antigens to achieve a broad vaccine-induced T cell response comparable to natural infection. Up to now, the role of immunosuppressive drugs for treatment of COVID-19 has been controversially discussed (37). Our results show that patients with severe disease mount a particularly strong cellular and humoral immune response. Although this immune response seems to be efficient in controlling viremia, contraction is required to prevent immunopathology associated with a hyperactive immune system. It is therefore tempting to speculate that immunosuppressive drugs are harmful when given in the induction phase but may have particular benefit in the contraction phase of the immune response. Data emerging from the RECOVERY Trial indeed provide first evidence for a particular survival benefit of dexamethasone treatment in ventilated patients with severe disease (38). Methods Study design and patient population. Patients who were hospitalized with PCR-confirmed COVID-19 (ICU patients) and patients with a milder course of disease in an outpatient setting were recruited, who had been matched with ICU patients according to the time since onset of clinical symptoms. In addition, individuals without evidence for infection with SARS-CoV-2 were tested as negative controls. ICU patients were recruited within the CORSAAR study, a cohort study on patients with COVID-19. Information on clinical symptoms was derived from patient charts or collected based on a questionnaire. Blood samples (4.7 mL) were collected in lithium heparin–containing tubes, and all analyses of antigen-specific T cells and lymphocyte subpopulations were carried out within 24 hours. Antibody testing was performed using frozen plasma samples. Quantitation of lymphocyte populations. Quantitation and characterization of lymphocyte subpopulations were performed on 100 μL of heparinized whole blood as described before (39) using monoclonal antibodies against CD3 (clone SK7), CD4 (clone SK3), CD8 (clones RPA-T8 and SK1), CD16 (clone 3G8), CD19 (clone HIB19), CD25 (clone M-A251), CD27 (clone L128), CD38 (clone HB7), CD56 (clone B159), CD127 (clone eBioRDR5, eBioscience, Thermo Fisher Scientific), CTLA-4 (clone BNI3), IgD (clone IA6-2), and PD-1 (clone MIH4, all from BD Biosciences). For samples that included anti-CD27 and anti-IgD, whole blood was washed with medium (RPMI) before staining to remove soluble CD27 and IgD. After 25 minutes of incubation, samples were treated with lysing solution (BD Biosciences). Thereafter, cells were washed with FACS buffer (PBS, 5% filtered FCS, 0.5% bovine serum albumin, 0.07% NaN3) and analyzed using flow cytometry (BD FACSCanto II) and FACSDiva V6.1.3 software (BD Biosciences). Gating strategies for each staining procedure are provided in Supplemental Figure 5. Intranuclear staining of Ki67 (clone B56) was performed using the Foxp3/transcription factor staining buffer set according to the manufacturer’s instructions (eBioscience, Thermo Fisher Scientific). Differentiation status of CD19+ B cells was assessed using antibodies against IgD and CD27. Plasmablasts were identified among switched memory B cells by additional staining of CD38. In addition, T cells were analyzed for expression of PD-1 and CTLA-4. Differential blood counts were used to calculate absolute lymphocyte numbers. CD4+ and CD8+ T cells were quantified among CD3+ T cells and these among lymphocytes. NK cells were identified using antibodies against CD3, CD16, and CD56 and quantified as CD3–CD16+/CD56+ lymphocytes. Tregs were identified among CD4+ T cells by high expression of CD25 and low CD127 expression. Detailed information on antibodies for flow cytometric stainings is given in Supplemental Table 1. Stimulation assays. Whole-blood samples were stimulated with overlapping peptide pools spanning the SARS-CoV-2 spike protein (spike vial 1, N-terminal receptor binding domain; and spike vial 2, C-terminal portion including the transmembrane domain), the NCAP protein, the membrane protein VME1, and the envelope small membrane protein VEMP (1 μg/mL each; JPT, Supplemental Table 2) to induce antigen-specific activation and cytokine induction as described previously (17). As a negative control, samples were treated with the diluent DMSO. Cells were stimulated with 2.5 μg/mL SEB (MilliporeSigma) to assess general characteristics of polyclonally stimulated T cells. Stimulation was performed from whole blood in the presence of costimulatory antibodies against CD28 and CD49d (1 μg/mL each) for 6 hours, with 10 μg/mL brefeldin A added after 2 hours of incubation. After 6 hours, samples were treated with 20 mM EDTA for 15 minutes; thereafter, cells were fixed using BD lysing solution, and stimulated cells were immunostained using anti-CD4 (clone SK3), anti-CD69 (clone L78), anti–IFN-γ (clone 4S.B3), anti–IL-2 (clone MQ1-17H12), anti–TNF-α (clone MAb11), anti–PD-1 (clone MIH4), anti–CTLA-4 (clone BNI3), anti-Ki67 (clone B56), or anti–granzyme B (clone GB11). All stainings except for PD-1 were performed after fixation. Ki67 staining was performed using the Foxp3/transcription factor staining buffer set as described above. Cells were analyzed using flow cytometry. Gating strategies are provided in Supplemental Figures 6 and 7. A schematic representation for cytokine profiling after stimulation with SARS-CoV-2 peptides and SEB is shown in Supplemental Figure 8. Analysis of SARS-CoV-2–specific antibodies. SARS-CoV-2–specific antibodies were quantified from heparinized plasma samples using an IgG and IgA assay coated with recombinant S1 domain of SARS-CoV-2 spike protein antigen according to the manufacturer’s instructions (Euroimmun). Antibody levels are expressed as ratios that are defined as the extinction of the patient sample divided by the extinction of a calibrator serum. Ratios less than 0.8 were scored negative, ratios between 0.8 and 1.1 were scored intermediate, and ratios of or greater than 1.1 were scored positive. Statistics. Statistical analysis was carried out using GraphPad Prism 8.0 software using 2-tailed t tests. An unpaired nonparametric Kruskal-Wallis test with Dunn’s posttest was used to analyze differences for lymphocyte subpopulations, T cell and antibody levels, as well as PD-1, CTLA-4, and Ki67 of total T cells among the 3 groups. Mann-Whitney U test was performed to compare nonparametric data between 2 groups (time since onset of symptoms and expression of CTLA-4, PD-1, Ki67, and granzyme B of specific T cells). Data with normal distribution were analyzed using unpaired t test (cytokine expression) or 1-way ANOVA test (age). Differences in sex were analyzed using χ2 test. Correlations between T cell levels, antibody titers, plasmablasts, and time from onset of symptoms were analyzed according to Spearman. A P value of less than 0.05 was considered statistically significant. Study approval. The study was approved by the ethics committee of the Ärztekammer des Saarlandes (references 76/20; l62/20), and all individuals or their legal representatives gave written informed consent. Author contributions DS, TS, US, SS, BCG, SLB, and MS designed the study; DS, TS, US, and MS designed the experiments. DS, VK, and TS performed experiments; SS, BCG, PML, HW, RB, JM, and HE contributed to study design, patient recruitment, and clinical data acquisition. DS, TS, US, and MS supervised all parts of the study, performed analyses, and wrote the manuscript. All authors approved the final version of the manuscript. Supplemental material Acknowledgments The authors thank Candida Guckelmus and Rebecca Urschel for excellent technical assistance. The authors also thank all participants in this study who contributed to the gain in knowledge from this project. The study was supported by institutional funds to MS and in part by grants of Saarland University (to MS and RB), the State of Saarland, and the Rolf M. Schwiete Stiftung to RB. Footnotes Conflict of interest: The authors have declared that no conflict of interest exists. Copyright: © 2020, Schub et al. This is an open access article published under the terms of the Creative Commons Attribution 4.0 International License. Reference information: JCI Insight. 2020;5(20):e142167.https://doi.org/10.1172/jci.insight.142167. References Huang C, et al. Clinical features of patients infected with 2019 novel coronavirus in Wuhan, China. Lancet. 2020;395(10223):497–506. View this article via: PubMed CrossRef Google Scholar Guan WJ, et al. Clinical characteristics of coronavirus disease 2019 in China. N Engl J Med. 2020;382(18):1708–1720. View this article via: PubMed CrossRef Google Scholar Wang F, et al. Characteristics of peripheral lymphocyte subset alteration in COVID-19 pneumonia. J Infect Dis. 2020;221(11):1762–1769. View this article via: PubMed CrossRef Google Scholar Chen G, et al. Clinical and immunological features of severe and moderate coronavirus disease 2019. J Clin Invest. 2020;130(5):2620–2629. View this article via: JCI PubMed CrossRef Google Scholar Wang F, et al. The laboratory tests and host immunity of COVID-19 patients with different severity of illness. JCI Insight. 2020;5(10):137799. View this article via: JCI Insight PubMed Google Scholar Zheng HY, et al. Elevated exhaustion levels and reduced functional diversity of T cells in peripheral blood may predict severe progression in COVID-19 patients. Cell Mol Immunol. 2020;17(5):541–543. View this article via: PubMed CrossRef Google Scholar Ni L, et al. Detection of SARS-CoV-2-specific humoral and cellular immunity in COVID-19 convalescent individuals. Immunity. 2020;52(6):971–977.e3. View this article via: PubMed CrossRef Google Scholar Grifoni A, et al. Targets of T cell responses to SARS-CoV-2 coronavirus in humans with COVID-19 disease and unexposed individuals. Cell. 2020;181(7):1489–1501.e15. View this article via: PubMed CrossRef Google Scholar Le Bert N, et al. SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls. Nature. 2020;584(7821):457–462. View this article via: PubMed CrossRef Google Scholar Sekine T, et al. Robust T cell immunity in convalescent individuals with asymptomatic or mild COVID-19. Cell. 2020;5(49):eabd6160. View this article via: CrossRef Google Scholar Weiskopf D, et al. Phenotype and kinetics of SARS-CoV-2-specific T cells in COVID-19 patients with acute respiratory distress syndrome. Sci Immunol. 2020;5(48):eabd2071. View this article via: PubMed CrossRef Google Scholar Guo L, et al. Profiling early humoral response to diagnose novel coronavirus disease (COVID-19). Clin Infect Dis. 2020;71(15):778–785. View this article via: PubMed CrossRef Google Scholar Wölfel R, et al. Virological assessment of hospitalized patients with COVID-2019. Nature. 2020;581(7809):465–469. View this article via: PubMed CrossRef Google Scholar Okba NMA, et al. Severe acute respiratory syndrome coronavirus 2-specific antibody responses in coronavirus disease patients. Emerging Infect Dis. 2020;26(7):1478–1488. View this article via: PubMed CrossRef Google Scholar Sester M, Leboeuf C, Schmidt T, Hirsch HH. The “ABC” of virus-specific T cell immunity in solid organ transplantation. Am J Transplant. 2016;16(6):1697–1706. View this article via: PubMed CrossRef Google Scholar Schub D, et al. CTLA-4-expression on VZV-specific T cells in CSF and blood is specifically increased in patients with VZV related central nervous system infections. Eur J Immunol. 2018;48(1):151–160. View this article via: PubMed CrossRef Google Scholar Sester U, Presser D, Dirks J, Gärtner BC, Köhler H, Sester M. PD-1 expression and IL-2 loss of cytomegalovirus- specific T cells correlates with viremia and reversible functional anergy. Am J Transplant. 2008;8(7):1486–1497. View this article via: PubMed CrossRef Google Scholar Schub D, et al. Altered phenotype and functionality of varicella zoster virus-specific cellular immunity in individuals with active infection. J Infect Dis. 2015;211(4):600–612. View this article via: PubMed CrossRef Google Scholar Schub D, et al. Assay for improved detection of antigen-specific immune cells from extrasanguinous fluids. Eur J Immunol. 2018;48(8):1412–1414. View this article via: PubMed CrossRef Google Scholar Schmidt T, et al. BK polyomavirus-specific cellular immune responses are age-dependent and strongly correlate with phases of virus replication. Am J Transplant. 2014;14(6):1334–1345. View this article via: PubMed CrossRef Google Scholar Sester U, et al. Whole-blood flow-cytometric analysis of antigen-specific CD4 T-cell cytokine profiles distinguishes active tuberculosis from non-active states. PLoS One. 2011;6(3):e17813. View this article via: PubMed CrossRef Google Scholar Braun J, et al. SARS-CoV-2-reactive T cells in healthy donors and patients with COVID-19 [published online July 29, 2020]. Nature. https://doi.org/10.1038/s41586-020-2598-9. Liao M, et al. Single-cell landscape of bronchoalveolar immune cells in patients with COVID-19. Nat Med. 2020;26(6):842–844. View this article via: PubMed CrossRef Google Scholar Naqvi AAT, et al. Insights into SARS-CoV-2 genome, structure, evolution, pathogenesis and therapies: structural genomics approach. Biochim Biophys Acta Mol Basis Dis. 2020;1866(10):165878. View this article via: PubMed CrossRef Google Scholar de Wilde AH, Snijder EJ, Kikkert M, van Hemert MJ. Host factors in coronavirus replication. Curr Top Microbiol Immunol. 2018;419:1–42. View this article via: PubMed Google Scholar Hou YJ, et al. SARS-CoV-2 reverse genetics reveals a variable infection gradient in the respiratory tract. Cell. 2020;182(2):429–446.e14. View this article via: PubMed CrossRef Google Scholar Sester U, Schmidt T, Kuhlmann MK, Gärtner BC, Uhlmann-Schiffler H, Sester M. Serial influenza-vaccination reveals impaired maintenance of specific T-cell memory in patients with end-stage renal failure. Vaccine. 2013;31(38):4111–4120. View this article via: PubMed CrossRef Google Scholar Schmidt T, et al. CD4+ T-cell immunity after pandemic influenza vaccination cross-reacts with seasonal antigens and functionally differs from active influenza infection. Eur J Immunol. 2012;42(7):1755–1766. View this article via: PubMed CrossRef Google Scholar Barber DL, et al. Restoring function in exhausted CD8 T cells during chronic viral infection. Nature. 2006;439(7077):682–687. View this article via: PubMed CrossRef Google Scholar Elsäßer J, et al. Antigen-specific CD4 T cells are induced after intravesical BCG-instillation therapy in patients with bladder cancer and show similar cytokine profiles as in active tuberculosis. PLoS One. 2013;8(9):e69892. View this article via: PubMed CrossRef Google Scholar Chen N, et al. Epidemiological and clinical characteristics of 99 cases of 2019 novel coronavirus pneumonia in Wuhan, China: a descriptive study. Lancet. 2020;395(10223):507–513. View this article via: PubMed CrossRef Google Scholar Rawson TM, et al. Bacterial and fungal co-infection in individuals with coronavirus: a rapid review to support COVID-19 antimicrobial prescribing [published online May 2, 2020]. Clin Infect Dis. https://doi.org/10.1093/cid/ciaa530. Zhao J, et al. Antibody responses to SARS-CoV-2 in patients of novel coronavirus disease 2019 [published online May 28, 2020]. Clin Infect Dis. https://doi.org/10.1093/cid/ciaa344. Taylor A, Foo SS, Bruzzone R, Dinh LV, King NJ, Mahalingam S. Fc receptors in antibody-dependent enhancement of viral infections. Immunol Rev. 2015;268(1):340–364. View this article via: PubMed CrossRef Google Scholar Cao WC, Liu W, Zhang PH, Zhang F, Richardus JH. Disappearance of antibodies to SARS-associated coronavirus after recovery. N Engl J Med. 2007;357(11):1162–1163. View this article via: PubMed CrossRef Google Scholar Tang F, et al. Lack of peripheral memory B cell responses in recovered patients with severe acute respiratory syndrome: a six-year follow-up study. J Immunol. 2011;186(12):7264–7268. View this article via: PubMed CrossRef Google Scholar Vabret N, et al. Immunology of COVID-19: current state of the science. Immunity. 2020;52(6):910–941. View this article via: PubMed CrossRef Google Scholar RECOVERY Collaborative Group, et al. Dexamethasone in hospitalized patients with Covid-19 - preliminary report [published online July 17, 2020]. N Engl J Med. https://doi.org/10.1056/NEJMoa2021436. Schoch J, et al. Quantitative, phenotypical, and functional characterization of cellular immunity in children and adolescents with down syndrome. J Infect Dis. 2017;215(10):1619–1628. View this article via: PubMed CrossRef Google Scholar Version history Version 1 (September 16, 2020): In-Press Preview Version 2 (October 15, 2020): Electronic publication

good health's curator insight,
January 12, 2024 7:18 AM
Acquista Online La Prescrizione Di Perdita Di Peso
https://globalefarmacia.com/Prodotto/acquista-ozempic-online/
https://www.bing.it/url?q=https://globalefarmacia.com/Prodotto/acquista-ozempic-online/
Scoop.it!
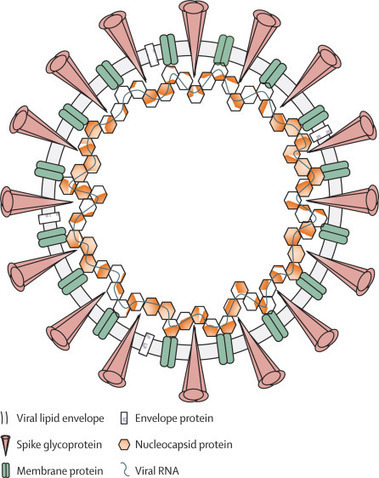
Understanding immune responses to severe acute respiratory syndrome coronavirus 2 Via HAS-veille
|
Scoop.it!

Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) is a highly transmissible and pathogenic coronavirus that emerged in late 2019 and has caused a pandemic of acute respiratory disease, named ‘coronavirus disease 2019’ (COVID-19), which threatens human health and public safety. In this Review, we describe the basic virology of SARS-CoV-2, including genomic characteristics and receptor use, highlighting its key difference from previously known coronaviruses. We summarize current knowledge of clinical, epidemiological and pathological features of COVID-19, as well as recent progress in animal models and antiviral treatment approaches for SARS-CoV-2 infection. We also discuss the potential wildlife hosts and zoonotic origin of this emerging virus in detail. In this Review, Shi and colleagues summarize the exceptional amount of research that has characterized acute respiratory syndrome coronavirus 2 (SARS-CoV-2) and coronavirus disease 2019 (COVID-19) since this virus has swept around the globe. They discuss what we know so far about the emergence and virology of SARS-CoV-2 and the pathogenesis and treatment of COVID-19.
Scoop.it!
Summary The factors responsible for the spectrum of coronavirus 19 (COVID‐19) disease severity and the genesis and nature of protective immunity against COVID‐19 remain elusive. Multiple studies ha...
Scoop.it!

Scientists across the world are closely tracking the spread of mutations in the coronavirus and investigating whether they could render current vaccines less effective. SARS-CoV-2 is no Ferrari among viruses when it comes to mutations. Scientists reckon that its 30,000-base RNA genome acquires around two single-letter mutations a month, a rate around half as fast as influenza and one-quarter the rate of HIV. But allowed to multiply and jump from body to body for more than a year, SARS-CoV-2 has inevitably flourished into a genetically diverse tree branching into countless different variants. Many variants—defined by a specific assortment of mutations—are relatively unremarkable. But scientists have been keeping a close watch on three rapidly spreading variants—first identified in the UK, South Africa, and Brazil—which harbor an unusual constellation of mutations. They all share a mutation called N501Y that affects the receptor binding domain (RBD) of the spike protein, which the virus uses to clasp onto human cells’ receptors and enter them. That mutation replaces SARS-CoV-2’s 501st amino acid, asparagine, with tyrosine, potentially allowing it to bind more tightly to ACE2 receptors, studies in cells and animal models suggest. By itself, that mutation isn’t unusual, but the variants possess an exceptionally large number of other mutations, some also on the spike protein. Substantive changes to a virus’ behavior, such as heightened transmissibility, are likely the result of multiple mutations rather than individual ones, molecular epidemiologist Emma Hodcroft of the University of Bern tells The Atlantic. The observation that similar mutations have appeared in three independent variants, and the fact that they are spreading, makes scientists suspect that they may have an evolutionary edge. “They have multiple, eight to ten, mutations in the spike protein all stacked up at once—that suggests that there [is] a lot of evolution and adaption of the protein happening,” Daniel Jones, a molecular pathologist at the Ohio State University, tells The Scientist. “The concern being that since that’s the target of vaccinations and . . . the target for antibody [therapies] like the Regeneron cocktail, for instance, that it might be the beginning of a virus that could evade antibody therapy and/or vaccine coverage.”
SARS-CoV-2 mutations’ effects on transmissibilityIt’s often in a virus’ interest to become more transmissible so it can spread and replicate more quickly. Earlier in the pandemic, a spike protein mutation known as D614G—which is widely believed to have made the virus more transmissible—surged to dominance around the world, notes virologist John Moore of Weill Cornell Medical College. Epidemiological data suggest that the B.1.1.7 variant, a descendant of the D614G lineage first identified in the UK that has spread to other parts of the world, also has heightened transmissibility. Eight of the 17 mutations it has recently accumulated are in the spike protein, which could feasibly have an effect on ACE2 binding and virus replication. Hypothetically, if a virus can bind more tightly to the body’s ACE2 receptors, it could be more capable of establishing an infection once it gets into the body and/or of generating more viral particles in the upper respiratory tract, making it easier to transmit to other people, particularly during the presymptomatic stage, explains Theodora Hatziioannou, a virologist at the Rockefeller University in New York. She adds that in her view, it’s hard to definitively ascribe case surges, including the current one in the UK, to single factors such as increased transmissibility, over other driving factors, such as what she sees as ineffective lockdown policies. “I’m not saying that [increased] transmissibility is out of the question. I’m just saying it’s extremely hard to prove.” In South Africa, epidemiologists have estimated that the new variant there, B.1.351 (also known as 501Y.V2), is around 50 percent more contagious compared with dominant lineages, based on its rapid spread, according to The Wall Street Journal. In Brazil, it’s too early to conclude whether a variant now circulating there, called P.1, is inherently more transmissible. First reported on January 12 in the state of Amazonas, it’s been associated with a devastating surge in cases in Manaus, a city where researchers had previously estimated that 75 percent of residents had already been infected with SARS-CoV-2. But it’s still unclear whether properties of the virus itself are contributing to the surge, says virologist Paola Resende of the Oswaldo Cruz Institute in Rio de Janeiro. “In Brazil, we can see a lot of parties, we can see the pubs crowded, and people are on the streets not wearing masks. I think this behavior of the population is the main reason [for] the increase.” Evading the immune systemOur immune system—and, in particular, antibodies—is a powerful evolutionary force on viruses. Some pathogens such as influenza, and maybe also common cold-causing coronaviruses, mutate their proteins toward new shapes to avoid being targeted by antibodies that would normally prevent them from infecting cells, a process known as antigenic drift. A study recently posted as a preprint to bioRxiv by Hatziioannou and her colleagues suggests that the RBD mutations present in the B.1.351 variant are due to antigenic drift. The team passaged a model virus bearing the dominant SARS-CoV-2 spike protein in the presence of individual neutralizing antibodies extracted from people who had received either the Moderna or Pfizer/BioNTech vaccine. Depending on which antibody they were cultured with, the viruses would gradually adopt a single mutation—either E484K, K417N, and N501Y—which are present in B.1.351. That suggests that “the virus is mutating in these positions to avoid antibodies,” Hatziioannou says. Such antibody-escape mutations don’t necessarily mean that the virus will cause more severe disease or entirely outwit the immune response, she cautions. There are other parts of the immune system to help clear the virus. There’s no evidence so far to suggest that the variants identified in South Africa or Brazil are more lethal. Based on an analysis of several datasets, scientists in the UK suggested last week there’s a “realistic possibility” that B.1.1.7 is deadlier than previous strains, but experts say it’s still too early to draw that conclusion. Another concern is about whether people who have overcome mild infections with older variants could become reinfected with a new one. Nobody that I know has been losing a moment of sleep over the UK variant from a vaccine-efficacy perspective..... Via Juan Lama
Scoop.it!

Alors que la pandémie de Covid-19 se poursuit, les scientifiques font chaque jour des progrès notables pour mieux comprendre la transmission du coronavirus SARS-CoV-2 ainsi que la réponse immunitaire qu’il déclenche lors d’une infection. Des chercheurs apportent de nouvelles données concernant les étapes très précoces de la réponse immunitaire.
Scoop.it!

Most of what we know about adaptive immunity has come from inbred mouse studies, using methods that are often difficult or impossible to confirm in humans. In addition, vaccine responses in mice are often poorly predictive of responses to those same vaccines in humans. Here we use human tonsils, readily available lymphoid organs, to develop a functional organotypic system that recapitulates key germinal center features in vitro, including the production of antigen-specific antibodies, somatic hypermutation and affinity maturation, plasmablast differentiation and class-switch recombination. We use this system to define the essential cellular components necessary to produce an influenza vaccine response. We also show that it can be used to evaluate humoral immune responses to two priming antigens, rabies vaccine and an adenovirus-based severe acute respiratory syndrome coronavirus 2 vaccine, and to assess the effects of different adjuvants. This system should prove useful for studying critical mechanisms underlying adaptive immunity in much greater depth than previously possible and to rapidly test vaccine candidates and adjuvants in an entirely human system. An in vitro human tonsil tissue-based system captures key features of a functional germinal center and can be used to study humoral immune responses to vaccines, new antigens and adjuvants.
Scoop.it!
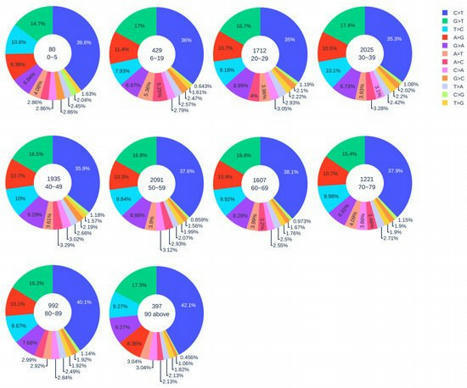
The transmission and evolution of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) are of paramount importance in controlling and combating the coronavirus disease 2019 (COVID-19) pandemic.
Scoop.it!
The British Society for Immunology has partnered with the Centre for Inflammation Research at the University of Edinburgh to present a three-part animated series for public audiences on the human immune system and how immune memories form in response to infections like coronavirus.
Gilbert C FAURE's insight:
insightful
Scoop.it!
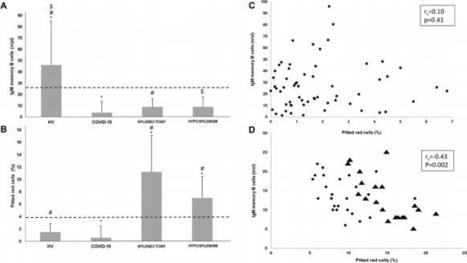
Impaired immune responses have been hypothesised to be a possible trigger of unfavourable outcomes in coronavirus disease 2019 (COVID-19). We aimed to characterise IgM memory B cells in patients with COVID-19 admitted to an internal medicine ward in Northern Italy. Overall, 66 COVID-19 patients (mean age 74 ± 16.6 years; 29 females) were enrolled. Three patients (4.5%; 1 female) had been splenectomised and were excluded from further analyses. Fifty-five patients (87.3%) had IgM memory B cell depletion, and 18 (28.6%) died during hospitalisation (cumulative incidence rate 9.26/100 person-week; 5.8–14.7 95% CI). All patients who died had IgM memory B cell depletion. A superimposed infection was found in 6 patients (9.5%), all of them having IgM memory B cell depletion (cumulative incidence rate 3.08/100 person-week; 1.3–6.8 95% CI). At bivariable analyses, older age, sex, number of comorbidities, and peripheral blood lymphocyte count < 1500/µl were not correlated with IgM memory B cell depletion. A discrete-to-marked reduction of the B-cell compartment was also noticed in autoptic spleen specimens of two COVID-19 patients. We conclude that IgM memory B cells are commonly depleted in COVID-19 patients and this correlates with increased mortality and superimposed infections.
Scoop.it!
Another host factor for SARS-CoV-2 Virus-host interactions determine cellular entry and spreading in tissues. Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) and the earlier SARS-CoV use angiotensin-converting enzyme 2 (ACE2) as a receptor; however, their tissue tropism differs, raising the possibility that additional host factors are involved. The spike protein of SARS-CoV-2 contains a cleavage site for the protease furin that is absent from SARS-CoV (see the Perspective by Kielian). Cantuti-Castelvetri et al. now show that neuropilin-1 (NRP1), which is known to bind furin-cleaved substrates, potentiates SARS-CoV-2 infectivity. NRP1 is abundantly expressed in the respiratory and olfactory epithelium, with highest expression in endothelial and epithelial cells. Daly et al. found that the furin-cleaved S1 fragment of the spike protein binds directly to cell surface NRP1 and blocking this interaction with a small-molecule inhibitor or monoclonal antibodies reduced viral infection in cell culture. Understanding the role of NRP1 in SARS-CoV-2 infection may suggest potential targets for future antiviral therapeutics. Science, this issue p. 856, p. 861; see also p. 765 Abstract Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), the causative agent of coronavirus disease 2019 (COVID-19), uses the viral spike (S) protein for host cell attachment and entry. The host protease furin cleaves the full-length precursor S glycoprotein into two associated polypeptides: S1 and S2. Cleavage of S generates a polybasic Arg-Arg-Ala-Arg carboxyl-terminal sequence on S1, which conforms to a C-end rule (CendR) motif that binds to cell surface neuropilin-1 (NRP1) and NRP2 receptors. We used x-ray crystallography and biochemical approaches to show that the S1 CendR motif directly bound NRP1. Blocking this interaction by RNA interference or selective inhibitors reduced SARS-CoV-2 entry and infectivity in cell culture. NRP1 thus serves as a host factor for SARS-CoV-2 infection and may potentially provide a therapeutic target for COVID-19. Severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) is the coronavirus responsible for the current coronavirus disease 2019 (COVID-19) pandemic (1, 2). A marked difference between the spike (S) protein of SARS-CoV-2 and SARS-CoV is the presence, in the former, of a polybasic sequence motif, Arg-Arg-Ala-Arg (RRAR), at the S1/S2 boundary. It provides a cleavage site for a host proprotein convertase, furin (3–5) (fig. S1A). The resulting two proteins, S1 and S2, remain noncovalently associated, with the serine protease TMPRSS2 further priming S2 (6). Furin-mediated processing increases infectivity and affects the tropism of SARS-CoV-2, whereas furin inhibition diminishes SARS-CoV-2 entry, and deletion of the polybasic site in the S protein reduces syncytia formation in cell culture (3–5, 7). The C terminus of the S1 protein generated by furin cleavage has an amino acid sequence (682RRAR685) that conforms to a [R/K]XX[R/K] motif, termed the “C-end rule” (CendR) (fig. S1B) (8). CendR peptides bind to neuropilin-1 (NRP1) and NRP2, transmembrane receptors that regulate pleiotropic biological processes, including axon guidance, angiogenesis, and vascular permeability (8–10). To explore the possibility that the SARS-CoV-2 S1 protein may associate with neuropilins, we generated a green fluorescent protein (GFP)–tagged S1 construct (GFP-S1) (fig. S1C). When expressed in human embryonic kidney 293T (HEK293T) cells engineered to express the SARS-CoV-2 receptor angiotensin-converting enzyme 2 (ACE2), GFP-S1 immunoprecipitated endogenous NRP1 and ACE2 (Fig. 1A). We transiently coexpressed NRP1-mCherry and either GFP-S1 or GFP-S1 ΔRRAR (a deletion of the terminal 682RRAR685 residues) in HEK293T cells. NRP1 immunoprecipitated the S1 protein, and deletion of the CendR motif reduced this association (Fig. 1B). Comparable binding was also observed with mCherry-NRP2, a receptor with high homology to NRP1 (fig. S1, D and E). In both cases, residual binding was observed with the ΔRRAR mutant, indicating an additional CendR-independent association between neuropilins and the S1 protein. To probe the functional relevance of this interaction, we generated HeLa wild-type and NRP1 knockout (KO) cell lines stably expressing ACE2, designated as HeLawt+ACE2 and HeLaNRP1KO+ACE2, respectively (the level of ACE2 expression was comparable between these lines) (fig. S1F). Using a clinical isolate SARS-CoV-2 (SARS-CoV-2/human/Liverpool/REMRQ001/2020), we performed viral infection assays and fixed the cells at 6 and 16 hours postinfection (hpi). SARS-CoV-2 infection was reduced in HeLaNRP1KO+ACE2 relative to HeLawt+ACE2 (Fig. 1C). HeLa cells lacking ACE2 expression were not infected (fig. S1G). In Caco-2 cells, a human colon adenocarcinoma cell line endogenously expressing ACE2 and widely used in COVID-19 studies, the suppression of NRP1 expression by short hairpin RNA (shRNA) greatly reduced SARS-CoV-2 infection at both 7 and 16 hpi, respectively, whereas that of vesicular stomatitis virus (VSV) pseudotyped with VSV-G was unaffected (Fig. 1D and figs. S1H and S2A). To determine if NRP1 was required for early virus infection, we established a sequential staining procedure using antibodies against SARS-CoV-2 S and N proteins to distinguish extracellular and intracellular viral particles (fig. S2B). Although NRP1 depletion did not affect SARS-CoV-2 binding to the Caco-2 cell surface (Fig. 1E), virus uptake was halved in NRP1-depleted cells compared to control cells after 30 min of internalization (Fig. 1F). Thus, NRP1 enhances SARS-CoV-2 entry and infection. We also observed that SARS-CoV-2–infected HeLawt+ACE2 cells displayed a multinucleated syncytia cell pattern, as reported by others (Fig. 1C) (5). Using an image analysis algorithm and supervised machine learning (fig. S2, C to F) (11), we quantified syncytia of infected HeLawt+ACE2 and HeLaNRP1KO+ACE2 cells. At 16 hpi, the majority of HeLawt+ACE2 cells formed syncytia, whereas in HeLaNRP1KO+ACE2 cells, this phenotype was reduced (fig. S2G). When infected with a SARS-CoV-2 isolate lacking the furin cleavage site (SARS-CoV-2 ΔS1/S2) (fig. S1A), the differences in infection and syncytia formation were less pronounced (fig. S2, H and I). However, a significant decrease in infection of HeLaNRP1KO+ACE2 was still observed at 16 hpi, indicating that NRP1 may additionally influence infection through a CendR-independent mechanism (fig. S2H). The extracellular regions of NRP1 and NRP2 are composed of two CUB domains (a1 and a2), two coagulation factor domains (b1 and b2), and a MAM domain (9). Of these, the b1 domain contains the specific binding site for CendR peptides (fig. S3A) (12). Accordingly, the mCherry-b1 domain of NRP1 immunoprecipitated GFP-S1, and a shortened GFP-S1 construct spanning residues 493 to 685 (figs. S1C and S3B). Isothermal titration calorimetry (ITC) established that the b1 domain of NRP1 directly bound a synthetic S1 CendR peptide (679NSPRRAR685) with an affinity of 20.3 μM at pH 7.5, which was enhanced to 13.0 μM at pH 5.5 (Fig. 2A). Binding was not observed to an S1 CendR peptide in which the C-terminal arginine was mutated to alanine (679NSPRRAA685) (Fig. 2A). We cocrystallized the NRP1 b1 domain in complex with the S1 CendR peptide (Fig. 2B). The resolved 2.35-Å structure revealed four molecules of b1 with electron density of the S1 CendR peptide clearly visible in the asymmetric unit (fig. S3C). S1 CendR peptide binding displayed strong similarity to the previously solved structure of NRP1 b1 domain in complex with its endogenous ligand VEGF-A164 (Fig. 2B and fig. S3D) (12). The key residues responsible for contacting the C-terminal R685 of the CendR peptide —Y297, W301, T316, D320, S346, T349 and Y353—are almost identical between the two structures (Fig. 2B and fig. S3D). The R682 and R685 side chains together engage NRP1 via stacked cation-π interactions with NRP1 side chains of Y297 and Y353. By projecting these findings onto the structure of the NRP1 ectodomain, the b1 CendR binding pocket appears to be freely accessible to the S1 CendR peptide (fig. S3E) (13). Site-directed mutagenesis of the S1 R685 residue to aspartic acid drastically reduced GFP-S1493-685 immunoprecipitation by mCherry-b1, confirming the critical role of the C-terminal arginine (Fig. 2C). Mutagenesis of the T316 residue within the mCherry-b1 domain of NRP1 to arginine also reduced association with GFP-S1493-685, consistent with its inhibitory impact on VEGF-A164 binding (12) (Fig. 2D). Accordingly, incubation of mCherry-b1 with VSV particles pseudotyped with trimeric S resulted in immunoprecipitation of processed forms of S1, which was dependent on the T316 residue (fig. S3F). Next, we transiently expressed either GFP, full-length NRP1 wt-GFP, or full length NRP1-GFP harboring the T316R mutation in HeLaNRP1KO+ACE2 cells. GFP expression and ACE2 expression levels were comparable and both constructs retained similar cell surface localization (fig. S3, G and H). SARS-CoV-2 infection was significantly enhanced in cells expressing NRP1 wt-GFP compared to GFP control, whereas it was not enhanced in cells expressing the T316R mutant (Fig. 2E). Thus, the SARS-CoV-2 S1 CendR and NRP1 interaction promotes infection. To establish the functional relevance of the S1 CendR-NRP1 interaction, we screened monoclonal antibodies (mAb#1, mAb#2, mAb#3) raised against the NRP1 b1b2 ectodomain. All three bound to the NRP1 b1b2 domain, displayed staining by immunofluorescence in NRP1-expressing PPC-1 (human primary prostate cancer) cells but not in M21 (human melanoma) cells that do not express NRP1 (fig. S4A) (8), and stained the extracellular domain of NRP1-GFP expressed in cells (fig. S4B). Of these antibodies, mAb#3, and to a lesser extent mAb#1, bound to the CendR-binding pocket with high specificity, as defined by reduced ability to bind to a b1b2 mutant that targets residues (S346, E348, T349) at the opening of the binding pocket (Fig. 3A) (12). Incubation of Caco-2 cells with mAbs#1 and 3 reduced SARS-CoV-2 infection compared to a control mAb targeting avian influenza A virus (H11N3) hemagglutinin (Fig. 3B). Consistent with this, mAb#3 inhibited binding of GFP-S1493-685 and mCherry-b1 (Fig. 3C). As a comparison, Caco-2 and Calu-3 cells were incubated with soluble ACE2, which inhibited SARS-CoV-2 infection in both cases (fig. S4C). Next, we turned to the small molecule EG00229, a selective NRP1 antagonist that binds the b1 CendR binding pocket and inhibits VEGF-A binding (Fig. 3D) (14). ITC established that EG00229 bound to the NRP1 b1 domain with a dissociation constant (Kd) of 5.1 and 11.0 μM at pH 7.5 and 5.5, respectively (Fig. 3E). EG00229 inhibited the direct binding between b1 and the S1 CendR peptide, and the immunoprecipitation of GFP-S1493-685 by mCherry-b1 (Fig. 3E and fig. S4D). Finally, incubation of Caco-2 cells with EG00229 reduced the efficiency of SARS-CoV-2 infection at 7 and 16 hpi (Fig. 3F). Thus, the SARS-CoV-2 interaction with NRP1 can be targeted to reduce viral infectivity in relevant human cell lines (fig. S5). Cell entry of SARS-CoV-2 depends on priming by host cell proteases (5, 6, 15). Our data indicate that a component of SARS-CoV-2 S protein binding to cell surface neuropilins occurs via the S1 CendR motif generated by the furin cleavage of S1/S2. Though not affecting cell surface attachment, this interaction promotes entry and infection by SARS-CoV-2 in physiologically relevant cell lines widely used in the study of COVID-19. The molecular basis for the effect is unclear, but neuropilins are known to mediate the internalization of CendR ligands through an endocytic process resembling macropinocytosis, (8, 16, 17). Notably, gene expression analysis has revealed an up-regulation of NRP1 and NRP2 in lung tissue from COVID-19 patients (18). A SARS-CoV-2 virus with a natural deletion of the S1/S2 furin cleavage site demonstrated attenuated pathogenicity in hamster models (19). NRP1 binding to the CendR peptide in S1 is thus likely to play a role in the increased infectivity of SARS-CoV-2 compared with SARS-CoV. The ability to target this specific interaction may provide a route for COVID-19 therapies. Supplementary Materials science.sciencemag.org/content/370/6518/861/suppl/DC1 Materials and Methods Figs. S1 to S5 Tables S1 to S3 References (20–33) MDAR Reproducibility Checklist https://creativecommons.org/licenses/by/4.0/ This is an open-access article distributed under the terms of the Creative Commons Attribution license, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. References and Notes ↵WHO Coronavirus disease, 2019 (COVID-19) Weekly Epidemiological Update – 31 August 2020. https://www.who.int/docs/default-source/coronaviruse/situation-reports/20200831-weekly-epi-update-3.pdf?sfvrsn=d7032a2a_4 ↵ E. Dong, H. Du, L. Gardner, An interactive web-based dashboard to track COVID-19 in real time. Lancet Infect. Dis. 20, 533–534 (2020). doi:10.1016/S1473-3099(20)30120-1pmid:32087114OpenUrlCrossRefPubMed ↵ D. Wrapp, N. Wang, K. S. Corbett, J. A. Goldsmith, C.-L. Hsieh, O. Abiona, B. S. Graham, J. S. McLellan, Cryo-EM structure of the 2019-nCoV spike in the prefusion conformation. Science 367, 1260–1263 (2020). doi:10.1126/science.abb2507pmid:32075877 A. C. Walls, Y.-J. Park, M. A. Tortorici, A. Wall, A. T. McGuire, D. Veesler, Structure, Function, and Antigenicity of the SARS-CoV-2 Spike Glycoprotein. Cell 181, 281–292.e6 (2020). doi:10.1016/j.cell.2020.02.058pmid:32155444OpenUrlCrossRefPubMed ↵ M. Hoffmann, H. Kleine-Weber, S. Pöhlmann, A multibasic cleavage site in the spike protein of SARS-CoV-2 is essential for infection of human lung cells. Mol. Cell 78, 779–784.e5 (2020). doi:10.1016/j.molcel.2020.04.022pmid:32362314OpenUrlCrossRefPubMed ↵ M. Hoffmann, H. Kleine-Weber, S. Schroeder, N. Krüger, T. Herrler, S. Erichsen, T. S. Schiergens, G. Herrler, N.-H. Wu, A. Nitsche, M. A. Müller, C. Drosten, S. Pöhlmann, SARS-CoV-2 cell entry depends on ACE2 and TMPRSS2 and is blocked by a clinically proven protease inhibitor. Cell 181, 271–280.e8 (2020). doi:10.1016/j.cell.2020.02.052pmid:32142651OpenUrlCrossRefPubMed ↵ J. Shang, Y. Wan, C. Luo, G. Ye, Q. Geng, A. Auerbach, F. Li, Cell entry mechanisms of SARS-CoV-2. Proc. Natl. Acad. Sci. U.S.A. 117, 11727–11734 (2020). doi:10.1073/pnas.2003138117pmid:32376634 ↵ T. Teesalu, K. N. Sugahara, V. R. Kotamraju, E. Ruoslahti, C-end rule peptides mediate neuropilin-1-dependent cell, vascular, and tissue penetration. Proc. Natl. Acad. Sci. U.S.A. 106, 16157–16162 (2009). doi:10.1073/pnas.0908201106pmid:19805273 ↵ H. F. Guo, C. W. Vander Kooi, Neuropilin functions as an essential cell surface receptor. J. Biol. Chem. 290, 29120–29126 (2015). doi:10.1074/jbc.R115.687327pmid:26451046 ↵ A. Plein, A. Fantin, C. Ruhrberg, Neuropilin regulation of angiogenesis, arteriogenesis, and vascular permeability. Microcirculation 21, 315–323 (2014). doi:10.1111/micc.12124pmid:24521511 ↵ R. Hollandi, A. Szkalisity, T. Toth, E. Tasnadi, C. Molnar, B. Mathe, I. Grexa, J. Molnar, A. Balind, M. Gorbe, M. Kovacs, E. Migh, A. Goodman, T. Balassa, K. Koos, W. Wang, J. C. Caicedo, N. Bara, F. Kovacs, L. Paavolainen, T. Danka, A. Kriston, A. E. Carpenter, K. Smith, P. Horvath, nucleAIzer: A parameter-free deep learning framework for nucleus segmentation using image style transfer. Cell Syst. 10, 453–458.e6 (2020). doi:10.1016/j.cels.2020.04.003OpenUrlCrossRef ↵ M. W. Parker, P. Xu, X. Li, C. W. Vander Kooi, Structural basis for selective vascular endothelial growth factor-A (VEGF-A) binding to neuropilin-1. J. Biol. Chem. 287, 11082–11089 (2012). doi:10.1074/jbc.M111.331140pmid:22318724 ↵ B. J. Janssen, T. Malinauskas, G. A. Weir, M. Z. Cader, C. Siebold, E. Y. Jones, Neuropilins lock secreted semaphorins onto plexins in a ternary signaling complex. Nat. Struct. Mol. Biol. 19, 1293–1299 (2012). doi:10.1038/nsmb.2416pmid:23104057OpenUrlCrossRefPubMed ↵ A. Jarvis, C. K. Allerston, H. Jia, B. Herzog, A. Garza-Garcia, N. Winfield, K. Ellard, R. Aqil, R. Lynch, C. Chapman, B. Hartzoulakis, J. Nally, M. Stewart, L. Cheng, M. Menon, M. Tickner, S. Djordjevic, P. C. Driscoll, I. Zachary, D. L. Selwood, Small molecule inhibitors of the neuropilin-1 vascular endothelial growth factor A (VEGF-A) interaction. J. Med. Chem. 53, 2215–2226 (2010). doi:10.1021/jm901755gpmid:20151671OpenUrlCrossRefPubMed ↵ J. K. Millet, G. R. Whittaker, Physiological and molecular triggers for SARS-CoV membrane fusion and entry into host cells. Virology 517, 3–8 (2018). doi:10.1016/j.virol.2017.12.015pmid:29275820OpenUrlCrossRefPubMed ↵ M. Simons, E. Gordon, L. Claesson-Welsh, Mechanisms and regulation of endothelial VEGF receptor signalling. Nat. Rev. Mol. Cell Biol. 17, 611–625 (2016). doi:10.1038/nrm.2016.87pmid:27461391OpenUrlCrossRefPubMed ↵ H. B. Pang, G. B. Braun, T. Friman, P. Aza-Blanc, M. E. Ruidiaz, K. N. Sugahara, T. Teesalu, E. Ruoslahti, An endocytosis pathway initiated through neuropilin-1 and regulated by nutrient availability. Nat. Commun. 5, 4904 (2014). doi:10.1038/ncomms5904pmid:25277522OpenUrlCrossRefPubMed ↵ M. Ackermann, S. E. Verleden, M. Kuehnel, A. Haverich, T. Welte, F. Laenger, A. Vanstapel, C. Werlein, H. Stark, A. Tzankov, W. W. Li, V. W. Li, S. J. Mentzer, D. Jonigk, Pulmonary vascular endothelialitis, thrombosis, and angiogenesis in Covid-19. N. Engl. J. Med. 383, 120–128 (2020). doi:10.1056/NEJMoa2015432pmid:32437596OpenUrlCrossRefPubMed ↵ S.-Y. Lau, P. Wang, B. W.-Y. Mok, A. J. Zhang, H. Chu, A. C.-Y. Lee, S. Deng, P. Chen, K.-H. Chan, W. Song, Z. Chen, K. K.-W. To, J. F.-W. Chan, K.-Y. Yuen, H. Chen, Attenuated SARS-CoV-2 variants with deletions at the S1/S2 junction. Emerg. Microbes Infect. 9, 837–842 (2020). doi:10.1080/22221751.2020.1756700pmid:32301390OpenUrlCrossRefPubMed ↵ A. D. Davidson, M. K. Williamson, S. Lewis, D. Shoemark, M. W. Carroll, K. J. Heesom, M. Zambon, J. Ellis, P. A. Lewis, J. A. Hiscox, D. A. Matthews, Characterisation of the transcriptome and proteome of SARS-CoV-2 reveals a cell passage induced in-frame deletion of the furin-like cleavage site from the spike glycoprotein. Genome Med. 12, 68 (2020). doi:10.1186/s13073-020-00763-0pmid:32723359OpenUrlCrossRefPubMed M. Berger Rentsch, G. Zimmer, A vesicular stomatitis virus replicon-based bioassay for the rapid and sensitive determination of multi-species type I interferon. PLOS ONE 6, e25858 (2011). doi:10.1371/journal.pone.0025858pmid:21998709OpenUrlCrossRefPubMed K. Smith, Y. Li, F. Piccinini, G. Csucs, C. Balazs, A. Bevilacqua, P. Horvath, CIDRE: An illumination-correction method for optical microscopy. Nat. Methods 12, 404–406 (2015). doi:10.1038/nmeth.3323pmid:25775044OpenUrlCrossRefPubMed O. Ronneberger, P. Fischer, T. Brox, U-net: Convolutional networks for biomedical image segmentation, in Medical Image Computing and Computer-Assisted Intervention –MICCAI 2015, N. Navab, J. Hornegger, W. Wells, A. Frangi, Eds., Lecture Notes in Computer Science (Springer International Publishing, 2015), vol. 9351, pp. 234–241. F. Piccinini, T. Balassa, A. Szkalisity, C. Molnar, L. Paavolainen, K. Kujala, K. Buzas, M. Sarazova, V. Pietiainen, U. Kutay, K. Smith, P. Horvath, Advanced cell classifier: User-friendly machine-learning-based software for discovering phenotypes in high-content imaging data. Cell Syst. 4, 651–655.e5 (2017). doi:10.1016/j.cels.2017.05.012pmid:28647475OpenUrlCrossRefPubMed B. A. Appleton, P. Wu, J. Maloney, J. Yin, W.-C. Liang, S. Stawicki, K. Mortara, K. K. Bowman, J. M. Elliott, W. Desmarais, J. F. Bazan, A. Bagri, M. Tessier-Lavigne, A. W. Koch, Y. Wu, R. J. Watts, C. Wiesmann, Structural studies of neuropilin/antibody complexes provide insights into semaphorin and VEGF binding. EMBO J. 26, 4902–4912 (2007). doi:10.1038/sj.emboj.7601906pmid:17989695 C. W. Vander Kooi, M. A. Jusino, B. Perman, D. B. Neau, H. D. Bellamy, D. J. Leahy, Structural basis for ligand and heparin binding to neuropilin B domains. Proc. Natl. Acad. Sci. U.S.A. 104, 6152–6157 (2007). doi:10.1073/pnas.0700043104pmid:17405859 B. G. Dorner, S. Steinbach, M. B. Hüser, R. A. Kroczek, A. Scheffold, Single-cell analysis of the murine chemokines MIP-1α, MIP-1β, RANTES and ATAC/lymphotactin by flow cytometry. J. Immunol. Methods 274, 83–91 (2003). doi:10.1016/S0022-1759(02)00498-2pmid:12609535 W. Kabsch, XDS. Acta Crystallogr. D Biol. Crystallogr. 66, 125–132 (2010). doi:10.1107/S0907444909047337pmid:20124692 P. R. Evans, G. N. Murshudov, How good are my data and what is the resolution? Acta Crystallogr. D Biol. Crystallogr. 69, 1204–1214 (2013). doi:10.1107/S0907444913000061pmid:23793146 A. J. McCoy, R. W. Grosse-Kunstleve, P. D. Adams, M. D. Winn, L. C. Storoni, R. J. Read, Phaser crystallographic software. J. Appl. Crystallogr. 40, 658–674 (2007). doi:10.1107/S0021889807021206pmid:19461840 P. D. Adams, P. V. Afonine, G. Bunkóczi, V. B. Chen, I. W. Davis, N. Echols, J. J. Headd, L.-W. Hung, G. J. Kapral, R. W. Grosse-Kunstleve, A. J. McCoy, N. W. Moriarty, R. Oeffner, R. J. Read, D. C. Richardson, J. S. Richardson, T. C. Terwilliger, P. H. Zwart, PHENIX: A comprehensive Python-based system for macromolecular structure solution. Acta Crystallogr. D Biol. Crystallogr. 66, 213–221 (2010). doi:10.1107/S0907444909052925pmid:20124702 V. B. Chen, W. B. Arendall 3rd, J. J. Headd, D. A. Keedy, R. M. Immormino, G. J. Kapral, L. W. Murray, J. S. Richardson, D. C. Richardson, MolProbity: All-atom structure validation for macromolecular crystallography. Acta Crystallogr. D Biol. Crystallogr. 66, 12–21 (2010). doi:10.1107/S0907444909042073pmid:20057044 ↵ L. Holm, P. Rosenström, Dali server: Conservation mapping in 3D. Nucleic Acids Res. 38, W545-9 (2010). doi:10.1093/nar/gkq366pmid:20457744 Acknowledgments: We thank the Bristol Synthetic Biology Centre and the Advanced Computing Research Centre for provision of HPC (Bluegem), and the University of Bristol Wolfson Bioimaging Facility. We thank the University of Queensland Remote Operation Crystallisation and X-ray facility (UQ-ROCX) and the staff for their support with the crystallization experiments, and the staff of the Australian Synchrotron for assistance with x-ray diffraction data collection. Funding: J.L.D. was supported by a Wellcome Trust studentship from the Dynamic Molecular Cell Biology Ph.D. program (203959/Z/16/Z), C.A.P. was supported by Beca Fundación Ramón Areces Estudios Postdoctorales en el Extranjero, and M.K.W. was supported by an MRC grant (MR/R020566/1) awarded to A.D.D. This project has received funding from the MRC (MR/P018807/1), Wellcome Trust (104568/Z/14/2), Lister Institute of Preventive Medicine, and Elizabeth Blackwell Institute for Health Research Rapid Response Call (COVID-19) awarded to P.J.C, the European Research Council under the European Union’s Horizon 2020 research and innovation program (No 856581 - CHUbVi), and from MRC-AMED (MR/T028769/1) awarded to Y.Y., the Swiss National Science Foundation and Kanton Zurich awarded to U.F.G. B.M.C. is supported by an Australian National Health and Medical Research Council (NHMRC) Senior Research Fellowship (APP1136021) and Project Grant (APP1156493), and the United States Food and Drug Administration grant no. HHSF223201510104C “Ebola Virus Disease: correlates of protection, determinants of outcome and clinical management” amended to incorporate urgent COVID-19 studies awarded to J.A.H., A.D.D., and D.A.M. R.H. and P.H. acknowledge support from the LENDULET-BIOMAG Grant (2018-342), from H2020-discovAIR (874656), and from Chan Zuckerberg Initiative, Seed Networks for the HCA-DVP. T.T. was supported by the European Regional Development Fund (Project no. 2014-2020.4.01.15-0012), by European Research Council grant GLIOGUIDE and Estonian Research Council (grants PRG230 and EAG79, to T.T.). Author contributions: J.L.D., B.S., A.H., P.J.C., and Y.Y. conceived the study. J.L.D., B.S., K.K, and Y.Y. performed most of the experiments. K.K., M.K.W., D.A.M., and A.D.D. performed all work with infectious SARS-CoV-2 supervised by A.D.D. M.K.W. and A.D.D. isolated SARS-CoV-2 strains used for the work. K.C., C.A.P., M.B., L.S.G., U.F.G., K.K., R.B.S., D.K.S., J.A.H., and T.T. did experimental work and/or provided essential reagents. R.H. and P.H. performed image analysis. B.S., A.D.D., B.M.C., P.J.C., and Y.Y. supervised the research. J.L.D., B.S., A.D.D., P.J.C., and Y.Y. wrote the manuscript and made the figures. All authors read and approved the final manuscript. Competing interests: T.T. is an inventor of patents on CendR peptides and a shareholder of Cend Therapeutics Inc., a company that holds a license for the CendR peptides and is developing the peptides for cancer therapy. J.A.H. is a member of the Department of Health, New and Emerging Respiratory Virus Threats Advisory Group (NERVTAG) and the Department of Health, Testing Advisory Group. U.F.G. is a consultant to F. Hoffmann–La Roche Ltd, Switzerland. All other authors declare no competing interests. Data and materials availability: Coordinates and structure factors for the NRP1 b1-S1 CendR peptide complex have been deposited at the Protein Data Bank (PDB) with accession code 7JJC. All other data are available in the manuscript or the supplementary materials. This work is licensed under a Creative Commons Attribution 4.0 International (CC BY 4.0) license, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. To view a copy of this license, visit https://creativecommons.org/licenses/by/4.0/. This license does not apply to figures/photos/artwork or other content included in the article that is credited to a third party; obtain authorization from the rights holder before using such material.
Scoop.it!
Studies signal that damage to the endothelium--cells that cover blood vessels like wallpaper--could underpin the thrombosis and inflammation induced by coronavirus infection.
Gilbert C FAURE's insight:
endothelial cells are immune competent cells
Scoop.it!
The innate immune system acts as the first line of defense against pathogens, including
Scoop.it!
Scientists have found a second doorway, called neuropilin-1, that the novel coronavirus uses to invade human cells.
|