 Your new post is loading...

|
Scooped by
Gilbert C FAURE
October 22, 3:48 AM
|
Dengue is an acute febrile disease caused by the Aedes mosquito-borne dengue viruses (DENV-1 to DENV-4). Annually, approximately 100 million people fall ill with dengue, which can cause debilitating pain and discomfort, reducing both physical functioning and quality of life. Some patients progress to life-threatening inflammation-driven circulatory failure. Disease burden remains primarily in urban centres; however, factors including increased travel and climate change are rapidly expanding the geographical distribution of dengue to rural and peri-urban environments. Dengue is diagnosed based on compatible clinical features, detection of viral RNA or antigens, or serological testing, depending on the phase of illness. There is no licensed antiviral or host-directed therapy for dengue; management is supportive, with close clinical monitoring and judicious fluid replacement to prevent circulatory failure while avoiding fluid overload. Thus, there is an increasing need for clinicians to be familiar with the clinical features, disease burden and management of dengue, along with the newly recognized post-acute sequelae. Although dengue vaccines have been licensed in several countries, their use has been restricted by uncertainties in dengue pathogenesis. Attention should be focused on how to use currently available vaccines to create the foundation of a larger strategy to mitigate dengue transmission and maximize public health impact. Dengue is an acute febrile disease caused by the Aedes mosquito-borne dengue viruses. In this Primer, Ooi et al. describe the epidemiology, mechanisms, diagnosis and management of dengue infection and highlight patients’ quality of life and questions for future research.
|
|
Scooped by
Gilbert C FAURE
November 15, 2022 12:19 PM
|
© Copyright 2022 Takeda Pharmaceutical Company Limited. All rights reserved. Takeda and the Takeda Logo are registered trademarks of Takeda Pharmaceutical Company Limited. some previously curated material on dengue https://www.scoop.it/topic/immunology?q=dengue
|
|
Scooped by
Gilbert C FAURE
May 12, 2020 3:50 AM
|
O'nyong-nyong virus (ONNV) is an arthritogenic alphavirus that caused two large epidemics in 1959 and 1996, affecting millions of people in Africa. More recently, sero-surveillance of healthy blood donors conducted in 2019 revealed high rates of unreported ONNV infection in Uganda. Due to similar clinical symptoms with other endemic mosquito-borne pathogens in the region, including chikungunya virus, dengue virus and malaria, ONNV infections are often un- or misdiagnosed. Elucidating the immunopathogenic factors of this re-emerging arbovirus is critical with the expanding geographic distribution of competent vectors. This study reports the establishment of an immune competent C57BL6/J mouse model to mechanistically characterize ONNV infection and assess potential treatment efficacy. This mouse model successfully recapitulated arthralgia and viremia profiles seen in ONNV patients. Furthermore, longitudinal in-vivo PET imaging with [18F]FB-IL-2 (CD25+CD4+ binding probe) and histopathological assessment in this model demonstrated the pathogenic role of CD4+ T cells in driving joint pathology. Concordantly, in vivo CD4+ T cell depletion, or suppression with fingolimod, an FDA-approved immunomodulating drug, abrogated CD4+ T cell-mediated disease. This study demonstrates the importance of this immune competent ONNV model for future studies on factors influencing disease pathogenesis, which could shape the discovery of novel therapeutic strategies for arthritogenic alphaviruses.
|
|
Scooped by
Gilbert C FAURE
January 25, 2019 5:12 AM
|
The existence of four different serotypes of dengue virus poses a challenge to vaccine development, as pre-existing immunity can lead to severe disease during infection with a heterologous serotype. This Review analyses the mechanisms of protective and pathological adaptive immune responses in primary and secondary dengue infection.

|
Suggested by
Société Francaise d'Immunologie
January 23, 2019 2:46 AM
|
Summary Natural killer (NK) cells are lymphocytes of the innate immune system with essential roles during viral infections. NK cell functions are mediated through a repertoire of non‐rearranging inhibitory and activating receptors that interact with major histocompatibility complex (MHC)–peptide complexes on the surface of infected cells. Recent work studying the conserved CD94–NKG2A and variable killer cell immunoglobulin‐like receptor–MHC systems suggest that these two receptor families may have subtly different properties in terms of interactions with MHC class I bound peptides, and in recognition of down‐regulation of MHC class I. In this review, we discuss how these properties generate diversity in the NK cell response to viruses. Abbreviations CMV cytomegalovirus DAP12 DNAX activation protein 12 HBV hepatitis B virus HCV hepatitis C virus HIV‐1 human immunodeficiency virus type 1 ITAM immunoreceptor tyrosine‐based activation motifs ITIM immunoreceptor tyrosine‐based inhibition motifs KIR killer cell immunoglobulin‐like receptors LILRB1 leucocyte immunoglobulin‐like receptor B1 MHC major histocompatibility complex MICA MHC class I polypeptide‐related sequence A MICB MHC class I polypeptide‐related sequence B NK natural killer Introduction Natural killer (NK) cells are a subset of innate lymphocytes that provide an essential first line of defence against invading pathogens such as viruses, parasites and tumour cells. Innate immune responses can be highly conserved and are thought to evolve under distinct selective pressures. Whereas the adaptive immune system possesses rearranging receptors, which can adapt to different pathogens within a single host, the innate system relies on germline‐encoded, non‐rearranging receptors and therefore adapts over evolutionary time.1 Hence, the genes of innate immunity may be important for dealing with current pathogens, but may also represent remnants of previous encounters as humans have evolved and migrated across the globe. The co‐evolution of hosts and their pathogens is a complex and dynamic process that requires reciprocal variation at a genomic level.2 The population diversity of polymorphic immune response genes, such as the major histocompatibility complex (MHC) and the killer cell immunoglobulin‐like receptors (KIR), implies that there is no single ‘optimized’ immune system, but variants that have selective advantage against specific pathogens. This has been highlighted by numerous association studies of these two gene families with infectious agents.3-5 Genetic association studies in different populations frequently differ in their results, indicating that there are additional genetic and environmental contexts in which these genes operate to determine their role in disease outcome.6 Furthermore, it indicates that similar selection pressures may lead to the emergence of distinct protective genes in different populations. Viruses are thought to exert a major selective force on human NK cells. The functions of NK cells against these pathogens include the detection and elimination of infected cells by releasing cytolytic granules and by producing antiviral cytokines such as interferon‐γ and tumour necrosis factor‐α.7 Viruses and NK cells are in a constant evolutionary arms race maintaining an equilibrium that preserves both host and pathogen as extant species.8 In particular, the rapidly evolving KIR and MHC genes constitute a linked system that has been driven by these forces. This review describes the relevance of conserved and variable NK cell receptor–MHC interactions in the context of viral infections and explains how this receptor–ligand system has been targeted by viruses to escape from immune surveillance. MHC class I receptors on NK cells: roles in viral infections Natural killer cell functions are determined by a balance between inhibitory or activating signals that occur after engagement of germline‐encoded, non‐rearranging receptors with their ligands. The wide repertoire of NK cell receptors in humans comprises KIR, CD94–NKG2 heterodimers, LILRB1, NKG2D and natural cytotoxicity receptors such as NKp30, NKp44 and NKp46. These receptors cooperate to generate activating signals that can overcome the tonic inhibition driven by KIR and CD94–NKG2A in humans. Ligands for these receptors include molecules from the MHC class I and MHC class I‐related proteins such as MHC class I polypeptide‐related sequence A (MICA), MICB and UL16 binding proteins, among many others (Fig. 1).9 In general, such receptor–ligand diversity allows NK cells to respond to multiple stimuli, and this diversity is augmented by the combinatorial manner in which NK cells can integrate signals from these multiple receptors. KIR receptors The family of KIR receptors are type 1 transmembrane glycoproteins encoded by polymorphic genes located within the leucocyte receptor complex in the long arm of chromosome 19 (19q13).10 These receptors have two or three extracellular domains (2D or 3D) and perform inhibitory or activating functions as determined by their cytoplasmic tails. Hence, inhibitory KIRs have long (L) cytoplasmic tails and contains immunoreceptor tyrosine‐based inhibition motifs (ITIMs). On the other hand, activating receptors have short (S) cytoplasmic tails and associate with adapter molecules containing immunoreceptor tyrosine‐based activation motifs (ITAMs), such as DNAX activation protein 12 (DAP12).9, 11 An exception to this rule is given by KIR2DL4, which, despite having a long cytoplasmic domain, has an activating function.12 Within an individual, NK cell clones exhibit diverse patterns of KIR expression, which is determined by gene content, copy number and allelism.13-15 Such diversity of receptor repertoires and the high degree of KIR polymorphism allow NK cells to generate rapid responses against a broad spectrum of pathogens. Ligands for KIR receptors are classical MHC class I molecules (human leucocyte antigens; HLA‐A, ‐B, ‐C) and are considered the most polymorphic in the human genome.16 MHC class I molecules bind intracellularly derived peptides from 8 to 10 amino acids in length, exposing them on the cell surface. Processing and presentation of endogenous peptides through MHC class I molecules are a mechanism of immune surveillance that allows host cells to alert both NK cells and CD8+ T lymphocytes to infections or malignant change.17 Engagement of inhibitory KIR receptors with their MHC class I ligands usually turns off NK cell functions. Conversely, these same interactions participate in NK cell education, which allows NK cells to become tolerant to healthy cells or ‘self’, while becoming fully functional.18, 19 During viral infections, expression of MHC ligands may be down‐regulated or absent (‘missing‐self’), due to strategies employed by viruses to escape CD8+ T‐cell recognition (reviewed in ref. 20). The lack of an inhibitor receptor–ligand interaction results in a dominant activating response within NK cells, promoting cytotoxicity or cytokine production. Viruses that down‐regulate MHC class I include herpesviruses,21 retroviruses 22 and papillomaviruses.23 Genetic diversity of KIR receptors The extensive polymorphism exhibited by KIR genes influences expression and function of KIR on individual NK cells. In humans, two KIR haplotypes have been defined: haplotypes A and B. Haplotype A displays a fixed gene content consisting of five inhibitory receptors, two activating receptors and one pseudogene.24 Conversely, haplotype B includes variable amounts of inhibitory and activating KIR and generates population diversity at the level of the locus.25, 26 The frequencies of the key inhibitory KIR (KIR2DL1, KIR2DL2/L3 and KIR3DL1) are maintained at a high level in most populations.27 Conversely, frequencies of activating KIR are more variable. KIR2DS1, KIR2DS2 and KIR3DS1 frequencies are high in Papua New Guinean and Australian populations (~70–90%) but low in African or Chinese populations (< 20%). KIR2DS1 is also frequent in Latin America (~60–90%), KIR2DS2 in India (~75%) and KIR3DS1 in Brazil (80%).27 This variability in KIR expression across populations suggests different selection pressures imposed by infectious diseases on the different KIR genes.25 In addition to haplotypic variability, allelism also contributes to the diversity of KIR receptors, with the most variable KIR gene being KIR3DL2, which has 158 alleles.26 KIR allelic diversity also generates receptors with different binding affinities to MHC class I ligands. This phenomenon is best described for inhibitory KIR2DL2 and KIR2DL3, which segregate as alleles at a single locus but have subtly different specificities for their HLA‐C ligands which, in turn, are modulated by the peptide bound by the HLA‐C molecule.28, 29 Additionally, KIR3DL1 alleles exhibit different levels of cell surface expression, which alter their inhibitory potential and differentially associate with protection in human immunodeficiency virus type 1 (HIV‐1) infection.30 Co‐evolution of the KIR–MHC system The concomitant evolution of KIR receptors and their MHC class I ligands is an intriguing topic. The rapid co‐evolution of KIR receptors and their MHC ligands is subject to balancing selection. This evolutionary process favours the preservation of heterozygosity in the population, which correlates with increased diversity and host fitness.31 Selection operates on gene segments that encode contact regions of KIR and the peptide‐binding site of MHC.32 This may be advantageous for the host because it facilitates the presentation of viral peptides that can be recognized by distinct KIR alleles, to increase the efficiency of the immune response. However, it could also favour virus persistence, because viral peptides that engage inhibitory receptors, would prevent the activation of NK cells. CD94:NKG2 receptors The invariant CD94 is a C‐type lectin‐like protein that forms heterodimers with receptors from the NKG2 family. These genes are all encoded within the NK complex, on the short arm of chromosome 12 (12p12.3‐p13.1) and unlike KIRs, are non‐polymorphic.33, 34 Ligands for these heterodimers are HLA‐E molecules, which are conserved, non‐polymorphic proteins. HLA‐E binds conserved leader peptides from the N‐terminus of classical and non‐classical HLA molecules. Binding of leader sequences to HLA‐E is therefore a mechanism to monitor normal synthesis and expression of classical MHC class I molecules (HLA‐A, ‐B and ‐C), and also of the non‐classical MHC molecule, HLA‐G.35, 36 The CD94:NKG2A receptor is inhibitory, containing two ITIMs, and plays an important role during viral infections.37 Viruses may down‐regulate MHC class I molecules through multiple different mechanisms, and this reduces the availability of leader peptides for presentation by HLA‐E. This then decreases the expression of HLA‐E on the cell surface, reducing inhibition of NKG2A+ NK cells, leading to their activation.35, 38 Conversely, heterodimers formed by CD94 with NKG2C, associate with DAP12, which contains ITAMs, and this generates activating signals.39, 40 As CD94:NKG2A and CD94:NKG2C are clonally expressed on NK cells, viruses that down‐regulate MHC class I, but maintain HLA‐E expression through the presentation of an HLA‐E binding peptide may still be recognized by this system. Consistent with this model, Gumá et al. have shown that individuals positive for cytomegalovirus (CMV) have higher counts of CD94:NKG2C+, and lower levels of CD94:NKG2A+ NK cells compared with non‐infected controls.41 Hence, during viral infections, NK cells can be activated through signals received from activating receptors or through the loss of expression of inhibitory ligands. Differential roles of polymorphic and non‐polymorphic receptor–ligand systems Throughout the evolution of primates, the polymorphic KIR appear to have continuously adapted whereas CD94:NKG2A has remained relatively conserved. The evolution of these receptor families is paralleled by that of their MHC class I ligands, which can be polymorphic (HLA‐A, ‐B, ‐C) or non‐polymorphic (HLA‐E, ‐F, ‐G) (Fig. 1). Having both receptor–ligand systems allows NK cells to sense changes in virus‐infected cells using discrete mechansims, which increases diversity in the mechanisms by which NK cells can respond to the multiplicity of viruses encountered by humans. Non‐polymorphic receptor–ligand interactions MHC‐E and CD94:NKG2A receptors are well conserved across species. Functional CD94:NKG2A receptors in the common chimpanzee (Pan troglodytes) appear to have the same specificity for MHC‐E and leader sequences as their human counterpart.42 This suggests a common function, namely detection of down‐regulation of other MHC class I molecules, which targets viruses with diverse means of down‐regulating MHC class I. Such mechanisms include direct targeting of MHC class I (CMV); inhibition of antigen processing (Epstein–Barr virus); or generic cellular processes such as the inhibition of protein synthesis (vaccinia virus) and trafficking through the endoplasmic reticulum (hepatitis C virus; HCV).43-46 HLA‐G is also relatively non‐polymorphic and interacts with NKG2A through its leader sequence. However, it can also interact with the inhibitory receptor LILRB1 and the activating receptor KIR2DL4, through an endosomal pathway.36, 47, 48 Although LILRB1 is not conserved between humans and the common chimpanzee, KIR2DL4 is highly conserved, a striking observation considering the rapid evolution of the KIR locus.42 HLA‐G can be up‐regulated during viral infections such as CMV, hepatitis B virus (HBV) and HCV.49-51 This raises the intriguing possibility that the HLA‐G–KIR2DL4 interaction may have an important biological role that has led to their conservation between humans and chimpanzees. Such conservation may be related to beneficial effects on pregnancy, as well as, or instead of, their effects on viral infections.47 HLA‐F has been shown to interact with KIR3DL2 and KIR2DS4 as an open conformer.52 Like KIR2DL4, KIR3DL2 is present in all individuals whereas KIR2DS4 is present in > 90% of individuals in most populations, although it may harbour a deletion and hence be present only in a secreted form.53 More recently, it has been shown that HLA‐F also binds KIR3DS1 and importantly, it is up‐regulated during both HIV‐1 and HCV infections.54, 55 Polymorphic receptor–ligand interactions The human classical MHC class I molecules interact with NK cell receptors either by directly binding KIR or indirectly through furnishing a leader peptide for HLA‐E. HLA‐A is the most ancient of these molecules, and all HLA‐A alleles have a methionine residue at position ‐21 (‐21M) and so a cognate leader peptide for HLA‐E to engage CD94:NKG2A. However, only a minority of HLA‐A molecules interact with KIR. HLA‐A*03 and HLA‐A*11 interact with KIR3DL2, whereas HLA‐A and HLA‐B molecules with a Bw4 serological epitope bind KIR3DL1.56 HLA‐B has a dimorphism, such that HLA‐BBw4 alleles that bind KIR3DL1 generally have a threonine residue at position ‐21 (‐21T) and so do not have a leader peptide cognate for HLA‐E, in comparison with those with the Bw6 serological motif, which do not bind KIR3DS1 but have ‐21M to engage CD94:NKG2A through HLA‐E.57 The cognate leader peptide is thought to be the ancestral leader sequence, implying that the functional interaction of HLA‐BBw4 with KIR has developed more recently. HLA‐C is the most recently evolved of the classical MHC class I molecules, and all HLA‐C molecules have a functional interaction with KIR. HLA‐C is expressed on the cell surface at levels of about 10% of HLA‐A and HLA‐B molecules and overall appears specialized to interact with NK cells, as opposed to having a primary role presenting antigens to T cells.56, 58 Combinatorial advantage for NK cell receptors The KIR and CD94:NKG2A systems are strongly interlinked through their contribution to NK cell function. This is further exemplified by the diversity in leader sequences among HLA‐B alleles. Individuals with HLA‐B alleles containing ‐21M have more CD94:NKG2A+ NK cells compared with those having HLA‐B alleles with ‐21T.57 Conversely, individuals with two ‐21T HLA‐B alleles have more KIR+ NK cells. Additionally, haplotypes having HLA‐B alleles with ‐21M contain group 1 HLA‐C alleles (HLA‐CAsn80), rather than group 2 HLA‐C alleles (HLA‐CLys80).57 Hence, genetic dimorphisms within NK cell receptors stratify the population with important consequences for the antiviral response. This has best been demonstrated for HIV‐1 infection, in which ‐21M HLA‐B alleles have a deleterious effect.59 The emergence of KIR and its rapid evolution suggests that this family of receptors may have subtly different functions from CD94:NKG2A. For instance, the stoichiometry of the response of NKG2A+ NK cells to down‐regulation of HLA‐E is different to that of KIR+ NK cells to HLA‐C down‐regulation.60 Both HLA‐C and HLA‐E are expressed at low levels on healthy cells compared with HLA‐A and HLA‐B, and HLA‐E is expressed at 25‐fold lower levels than HLA‐C.58 However, at low levels of MHC‐I, NKG2A+ NK cells are more sensitive to small changes in surface levels of MHC‐I compared with KIR+ NK cells. This implies that NKG2A+ NK cells, but not KIR+ NK cells, are finely tuned to detect small changes in cell surface MHC‐I, which can be driven by changes in expression of classical HLA class I molecules, in addition to a direct down‐regulation of HLA‐E (Fig. 2). At a functional level, this difference is evident in assays of vaccinia virus infection in vitro. Vaccinia virus inhibits host protein synthesis,44 inducing down‐regulation of MHC‐I, such that NKG2A+, but not KIR+, NK cell clones lyse vaccinia virus‐infected targets.38 Hence, although NKG2A+ NK cells are tuned to detect MHC class I down‐regulation, this begs the question as to the role of KIR, which appear to be more specialized and more recently evolved. Peptide selectivity of NK cell receptors Both KIR and CD94:NKG2A bind MHC class I and additionally contact the presented peptide. Therefore, both types of receptors are sensitive to peptides bound within the MHC groove.61 Changes in the peptide repertoire can abrogate recognition of MHC class I by inhibitory receptors, which leads to NK cell activation. There appear to be two different classes of apparently ‘null’ peptides, with opposing actions on the KIR and CD94:NKG2A systems. These are peptides that, in isolation, do not affect NK cell reactivity, but can modulate inhibitory signals. For KIR2DL2/L3 and HLA‐C, we have identified peptide antagonists.62 In relatively small quantities, these peptides can down‐modulate the inhibitory KIR signals to permit their activation against target cells (Fig. 2).63 Mechanistically, they induce SHP‐1 recruitment, but without Vav1 dephosphorylation.64 Additionally, there are peptides that bind HLA‐E, which alone do not inhibit NKG2A+ NK cells, but augment the inhibition due to canonical HLA‐E‐binding class I leader peptides.60 These peptides engage CD94 in the absence of NKG2A, most likely in its homodimeric form, and include sequences derived from HIV‐1 (AISPRTLNA), HCV (YLLPRRGPRL) and EBV (SQAPLPCVL).65-67 Interestingly, these peptides do not have the canonical HLA‐E binding motif, which is consistent with a broad peptide‐presenting role for HLA‐E.68 Hence, peptide modulation through KIR appears beneficial to the host but modulation through NKG2A may be detrimental. Viral peptides A number of virus‐derived peptides that augment NK cell inhibition have been described. These include the peptides for HLA‐E mentioned above, but also other peptides from HIV‐1 and HCV have been identified.69-71 In general, these viral sequences act as inhibitory peptides for KIR receptors. The most compelling data come from the identification of ‘KIR footprints’ on the HIV‐1 genome and the association of an inhibitory peptide from HIV‐1 in individuals with a KIR2DL2 gene.72 The complex changes of the peptide repertoire that occur during viral infections may be sufficient to modulate NK cell activity.73 For instance, in measles virus infection, quantitative peptide elution has shown that, although relatively few viral epitopes are presented by HLA‐C, they can be of extremely high abundance.74 Activating receptors for MHC class I:peptide complexes The specificity and role of activating receptors for MHC class I have been more challenging to unearth. NKG2C has a lower affinity than its inhibitory counterpart NKG2A.75 However, NKG2C is associated with adaptive NK cells in CMV+ individuals, suggesting that they are involved in the control of CMV infection.76 This appears to be related to the recognition of the UL40 peptide, which is similar in sequence to MHC class I leader peptides.77 Both NKG2A and NKG2C recognize the UL40 peptide, and hence, cells expressing NKG2A may be prevented from expanding by this inhibitory signal leading to domination of the NK cell repertoire by NKG2A– cells. In TAP1‐deficient patients there is an expanded NKG2C+ NK cell population, which may contribute to anti‐viral immunity and in healthy blood donors, NK cells expressing activating KIR can also be expanded, implying that NK cell expansions can be driven by any receptor associating with DAP12, rather than purely through NKG2C.76, 78 The activating counterparts of inhibitory KIR2DL1 and KIR2DL2/L3 are KIR2DS1 and KIR2DS2, respectively. Based on their high sequence homology, these activating KIRs share similar HLA‐C specificities. KIR2DS1 binds HLA‐C group 2, in contrast to KIR2DL1, which binds both HLA‐C group 1 and group 2 alleles.79 KIR2DS2 appears to have a subtly different specificity from its inhibitory counterparts KIR2DL2 and KIR2DL3, having a tyrosine for phenylalanine substitution at residue 45, adjacent to residue 44 which defines the HLA‐C specificity of the KIR molecule.80 Recent work has shown that KIR2DS2 specifically recognizes peptides derived from the NS3 helicase of plus‐strand RNA viruses in the context of HLA‐C alleles. These include HCV and a number of related globally important flaviviruses such as dengue virus, Zika virus, Japanese encephalitis virus, tick‐borne encephalitis virus and West Nile virus. The peptide in the NS3 protein from flaviviruses contains a unique ‘MCHAT’ motif that is not present in the human genome and is recognized by KIR2DS2. This viral motif is present in 61 out of 63 flaviviruses, which are highly divergent in other regions of their genome. This unusually high degree of conservation has a structural basis, in that it forms part of the RNA‐binding motif of the helicase protein, which is critical to viral replication.81 Flaviviruses are carried by insect vectors and cause a wide spectrum of disease across the globe. For instance, tick‐borne encephalitis virus is a problem in temperate regions, whereas Zika and dengue virus infections are more common in tropical regions.82-84 Hence, as a family, these viruses have the potential to exert a huge selection pressure on the immune system. The observation that the MCHAT sequence is present in many different flaviviruses and is absent in humans is strongly suggestive that pathogenic flaviviruses are a key driver of the evolution of KIR2DS2. Finally, although KIR3DS1 has a high sequence homology to the inhibitory KIR3DL1 molecule, binding of KIR3DS1 to HLA‐B has been largely inferred from sequence homology and disease association studies, especially in HIV‐1 infection. It has been shown that KIR3DS1 can bind HIV‐derived peptides presented by HLA‐B, but the relevance of this for HIV‐1 infection is not clear at present.85 More recently, it has been demonstrated that KIR3DS1 recognizes open conformers of HLA‐F.54 These are up‐regulated in HIV‐1 and HCV infections, indicating that this may be a more general mechanism for the recognition of viruses.55 Conversely, peptide‐loaded HLA‐F binds LILRB1 with high affinity.86 As LILRB1 is expressed on both NK cells and macrophage/monocytes, this interaction may be important for the immune response generated by one or both cell types. NK cell immune evasion by viruses: effects on MHC class I receptors The diversity of viral pathogens for humans is enormous. They cause different types of infections including acute severe infection or more indolent chronic conditions, which may or may not be associated with disease. For example, DNA viruses such as the herpeseviruses cause long‐term latent infections, with little long‐term human disease in immunocompetent hosts. They can accommodate homologues of human genes to counteract immune defences, an escape mechanism not available for the much smaller RNA viruses. This allows DNA viruses to have multiple methods of modulating the immune system, targeting both T cells and NK cells. Human CMV encodes multiple proteins such as US2, US3, US6, US10, US11 and UL83, which down‐regulate the expression of HLA class I molecules.45 This mechanism allows viruses to avoid T‐cell recognition, but leaves infected cells susceptible to NK cell killing. CMV express ligands for NK cell inhibitory receptors by multiple pathways, which overcomes this vulnerability (Fig. 3). In this regard, US2 and US11 proteins only target HLA‐A and HLA‐B, leaving HLA‐C and HLA‐E available for interaction with inhibitory NK receptors.87, 88 Additionally, the CMV‐encoded protein UL40 expresses a sequence identical to the leader peptide of some HLA‐C alleles.89 This peptide can bind HLA‐E and serve as ligand for inhibitory CD94:NKG2A receptors.90, 91 Furthermore, UL18, an MHC class I homologue expressed by CMV, can inhibit NK cells through interaction with LILRB1.92 CMV also targets the activating NKG2D pathway through UL16, UL142, US9, US18 and US20, which prevents expression of MICA, MICB or UL16 binding protein ligands on the cell surface.93-97 The net result of these interactions is that the virus can co‐exist with its human host in the majority of individuals, in general becoming problematic to human health only following in utero transmission, or in the iatrogenic context of immunosuppression or transplantation. While these multiple mechanisms have been best demonstrated for human CMV, other herpesviruses also down‐regulate MHC class I and inhibit NK cell function. The K3 protein of human herpesvirus‐8 targets HLA‐A, ‐B and ‐C, whereas the K5 protein preferentially targets HLA‐A and ‐B, as well as multiple ligands for NK cell receptors including MICA, MICB and activation‐induced C‐type lectin (reviewed in ref. 98). In contrast to DNA viruses, flaviviruses do not specifically target MHC class I. Instead, they have developed numerous mechanisms for attenuating type I interferon signalling.99 Despite this, NK cells are activated in the acute phase of flaviviral infection and precede T‐cell responses. At this phase of infection, an enhanced NK cell response may speed up clearance of the virus and so reduce transmission, providing enhanced protection on a population, as well as an individual basis. Protective effects of KIR–MHC–peptide against RNA viruses In general, RNA viruses cause acute infections, with some exceptions such as HIV‐1 and HCV. Genetic studies of these chronic infections have informed KIR biology and demonstrate the important role that KIR diversity may have on the outcome of the infection. For instance, protection against HIV‐1 has been associated with KIR3DS1, and also different alleles of KIR3DL1.5, 30 For HCV infection, different KIR genotypes have been associated with protection, with the most prominent being KIR2DL3 and HLA‐C group 1. This was originally identified in both a UK Caucasian and an African American population.4 These data illustrate the influence that inhibitory receptors can have on the outcome of viral infections, and in the absence of substantial HLA‐C down‐regulation by either of these viruses, its protective effect may be more related to changes in peptide content (Fig. 3).69, 70, 72 Intriguingly, HCV can also present a peptide that is recognized by KIR2DS2 in the context of HLA‐C*0102, and in the UK population, KIR2DS2 is protective against HCV infection.81 Similar to the peptide in the flaviviruses, this peptide is also present in the NS3 helicase region of the virus and directly contacts the viral RNA. The peptide LNPSVAATL is conserved among all HCV genotypes, which in general share approximately only 70% nucleotide identity.100 Key to its critical function in viral replication, mutation of the KIR2DS2 binding residues (alanine P7 and threonine P8) abrogate HCV replication. Interestingly, LNPSVAATL is in the Walker 1a, rather than the Walker 1b motif, showing that KIR2DS2 recognizes distinct RNA‐binding viral sequences, rather than a single motif. It may be therefore that KIR2DS2 represents an adaptation of the host to RNA viruses. This begs the question as to whether the other activating KIR may have similar, as yet unrecognized functions in recognition of pathogens. Concluding remarks The MHC class I receptors on NK cells provide a remarkably elaborate system for controlling the functions of NK cells in the context of the diverse nature of human pathogens. Overall, there are a number of key interactions that are well established, and valuable new insights into the roles of the individual receptor–ligand pairings are now being gained. The diversity of these interactions highlights how a system of non‐rearranging receptors has adapted to the various challenges of infectious diseases that can range from latent to fatal infection. Understanding the interactions between a broad range of viruses and NK cells may be the key to unravelling the complex network of receptors and ligands that determine NK cell function. Funding LB‐L was funded by a scholarship from the Departamento administrativo de Ciencia, Tecnologia e Innovacion – Colciencias, the University of Southampton and the Newton Fund, and research in SIKs group is supported by The MRC. Author contribution LB‐L and SIK wrote the manuscript. Disclosures None. References
|
|
Suggested by
Société Francaise d'Immunologie
January 7, 2019 1:31 PM
|
Immune evasion strategies employed by intracellular pathogens Pathogens and their hosts co‐evolve, and there are clear signs of selective pressure on host factors such as DNA and RNA sensors on the one hand and pathogen‐encoded immune evasion proteins on the other.65-67 Immunomodulatory proteins and virulence factors are finely tuned to adapt to the host range and life cycle of the pathogen. The precise interplay between host and pathogen factors is often unique, and can differ in different host organisms, cell types and among even closely related pathogens. However, mapping these host–pathogen interactions at a molecular level can provide clues about the importance of host signalling cascades, can help us to understand changes in species specificity and virulence of emerging pathogens, and aid in the design of vaccine vectors. As PRR signalling pathways are being characterized in more molecular detail, the intricate counterstrategies employed by pathogens to evade recognition are also becoming apparent. Some general principles by which intracellular pathogens hide from detection or intercept the cell's signalling cascades are described below. Sequestration of PAMPs Pathogens that reside inside host cells are already sheltered from the immune system to some extent, by avoiding exposure to antibodies or complement components. However, due to the existence of intracellular PRRs, additional camouflage strategies are essential for the establishment of infection. Intracellular bacteria and protozoan parasites often co‐opt vacuoles as a niche for replication, which prevents pathogen‐derived nucleic acids and other PAMPs from being exposed to the cell's PRRs. Hence, detection of intracellular nucleic acids during bacterial infection often requires the presence of bacterial secretion systems. For instance, the type VII secretion system ESX from Mycobacterium tuberculosis is responsible for the exposure of bacterial DNA to cGAS in macrophages, but also secretes virulence factors that interfere with host functions.56, 68 Viruses require greater access to host factors for replication than bacteria, but also try to shield their nucleic acids from detection. Some RNA viruses, including Dengue virus and hepatitis C virus, sequester their genome and replication machinery in membrane‐bound compartments, which function to create locally high concentrations of replication factors, as well as hiding viral RNA genomes from recognition by RIG‐I.69, 70 Human immunodeficiency virus type 1 carries out reverse transcription and replication of its genome inside its capsid, which contains selective pores to allow entry for nucleotides from the host cell, while shielding viral DNA from recognition by cGAS.71 Modification of viral RNA and DNA Many pathogens aim to keep PAMP levels at a minimum: coronaviruses for instance quickly degrade any excessive dsRNA formed during the viral life cycle,72 and Group B streptococcus degrades cyclic di‐AMP using an ectonuclease.73 However, the production of nucleic acid PAMPs cannot be avoided altogether; thus, more sophisticated strategies of camouflage have evolved, so that the pathogen can blend into the cellular environment. As viral RNA polymerases generate RNA species with a 5′ triphosphate moiety, many viruses employ additional strategies to modify their RNA, so that it is not recognized efficiently by RIG‐I. For instance, Picornaviridae, Caliciviridae and Astroviridae covalently attach a protein, Vpg, to the 5′ end of viral RNAs, which prevents RIG‐I‐mediated recognition.15 Processing of the negative‐strand ssRNA genome of members of the Bornaviridae and Bunyaviridae families involves the cleavage of the first nucleotide by a viral endonuclease to generate a monophosphate group at the 5′ end.74 Viruses that transcribe their mRNAs in the nucleus, including the DNA viruses of the Herpesviridae and Papillomaviridae families and retroviruses such as human immunodeficiency virus, co‐opt the cell's own capping machinery to protect the 5′ end of their mRNAs with a 7‐methylguanosine cap, while others, including IAV, use ‘cap snatching’ to remove the capped 5′ ends from cellular mRNAs and incorporate them into viral RNA transcripts.75 Many viruses, including poxviruses and flaviviruses, encode their own capping enzymes that synthesize RNA caps that are indistinguishable from the mammalian cap structure.75 Yellow fever virus in addition recapitulates the 2′ O‐methylation of the first RNA nucleotide next to the cap, which is found in cellular mRNAs and further decreases recognition by RIG‐I.76 Bacteria and protozoa also cap their mRNAs, but not always with 100% efficiency. RNA derived from intracellular bacteria can activate the RNA sensing pathway if it reaches the cytosol, but it remains to be determined whether this is important during infection.77 So far, it is not known whether DNA modifications could prevent recognition by cGAS or other DNA sensors. It has been proposed that IFI16 may be able to distinguish viral DNA from the cell's own genome by recognizing longer (>40 nucleotides) stretches of free DNA,43, 44 and the detection of DNA by cGAS has also been shown to be length‐dependent.78 It remains to be tested whether the assembly of nucleosomes on the genomes of DNA viruses such as herpesviruses and papillomaviruses could be a strategy to limit their detection by intracellular DNA sensors. Degradation and inhibition of host signalling factors All intracellular pathogens encode virulence factors that interfere with the host's signalling cascades. Viral immunomodulatory proteins are usually expressed as immediate early genes, or are even part of the viral particle, so that they are able to inhibit the host's signalling cascades as soon as PAMPs are detected early in infection. Intracellular bacteria employ secretion systems to transport effector proteins through the vacuolar and bacterial membranes into the host cell, whereas protozoans can secrete virulence factors via exosomes or other membrane‐bound vesicles. A vast repertoire of virulence factors that influence the cell's innate immune signalling cascades have been described, particularly in viruses, which often dedicate a large portion of their genome to interfering with the host's innate immune response. Although many viruses encode only a few proteins, these are often multi‐functional and target several key host factors. Large DNA viruses, such as poxviruses and herpesviruses, encode a larger repertoire of dozens of immunomodulatory proteins that interfere with anti‐viral signalling cascades in the cell at multiple points.79, 80 Bacteria and protozoa encode thousands of genes, and so have an even greater capacity to interfere with host functions, but comparatively few immune evasion proteins have been described so far, with many pathogen‐encoded effector proteins still uncharacterized.3, 4, 64 Many pathogens have evolved similar strategies to inhibit the innate immune signalling cascades in the host cell: virulence factors act to either eliminate host signalling factors by degradation, sequester them or block their function in the signalling cascade. As we learn more about the regulation of innate immune signalling cascades that detect pathogens, more examples of counterstrategies employed by pathogens also emerge. Degradation and inhibition of RNA sensors Since the discovery of the intracellular RNA sensing system, many immune evasion proteins that target RLRs or MAVS have been identified (see Fig. 1), mostly in viruses with an RNA genome, for which RIG‐I and/or MDA5 are the key PRRs during infection. Some viral proteases cleave RNA sensors, with several picornaviruses using their 3C protease to cleave RIG‐I, and the 2A protease to cleave MDA5.81-83 The leader protease Lpro from foot‐and‐mouth‐disease virus also cleaves Lpg2, a co‐factor for MDA5 activation.84 Some viruses modify RLRs with K48‐linked poly‐ubiquitin chains, diverting the RNA sensors for degradation by the cell's proteasome. Toscana virus non‐structural proteins and the rotavirus NSP1 protein cause the degradation of RIG‐I,85, 86 whereas West Nile virus NS1 targets both RIG‐I and MDA5.87 RIG‐I mRNA expression and translation can also be inhibited during viral infection: for instance, EBV expresses the virus‐encoded microRNA miR‐BART6‐3p, which targets RIG‐I mRNA,88 and hepatitis B virus induces the cellular microRNA miR146a, which inhibits RIG‐I expression.89 Even under conditions where the expression of RIG‐I and MDA5 is intact, the RNA sensors can be prevented from carrying out their signalling function by viral proteins that bind to them. The HSV‐1 protein UL37 interacts with RIG‐I and causes the de‐amidation of its helicase domain, which renders RIG‐I unable to sense RNA ligands.90 Another HSV‐1 protein, US11 inhibits RNA sensing by associating with the dsRNA binding protein PACT, which potentiates RNA‐induced responses.91, 92 PACT is also targeted by Influenza A virus NS1, the VP35 protein from Ebola virus and the 4a protein from Middle East respiratory syndrome coronavirus.93-95 Many of the PACT‐interacting proteins also bind dsRNA, so they probably shield the viral RNA from detection while at the same time inactivating PACT and RNA sensors. The activity of RIG‐I and MDA5 is tightly regulated in the cell: In the absence of infection, the CARD of the RNA sensors are kept in a phosphorylated state, and activation involves their dephosphorylation catalysed by protein phosphatase 1.96 RIG‐I activity is further enhanced by the assembly of K63‐linked poly‐ubiquitin chains catalysed by the E3 ubiquitin ligases tripartite motif containing 25 (TRIM25) and Riplet, which release RIG‐I from its autoinhibited state.97, 98 Given the importance of these post‐translational modifications, it is not surprising that many viruses have evolved ways of inhibiting these regulatory mechanisms. For instance, measles virus uses an elaborate signalling strategy involving the activation of the C‐type lectin DC‐SIGN to inhibit protein phosphatase 1, thus keeping the RLRs phosphorylated and inactive.99 The E3 ubiquitin ligase Riplet is inhibited by the multifunctional IAV NS1 protein100 and is cleaved by the NS3/4A protease from hepatitis C virus.101 Multiple viruses also inhibit TRIM25, including again IAV NS1, the SARS coronavirus N protein, the V protein from various paramyxoviruses, the large tegument protein BPLF1 from EBV and the E6 protein from human papillomavirus 16.102-107 The subgenomic flavivirus RNA from Dengue virus can also bind and inactivate TRIM25 in an RNA sequence‐specific manner.108 RIG‐I ubiquitylation by TRIM25 is also inhibited by the bacterial quorum sensing molecule cyclo(Phe‐Pro) from the opportunistic pathogen Vibrio vulnificus. Cyclo(Phe‐Pro) specifically binds to RIG‐I and prevents it from being ubiquitylated by TRIM25,109 possibly providing a link between bacterial infection and susceptibility to co‐infection with viruses. A multitude of viral immunomodulators prevent RIG‐I and MDA5 from interacting with its adaptor protein MAVS, so blocking the nucleation event that allows MAVS to form higher‐order signalling assemblies. Dengue virus NS3 binds 14‐3‐3ε to prevent the translocation of RIG‐I to MAVS.110 The interaction between RLRs and MAVS is also disrupted by the picornavirus 3Cpro proteases, the Z and N proteins of some arenaviruses, NS2 from respiratory syncytial virus, NS1 from IAV, NSP1 from rotavirus and US11 from HSV‐1.16, 86, 111-114 MAVS is also targeted directly by many viruses. MAVS‐interacting proteins include the metapneumovirus protein M2‐2,115 the NS4A proteins of Zika and Dengue viruses,116, 117 viral IRF1 from human herpesvirus 8118 and ORF9b from SARS coronavirus.119 MAVS is also diverted for proteasome‐mediated degradation by the hepatitis B virus X protein,120 and is cleaved by the hepatitis C virus protease NS3/4A, which releases it from the mitochondria and other intracellular membranes to disrupt signalling.121-124 The US9 protein from HSV‐1 causes MAVS to leak from the mitochondria by disrupting the mitochondrial membrane potential,125 and the IAV protein PB1‐F2 decreases mitochondrial membrane potential causing mitochondrial fragmentation.126, 127 Disrupting mitochondrial physiology is a common mechanism to block MAVS signalling. Infection with Dengue and Zika viruses causes mitochondrial elongation, which also blocks MAVS function.128 The sustained interferon production caused by MAVS signalling from the peroxisomes is inhibited by the MIA protein from human cytomegalovirus (hCMV) and the VP16 protein from HSV‐1.118, 129, 130 Although there are abundant examples of inhibition of RNA sensing by pathogens, and in particular viruses, there is one instance where a pathogen actually enhances signalling by RIG‐I and MDA5. The food‐borne pathogen Salmonella typhimurium uses its effector protein SopA, an E3 ubiquitin ligase, to ubiquitylate the host proteins TRIM56 and TRIM65, which in turn promote RIG‐I and MDA5 signalling.131, 132 This is an example of subversion, rather than evasion, of the interferon response, in line with the observation that the production of type I interferons can be advantageous to the pathogen, rather than the host, during some bacterial infections.64 Degradation and inhibition of DNA sensors Even though the cGAS/STING DNA sensing pathway was only discovered relatively recently, several viral and bacterial virulence factors that target this pathway have already been discovered, see Fig. 2. The nuclear DNA viruses hCMV, HSV‐1 and Kaposi's sarcoma‐associated herpesvirus all target several key DNA sensing factors to prevent the detection of their genomic DNA. HSV‐1 uses its ICP27 protein to inhibit STING.133 In addition, the E3 ubiquitin ligase ICP0 causes the degradation of IFI16 protein, and the virion host shutoff protein UL41 promotes the turnover of the mRNAs encoding IFI16 and cGAS.42, 134, 135 In addition, the HSV‐1 virion protein VP22 interacts with cGAS and inhibits its enzymatic activity136 and also interacts with AIM2 and blocks its oligomerization.137 HSV‐1 tegument protein UL37, which targets and deamidates RIG‐I, also deamidates cGAS, impairing cGAMP synthesis.138 The deployment of different virulence factors to target several components of the DNA sensing pathway may be necessary to block the pathway more efficiently, and/or to inhibit some non‐overlapping functions of cGAS and IFI16 which have been observed during herpesvirus infection.139 Analogously, several different hCMV proteins inhibit DNA sensing: pUL31 binds to cGAS and dissociates it from DNA,140 pUL83 inhibits both cGAS and IFI16,141-143 pUL82 inhibits STING translocation,144 IE2 causes STING degradation,145 and US9 inactivates both MAVS and STING.125 Furthermore, pUL83 binds AIM2 and facilitates the degradation of AIM2‐driven inflammasomes.146 A similar multi‐pronged approach has also been observed for the gammaherpesvirus Kaposi's sarcoma‐associated herpesvirus.147-150 STING is also inhibited by oncoproteins from the nuclear DNA viruses human adenovirus and human papillomavirus,151 and by vaccinia virus, a DNA virus that resides in the cytosol.152 Vaccinia virus also inhibits DNA‐PK, using its virulence factor C16 to bind the Ku70/Ku80 subunits of the DNA‐PK complex.153 The viral inhibitor of RIP activation (vIRA) from mouse CMV targets another proposed DNA sensor, DAI, to prevent the induction of programmed necrosis upon viral infection.154 Surprisingly, not only DNA viruses but also some RNA viruses have been found to antagonise STING – even though they do not produce DNA or cyclic dinucleotides during their replication cycle. It has been reported that STING can function in a cGAS‐independent manner during the detection of viral membrane fusion, for instance during infection with IAV.155 This non‐canonical STING signalling pathway is antagonized by the IAV fusion peptide.156 Flaviviruses, enveloped viruses with a positive‐stranded ssRNA genome, also inhibit STING‐dependent DNA sensing. Viral NS2B proteases encoded by Dengue virus, Zika virus, West Nile virus and Japanese encephalitis virus cleave human STING protein, but not its mouse orthologue.157, 158 The dengue virus NS2B co‐factor also targets cGAS for degradation.55 This prevents the activation of an innate immune response after the release of mitochondrial DNA, which occurs during Dengue virus infection,55, 159 highlighting the breadth of pathogen classes that can be detected directly or indirectly by the DNA sensing pathway (Fig. 2). While the production of type I interferons is not always an effective strategy to limit bacterial infections, the activation of STING by bacterial DNA or cyclic dinucleotides can also promote autophagy to clear bacteria from the infected cells. For this reason, some intracellular bacteria also inhibit STING.62 For instance, the Shigella effector protein IpaJ inhibits STING translocation from the endoplasmic reticulum to endoplasmic reticulum–Golgi intermediate compartment,38 and the Yersinia YopJ protein also blocks STING trafficking and causes its de‐ubiquitylation.160 Mycobacterium tuberculosis secretes the cyclic di‐nucleotide phosphodiesterase CdnP (also known as Rv2837c), which degrades cGAMP and bacterial cyclic dinucleotides, thus inhibiting both DNA‐ and cyclic‐dinucleotide‐induced STING activation.161 Group A streptococcus, Streptococcus pyogenes, subverts, rather than evades, STING signalling: it uses its M protein to activate STING, resulting in the production of the anti‐inflammatory cytokine interleukin‐10 downstream of type I interferon signalling.162 In this way, the bacterium exploits the reciprocal antagonism between the interferon response and inflammation, and shapes the immune response to favour the pathogen, rather than the host.
|
|
Scooped by
Gilbert C FAURE
December 24, 2018 11:40 AM
|
Dengue virus (DENV) and Zika virus (ZIKV) are mosquito-borne pathogens that have a significant impact on human health. Immune sera, mAbs, and memory B cells (MBCs) isolated from patients infected with one DENV type can be cross-reactive with the other three DENV serotypes and even more distantly related flaviviruses such as ZIKV. Conventional ELISPOTs effectively measure Ab-secreting B cells but because they are limited to the assessment of a single Ag at a time, it is challenging to distinguish serotype-specific and cross-reactive MBCs in the same well. We developed a novel multifunction FluoroSpot assay using fluorescently labeled DENV and ZIKV (FLVs) that measures the cross-reactivity of Abs secreted by single B cells. Conjugation efficiency and recognition of FLVs by virus-specific Abs were confirmed by flow cytometry. Using a panel of DENV immune, ZIKV immune, and naive PBMC, FLVs were able to simultaneously detect DENV serotype-specific, ZIKV-specific, DENV serotype cross-reactive, and DENV/ZIKV cross-reactive Abs secreted by individual MBCs. Our findings indicate that the FLVs are sensitive and specific tools to detect specific and cross-reactive MBCs. These reagents will allow the assessment of the breadth as well as the durability of DENV/ZIKV B cell responses following vaccination or natural infection. This novel approach using FLVs in a FluoroSpot assay can be applied to other diseases such as influenza in which prior immunity with homosubtype- or heterosubtype-specific MBCs may influence subsequent infections.
|
|
Scooped by
Gilbert C FAURE
October 10, 2018 2:49 PM
|
|
|
Scooped by
Gilbert C FAURE
May 7, 2017 5:51 AM
|
Publication date: 4 May 2017
Source:Cell, Volume 169, Issue 4
Author(s): Davide F. Robbiani, Leonia Bozzacco, Jennifer R. Keeffe, Ricardo Khouri, Priscilla C. Olsen, Anna Gazumyan, Dennis Schaefer-Babajew, Santiago Avila-Rios, Lilian Nogueira, Roshni Patel, Stephanie A. Azzopardi, Lion F.K. Uhl, Mohsan Saeed, Edgar E. Sevilla-Reyes, Marianna Agudelo, Kai-Hui Yao, Jovana Golijanin, Harry B. Gristick, Yu E. Lee, Arlene Hurley, Marina Caskey, Joy Pai, Thiago Oliveira, Elsio A. Wunder, Gielson Sacramento, Nivison Nery, Cibele Orge, Federico Costa, Mitermayer G. Reis, Neena M. Thomas, Thomas Eisenreich, Daniel M. Weinberger, Antonio R.P. de Almeida, Anthony P. West, Charles M. Rice, Pamela J. Bjorkman, Gustavo Reyes-Teran, Albert I. Ko, Margaret R. MacDonald, Michel C. Nussenzweig
Antibodies to Zika virus (ZIKV) can be protective. To examine the antibody response in individuals who develop high titers of anti-ZIKV antibodies, we screened cohorts in Brazil and Mexico for ZIKV envelope domain III (ZEDIII) binding and neutralization. We find that serologic reactivity to dengue 1 virus (DENV1) EDIII before ZIKV exposure is associated with increased ZIKV neutralizing titers after exposure. Antibody cloning shows that donors with high ZIKV neutralizing antibody titers have expanded clones of memory B cells that express the same immunoglobulin VH3-23/VK1-5 genes. These recurring antibodies cross-react with DENV1, but not other flaviviruses, neutralize both DENV1 and ZIKV, and protect mice against ZIKV challenge. Structural analyses reveal the mechanism of recognition of the ZEDIII lateral ridge by VH3-23/VK1-5 antibodies. Serologic testing shows that antibodies to this region correlate with serum neutralizing activity to ZIKV. Thus, high neutralizing responses to ZIKV are associated with pre-existing reactivity to DENV1 in humans.
Graphical abstract Teaser Individuals with high neutralizing antibody response against Zika virus have expanded clones of B cells that express the same heavy and light immunoglobulin genes and that are cross-reactive against dengue 1 virus.
|
|
Scooped by
Gilbert C FAURE
August 19, 2016 1:06 AM
|
Dengue is caused by infection with any of the four dengue virus serotypes. This PrimeView highlights the mechanisms underlying the clinical course of a dengue infection, which can range from mild febrile illness through to haemorrhagic fever and circulatory shock.
|
|
Scooped by
Gilbert C FAURE
July 19, 2016 1:22 AM
|
Zika virus (ZIKV), a mosquito-borne flavivirus with homology to Dengue virus (DENV), has become a public health emergency. By characterizing memory cells from ZIKV-infected patients, we dissected ZIKV-specific and DENV-crossreactive immune responses. Antibodies to NS1 were largely ZIKV-specific and were used to develop a serological diagnostic tool. In contrast, antibodies against E protein domain I/II (EDI/II) were cross-reactive and, while poorly neutralizing, potently enhanced ZIKV and DENV infection in vitro and lethally enhanced DENV disease in mice. Memory T cells against NS1 or E proteins were poorly crossreactive, even in donors pre-exposed to DENV. The most potent neutralizing antibodies were ZIKV-specific and targeted EDIII or quaternary epitopes on infectious virus. An EDIII-specific antibody protected mice from lethal ZIKV infection, illustrating the potential for antibody-based therapy.
Flaviviruses--such as Zika, dengue, and yellow fever--have emerged as human (and other primate) pathogens because of their ability to specifically overcome our anti-viral defenses. In the case of Zika..
Via Kenzibit
|
|
Scooped by
Gilbert C FAURE
January 20, 2016 9:09 AM
|
Both dengue NS1 antigen and serum interleukin (IL)-10 levels have been shown to associate with severe clinical disease in acute dengue infection, and IL-10 has also been shown to suppress dengue-specific T cell responses.
|
|
|
Rescooped by
Gilbert C FAURE
from EntomoNews
December 20, 2022 2:01 PM
|
Discussed the current research on the role of molecular mechanisms in mediating immune priming in insects and regulating vector-borne disease transmission. Modulation of insect immunity to control vector-borne diseases By Dr. Chinta Sidharthan Dec 19 2022 Reviewed by Aimee Molineux ------- NDÉ Traduction Contexte La dengue, le paludisme, la filariose et le Zika sont quelques-unes des principales maladies infectieuses transmises par des insectes dans le monde. Au cours des dernières décennies, la dengue et le paludisme ont augmenté de manière significative. En outre, bien que les insecticides réduisent la propagation des maladies transmises par les insectes dans certaines régions du monde, la résistance croissante aux insecticides dans les populations naturelles d'insectes indique la nécessité de trouver d'autres stratégies pour limiter la transmission des maladies transmises par les insectes. L'un des domaines qui retient l'attention est l'amorçage immunitaire pour réduire la transmission de la maladie. La compétence du vecteur, c'est-à-dire sa capacité à transmettre l'agent pathogène, dépend de sa réponse immunitaire. Chez les insectes, l'immunité est régulée par des voies de signalisation telles que les voies c-Jun N-terminal kinase (JNK), Janus kinase-signal transducteur et activateur de transcription (JAK-STAT), immunodéficience (IMD), Toll et interférence de l'acide ribonucléique (ARNi). Les recherches récentes sur les maladies à transmission vectorielle ont porté sur l'utilisation de ces mécanismes moléculaires pour cibler l'amorçage immunitaire et réduire la transmission des maladies.
Le système immunitaire des insectes
Comme les insectes dépendent d'un système immunitaire inné, on pensait qu'ils n'avaient pas la capacité de développer et de maintenir une réponse immunitaire adaptative après une exposition à des agents pathogènes. Cependant, des études ont mis en évidence l'existence d'un amorçage immunitaire chez les insectes, où l'exposition à des agents pathogènes entraîne une modification durable des cellules qui renforce la réponse immunitaire lors d'infections ultérieures. Chez les blattes (Periplaneta americana), il a été démontré que l'immunisation par Pseudomonas aeruginosa inactivé protégeait les insectes contre les infections par la bactérie vivante, et que les effets duraient des semaines. Des résultats similaires ont été observés chez la drosophile immunisée avec Streptococcus pneumoniae. Les études montrent que l'amorçage immunitaire peut être spécifique ou non de l'agent pathogène et peut s'étendre à d'autres stades de vie de l'insecte. Lorsque P. americana immunisé contre P. aeruginosa a été exposé à d'autres bactéries, les effets protecteurs n'ont duré que trois jours. Cependant, il a été démontré que l'amorçage chez les larves d'insectes augmentait l'immunité chez la forme adulte. Il a également été démontré que d'autres facteurs, tels que le stress dû à un manque de nutrition, la compétition et les blessures, produisent des phénotypes similaires à l'amorçage. Bien que les preuves suggèrent que l'amorçage immunitaire est similaire à la mémoire immunitaire, les voies et les mécanismes moléculaires restent largement inexplorés.
Preuve de l'amorçage immunitaire
L'immunité antivirale chez la drosophile adulte est renforcée lorsque les hémocytes produisent un petit ARN interférent (ARNi) viral secondaire en utilisant l'acide désoxyribonucléique (ADN) viral comme matrice. L'ARNi est délivré par des vésicules de type exosome à d'autres tissus de l'insecte. Une étude sur le virus C de la drosophile a montré que l'infection orale du virus chez les larves de drosophiles augmentait la tolérance à l'infection chez les formes adultes. Les drosophiles femelles exposées à des virus à ARN simple brin positifs ont présenté un amorçage immunitaire transgénérationnel (TGIP) avec une immunité antivirale spécifique de la séquence et dépendante de l'ARN chez la progéniture pour les cinq générations suivantes. Des TGIP similaires ont été observés chez les larves de moustiques Aedes aegypti lorsque les femelles adultes ont été exposées au virus du chikungunya. Bien que l'on pense que l'ADN viral joue un rôle important dans la TGIP, les mécanismes de transfert et d'amplification de l'ADN viral restent flous. Les moustiques anophèles ont montré une immunité renforcée dépendante des hémocytes contre les infections ultérieures après une exposition au Plasmodium. Des études ont signalé le rôle du microbiote intestinal dans l'établissement et le rappel de la mémoire immunitaire antiplasmodiale, qui est permanente et dépend des granulocytes circulants. Les lipides eicosanoïdes tels que les lipoxines et les prostaglandines jouent le rôle de molécules de signalisation dans l'immunité coordonnée observée dans divers tissus d'insectes. Les hèmes-peroxydases HPX7 et HPX8, induites pendant l'infection par Plasmodium, médient la synthèse de la prostaglandine E2 (PGE2) par le microbiote de l'intestin moyen. La libération de PGE2 déclenche la libération du facteur de différenciation des hémocytes, qui est un complexe lipoxine-lipocaline. La PGE2 provoque également une augmentation de la double peroxydase par les cellules de l'adipocyte appelées oenocytes.
Une immunité entraînée
Des recherches récentes ont porté sur l'entraînement immunitaire, dans lequel les niveaux de transcription des effecteurs immunitaires reviennent à l'état basal après l'exposition initiale à l'agent pathogène. L'infection ultérieure entraîne une meilleure réponse des cellules effectrices que dans le cas de l'amorçage immunitaire. L'entraînement immunitaire (...) L'étude Can immune memory impact vector-borne disease transmission? Despite its remarkable plasticity, activation of vector immunity often restricts infection under tolerable levels, instead of completely eliminating the pathogen [52]. Nevertheless, refractory or quasi-refractory populations are observed worldwide [53], and experimental infections of field-caught mosquitoes reveal remarkable variability between individuals. While stochastic variations [54] and genetic components [55,56] are important factors driving this heterogeneity, differences in individual life histories also shape host immunological status [57–60]. Immune priming, immune tolerance, and immune training are likely to be important modulators of individual vector competence. Recently, features of trained immunity were described in nonimmune vertebrate cells, such as epithelial and mesenchymal cells [61], and the role of the gut microbiota has been proposed [62]. Interestingly, the vector gut microbiota is also a major driver of mosquito immunity [63]. It remains to be established whether insect immune priming and trained immunity share some regulatory signaling pathways, such as those activated by the gut microbiota. Thus, priming the immune system of insect vectors is a potential strategy to reduce disease transmission. Manipulation of larvae would be an interesting strategy to reduce vectorial capacity, as infection or immune challenge of larvae, nutritional manipulation, and intraspecific competition have been shown to enhance immunity in adult stages [26,27,64] and logistics to target larval breeding sites are well established [65–67]. While the epigenetic regulation of immunometabolism is an important factor driving susceptibility in vertebrates (and a target for therapeutics), it has only recently started to be investigated in models of disease vectors [40,68,69]. Further identification of molecular markers will make it possible to establish the frequency and intensity of such events in natural populations. [Image] Immune priming in An. gambiae mosquitoes.
Via Bernadette Cassel
|
|
Scooped by
Gilbert C FAURE
August 15, 2020 2:33 AM
|
Antibody-dependent enhancement (ADE) has been described as a mechanism that contributes to the pathogenesis of dengue virus infection. Limited evidence also suggests that it can also occur in other viral infections.
|
|
Scooped by
Gilbert C FAURE
November 28, 2019 2:27 AM
|
Understanding T cell responses to dengue infection is important for developing effective
vaccines. Chng et al. used high-dimensional CyTOF profiling and peptide-HLA tetramer
screening to track dengue-specific T cell activation and differentiation into memory
cells in naturally infected patients. They found that dengue infection causes broad
immune cell activation and that dengue-specific T cells differentiate into two major
cell fates.
|
|
Scooped by
Gilbert C FAURE
January 24, 2019 2:24 PM
|
Children were 38 percent less likely to show signs of Zika infection if they had previously had dengue.
|
|
Suggested by
Société Francaise d'Immunologie
January 9, 2019 2:55 AM
|
Dengue is the most rapidly spreading viral disease transmitted by the bite of infected Aedes mosquitos. The pathogenesis of dengue is still unclear; although host immune responses and virus serotypes have been proposed to contribute to disease severity.
|
|
Scooped by
Gilbert C FAURE
December 29, 2018 1:48 PM
|
PLoS Negl Trop Dis. 2018 Dec 17;12(12):e0006975. doi: 10.1371/journal.pntd.0006975.[Epub ahead of print]...
|
|
Suggested by
Société Francaise d'Immunologie
December 11, 2018 3:30 AM
|
Summary The role of the host extracellular matrix (ECM) in infection tends to be neglected. However, the complex interactions between invading pathogens, host tissues and immune cells occur in the context of the ECM. On the pathogen side, a variety of surface and secreted molecules, including microbial surface components recognizing adhesive matrix molecules and tissue‐degrading enzymes, are employed that interact with different ECM proteins to effectively establish an infection at specific sites. Microbial pathogens can also hijack or misuse host proteolytic systems to modify the ECM, evade immune responses or process biologically active molecules such as cell surface receptors and cytokines that direct cell behaviour and immune defence. On the host side, the ECM composition and three‐dimensional ultrastructure undergo significant modifications, which have a profound impact on the specific signals that the ECM conveys to immune cells at the forefront of infection. Unexpectedly, activated immune cells participate in the remodelling of the local ECM by synthesizing ECM glycoproteins, proteoglycans and collagen molecules. The close interplay between the ECM and the innate immune response to microbial pathogens ultimately affects the outcome of infection. This review explores and discusses recent data that implicate an active role for the ECM in the immune response to infection, encompassing antimicrobial activities, microbial recognition, macrophage activation, phagocytosis, leucocyte population balance, and transcriptional and post‐transcriptional regulation of inflammatory networks, and may foster novel antimicrobial approaches. Introduction To successfully establish an infectious disease, most pathogenic bacteria adhere to the host, invade underlying tissues, and multiply and grow while evading or overcoming host immune defences.1 The underlying host–pathogen interactions are remarkably specific and involve a variety of substrates within the host. The interactions of pathogens with eukaryotic cells have been intensively studied in microbiology, immunology, cell biology, genetics and ecology research. Less attention has been given to the host extracellular matrix (ECM). However, the individual components of the ECM are substrates that pathogens can directly bind to or degrade, facilitating adhesion and penetration into the host; evidence for this started to accumulate 40 years ago.2, 3 Furthermore, the ECM is a fundamental component of the host cellular microenvironment where most of the events leading to infection, disease and tissue repair take place and is also a reservoir of diverse and tissue‐specific signals that feed into immunological pathways.4, 5 Recently, evidence has emerged that the ECM conveys specific signals to cells, thereby modulating essential immune functions, immune cell migration into and within infected tissues, and immune cell activation, proliferation and differentiation. Moreover, the ECM composition undergoes significant alterations during infection and, notably, specific immune cell types appear to contribute to that. Hence, regulatory circuits closely link the ECM and the immune system. Important questions to emerge from these studies include (i) does the ECM play an active role in infection rather than simply providing a scaffold for bacterial adhesion or being a barrier to breach; (ii) which ECM–pathogen interactions significantly impact the ability of pathogens to colonize and invade host tissues, and/or bypass host defences, and influence how host cells respond to pathogens; and (iii) can we interfere with these interactions to develop new antimicrobial strategies or improve existing ones. Here, we briefly review the ECM and its interactions with microbial pathogens, and discuss the evidence for a direct implication of the ECM in the immune response to infection. The ECM: an immunological perspective Most infections and the resulting immune responses are tissue‐specific. Each tissue has distinct ECM signatures that arise from complex and dynamic combinations of up to ~ 300 different proteins in varying concentrations and geometries within the three‐dimensional extracellular space. This ever increasing number of proteins that contribute to matrices (the ‘matrisome’) include approximately 43 collagen subunits, 36 proteoglycans and 200 glycoproteins.6 ECM molecular multiplicity and complexity are amplified by post‐translational modifications, which can unveil cryptic epitopes or generate new ones capable of triggering immune reactions, and alternative splicing, which generates several isoforms with distinct functions.7, 8 For instance, laminin α4 and α5 isoforms in basement membranes contribute to immune cell subtype selectivity during leucocyte recruitment to sites of inflammation.9, 10 Interstitial ECMs, loose fibril‐like matrices that fill the tissue stroma, and basement membranes, laminar sheets that anchor cell layers to underlying tissues, are basic forms of ECM. Additionally, specialized reticular fibre networks combining features of these two ECM structures are found in secondary lymphoid organs.11, 12 The ECM is a highly dynamic yet strictly regulated tissue component. Its composition and normal function are determined and maintained by a fine balance between ECM synthesis, orchestrated by cytokines such as transforming growth factor‐β (TGF‐β), and turnover, accomplished by matrix metalloproteinases (MMPs), a disintegrin and metalloproteinases (ADAMs) and a disintegrin and metalloproteinases with thrombospondin motifs (ADAMTSs), whose activity is controlled by tissue inhibitors of metalloproteinases (TIMPs).13 During injury and infection, these enzymes are produced by activated immune cells such as monocytes/macrophages and promote immune cell migration into sites of infection and tissue damage, and affect their ability to mount inflammatory responses.14 The central dogma of matrix biology describes how the ECM provides structural support for cells and contributes to the unique structure of a tissue. However, this is only one function of the ECM. Host immune responses are carried out in the context of the ECM, so when immune cells contact the ECM, they receive vital instructions for their survival, proliferation, differentiation and activation, in addition to support for adhesion and guidance for migration. Several mechanisms are responsible for the communication between the ECM and cells. One such mechanism is signalling through cell surface adhesion molecules and receptors, including integrins and discoidin‐domain receptors (reviewed in refs 15, 16). Others involve binding, storage, activation and release of secreted molecules with potent immunomodulatory activity, including cytokines, chemokines and growth factors.17, 18 For instance, TGF‐β has been shown in vitro and in vivo to affect activation, proliferation and differentiation of most immune cell types, modulating nearly all stages of the immune response.19 Moreover, bioactive ECM fragments generated by tissue destruction (e.g. hyaluronan and heparan sulphate oligosaccharides) and ECM molecules whose expression is specifically induced upon tissue injury (e.g. fibronectin isoforms containing extra domain A, versican and biglycan) promote inflammation by inducing pro‐inflammatory gene expression or exhibiting chemoattractant properties (reviewed in refs 20, 21). These molecules form a class of endogenous damage‐associated molecular patterns,22 which, by activating pattern recognition receptors (PRRs) such as toll‐like receptors (TLRs) in immune cells (e.g. macrophages and dendritic cells) and non‐immune cells (e.g. fibroblasts and epithelial cells) alert the immune system to tissue damage and infection, which initiates not only pathogen clearance, but also tissue repair.23 Hence, the ECM and the immune system are intertwined: signals from the ECM help to coordinate immune responses and, in turn, immune cells promote ECM repair and regeneration through the release of cytokines such as tumour necrosis factor (TNF), interferon‐γ (IFN‐γ) and TGF‐β, which regulate the expression of many ECM molecules. ECM–pathogen interactions A tale of adhesion and colonization of the host Tissue adherence represents the first essential mechanism that bacteria adopt to colonize the host. Failure to do so results in the organism being removed by physiological cleansing systems at sites of entry. The surface of host cells and the ECM are negatively charged and microbes employ a number of physico‐chemical forces to overcome these repulsive forces and establish interactions between a microbial ligand or ‘adhesin’ and a complementary molecule or ‘receptor’ on the host tissue. These interactions are highly specific, contributing to tissue tropism, species specificity and genetic specificity within a species. Bacterial adhesins are components of capsules, cell walls, pili or fimbriae, and those that bind to ECM components are called ‘microbial surface components recognizing adhesive matrix molecules’. Host receptors are usually glycoproteins found on the cell membrane and ECM components.24 The binding of microbial pathogens to specific ECM proteins has been extensively reviewed elsewhere1, 3, 25, 26 and will be briefly discussed here. The first report of a host ECM–pathogen interaction was published in 1978 by Kuusela et al.2 who studied the binding of Staphylococcus aureus to fibronectin and, a few years later, revealed two separate binding sites on fibronectin, in the N‐terminus and C‐terminus, respectively.27 Other groups further characterized the interaction of this ubiquitous and promiscuous ECM glycoprotein with Staphylococcus aureus and Streptococcus pyogenes, which has a remarkably large number of fibronectin binding adhesins.28-33 Several other ECM proteins such as laminin, collagen, heparan and chondroitin sulphate, vitronectin, thrombospondin, elastin, bone sialoprotein and tenascin‐C, have since been implicated in specific interactions with pathogenic bacteria26, 34 (Table 1). ECM molecule Pathogen Adhesin Effect of interaction Disease References Fibronectin Enterohaemorrhagic Escherichia coli O157:H7 Lpf fimbriae (LpfA1 major subunit) Colonization of GI tract Acute diarrhoea; bloody diarrhoea; haemolytic uraemic syndrome 130 Streptococcus pyogenes (group A streptococci, GAS) Protein F1 (functional upstream domain) Fibronectin links F1 to integrin receptors, helping bacterial uptake Tonsillopharyngitis; necrotizing fasciitis; myositis; streptococcal toxic shock syndrome 131-133 Protein F2 (C‐terminal domains) Host cell adhesion and internalization 33 SfbII (C‐terminal domain) Host cell adhesion and internalization 134 Fba Host cell adhesion and internalization 31* Staphylococcus aureus MntC Mucosal colonization Nosocomial infections, septicaemia, osteomyelitis, endocarditis, etc. 135 Salmonella typhimurium MisL (N‐terminal non‐conserved region) Intestinal colonization Gastroenteritis 136* ShdA 137 Plasma fibronectin Borrelia burgdorferi BBK32 Binding to fibronectin 13FnIII repeat module and intestinal colonization Lyme disease 35 Fibronectin N‐terminal proteolytic fragments (30 and 70 kDa) Streptococcus pyogenes Protein F2(C‐terminal domains) Fibronectin polymerization and colonization of vascular surfaces Tonsillopharyngitis; necrotizing fasciitis; myositis; streptococcal toxic shock syndrome 33 130 Laminin EnterohaemorrhagicEscherichia coli O157:H7 Lpf fimbriae (LpfA1 major subunit) Eukaryotic cell adhesion and internalization Acute diarrhoea; bloody diarrhoea; haemolytic uraemic syndrome 130 EnterohaemorrhagicEscherichia coli O157:H7 Lpf fimbriae (LpfA1 major subunit) Colonization of GI tract Acute diarrhoea; bloody diarrhoea; haemolytic uraemic syndrome 135 Staphylococcus aureus MntC Colonization of GI tract Nosocomial infections, septicaemia, osteomyelitis, endocarditis, etc. 138 Streptococcus gallolyticus (gallolyticus endocarditis isolates) FimB, gtf and pilB Mucosal colonization Infective endocarditis 139 Collagen I Borrelia burgdorferi ErpX Adhesion and invasion of endothelial cells Lyme disease 138 Streptococcus gallolyticus (gallolyticus endocarditis isolates) FimB, gtf and pilB Long‐term host tissue colonization Infective endocarditis 137 Salmonella typhimurium ShdA Adhesion and invasion of endothelial cells Gastroenteritis 140* Collagen II Enterococcus faecium Pilus subunits EmpA and EmpB Intestinal colonization and persistence UTIs, bacteraemia, and infective endocarditis 138 Collagen IV Streptococcus gallolyticus (gallolyticus endocarditis isolates) FimB, gtf and pilB Adherence to host tissue and biofilm formation Infective endocarditis 130 EnterohaemorrhagicEscherichia coli O157:H7 Lpf fimbriae (LpfA1 major subunit) Adhesion and invasion of endothelial cells Acute diarrhoea; bloody diarrhoea; haemolytic uraemic syndrome 135 Staphylococcus aureus MntC 138 Streptococcus gallolyticus (gallolyticus endocarditis isolates) FimB, gtf and pilB Colonization of GI tract Nosocomial infections, septicaemia, osteomyelitis, endocarditis, etc. 136* Collagen V Salmonella typhimurium MisL (N‐terminal non‐conserved region) Mucosal colonization Infective endocarditis 141 Collagen VI Enterococcus faecium EcbA Adhesion and invasion of endothelial cells Gastroenteritis 142* Tenascin‐C Legionella pneumophila Mip Intestinal colonization UTIs, bacteraemia, and infective endocarditis 138 Vitronectin Streptococcus gallolyticus (gallolyticus endocarditis isolates) FimB, gtf and pilB Host tissue adhesion and biofilm formation Legionellosis 138 Streptococcus gallolyticus (gallolyticus endocarditis isolates) FimB, gtf and pilB Adhesion to lung tissue and bacterial dissemination Infective endocarditis 143* Yersinia enterocolitica YadA Adhesion and invasion of endothelial cells Infective endocarditis 46 Thrombospondin Trypanosoma cruzi TcCRT Adhesion and invasion of endothelial cells Enteric and systemic diseases 144* Decorin Borrelia burgdorferi DbpA and DbpB Adhesion to host cells and tissue; improved bacterial survival Chagas disease 141 Nidogen 1 and 2 Enterococcus faecium SgrA Enhancement of cellular infection Lyme disease 145, 146 Soluble and immobilized fibrinogen(α‐ and β‐chains) Staphylococcus aureus ClfA, ClfB Specific localization to decorin‐rich niches in the tunica adventitia and myocardial connective tissue; persistence of infection UTIs, bacteraemia, and infective endocarditis Host tissue adhesion and biofilm formation Nosocomial infections, septicaemia, osteomyelitis, endocarditis, etc. Colonization of biomaterial implants; bacterial spread GI, gastrointestinal; UTI, urinary tract infection; LpfAI, long polar fimbrae subunit 1; SfbII, fibronectin surface binding protein II; Fba, fibronectin binding protein; MntC, manganese transport protein C; MisL, autotransport protein MisL; FimB, type I fimbriae regulatory protein FimB; gtf, glucosyltransferase; pilB, type 4 fimbrial assembly protein; EcbA, E. faecium collagen binding protein A; MIP, macrophage infectivity potentiator; YadA, adhesin YadA; TcCRT, Trypanosoma cruzi calreticulin; DdpA/ DdpB, decorin binding protein A and B; SgrA, serine‐glutamate repeat containing protein A; ClfA/ClfB, clumping factor A and B. Early studies were mostly limited by the use of binding assays, involving bacterial cells or recombinant adhesins and ECM molecules, and inhibition experiments to demonstrate these interactions. Cutting‐edge technologies, including live cell imaging and particle‐tracking methods, have now started to reveal the implications of these interactions in pathogenesis. For example, Niddam et al. showed that the Lyme disease spirochaete Borrelia burgdorferi exploits fibronectin to interact with vascular surfaces under physiological shear stress. Specifically, it recruits and induces polymerization of soluble plasma fibronectin that strengthens and stabilizes bacterial interactions with endothelia by a catch–bond mechanism.35 Breaking down barriers to invade the host Having colonized the host, most pathogens need to invade tissues to cause disease. This requires the breakdown of primary and/or secondary defences of the host, involving the crossing of basement membranes and interstitial matrices. Pathogens have developed distinct ways to modify the ECM.1, 36 They can directly degrade ECM components using ‘invasins’ or bacterial tissue‐degrading enzymes such as hyaluronidases and collagenases, causing local tissue damage. Specific examples of these interactions are reported in Table 2 and reviewed elsewhere.26, 36 Degradation of the ECM not only facilitates the spread of pathogens, but can also favour tissue necrosis, bacterial toxin diffusion and host cell adhesion, migration and survival. Pathogens can also indirectly modify the ECM by altering the synthesis and turnover of ECM components by host cells in response to their presence (discussed later in this review). Moreover, pathogens can hijack or misuse host proteolytic systems. For instance, Staphylococcus aureus,37 Haemophilus influenzae38 and Pseudomonas aeruginosa,39 among other common pathogenic bacteria, manipulate the plasminogen–plasmin system thereby degrading laminin and fibronectin and activating MMP zymogens that not only degrade all types of ECM proteins, but also process many biologically active molecules (e.g. cell surface receptors and cytokines) that direct cell behaviour and host defence. ECM molecule Pathogen Microbial enzyme Effect of ECM cleavage Disease References Laminin Psedomonas aeruginosa Elastase; alkaline protease Tissue invasion and necrosis Necrotizing pneumonia, septic shock, UTI, skin and soft‐tissue infections 147 # Clostridium difficile Cwp84 Tissue integrity loss; facilitation of toxin diffusion Pseudomembranous colitis and nosocomial diarrhoea 148 Collagen I Porphyromonas gingivalis Gingipains in P. gingivalis supernatant Tissue degradation Periodontal disease 149 Vibrio parahaemolyticus Metalloprotease VppC Tissue damage Acute gastroenteritis 150 Collagen I, II, III, IV, V and VI Clostridium histolyticum Class I and II collagenases (ColG, ColH) Necrotic tissue degradation; promote keratinocyte migration Gas gangrene, infective endocarditis 151, 152 Collagen IV Streptococcus gordonii Serine protease Basement membrane breakdown Infective endocarditis 153 Fibronectin Clostridium difficile Cwp84 Tissue integrity loss; facilitation of toxin diffusion Pseudomembranous colitis and nosocomial diarrhoea 148 Porphyromonas gingivalis Gingipains in P. gingivalis supernatant; HRgpA and RgpB gingipains Cleavage and inactivation of cell‐binding region of fibronectin; gingival fibroblast detachment and death; tissue destruction Periodontal disease 149, 154 # Vitronectin Clostridium difficile Cwp84 Tissue integrity loss; facilitation of toxin diffusion Pseudomembranous colitis and nosocomial diarrhoea 148 Tenascin‐C (large isoforms) Porphyromonas gingivalis HRgpA, RgpB and Kgp gingipains Enhanced anti‐adhesive activity of tenascin‐C; gingival fibroblasts detachment, apoptosis and tissue destruction Periodontal disease 154 # Cwp84, putative cell surface‐associated cysteine protease; HRgpA and RgpB, arginine‐gingipains; Kgp, lysine‐gingipains; UTI, urinary tract infection. Strategies to evade the host immune response? Although numerous pathogens undoubtedly exploit ECM components and ECM‐associated molecules to adhere to and degrade tissues for efficient host colonization and invasion, it is not always clear whether pathogens interact with these ECM molecules also to evade immune responses. For instance, Borrelia burgdorferi can avoid antibody‐mediated clearance and this may be partly explained by its specific interaction with decorin.36 The Haemophilus influenzae surface protein E binds to plasminogen, which is converted to plasmin, and uses plasmin for complement evasion and innate immune escape.37 Several other pathogenic bacteria take advantage of the host plasminogen system to facilitate their own spread and invasion through tissues.40, 41 Notably, Helicobacter pylori benefits from the complement regulatory property and the plasminogen‐binding ability of vitronectin to protect itself from innate immune responses.42 Furthermore, Group B streptococci and other Gram‐positive bacteria secrete hyaluronidases, whose activity allows immune evasion besides tissue invasion. Specifically, their hyaluronidases process pro‐inflammatory hyaluronan fragments into disaccharides, which block TLR2/4 signalling triggered by host‐derived hyaluronan fragments and pathogenic ligands, including lipopolysaccharide (LPS), thereby evading immune detection.43 Altered ECM dynamics in infection and its implications The ECM undergoes significant alterations upon infection that promote or inhibit the establishment of infection and the host response to it. Below is an overview of the changes in ECM synthesis, degradation and post‐translational modification during infection and a discussion of their implications in pathogenesis. ECM synthesis and deposition Signal transduction pathways activated upon pathogen entry and recognition, and by mediators of inflammation and tissue repair during infection all contribute to ECM synthesis and deposition. This involves structural ECM proteins (e.g. collagens, laminins and proteoglycans) as well as non‐structural ECM components termed ‘matricellular proteins’, which are normally absent or scarcely expressed in healthy tissues (e.g. osteopontin, thrombospondins, galectins, tenascins). For instance, rhinovirus activates TLR3 and TLR7/8 signalling in airway smooth muscle cells, which leads to increased deposition of fibronectin, perlecan and collagen IV, contributing to airway remodelling and facilitating the migration of airway smooth muscle cells to the infection site.44 Interleukin‐33 (IL‐33) signalling induced by Staphylococcus aureus enhances fibronectin and collagen IIIa expression and deposition, accelerating wound repair.45 Systems biology approaches elucidating the ECM interactome network regulated by Trypanosoma cruzi and its gp83 ligand, which mediates trypanosome attachment and entry, have shown that activation of gp83 receptors in the cell via extracellular signal‐regulated kinase 1/2 results in up‐regulation of laminin γ1 and thrombospondin expression to facilitate trypomastigote recruitment, enhancing cellular infection.46 In mice, Citrobacter rodentium infection induces osteopontin and fibronectin expression through integrin‐linked kinase activation, facilitating bacterial colonization of the intestine.47 High expression levels of osteopontin have also been shown to be induced in murine acute and chronic coxsackievirus B3‐myocarditis together with those of MMP‐3, TIMP1, urokinase‐type plasminogen activator and TGF‐β1 and, in turn, procollagen‐1α mRNA expression and fibrosis. Accordingly, osteopontin‐null mice are protected from viral myocarditis, and inhibition of osteopontin transcription by vitamin D decreases cardiac fibrosis in wild‐type animals.48 Viral myocarditis also results in up‐regulation of tenascin‐C before immune cell infiltration occurs and until scar tissue is formed.49 Elevated tenascin‐C levels have also been reported in patients with sepsis, parapneumonic infection, tuberculosis and Staphylococcus aureus infection.50-54 Furthermore, the lungs of mice infected with Gram‐negative bacteria show accumulation of versican, a chondroitin sulphate proteoglycan with multiple cytokine, chemokine, adhesion molecule and growth factor‐binding domains, that is implicated in the innate immune response.55 Similarly, when primary human lung fibroblasts are treated with the viral mimetic Poly I:C, they deposit a higher‐order structured ECM, rich in versican and hyaluronan, to which T cells avidly adhere and cease migration, an effect reversed by hyaluronidase treatment or versican antibody during matrix formation.56 Importantly, besides expression levels, infection can also alter the spatial distribution of ECM components as it emerges from influenza‐infected lungs, which show distinct regions that are enriched with either fibronectin or collagen.57 Hence, specific infectious diseases seem to generate distinct compositional changes of the ECM, inevitably influencing its biophysical structure and presentation of bioactive compounds that impact bacterial colonization and invasion, immune cell response and tissue repair. ECM degradation The catabolic machinery that breaks down and remodels the ECM is also altered upon infection, affecting the supportive, barrier and biological functions of the ECM. Tissue degrading enzymes such as MMPs play a crucial role in regulating immune cell recruitment: they cleave the basement membrane ECM; expose cryptic pro‐migratory sites of ECM components (e.g. γ2 chain of laminin 5); target non‐ECM proteins such as adhesion molecules (e.g. E‐cadherin); activate, deactivate or regulate the bioavailability of chemokines (e.g. monocyte cheomattractant protein‐1 and IL‐8) and cytokines (e.g. IL‐1β and TNF‐α); and shed cell surface receptors associated with cell migration (e.g. CD44), modulating inflammation (reviewed in refs 58-60). With the exception of neutrophils, tissue‐degrading enzymes are not stored, but require de novo synthesis that is strictly regulated and can be induced by pro‐inflammatory cytokines (e.g. TNF‐α and IL‐1) and also by bacterial products (e.g. LPS and chlamydial heat‐shock proteins).61 Several pathogens, including Mycobacterium bovis, Mycobacterium tuberculosis, Streptococcus pyogenes and Helicobacter pylori, induce expression and activity of a number of MMPs, including MMP‐1, MMP‐2, MMP‐7, MMP‐9 and MMP‐13.62-64 In particular, the extensive production of MMP‐2 and MMP‐9 during mycobacterial infection is regulated by macrophage‐derived and T‐cell‐derived cytokines and causes ECM breakdown. This may be necessary for cell recruitment and granuloma formation, both protective immune responses to mycobacteria. However, dysregulation of MMP production at late stages of the infection could contribute to tissue damage and, by compromising tissue integrity, may facilitate bacterial dissemination and persistence of infection.62 Systemic Escherichia coli infection, acute Lyme neuroborreliosis and pneumococcal meningitis can all lead to secretion of high amounts of MMP‐9. In meningitis, MMP‐9 has been suggested to contribute to blood–brain barrier destruction and neuronal injury.65-67 Similarly, gastrin‐dependent induction of MMP‐7 upon Helicobacter pylori infection has been implicated in the development of gastric cancer through the release of heparin‐binding epidermal growth factor.64 Chlamydia trachomatis, which causes trachoma and blindness, up‐regulates MMP‐7, MMP‐9, MMP‐12 and TIMP‐1 expression, while it down‐regulates MMP‐10 and SPARC (secreted protein, acidic, cysteine‐rich)‐like 1, a matricellular protein that regulates decorin production and collagen assembly.68 In this study the expression pattern of these ECM‐modifying enzymes was correlated with the clinical scarring grade and inflammation. Interestingly, a dual function has been shown for MMP‐12 in viral myocarditis caused by coxsackievirus type B3. While intracellular MMP‐12 causes IFN‐α secretion and host protection, extracellular MMP‐12 cleaves the IFN‐α receptor 2 binding site of IFN‐α, preventing an uncontrolled immune response.69 In the same model of viral myocarditis, MMP‐9 exerts a protective role by inactivating IFN‐β/γ. Indeed, MMP‐9‐null mice display higher viral load, infiltration of CD3+ cells and tissue damage.70 However, murine MMP‐9 can also enhance susceptibility to infection and increase morbidity and mortality. This is the case in Francisella tularensis pulmonary infection where MMP‐9 generates pro‐inflammatory ECM‐derived peptides (i.e. Pro‐Gly‐Pro peptide from collagen I), enhancing neutrophil infiltration to lungs.71 In addition to inducing MMP expression, pathogens can also activate pro‐MMPs by secreting their own activating enzymes, as in the case of Pseudomonas aeruginosa, which activates pro‐MMP‐2 using LasB, a thermolysin‐like metalloprotease.39 The role of dysregulated tissue‐degrading enzymes, individually or in combination, is not well understood in every infectious disease. However, it is clear that the MMP/TIMP system changes the ECM composition and biophysics and its presentation of bioactive molecules, generating environmental cues that are detected and processed by immune cells into signalling events that direct their behaviour and response to infection. ECM post‐translational modification Post‐translational modifications (PTMs) add complexity to the ECM. Some are generated by proteolytic cleavage, while others are generated by citrullination of arginine, glycosylation, cross‐linking, hydroxylation of prolines, nitrosylation of tyrosines and aspartate isomerization (reviewed in ref. 7). Given the ability of pathogens to hijack host enzymes or secrete enzymes targeting host molecules, it is tempting to ask whether PTMs in the ECM are altered in infection. Indeed, the Porphyromonas gingivalis enzyme peptidylarginine deiminase can convert arginine residues to citrulline in mammalian ECM proteins, including fibrinogen, collagen II, fibronectin and tenascin‐C.72-76 Although arginine is positively charged at neutral pH, citrulline is uncharged, increasing protein hydrophobicity and, hence, altering protein three‐dimensional structure and function. Notably, Porphyromonas gingivalis periodontal infection has been linked to rheumatoid arthritis, an autoimmune disease of the joints characterized by high levels of citrullinated proteins and anti‐citrullinated ECM protein antibodies.77 Trypanosoma cruzi, the aetiological agent of Chagas disease, which features extensive inflammation and fibrosis of the heart, has been reported to increase the expression of lysyl oxidase (LOX).78 This enzyme carries out cross‐linking of collagen fibres thereby altering matrix stiffness, which has been linked to cancer metastasis.79 By irreversibly altering collagen structure and function, LOX has been proposed to cause dysfunction of cardiomyocytes and, in turn, of the heart in Chagas disease. Similarly, dengue virus infection has been shown to suppress the expression of cartilage‐associated protein (CRTAP), alongside the protein associated to tight junctions (PATJ). CRTAP associates with the proteoglycan leprecan, which has collagen prolyl 3‐hydroxylase activity, and cyclophilin B in the endoplasmic reticulum. This trimeric complex is required for proline 3‐hydroxylation of collagen and, hence, collagen assembly. As the levels of CRTAP mRNA negatively correlate with viral replication, the authors of the study have speculated that CRTAP, together with PATJ, restrict dengue infection by influencing cell–cell adhesion.80 While evidence supporting a link between specific PTMs of ECM proteins and diseases such as arthritis and cancer is accumulating, the implications of altered PTMs of ECM components during infection are only beginning to emerge. For example, collagen fibre cross‐linking mediated by LOX can significantly alter tissue structure and ECM mechanics. Mammoto et al. recently showed that LOX‐dependent changes in ECM mechanics control vascular permeability and pulmonary oedema. In vivo, mouse lungs treated with LPS, which contributes to pulmonary oedema and acute respiratory distress syndrome in patients with sepsis,81 become much stiffer than untreated lungs and exhibit enhanced vascular permeability. Increased LOX expression and LOX and LOX1 protein isoform activity control alveolar architecture and vascular permeability, which are restored by LOX activity inhibition.82 Macrophages: not just destroyers of the ECM In bacterial and viral infection, activated macrophages [e.g. M(IFN‐γ), M(LPS)] have long been implicated in ECM destabilization and destruction through the secretion of tissue‐degrading enzymes, including MMP‐9. Similarly, parasitic infections involve activated macrophages [i.e. M(IL‐4)], which release proteases such as MMP‐1 and MMP‐12.83 However, macrophages can also produce a number of ECM proteins. Increasing evidence of this and its implications are discussed below. Fibronectin is the first ECM glycoprotein reported to be produced by human macrophages and IFN‐γ‐stimulated mouse peritoneal macrophages.84, 85 Moreover, bacterial components induce tenascin‐C expression in human monocyte‐derived and mouse bone‐marrow‐derived macrophages.53, 86 Lipopolysaccharide from Porphyromonas gingivalis induces thrombospondin‐1 production in THP‐1 cells,87 while LPS from Escherichia coli and IFN‐γ up‐regulate galectin‐1 and galectin‐3, including five galectin‐3 truncated forms, in primary human macrophages.88 In mice with viral myocarditis, macrophages infiltrating the heart are the main producers of osteopontin.48 Notably, in murine macrophages, LPS causes the formation of chromosomal loops in the osteopontin promoter by bridging nuclear factor‐κB (NF‐κB) and activator protein‐1 together, leading to osteopontin transcription,89 which is negatively regulated by GSK3b.90 Macrophage expression of proteoglycans has also been demonstrated. Treatment of bone marrow‐derived and alveolar macrophages with Escherichia coli LPS results in rapid induction of versican and hyaluronan synthase 1, and simultaneous inhibition of the major hyaluronan‐degrading enzymes (hyaluronidases 1/2).91 Serglycin, decorin and biglycan are also secreted by LPS‐activated mouse peritoneal macrophages.92-94 By using inhibition, chromatin immunoprecipitation and NF‐κB reporter gene assays, some of these studies have demonstrated that pathogenic activation of the NF‐κB signalling pathway downstream of TLR4 leads to ECM molecule transcription.86, 89, 93-95 Importantly, in the case of tenascin‐C, biglycan and decorin, which can activate TLR4, this can promote autocrine loops of inflammation.86, 93, 94 Hence, the infected cellular microenvironment influences TLR function and, in turn, TLR activation affects the microenvironment. Intriguingly, there is mounting evidence that macrophages can synthesize collagen molecules. In Drosophila, phagocytes (haemocytes) produce functional collagen IV, which controls key signalling events in the germline stem cell niche.96 The first reports of collagen synthesis by mammalian macrophages were published in the 1990s. The first showed collagen I synthesis in mouse peritoneal macrophages and the second demonstrated collagen VIII synthesis and secretion in human macrophages, which was decreased by IFN‐γ and LPS treatment.97, 98 Collagen VIII is a short‐chain, non‐fibrillar collagen that forms unique hexagonal lattice structures and possesses both structural and signalling properties. Later, human macrophages were shown to secrete collagen VI, which forms beaded filaments with a multidomain structure that interact with ECMs and cell surface receptors to anchor interstitial structures and cells within tissues. Expression of collagen VI was decreased by IFN‐γ and LPS, but increased upon IL‐4 treatment.99 Recently, the expression of all 28 collagen‐encoding mRNAs was quantified in steady‐state and LPS‐activated primary human macrophages and compared with that of human dermal fibroblasts, an abundant matrix source.95 Steady‐state macrophages expressed basal levels (lower than those in dermal fibroblasts) of collagen mRNAs with the exception of collagen III, X, XI, XVI, XX and XXVI. However, LPS specifically increased the expression of fibril‐associated collagens with interrupted triple helices (FACITs; collagen VII, XII, XV, XIX and XXI), the collagenase‐resistant collagen V, the collagen‐containing von Willebrand factor collagen XXVIII and collagen I, IV, XVIII, XXV and XXVII. Collagen II, VIII, IX, XIII, XIV, XXIII and XXIV expression was not increased. LPS also down‐regulated the expression of collagen VI, confirming previous studies,99 and collagen XIII and XVII.95 By secreting collagens, depending upon their mode of activation, macrophages may contribute to the ECM, and therefore to tissue stabilization and repair, and to cell–cell and cell–matrix interactions (e.g. in vitro, monocytes adhere strongly to collagen VI99). Furthermore, macrophages may bind to their secreted collagen molecules as they express several receptors known to interact with collagen (e.g. integrins and proteoglycans). However, collagen secretion by macrophages and its potential role in macrophage adhesion and the immune response in vivo remain to be clarified. The ECM: an integral part of the innate immune response to infection? Antimicrobial activity of the ECM The innate immune system employs endogenous peptides like α‐defensin and LL‐37, which bind to heparin and dermatan sulphate glycosaminoglycans and have antimicrobial properties. During the inflammatory response to infection, tissue‐degrading enzymes generate bioactive ECM fragments. A number of studies showed that heparin‐binding peptides derived from laminin isoforms, vitronectin, thrombospondin and fibronectin, exert antimicrobial activities against Gram‐positive and Gram‐negative bacteria, and the fungus Candida albicans.100-102 Certain ECM proteins are also found in biological fluids. One such protein is tenascin‐C, which has been found in human breast milk (2·2–671 μg/ml) where it acts as an innate broad‐spectrum human immunodeficiency virus 1 (HIV‐1) ‐neutralizing protein.103 Tenascin‐C directly captures HIV‐1 virions by binding to the HIV‐1 envelope gp120 protein at a CD4‐inducible epitope that overlaps the chemokine co‐receptor binding site. Accordingly, tenascin‐C depletion abolishes the HIV‐1‐neutralizing activity of milk.103 Direct antimicrobial activity has also been reported for the ECM‐associated protein MMP‐12, which is abundantly expressed in mature tissue macrophages and mobilized to macrophage phagolysosomes after the ingestion of bacteria. Inside phagolysosomes, MMP‐12 adheres to bacterial cell walls and disrupts cellular membranes, killing the bacteria. Notably, the C‐terminal domain of MMP‐12, but not its catalytic domain, contains a four‐amino‐acid sequence on an exposed β loop of the protein that is unique in nature and confers antimicrobial activity.104 Together, these data may help the search for safe, endogenous antimicrobial molecules from complex biological mixtures. Furthermore, binding epitopes could serve as templates for de novo synthesis of novel antimicrobial molecules. ECM‐mediated recognition of microbial pathogens, macrophage activation and phagocytosis The innate immune system employs highly conserved receptors, namely PRRs, to recognize conserved motifs in microbial pathogens, called pathogen‐associated molecular patterns. Mindin, a member of the mindin‐F‐spondin family of secreted ECM proteins, has emerged as a unique pattern recognition molecule in the ECM for microbial pathogens and has been proposed to function as an integral part of the innate immune response.105 He et al., showed that genetic ablation of mindin confers resistance to LPS‐induced shock and systemic Salmonella typhimurium and Streptococcus pneumoniae infections in vivo. Moreover, mindin‐null mice feature impaired bacterial clearance in lungs infected with Gram‐positive group B streptococcus or Haemophilus influenzae. In vitro, macrophages and mast cells lacking mindin display impaired TNF‐α and IL‐6 production and defective phagocytosis. By using recombinant mindin, the authors showed that this ECM protein recognizes carbohydrate moieties of Gram‐positive and Gram‐negative bacterial components and, by binding to them, it agglutinates bacteria. As glucose inhibited not only mindin binding to pathogens but also macrophage activation by LPS, the authors concluded that mindin‐mediated carbohydrate recognition of microbial pathogens is a secondary stimulation necessary for the activation of macrophages and mast cells105 (Fig. 1). Notably, mindin is not a universal, but is a specific pattern recognition molecule as it only recognizes and opsonizes certain bacteria. Following this, the innate immune function of mindin has been extended to include promoting influenza virus clearance from the nasal cavity by allowing efficient macrophage activation.106 Furthermore, the proteoglycan lumican, whose core protein contains tandem repeats of leucine‐rich motifs similarly to PRRs, interacts with CD14 on the surface of macrophages and neutrophils, promoting CD14‐TLR4‐mediated responses to LPS (Fig. 1). Hence, lumican‐null mice are hyporesponsive to LPS‐induced septic shock.107 In a Pseudomonas aeruginosa model of lung infection, mortality of lumican‐deficient mice is increased as animals fail to clear bacteria from tissues. This study showed that CD14‐mediated phagocytosis of Escherichia coli and Pseudomonas aeruginosa bacteria by macrophages is impaired in the absence of lumican and identified Tyr‐20 as a vital residue for CD14 binding and phagocytosis.108 Finally, infection of the cornea with Pseudomonas aeruginosa readily increases lumican expression before inflammatory cell infiltration, and lumican‐null mice display poor resolution of bacterial keratitis and sustained production of pro‐inflammatory cytokines.109 Another ECM protein that senses a number of microbial pathogens is galectin‐3, which binds to carbohydrate structures on glycoproteins and glycolipids (e.g. N‐acetyl‐d‐lactosamine and LPS) from (myco)bacteria, protozoan parasites and yeast.110 Although the in vivo function of galectin‐3 during infection has not been fully investigated, upon microorganism recognition, it contributes to macrophage‐mediated phagocytosis, at least in vitro111 (Fig. 1). Whether these ECM components exert the same essential immune functions in humans represents an outstanding, important question. Leucocyte population balance in infection: emerging roles for ECM components Severe infection demands large numbers of leucocytes that are compensated by the emergency myelopoiesis response, which is initiated by activated PRRs and cytokines, including IL‐6, granulocyte–macrophage colony‐stimulating factor and granulocyte colony‐stimulating factor. This protects the host from systemic infection by quickly generating the required leucocyte population. Kanayama et al.112 have recently found that osteopontin skewed the balance of myeloid and lymphoid cell populations during systemic infection with Candida albicans. Specifically, the authors showed that osteopontin limited the supply of neutrophils and Ly6C+ monocytes–macrophages by enhancing the apoptosis of common myeloid and granulocyte–macrophage progenitors through a down‐regulation of the expression of the apoptosis inhibitor survivin. This resulted in greater fungal load in kidneys and significantly higher mortality of wild‐type mice with systemic fungal infection compared with osteopontin‐deficient littermates. The detrimental effect of osteopontin was observed early, 24 hr after infection.112 However, it is unclear if this effect is maintained, exacerbated or reversed at later stages of infection. Dendritic cells (DCs) are the main antigen‐presenting cells and, upon capturing microbial pathogens, mature and migrate to lymphoid tissues where they activate naive T cells. Distinct classes of microbes elicit lineage‐specific responses from the effector T‐cell repertoire. Type 1 helper T (Th1) cells are involved in infection by intracellular bacteria and viruses, Th2 cells in parasitic infection, and Th17 cells in infection by extracellular pathogens and facultative and obligate intracellular bacteria and fungi. Regulatory T cells hold the inflammatory response in check. Specific ECM proteins have been shown to contribute to the T‐cell polarizing function of DCs without affecting DC development. For instance, generation of Th17 cells by Escherichia coli LPS or Mycobacterium tuberculosis stimulated bone marrow‐derived DCs from tenascin‐C‐null mice is significantly impaired.113 Furthermore, the expression of galectin‐3 in DCs controls the magnitude of T‐cell priming in vitro and in vivo during helminthic infection with Schistosoma mansoni. Galectin‐3‐deficient mice have significantly fewer T cells in their spleen and higher cellular and humoral Th1 responses.114 Although this study shows that galectin‐3 expression by DCs modulates the proliferation and cytokine release by T cells, it does not explain the mechanism responsible for the biased Th1 response. Efficient T‐cell priming by DCs has also been shown to depend on mindin.115 When DCs from mindin‐null mice are activated with bacterial components, including LPS from Salmonella typhosa or Escherichia coli and lipoteichoic acid from Staphylococcus aureus, CD4+ T‐cell priming is 60–70% lower than that of wild‐type mice. Investigation of this demonstrated that DCs interact with mindin via integrins α4β1 and α5β1, leading to up‐regulated expression of the Rho GTPases Rac1/2, which are known to regulate DC priming of T cells.115 As DCs link innate to adaptive immunity and unbalanced effector T‐cell populations lead to pathological inflammation, understanding how the ECM can regulate T‐cell responses is crucial. Transcriptional and post‐transcriptional roles for ECM molecules in host defence signalling pathways Pathogen recognition via PRRs initiates inflammatory signalling pathways that are tightly regulated to allow microbial clearance with minimal damage to the host. Recent research implicates a role for ECM and ECM‐associated proteins in regulating inflammatory networks at the transcriptional and post‐transcriptional levels during the immune response to infection. An elegant study by Marchant et al.69 found a transcriptional role for MMP‐12 (macrophage elastase) in immunity against viral infection. During coxsackievirus type B3 and respiratory syncytial virus infections, MMP‐12‐null mice display increased viral load, mortality and lower levels of IFN‐α, which is essential for viral immunity. Mechanistically, secreted MMP‐12 is taken up by virus‐infected cells and traffics to the nucleus, where it binds to the NFKBIA promoter, driving its transcription, which is essential for optimal IFN‐α secretion and host protection. Additionally, MMP‐12 regulates specific substrates by two distinct mechanisms: (i) through DNA binding of gene exons (e.g. exons encoding PSME3, the immunoproteasome cap protein, and SPARC‐like protein 1, which decreases their mRNA and protein levels in MMP‐12‐null mice); and (ii) extracellularly, through substrate protein cleavage (e.g. IFN‐α receptor 2 binding site). Hence, MMP‐12 clears systemic IFN‐α and, accordingly, selective inhibition of extracellular MMP‐12 in infected wild‐type mice elevates systemic IFN‐α levels and reduces viral replication.69 At the post‐transcriptional level, a role for decorin and tenascin‐C has been found in regulating microRNAs in LPS‐induced sepsis.53, 93, 116 Merline et al. detected increased decorin levels in patients with sepsis and mice with LPS‐induced sepsis, and elevated IL‐10 amounts in decorin‐null mice. They demonstrated that, in the presence of LPS, decorin reduces the levels of the anti‐inflammatory cytokine IL‐10 through two mechanisms. First, it activates extracellular signal‐regulated kinase and p38 mitogen‐activated protein kinases downstream of TLR2 and TLR4, thereby inducing the expression of the pro‐inflammatory modulator programmed cell death 4 (PDCD4), which translationally represses IL‐10. Second, decorin inhibits TGF‐β1 signalling, leading to lower levels of the microRNA miR‐21, which represses PDCD4 expression and so decreases IL‐10 levels.93 Soon after, tenascin‐C was shown to orchestrate the secretion of specific cytokine subsets in response to LPS. Specifically, tenascin‐C regulates the biosynthesis of the LPS‐responsive miRNA miR‐155, allowing optimal TNF‐α production in macrophages and effective immune response to LPS in vivo.53 Hence, specific ECM and ECM‐associated proteins possess previously unknown transcriptional and post‐transcriptional regulatory activities, which fine‐tune the innate immune response to infection. The ECM in infectious granulomas Tuberculosis, syphilis, toxoplasmosis, infectious mononucleosis and measles are a few examples of infectious diseases characterized by the formation of granulomas. Traditionally considered host‐protective structures, infectious granulomas are compact, organized immune cell clusters that are generated in response to specific pathogens. Granulomas contain large numbers of mature macrophages, which can fuse into multinucleated giant cells or differentiate into foam cells. Neutrophils, dendritic cells, B, T and natural killer cells, and fibroblasts are also found in granulomas, which are surrounded by epithelial cells. Granulomas also contain ECM proteins, whose expression and function in infectious granulomatous disease pathogenesis has only recently been investigated. In humans, osteopontin has been detected in granulomas of diverse aetiology;117 in those caused by Paracoccidioides brasiliensis, it localizes in ECM, macrophages and multinucleated giant cells at the centre of lesions in the early phase of infection.118 In tuberculosis granulomas, osteopontin is markedly expressed within lymphocytes, macrophages, epithelioid cells and multinucleated giant cells, but not in the central necrotic core.54 These granulomas also stain strongly for tenascin‐C in the surrounding fibrotic rings and weakly inside, in the ECM. A diffuse ECM‐associated staining of galectin‐9 is detected in the granuloma and in epithelioid and multinucleated giant cells. Notably, osteopontin, tenascin‐C and galectin‐9 are absent in non‐infectious Crohn disease granulomas.54 Analysis of human lung biopsies from patients with atypical mycobacteriosis and tuberculosis revealed expression of tenascin‐C and precursor proteins of collagens I and III around granulomas. Precursor proteins of collagen I were also found within granulomas that co‐localized with myofibroblasts.119 In mice infected with Paracoccidioides brasiliensis, Gonzalez et al. detected increased expression of laminin, fibronectin, fibrinogen, collagen I, collagen III, elastic fibres and proteoglycans during granuloma formation.120 Analysis of their arrangement showed that they were mostly surrounding the granuloma, but sporadically inside it. Initially arranged in a disorganized manner, ECM fibres later acquired a compact, concentric arrangement, which originated from an anchorage point that may contribute to tissue integrity and enhance distribution of growth factors and cytokines.120 Notably, during chronic mycobacterial infection, the fibrinolytic system has been shown to limit progressive fibrosis with plasminogen regulating the turnover of ECM proteins within the granuloma.121 Recent studies on ECM turnover in tuberculosis granuloma have helped to rewrite tuberculosis immunopathology. Traditionally considered a host‐protective structure that ‘quarantines’ the infecting mycobacteria, tuberculosis granuloma has been implicated in the expansion and dissemination of infection. Specifically, caseous necrosis leading to ECM destruction and bacterial dissemination was thought to be the cornerstone of tuberculosis pathogenesis. Conversely, collagen destruction has now been proposed to initiate caseous necrosis. Elkington et al.122 have first shown that MMP‐1‐expressing mice develop collagen destruction within granulomas upon infection with Mycobacterium tuberculosis in the absence of caseous necrosis. They then demonstrated that proteolytic collagen destruction of the lung ECM is the initial pathological event that reduces the survival of Mycobacterium tuberculosis‐infected cells, resulting in caseous necrosis and cavitation, and so diverting the immune response in favour of the pathogen. Conversely, intact collagen fibrils increase survival of infected cells.123, 124 In line with this, Parasa et al. reported up‐regulation of MMP‐1, MMP‐3, MMP‐9 and MMP‐12 in a human lung‐tissue model and in biopsies from patients with non‐cavitary tuberculosis. Global MMP inhibition via marimastat reduced granuloma formation and bacterial load.125 Future work should take into account the hypoxic conditions in infectious granulomas and include unbiased global analyses of ECM and ECM‐associated molecules in granulomas at various disease stages and gain‐ and loss‐of‐function experiments in three‐dimensional systems and/or genetically modified animals to understand the role of the ECM in granuloma formation and function. Concluding remarks and future perspectives The ECM and the innate immune response to infection are inextricably linked. Largely ignored or overlooked, the diverse yet specific functions of the ECM in infection influence the establishment and dissemination of microbial pathogens in host tissues as well as the outcome of the immune response to the infection (Fig. 2). In addition to the studies discussed here, ECM immunological research, which is expanding into the areas of prion disease,126 virus transmission,127 exosomes in viral pathogenesis128 and vaccine development,129 shows the breadth and complexity of ECM activity and regulation in infection. The ECM undergoes significant changes upon microbial invasion, magnifying the complexity of the cellular microenvironment at sites of infection. This presents challenges in setting up appropriate model systems and identifying the ECM and immunological pathways that are directly responsible for the outcome of individual infectious diseases. Unbiased omics, systems biology and genome editing approaches are promising resources for defining these pathways, designing mechanistic studies, and, in the longer‐term, elucidating them in the context of the microbiota. As antimicrobial resistance is of global concern and tackling it is becoming increasingly challenging, investigating the now evident role of the ECM in infection may reveal novel therapeutic strategies or improve existing ones. It may also inform biomaterials and tissue engineering in their effort to prolong the lifespan and integrity of medical devices that are compromised by infection. Acknowledgements The authors are supported by an Anne McLaren Fellowship (University of Nottingham; awarded to AMP) and a BBSRC‐DTP studentship (HT). We thank E.P. Ling for assistance with the literature search and N. Zordan for help with the figures. Disclosures None to declare. References Notes : GI, gastrointestinal; UTI, urinary tract infection; LpfAI, long polar fimbrae subunit 1; SfbII, fibronectin surface binding protein II; Fba, fibronectin binding protein; MntC, manganese transport protein C; MisL, autotransport protein MisL; FimB, type I fimbriae regulatory protein FimB; gtf, glucosyltransferase; pilB, type 4 fimbrial assembly protein; EcbA, E. faecium collagen binding protein A; MIP, macrophage infectivity potentiator; YadA, adhesin YadA; TcCRT, Trypanosoma cruzi calreticulin; DdpA/ DdpB, decorin binding protein A and B; SgrA, serine‐glutamate repeat containing protein A; ClfA/ClfB, clumping factor A and B. Cwp84, putative cell surface‐associated cysteine protease; HRgpA and RgpB, arginine‐gingipains; Kgp, lysine‐gingipains; UTI, urinary tract infection. Citing Literature Number of times cited: 1 Abha Sahni, Hema Narra, Jignesh Patel and Sanjeev Sahni, MicroRNA-Regulated Rickettsial Invasion into Host Endothelium via Fibroblast Growth Factor 2 and Its Receptor FGFR1, Cells, 10.3390/cells7120240, 7, 12, (240), (2018). Crossref
|
|
Scooped by
Gilbert C FAURE
January 20, 2018 2:20 AM
|
CD4+ cytotoxic T lymphocytes (CD4-CTLs) were initially identified in patients with chronic viral infections, including dengue virus (DENV) infection, and these cells have been associated with protection in the context of severe DENV infection. Here, Patil et al . have carried out single RNA-seq and sequenced the T cell receptors (TCRs) of CD4+ T cells from human blood to identify precursors that give rise to CD4-CTLs. They report that CD4-CTLs undergo significant clonal expansion and that CD4-CTL precursor cells are characterized by high expression of interleukin-7 receptor. By defining the gene expression signature of CD4-CTLs and their precursors, their studies should facilitate improved vaccine design in the context of chronic viral infections.

|
Suggested by
LIGHTING
December 10, 2016 12:40 PM
|
Dengue virus (DENV) has spread through most tropical and subtropical areas of the world and represents a serious public health problem. The control of DENV infection has not yet been fully successful due to lack of effective therapeutics or vaccines. Nevertheless, a better understanding of the immune responses against DENV infection may reveal new strategies for eliciting and improving antiviral immunity. T cells provide protective immunity against various viral infections by generating effector cells that cooperate to eliminate antigens and memory cells that can survive for long periods with enhanced abilities to control recurring pathogens. Following activation, CD8 T cells can migrate to sites of infection and kill infected cells, whereas CD4 T cells contribute to the elimination of pathogens by trafficking to infected tissues and providing help to innate immune responses, B cells, as well as CD8 T cells. However, it is now evident that CD4 T cells can also perform cytotoxic functions and induce the apoptosis of target cells. Importantly, accumulating studies demonstrate that cytotoxic CD4 T cells develop following DENV infections and may play a crucial role in protecting the host from severe dengue disease. We review our current understanding of the differentiation and function of cytotoxic CD4 T cells, with a focus on DENV infection, and discuss the potential of harnessing these cells for the prevention and treatment of DENV infection and disease.
|
|
Scooped by
Gilbert C FAURE
July 30, 2016 1:38 AM
|
Dengue virus infects immune cells, including monocytes, macrophages and dendritic cells (DC). We compared virus infectivity in macrophages and DC, and found that the virus origin determined the cell tropism of progeny virus. The highest efficiency of re-infection was seen for macrophage-derived dengue virus. Furthermore, in the presence of enhancing antibodies, macrophage-derived virus gave greater enhancement of infection compared with immature DC-derived virus. Taken together, our results highlight the importance of macrophages in dengue infection.
|
|
Scooped by
Gilbert C FAURE
May 29, 2016 11:53 AM
|
Author Summary Dengue is a globally important viral disease. Despite this, there is still much unknown about the immunology, virology and epidemiology of dengue.
Antibodies to dengue virus enhance infection of cells by Zika virus, which may explain neurological and fetal disease caused by infection.
Via Krishan Maggon
|


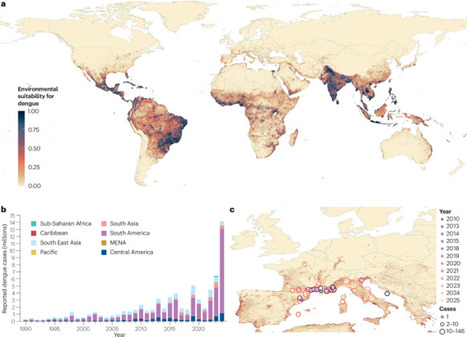





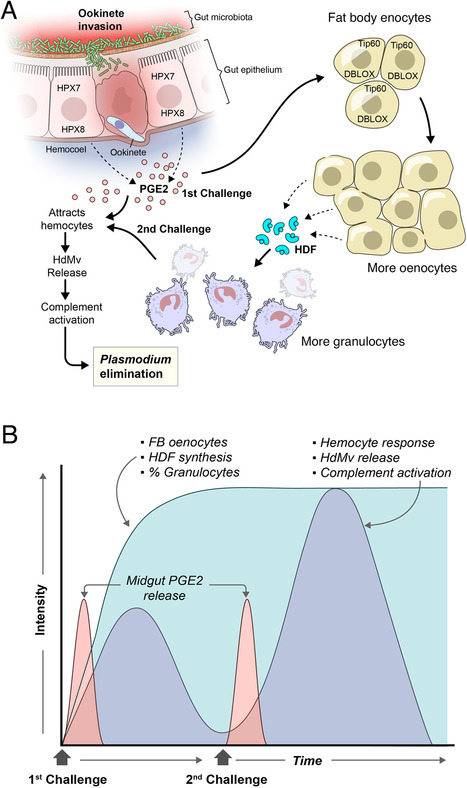












https://www.scoop.it/topic/immunology?q=dengue
> 70 posts