J’y effectue actuellement mon SIR et je dois dire que les formations de chirurgie robotique proposées sont de grande qualité : l’école dispose de matériel et de robots à la pointe de la technologie (Da Vinci notamment…). Elle est également le siège de nombreux projets de recherches tout aussi passionnants et innovants !
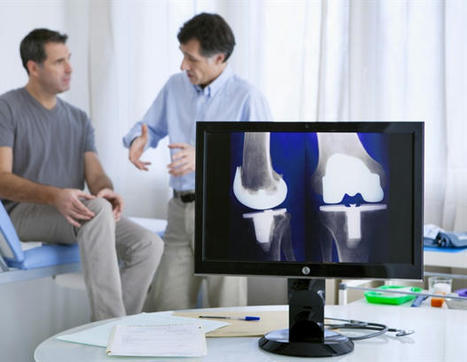
A systematic review indicates that robotic-assisted total knee arthroplasty does not show a consistent economic advantage over conventional surgery across comparative health economic evaluations.
Since Emile Holman, MD, became the surgery department’s first academic chair at Stanford Medicine in 1926, its members have built a legacy of research, innovation and patient care — and logged significant milestones.
The NHS recently outlined plans to expand robotic surgery sevenfold by 2035, but initial findings from the first UK big data studies on this topic published by The BMJ suggest that robotic assisted hip and knee replacements offer no clear benefit over conventional surgery for implant survival,...
/PRNewswire/ -- Medtronic (NYSE: MDT), a global leader in healthcare technology, today announced the U.S. Food and Drug Administration (FDA) has cleared the...
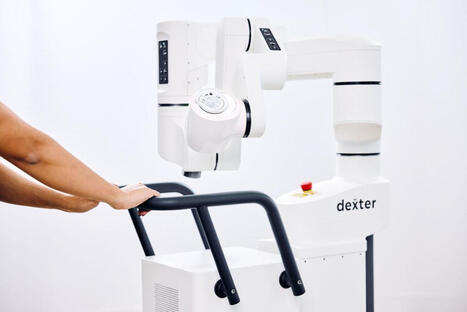
Distalmotion, the Lausanne-area medtech behind DEXTER, has advanced its compact mobile soft-tissue surgical robot through a further regulatory step. DEXTER is designed to fit into existing operating rooms and let surgeons switch between robotic and manual technique during the same procedure.
Why it matters: 🏥 Compact design lowers the cost barrier to robotic surgery 📋 Regulatory clearance is the real moat in medtech 🇨🇭 Swiss precision engineering competing directly with US incumbents
In medtech, the hardest engineering problem is often the approval pathway rather than the device.
Take the next step in robotic surgery with an immersive two-day training experience combining hands-on robotic surgery, AI, telesurgery, and metaverse-based surgical education.
📍 Shanghai, China or Metaverse 📅 September 15–16, 2026 🩺 2-Day Course | 1 Day Dry Lab + 1 Day Wet Lab
👨⚕️ Trainer Introduction
Prof. Dr. Mohanad Al Ansari Board-Certified Surgeon Minimal Invasive GI Surgery | Robotic Surgical Oncology | Telesurgery CEO & Chief Surgeon, Metaverse Surgical Hospital, USA Dean of Robotic Surgery Academy, Canadian Specialist Hospital, Dubai, UAE
Zhenyu Jin Director of Clinical Training, MicroPort MedBot 10+ years of robotic surgery training experience 1000+ physicians trained
🤖 What Will You Learn?
🔹 AI & Metaverse Surgery 🔹 Toumai® Surgical System Components & Robotic Instruments 🔹 Robotic Dissection & Camera Control 🔹 Robotic Suturing 🔹 Robotic Anastomosis 🔹 Telesurgery Tips & Techniques 🔹 Avatar-Based Tele-mentoring 🔹 3D Reconstruction 🔹 Metaverse Hospital Tour
💡 Course Options
Physical Presence USD 3,000 | 2-day course Avatar Presence USD 300 | 2-day online course via the Metaverse
🎓 Certificate of Training Provided
Whether you are looking to strengthen your hands-on robotic skills or explore the future of AI-enabled, immersive and remote surgical education, this course offers an opportunity to learn, practice and connect with experts across borders.
At the forefront of next-generation spine care is robotic-assisted surgery—a minimally invasive approach that combines robotic technology, advanced navigation systems, and real-time imaging...
MicroPort® MedBot™ Achieves First-Ever Half-Year Profitability, Expects Net Profit of RMB 28–40 Million
July 22, 2026 — Shanghai MicroPort MedBot (Group) Co., Ltd. (HKEX: 02252, “MicroPort® MedBot™”) has issued a profit alert for the first half of 2026. According to the announcement, the Company expects to record an unaudited net profit of approximately RMB 28 million to RMB 40 million for the six months ended June 30, 2026.
This marks the Company's first-ever half-year profitability since its listing, representing a significant milestone in its operational performance and high-quality development.
The Company's turnaround from a net loss to a net profit during the Reporting Period was primarily attributable to the following factors:
✅ Substantial Revenue Growth — During the Reporting Period, the Group recorded a year-on-year revenue increase of approximately 200% to 230%.
✅ Significant Improvement in Gross Profit Margin — The Group's overall gross profit margin increased by more than 15 percentage points compared with the same period last year.
✅ Continued Optimisation of Expense Control — The Group continued to strengthen expense management and resource allocation, further improving overall operating efficiency.
Robotic-assisted laparoscopic surgery has made progress in addressing many of the technical challenges associated with conventional laparoscopy. Recently, a new robotic surgical system, Carina Platform, has been developed.
Human-in-the-loop robotic systems could begin to redefine task allocation across the surgical pathway.
Future operating rooms may integrate embodied AI agents capable of workflow understanding and adaptive assistance. This could support surgeons while reshaping how responsibilities are distributed across hybrid human and machine teams.
Read more and download the article in Frontiers in Science ⬇️
The Part of Joint Replacement Surgery You Sleep Through #shorts
Most patients sleep through the most interesting part of their own surgery. Here is what happens after you fall asleep, and why.
1. Time-out. Before anything starts, the whole team stops and confirms out loud who you are, which operation you are having and which side - one of the simplest safety checks in surgery.
2. Prep. Your leg is scrubbed with antiseptic while a team member holds it up, so the whole limb can be cleaned and draped - heavier than most people expect.
3. Warmth. The room is kept cool for a gowned, hooded team, so a warming blanket helps keep your body temperature normal.
4. Planning. With robotic-arm assisted surgery, your bone is matched to a 3D model built from your CT scan before the first cut.
5. Noise. Bone saws have been measured at levels comparable to a concert - you sleep comfortably through it all.
6. Trials. A trial implant goes in first so we can check motion, stability and balance. The real implant stays sealed until the fit is right.
7. Mallet. The final parts are tapped into place for a secure fit.
8. Closure. The incision is closed in layers and covered with a waterproof dressing.
9. Time. It may feel like a few minutes, but anesthesia and the recovery room add to the time your family waits.
10. Family. When we finish, someone calls your family right away.
About Dr. Cory Calendine, MD - 3000 Edward Curd Lane, Franklin, TN 37067 In the operating room, I get to perform more than 700 hip & knee replacement surgeries each year. From LIVE surgical demos to viral video highlights, together let's explore - react - discuss all things related to bone and joint health. #orthopedicsurgeon #jointreplacement
THANK YOU for your comments, questions and suggestions. If there’s a medical topic or question you want me to discuss, please comment below. We are building a library of orthopedic medical video content focused on your requests and responses.
𝐃𝐈𝐒𝐂𝐋𝐀𝐈𝐌𝐄𝐑𝐒: Opinions expressed are solely my own and do not express the views or opinions of my employer. Information in this video is not intended or implied to be a substitute for professional medical advice, diagnosis and/or treatment. All content [images, digital graphics, text, and other information] contained in this video is for general information purposes only and does not replace or substitute for a consultation with a qualified physician or health professional.
/PRNewswire/ -- OrthAlign, Inc., the leader in handheld orthopedic technology, today announced the full commercial launch of Lantern® ASC for total hip and...
“It is always too early to evaluate a new technology until, unfortunately, suddenly it’s too late”Buxton’s law1Robot assisted surgeries in the UK are planned to increase from about 70 000 annually to 500 000 by 2035, according to the NHS—a sevenfold expansion over the coming decade,2 with similar ambitions emerging elsewhere. Yet the National Institute for Health and Care Excellence concludes that although robot assisted surgery can improve the precision of implant positioning in hip and knee arthroplasty, it remains uncertain whether this translates into better clinical outcomes and calls for further evidence generation.3 Plans for rapid expansion are therefore taking shape just as evidence about the clinical value of robot assisted arthroplasty is beginning to emerge.The promise of robot assisted arthroplasty is straightforward: greater precision in bone preparation and implant positioning should mean fewer technical errors—and ultimately better outcomes for patients. This promise is particularly attractive in knee arthroplasty,...
HIBA Case: Robotic Surgery Volume Grows Fivefold in 10 Months with Toumai®
On August 19, 2026, at the VIII Congreso de Salud Adecra+Cedim 2026, Dr. Gustavo García Fornari, Head of the Department of Surgery at Hospital Italiano de Buenos Aires (HIBA), delivered a presentation titled “How to Develop a Rapidly Expanding Robotic Surgery Program? The HIBA Case.” Drawing on HIBA’s experience, he shared key insights into building and scaling a robotic surgery program.
According to Dr. García Fornari, HIBA currently has two surgical robotic systems, one of which is the Toumai® Endoscopic Surgical Robotic System. During his presentation, he highlighted Toumai® and its clinical applications at HIBA.
“We increased the number of robotic surgeries from 12 to 60 per month in just 10 months. In other words, we are now performing five times as many robotic surgeries each month. And we are aiming to reach 80. However, beyond the numbers, it is essential to have a structured implementation program.”
Emphasizing the importance of a comprehensive implementation strategy, Dr. García Fornari noted:
✅ “It is not simply about purchasing a robot; it is about having a program to implement it.”
✅ He then outlined several key components of HIBA’s robotic surgery program:
✅ Building a dedicated multidisciplinary team for robotic surgery;
✅ Developing budgets and operational plans for robotic system acquisition and maintenance;
✅ Exploring payment models and negotiating with relevant healthcare stakeholders to establish a hybrid payment system;
✅ Professional training: providing systematic training for surgeons, surgical technologists, anesthesiologists, nurses, and technicians, supported by simulation and hands-on training;
✅ Certification and accreditation: newly trained robotic surgeons received MicroPort® MedBot certification;
✅ Quality and safety management: establishing standardized protocols and procedures, together with continuous monitoring and evaluation mechanisms.
HIBA’s experience demonstrates that scaling robotic surgery requires more than simply introducing a robotic system. It calls for a comprehensive program encompassing clinical applications, multidisciplinary training, operational management, and quality and safety assurance. HIBA’s experience with Toumai® offers a practical example of how leading medical institutions can develop and scale their robotic surgery capabilities.
When a surgical robot arrives at a training institute, the temptation is to write about the machine. The more interesting thing about Cornerstone Robotics going live at IRCAD-Taiwan/ AITS Taiwan is what it does to distance.
Robotic surgery has reached a mature stage, as Dr. Huang Wayne Shih-Wei Shih-Wei Huang puts it in the film, with the different platforms converging on a similar look and a similar feel — usually the sign of a technology settling into itself. What tends to follow maturity is competition, and that is where Dr. Charles Lin picks the story up: for years a single company defined this field, and there are now twenty, thirty, perhaps forty systems arriving behind it. A market that one-sided is rarely a healthy one, and it is about to stop being one-sided.
For a training institute, though, the specification that matters is not the hardware but the second console. One surgeon operating and one mentor guiding, in the same case at the same time, is the mechanism by which a young surgeon's complication rate comes down, because the teaching happens during the procedure rather than in the debrief afterwards. Over the coming year that mechanism gets tested properly: consoles will be placed in cities across Taiwan, all of them connected back to the system in Lukang, and the question under study is whether training delivered by teleoperation genuinely transfers into surgical performance.
It is a question with a cost attached, because IRCAD Taiwan is the base for minimally invasive surgery training in Asia, and being the base means surgeons fly here — this week from the Philippines — which takes both time and money, and then go home to practice alone between cases. A console at the other end of the line turns proctoring and follow-up into something continuous rather than episodic, available at any time and from any place.
None of which is the same as operating on a patient in another city. That remains an ethics and safety question and will for some time yet, but the technology itself is already here, and training does not have to wait for the rest of it to catch up.
In The Week’s “Deskilling: A Dangerous Side Effect of AI Use,” the first line beneath the image reads: “Atrophied skills have been observed across a wide array of fields, including medical and mental health.” As an organizational learning and development strategist for a large behavioral health care provider, I have had this on my radar for quite some time, but I believe it should be on yours as well. Even more, as a longtime L&D professional and computer information systems educator with professional and academic backgrounds spanning adult education, higher education, information technology and organizational learning, I find this outcome unsurprising. Of course, technology has always reshaped work. What is different today is the speed with which large language models have been introduced at scale, often without sufficient preparation, governance or thoughtful integration. Hype cycles have a way of running ahead of practice, and eventually the dust settles. The Week’s article also provided examples from each of the three primary domains in which I work: In mental health, therapists are “allowing themselves to become passive in the act of therapy,” essentially becoming a “supervisor over the AI use for therapy” while limiting their “reflexive diagnostic thinking,” according to Forbes. In technology, computer coding is increasingly being delegated to AI, shifting human developers toward integration, monitoring and higher-level analysis, according to the American Enterprise Institute. In education, many students are using AI to write essays or conduct research. Yet, as The Atlantic notes, “The term paper, for all its tedium, teaches a discipline that’s hard to reproduce in conversation: building an argument step by step, weighing evidence, organizing material, honing a voice.” Over the past three years, I have intentionally observed this unfold. I’ve followed analyses from fellow L&D professionals and from professionals across industries. Some of those conversations have lacked nuance, particularly in sectors like health care, where the context differs significantly from many commercial environments. Too often in these conversations, AI has been presented as inherently good and urgently in need of implementation without sufficient clarity about the problems being solved, the value being created or how people will adopt, integrate and sustain the change over time. For nearly my entire career, I have worked to understand both sides: the human and the technological. I have never chosen a lane. But I have always believed there is an ethical order of prioritization. One of The Week article’s most important observations is that deskilling is not inherently negative. It has occurred throughout history and has contributed to many of the advances we benefit from today. The more important question is not whether deskilling occurs, but, rather, how much is appropriate, in what contexts and with what safeguards. Those questions require systematic and systemic thinking. The article also highlights another concern I have also been raising: What happens when the technology is unavailable? When I recently discussed on LinkedIn the importance of surgeons maintaining the ability to perform procedures without robotic assistance should a system fail mid-operation, another LinkedIn user made a similar point. The same principle explains why pilots continue to practice manual landings even though commercial aviation relies heavily on automation. Automation can extend human capability, but resilience depends on preserving essential human expertise. Then there is the question of equity. At times, conversations on LinkedIn proceed as though everyone, everywhere, has equal access to the same technologies and will experience AI in the same way. They will not. Not every health care system can afford multimillion-dollar surgical robotics platforms. When I underwent surgery in 2013, the robotic system being used at Johns Hopkins Medicine was, at the time, unique within my region. Access to advanced technology varies considerably across health care organizations, communities and countries. We also tend to overlook the ongoing costs of these systems. Sometimes discussions treat AI adoption as though it is inevitable and self-sustaining. Yet these technologies depend upon continual investment in fresh knowledge and research, much of which comes from institutions that some now argue AI is replacing, including higher education and journalism. They also depend upon significant computing infrastructure, energy, water and the people who build, maintain, govern and improve these systems. Because I completed my doctoral work within a school of education and urban studies grounded in a social justice mission, equity will always be one of the lenses I bring to both research and practice. That perspective also shaped my own doctoral research. I examined how systems usability varied across regions, including rural and urban communities where differences in digital infrastructure significantly affected access and user experience. Those same infrastructure differences continue to matter in health care today. I also tried to ensure my professional experiences reflected those realities. In 2012, I accepted a significant pay cut to work in a rural community while completing my doctorate. Later, I returned to a larger suburban region outside Washington, D.C., continuing my work across different organizational settings. Experiencing multiple contexts has been important to developing a broader perspective rather than assuming one environment represents everyone. I mention this because it matters. When people make decisions that affect others, they must understand the people those decisions affect and make reasonable efforts to understand their experiences. Not everyone will have opportunities to work across as many settings as I have, but I have found one principle to be consistently true: When we neglect those whose needs are less visible, the consequences eventually extend far beyond those communities. This is why I continue to advocate for partnership, unhurried practice and thoughtful exploration before deciding what should and should not be delegated to AI. Those decisions should be considered through multiple lenses. Philosophically, we should ask questions about ethics, equity, justice, human agency, professional responsibility and what kinds of expertise we believe society ought to preserve. Practically, we should examine patient safety, workforce capability, organizational resilience, regulatory requirements, cost, infrastructure, accessibility, continuity during system failures and long-term learning. Technology has always changed what people do. The more enduring question is whether we are being equally intentional about preserving what people still need to know.
MediThinQ, a South Korea-based innovator in surgical visualization technologies, has entered into an exclusive multi-year distribution agreement with Synovis ...
The safe deployment of surgical AI depends on governance as well as technology.
Addressing bias, liability, regulatory gaps, and unequal access will be critical to ensure AI and robotics improve outcomes without reinforcing existing health disparities.
Read article by Prokar Dasgupta, Alejandro Granados, Nicholas Raison, Tom Vercauteren, and others from King’s College London, San Raffaele Hospital, Guy’s Hospital, and more ⬇️
A revolutionary leap in maxillofacial reconstructive surgery has been unveiled with the development of an integrated system that combines robot-assisted osteotomy and augmented reality (AR) guidance.This groundbreaking approach, spearheaded by a team of researchers at the Beijing Institute of Technology,...
Discover the top robotic surgery companies and healthcare stocks to watch in 2026, including leaders in AI-assisted surgical systems and minimally invasive technology.
To get content containing either thought or leadership enter:
To get content containing both thought and leadership enter:
To get content containing the expression thought leadership enter:
You can enter several keywords and you can refine them whenever you want. Our suggestion engine uses more signals but entering a few keywords here will rapidly give you great content to curate.


 Your new post is loading...