Your new post is loading...

|
Scooped by
nrip
May 18, 2021 11:48 PM
|
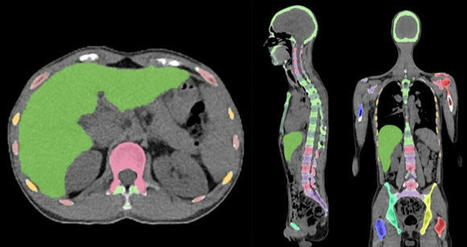
Skeleton/bone marrow involvement in patients with newly diagnosed Hodgkin’s lymphoma (HL) is an important predictor of adverse outcomes1. Studies show that FDG-PET/CT upstages patients with uni- or multifocal skeleton/bone marrow uptake (BMU) when iliac crest bone marrow biopsy fails to find evidence of histology-proven involvement. The general recommendation is, therefore, that bone marrow biopsy can be avoided when FDG-PET/CT is performed at staging. Our aim was to develop an AI-based method for the detection of focal skeleton/BMU and quantification of diffuse BMU in patients with HL undergoing staging with FDG-PET/CT. The output of the AI-based method in a separate test set was compared to the image interpretation of ten physicians from different hospitals. Finally, the AI-based quantification of diffuse BMU was compared to manual quantification. Artificial intelligence-based classification A convolutional neural network (CNN) was used to segment the skeletal anatomy11. Based on this CNN, the bone marrow was defined by excluding the edges from each individual bone; more precisely, 7 mm was excluded from the humeri and femora, 5 mm was excluded from the vertebrae and hip bones, and 3 mm was excluded from the remaining bones. Focal skeleton/bone marrow uptake The basic idea behind our approach is that the distribution of non-focal BMU has a light tail and most pixels will have an uptake reasonably close to the average. There will still be variations between different bones. Most importantly, we found that certain bones were much more likely to have diffuse BMU than others. Hence, we cannot use the same threshold for focal uptake in all bones. At the other end, treating each bone individually is too susceptible to noise. As a compromise, we chose to divide the bones into two groups: -
“spine”—defined as the vertebrae, sacrum, and coccyx as well as regions in the hip bones within 50 mm from these locations, i.e., including the sacroiliac joints. -
“other bones”—defined as the humeri, scapulae, clavicles, ribs, sternum, femora, and the remaining parts of the hip bones. For each group, the focal standardized uptake values (SUVs) were quantified using the following steps: - Threshold computation. A threshold (THR) was computed using the mean and standard deviation (SD) of the SUV inside the bone marrow. The threshold was set to
- 2. Abnormal bone region. The abnormal bone region was defined in the following way:
Only the pixels segmented as bone and where SUV > THR were considered. To reduce the issues of PET/CT misalignment and spill over, a watershed transform was used to assign each of these pixels to a local maximum in the PET image. If this maximum was outside the bone mask, the uptake was assumed to be leaking into the bone from other tissues and was removed. Finally, uptake regions smaller than 0.1 mL were removed. - 3.Abnormal bone SUV quantification. The mean squared abnormal uptake (MSAU) was first calculated as
MSAU=meanof(SUV−THR)2overtheabnormalboneregion. To quantify the abnormal uptake, we used the total squared abnormal uptake (TSAU), rather than the more common total lesion glycolysis (TLG). We believe TLG tends to overestimate the severity of larger regions with moderate uptake. TSAU will assign a much smaller value to such lesions, reflecting the uncertainty that is often associated with their classification. Instead, TSAU will give a larger weight to small lesions with very high uptake. This reflects both the higher certainty with respect to their classification and the severity typically associated to very high uptake. TSAU=MSAU×(volumeoftheabnormalboneregion). This calculation leads to two TSAU values; one for the “spine” and one for the “other bones”. As the TSAU value can be nonzero even for patients without focal uptake, cut-off values were tuned using the training cohort. The AI method was adjusted in the training group to have a positive predictive value of 65% and a negative predictive value of 98%. For the “spine”, a cut-off of 0.5 was used, and for the “other bones”, a cut-off of 3.0 was used. If one of the TSAU values was higher than the corresponding cut-off, the patient was considered to have focal uptake. Results Focal uptake Fourteen of the 48 cases were classified as having focal skeleton/BMU by the AI-based method. The majority of physicians classified 7/48 cases as positive and 41/48 cases as negative for having focal skeleton/BMU. The majority of the physicians agreed with the AI method in 39 of the 48 cases. Six of the seven positive cases (86%) identified by the majority of physicians were identified as positive by the AI method, while the seventh was classified as negative by the AI method and by three of the ten physicians. Thirty-three of the 41 negative cases (80%) identified by the majority of physicians were also classified as negative by the AI method. In seven of the remaining eight patients, 1–3 physicians (out of the ten total) classified the cases as having focal uptake, while in one of the eight cases none of the physicians classified it as having focal uptake. These findings indicate that the AI method has been developed towards high sensitivity, which is necessary to highlight suspicious uptake. Conclusions The present study demonstrates that an AI-based method can be developed to highlight suspicious focal skeleton/BMU in HL patients staged with FDG-PET/CT. This AI-based method can also objectively provide results regarding high versus low BMU by calculating the SUVmedian value in the whole spine marrow and the liver. Additionally, the study also demonstrated that inter-observer agreement regarding both focal and diffuse BMU is moderate among nuclear medicine physicians with varying levels of experience working at different hospitals. Finally, our results show that the automated method regarding diffuse BMU is comparable to the manual ROI method. read the original paper at https://www.nature.com/articles/s41598-021-89656-9
|
|
Scooped by
nrip
May 18, 2021 12:56 PM
|
The aim of the Connected Healthcare Study was to understand the impact COVID-19 has had on health care and communication with providers and gain insights into experiences and preferences as it relates to telehealth and online health care tools. More than two-thirds of U.S. patients (69%) had seen a health care provider via telehealth since the COVID-19 pandemic began, with more than two in five (46%) meeting with a PCP and about one in five (19%) meeting with a mental health care provider. Other providers whom respondents have seen via telehealth since the pandemic began included specialties like ophthalmology and women’s health and orthopedic care, which were not considered typical telehealth users before the pandemic. Telehealth is clearly emerging from the COVID-19 pandemic as the new normal – an overwhelming majority (84%) of respondents who received telehealth services since March 2020 reported that they plan to continue using telehealth appointments in the future, with the top reasons being that it’s more convenient (43%) or to avoid being around people who are ill (39%). One of the most striking results of the survey was that nearly half of U.S. patients (48%) reported that they have sought (4%) or would be likely to seek care (44%) from a different health care provider if their current provider did not offer telehealth appointments. This is clearly a resounding message of support for telehealth from patients to their physicians. As we look back on the broader impact of the COVID-19 pandemic, it will have catapulted patient awareness and acceptance of telehealth and virtual care to the extent that would have been inconceivable before the pandemic. It has also brought to the forefront many other aspects of patient electronic and virtual engagement with providers across all specialties. read the entire post at https://www.kevinmd.com/blog/2021/05/how-do-patients-really-feel-about-virtual-care-and-electronic-patient-engagement.html
|
|
Scooped by
nrip
May 18, 2021 1:22 AM
|
Low anterior resection syndrome (LARS) is a common functional disorder that develops after patients with rectal cancer undergo anal preservation surgery. Common approaches to assess the symptoms of patients with LARS are often complex and time-consuming. Instant messaging/social media has great application potential in LARS follow-up, but has been underdeveloped. Objective: The aim of this study was to compare data between a novel instant messaging/social media follow-up system and a telephone interview in patients with LARS and to analyze the consistency of the instant messaging/social media platform. Methods: Patients with R0 resectable rectal cancer who accepted several defecation function visits via the instant messaging/social media platform and agreed to a telephone interview after the operation using the same questionnaire including subjective questions and LARS scores were included. Differences between the 2 methods were analyzed in pairs and the diagnostic consistency of instant messaging/social media was calculated based on telephone interview results. Conclusions The instant messaging/social media system provides a promising solution to accommodate the primary follow-up needs of patients with LARS by integrating complex functional follow-up tools into smartphone apps. Although it is currently not a substitute for manual follow-up, it has the potential of becoming a major LARS screening method. However, further research on response rate, information accuracy, and user acceptance is needed before an advanced system can be implemented
|
|
Scooped by
nrip
May 16, 2021 1:52 PM
|
As we move through the world, what we see is seamlessly integrated with our memory of the broader spatial environment. How does the brain accomplish this feat? A new study from Dartmouth College reveals that three regions of the brain in the posterior cerebral cortex, which the researchers call "place-memory areas," form a link between the brain's perceptual and memory systems. The findings are published in Nature Communications. For the study, an innovative methodology was employed. Participants were asked to perceive and recall places that they had been to in the real world during functional magnetic resonance imaging (fMRI), which produced high-resolution, subject specific maps of brain activity. Past studies on scene perception and memory have often used stimuli that participants knew of but had never visited, like famous landmarks, and have pooled data across many subjects. By mapping the brain activity of individual participants using real-world places that they had been to, researchers were able to untangle the brain's fine-grained organization. In one experiment, 14 participants provided a list of people that they knew personally and places that they have visited in real-life (e.g., their father or their childhood home). Then, while in the fMRI scanner, the participants imagined that they were seeing those people or visiting those places. Comparing the brain activity between people and places revealed the place-memory areas. Importantly, when the researchers compared these newly identified regions to the brain areas that process visual scenes, the new regions were overlapping but distinct. "Learning how the mind is organized is at the heart of the quest of understanding what makes us human. The place-memory network provides a new framework for understanding the neural processes that drive memory-guided visual behaviors, including navigation," explains Robertson. The research team is currently using virtual reality technology to explore how representations in the place-memory areas evolve as people become more familiar with new environments. read the original unedited article at https://medicalxpress.com/news/2021-05-reveals-memories-familiar-brain.html read the study paper "A network linking scene perception and spatial memory systems in posterior cerebral cortex" at http://dx.doi.org/10.1038/s41467-021-22848-z
|
|
Scooped by
nrip
May 15, 2021 4:50 PM
|
Bose is entering the digital health market launch of Bose SoundControl Hearing Aids – the first FDA-cleared, direct-to-consumer hearing aid. Weighing 3 grams each, the new SoundControl™ Hearing Aids are developed for adults with perceived mild to moderate hearing loss. – Paired with the revolutionary Bose Hear app, users can fit, program, and control a SoundControl Hearing Aid for clinically proven, audiologist-quality results — without a doctor visit, hearing test, or prescription. And they can make setting adjustments themselves, in real-time and real-world environments, without assistance from a healthcare professional. Clinical Study Outcomes/Results In a clinical study with researchers at Northwestern University, Bose CustomTune technology yielded results that were as good if not better than those achieved by traditional prescription-fitting methods used by audiologists. The study’s participants were split into two groups with similar levels of hearing loss. One group used Bose CustomTune technology to self-tune a device, the other had the same device fit and tuned by an audiologist. Participants using Bose CustomTune technology reported being more satisfied with their sound quality than those whose devices were tuned by a hearing health professional. read more at https://hitconsultant.net/2021/05/12/bose-launches-first-fda-cleared-dtc-hearing-aids/
|
|
Scooped by
nrip
May 15, 2021 1:32 AM
|
The use of technology in health care has proven to increases care providers, the capabilities and to patients, access to improved quality of healthcare. During the GDD summit organized by BAO Systems, it occurred that some of the most beneficial countries include Nigeria. Speaking at the summit, InStrat Global Health Solution (InStratGHS) CEO, Okey Okuzu, discussed the design, deployment, and impact of Artificial Intelligence (AI) tool – EWORS for TB case finding in Nigeria. EWORS is built on the MediXcel Digital Health Platform by Plus91 “Our goal is to overcome barriers to healthcare delivery in low resource settings presented by infrastructural challenges,” he noted. “We achieve this by leveraging mobile health technologies that allow for smooth flow of information across the health system for more effective patient health management or policy decisions regardless of physical location.” The MediXcel-EWORS system is designed to drive actionable AI for public health intervention by sieving through a large volume of data to enable specific geospatial identification of disease cases and also predict the possibility of an outbreak based on historical data and set algorithm threshold. This helps local surveillance personnel to make data-informed decisions to curb the spread of diseases. Field data, captured on android devices wirelessly transferred to a cloud server for storage and analysis. “The EWORS engine conducts advanced analytics to detect unexpected elevations in indicator data and populates this information on real-time GIS heat maps, reports, and alert notifications,” he added. The alert notifications are generated in form of emails/SMS and sent to designated individuals when data from local areas exceed set thresholds, indicating undetected community spread. Designated teams review alarms and mobilize to conduct mass screening outreach at Alarm locations. Under a USAID-funded program led by the KNCV TB Foundation, and in partnership with Plus91 PVT, InStrat GHS deployed its EWORS predictive engine to 14 Nigerian states as a solution to find undetected TB cases in the country. The Analyses of the data from program inception to date demonstrate that prioritization of case finding outreach efforts, based on hotspot analytics and alarms, increases the yield of those efforts. This strategy is crucial to finding missing TB cases and improving case-finding, especially in low resource settings, read more at https://www.cio.co.ke/role-of-ai-in-healthcare-tb-prevalence-in-nigeria/ read about Instrats at https://instratghs.com/ read about Plus91 and MediXcel at https://plus91.in/about-us/ read about KCNV at https://kncvnigeria.org/
|
|
Scooped by
nrip
May 13, 2021 11:55 PM
|
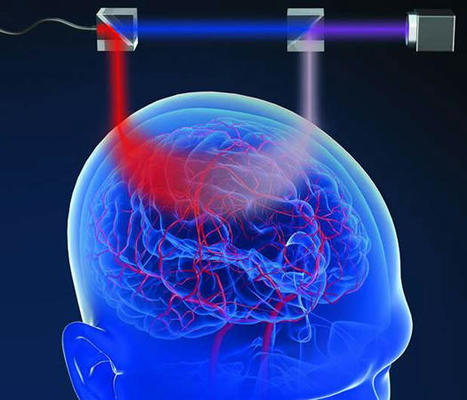
A new, noninvasive method for measuring brain blood flow with light has been developed by biomedical engineers and neurologists at the University of California, Davis, and used to detect brain activation. The new method, functional interferometric diffusing wave spectroscopy, or fiDWS, promises to be cheaper than existing technology and could be used for assessing brain injuries, or in neuroscience research. The human brain makes up 2% of our body weight but takes 15% to 20% of blood flow from the heart. Measuring cerebral blood flow is important for diagnosing strokes, and for predicting secondary damage in subarachnoid hemorrhages or traumatic brain injuries. Doctors who provide neurological intensive care, would also like to monitor a patient's recovery by imaging brain blood flow and oxygenation. Existing technology is expensive and cannot be applied continuously or at the bedside. For example, current techniques to image cerebral blood flow require expensive MRI or computed tomography scanners. There are light-based technologies, such as near-infrared spectroscopy, but these also have drawbacks in accuracy. The new method takes advantage of the fact that near-infrared light can penetrate through body tissues. If you shine a near-infrared laser on someone's forehead, the light will be scattered many times by tissue, including blood cells. By picking up the fluctuation signal of the light that finds its way back out of the skull and scalp, you can get information about blood flow inside the brain. read more at https://medicalxpress.com/news/2021-05-brain-blood.html
|
|
Scooped by
nrip
May 13, 2021 7:38 AM
|
As the use of artificial intelligence (AI) in health applications grows, health providers are looking for ways to improve patients' experience with their machine doctors. Researchers from Penn State and University of California, Santa Barbara (UCSB) found that people may be less likely to take health advice from an AI doctor when the robot knows their name and medical history. On the other hand, patients want to be on a first-name basis with their human doctors. When the AI doctor used the first name of the patients and referred to their medical history in the conversation, study participants were more likely to consider an AI health chatbot intrusive and also less likely to heed the AI's medical advice, the researchers added. However, they expected human doctors to differentiate them from other patients and were less likely to comply when a human doctor failed to remember their information. The findings offer further evidence that machines walk a fine line in serving as doctors. Machines do have advantages as medical providers, said Joseph B. Walther, distinguished professor in communication and the Mark and Susan Bertelsen Presidential Chair in Technology and Society at UCSB. He said that, like a family doctor who has treated a patient for a long time, computer systems could — hypothetically — know a patient’s complete medical history. In comparison, seeing a new doctor or a specialist who knows only your latest lab tests might be a more common experience, said Walther, who is also director of the Center for Information Technology and Society at UCSB. “This struck us with the question: ‘Who really knows us better: a machine that can store all this information, or a human who has never met us before or hasn’t developed a relationship with us, and what do we value in a relationship with a medical expert?’” said Walther. “So this research asks, who knows us better — and who do we like more?” Accepting AI doctors As medical providers look for cost-effective ways to provide better care, AI medical services may provide one alternative. However, AI doctors must provide care and advice that patients are willing to accept, according to Cheng Chen, doctoral student in mass communications at Penn State. “One of the reasons we conducted this study was that we read in the literature a lot of accounts of how people are reluctant to accept AI as a doctor,” said Chen. “They just don’t feel comfortable with the technology and they don’t feel that the AI recognizes their uniqueness as a patient. So, we thought that because machines can retain so much information about a person, they can provide individuation, and solve this uniqueness problem.” The findings suggest that this strategy can backfire. “When an AI system recognizes a person’s uniqueness, it comes across as intrusive, echoing larger concerns with AI in society,” said Sundar. In the future, the researchers expect more investigations into the roles that authenticity and the ability for machines to engage in back-and-forth questions may play in developing better rapport with patients. read more at https://news.psu.edu/story/657391/2021/05/10/research/patients-may-not-take-advice-ai-doctors-who-know-their-names
|
|
Scooped by
nrip
May 12, 2021 7:26 PM
|
In this seventh installment in Healthcare IT News' feature series, Health IT Lessons Learned During the COVID-19 Era, A CIO, a CMIO and two IT directors offer readers what they've discovered since the pandemic response has reshaped health system priorities. They share what they've learned during the past year and discuss how they're applying these lessons to improve their organizations. The increased importance of data and analytics Overall, the COVID-19 pandemic has catapulted the importance of data analytics and data in general, For example, the data analytics team at Sanford Health designed an algorithm to sort and pull relevant data from the records of more than 100,000 patients who had been diagnosed with COVID-19, identifying those at highest risk of complications from the virus. More, more, more patient engagement For Averill of St. Luke's Regional Healthcare System, the impact of patient engagement using patient portal communication, virtual visits and digital appointment-scheduling provided a big lesson. They also expanded the amount of clinical information sent in real time to the portal since delivering in-person results wasn't possible. When telehealth is not up to par One major lesson Helio Health learned last year was that its telehealth presence was not up to par. On the other hand, the health system also learned that its teams could implement a telehealth presence fairly quickly. They had to pivot quickly to be certain their patients' critical care would not be interrupted by restrictions put in place as a result of COVID-19 Leveraging technology to further strategy Rollins of Freeman Health System said 2020 was a great year for health IT for many reasons. Many important initiatives were pushed forward and implemented in attempts to react to the ever-changing needs of our customers. Keeping strategies dynamic Another lesson Rollins has learned over the past year is that health IT and organizational strategies must leave room to adapt to the environment. Streamlined and efficient decision-making On another front, the pandemic has underscored the importance of having a structured mechanism and system in place for streamlined and efficient decision-making, Standardized processes and equipment Another lesson Helio Health has learned is the need for standardization of equipment and processes,. "The vast majority of our computers were desktop PCs," he noted. "With a grant from the FCC, we were able to standardize our outpatient facilities with Microsoft laptops, which allow us to work and provide support from anywhere. Users are able to come and go, from remote work to in-person work, easily. With a recent merger between Helio Health and two other organizations, much of the hardware from the other organizations was dissimilar to Helio Health's standards. read the details at https://www.healthcareitnews.com/news/it-execs-talk-new-strategies-analytics-patient-engagement-telehealth-and-more
|
|
Scooped by
nrip
May 12, 2021 1:27 AM
|
“ATMAN AI”, an Artificial Intelligence algorithm that can detect the presence of COVID-19 disease in Chest X Rays, has been developed to combat COVID fatalities involving lung. ATMAN AI is used for chest X-ray screening as a triaging tool in Covid-19 diagnosis, a method for rapid identification and assessment of lung involvement. This is a joint effort of the DRDO Centre for Artificial Intelligence and Robotics (CAIR), 5C Network & HCG Academics. This will be utilized by online diagnostic startup 5C Network with support of HCG Academics across India. Triaging COVID suspect patients using X Ray is fast, cost effective and efficient. It can be a very useful tool especially in smaller towns in India owing to lack of easy access to CT scans there. This will also reduce the existing burden on radiologists and make CT machines which are being used for COVID be used for other diseases and illness owing to overload for CT scans. The novel feature namely “Believable AI” along with existing ResNet models have improved the accuracy of the software and being a machine learning tool, the accuracy will improve continually. Chest X-Rays of RT-PCR positive hospitalized patients in various stages of disease involvement were retrospectively analysed using Deep Learning & Convolutional Neural Network models by an indigenously developed deep learning application by CAIR-DRDO for COVID -19 screening using digital chest X-Rays. The algorithm showed an accuracy of 96.73%. read more at http://indiaai.gov.in/news/drdo-cair-5g-network-and-hcg-academics-develop-atman-ai
|
|
Scooped by
nrip
May 11, 2021 12:26 PM
|
Eko, a cardiopulmonary digital health company, today announced the peer-reviewed publication of a clinical study that found that the Eko artificial intelligence (AI) algorithm for detecting heart murmurs is accurate and reliable, with comparable performance to that of an expert cardiologist. These findings suggest utility of the FDA-cleared Eko AI algorithm as a front line clinical tool to aid clinicians in screening for cardiac murmurs that may be caused by valvular heart disease. For moderate-to-severe aortic stenosis, the algorithm was found to have sensitivity of 93.2% and specificity of 86.0%. The algorithm significantly outperformed general practitioners listening for moderate-to-severe valvular heart disease, as a 2018 study showed general practitioners had sensitivity of 44% and specificity of 69%.
|
|
Scooped by
nrip
May 10, 2021 1:17 PM
|
The Internet of Things (IoT) is a network of physical objects that can share electronic information when gathered together. They include sensors that have the ability to track information about the human body or industrial machines that transmit the production process data to the nearby sensors. The IoT is all over and is used in smart homes and even retail. It also plays a crucial role in healthcare. The Internet of Things (IoT) is changing healthcare in different ways, including improving the care patients get, better results from treatments, and reducing the costs of treatments for patients. Patients get to connect better with the healthcare providers, and their performance is also enhanced. The main benefits it has brought about to the healthcare industry include: - Real-time monitoring of patients remotely, which reduces the costs incurred during readmissions and doctor visits.
- Errors are much less likely to occur with IoT devices. The data plays an essential role in ensuring effective decision-making, and all the operations in the healthcare industry are functioning smoothly. This helps reduce the overall number of errors.
- The quality of treatment received is excellent since physicians make decisions from evidence-based information. Hence there’s complete transparency.
- Equipment and drugs are better managed. It has always been a significant challenge to manage drugs and equipment in healthcare. However, with devices being connected, the drugs and equipment are utilized and managed efficiently, which helps with cost reduction.
- Diagnosis is much faster and more accurate. A patient can be diagnosed more efficiently due to consistent remote monitoring. Real-time data is collected, and it helps with the diagnosis of a vast number of different diseases. They are diagnosed at an early stage before they worsen or even before the disease develops fully.
IoT devices are revolutionizing how healthcare is delivered and monitored. We guess that we still have only seen the tip of the iceberg. In the years to come, the question will not be if we are connected but how we will be connected and protect our privacy: digital tattoos, smartwatches, smart lenses, or smart pills being just some of the possibilities. The Internet of Things and the multitude of connected devices it offers is on a path to disrupt how healthcare is carried out. Discover how by reading the original article at https://digitalhealthcentral.com/2021/05/07/the-benefits-of-internet-of-things-in-healthcare/
|
|
Scooped by
nrip
May 8, 2021 1:54 AM
|
Since the start of the pandemic, new technologies have been developed to help reduce the spread of the infection. Some of the most common safety measures today include measuring a person’s temperature, covering your nose and mouth with a mask, contact tracing, disinfection, and social distancing. Many businesses have adopted various technologies, including those with artificial intelligence (AI) underneath, helping to adhere to the COVID-19 safety measures. As an example, numerous airlines, hotels, subways, shopping malls, and other institutions are already using thermal cameras to measure an individual’s temperature before people are allowed entry. In its turn, public transport in France relies on AI-based surveillance cameras to monitor whether or not people are social-distancing or wearing masks. Another example is requiring the download of contact-tracing apps delivered by governments across the globe. However, there are a number of issues. While many of these solutions help to ensure that COVID-19 prevention practices are observed, many of them have flaws or limits. In this article, we will cover some of the issues creating obstacles for fighting the pandemic. Issue #1. Manual temperature scanning is tricky Issue #2. Monitoring crowds is even more complex Issue #3. Contact tracing leads to privacy concerns Issue #4. UV rays harm eyes and skin Issue #5. UVC robots are extremely expensive Issue #6. No integration, no compliance, no transparency Regardless of the safety measures in place and existing issues, innovations are already playing a vital role in the fight against COVID-19. By improving on existing technology, we can make everyone safer as we all adjust to the new normal. read the details at https://www.altoros.com/blog/whats-wrong-with-ai-tools-and-devices-preventing-covid-19/
|
|
|
Scooped by
nrip
May 18, 2021 7:12 PM
|
The pandemic has accelerated some trends here, notably telemedicine. That’s given a healthy push to an emerging field – remote diagnostics. Your phone is gradually – with some extensions – turning into a remote diagnostic tool to replace doctor visits and expensive tests. That’s fairly well known, even if it is extraordinary: blood oxygen levels are captured by a device costing less than $20, while an always-on cardiac monitor tracks heart activity, for example. But that’s just the very tip of the iceberg. Remote diagnosis can transform the entire scientific basis of modern medicine. Currently, the gold standard for testing the safety and efficacy of treatments is the randomized control trial (RCT), in which some part of the trial group is treated while another part is not. Both are tracked to see whether the treatment worked, and to look for adverse events like additional illness or even deaths. Outcomes are assessed using standard statistical tools to compare the two groups. This is the gold standard. But it is based on a single core assumption: that humans by and large react similarly to treatments, and hence that the best way to address disease is to identify treatments that work effectively for large numbers of patients. Ideally, treatments work for everyone, although sometimes RCTs and subsequent tracking find groups for which a treatment doesn’t work, or another for which it works especially well – maybe the old (or young), men (or women), or people with specific pre-existing conditions. Still, this is definitely mass-oriented medicine: it’s based on the impact of treatments on what might be called the median patient. Amazon is about to enter healthcare in a big way. It is already planning to offer Amazon Care (its primary care system organized around telehealth) not just to its 1.2 million employees, but to other employers as a service, much like it offered Amazon Web Services 15 years ago (and AWS is now the leading provider of internet infrastructure in the world). It also purchased Pillpack and set up Amazon Pharmacy to deliver medications and other health products online for delivery. But the real revolution is coming inside the home. The Amazon Halo is a new health monitoring device (with some admittedly creepy privacy-related features). It is designed to apply the capabilities of AI to the needs of individual patients. And then there is Alexa, which is clearly going to be Amazon’s device of choice for wellness in the home. It’s already partnered with Sharecare to provide automated advice on 80,000 wellness and health questions, as a first line response to health concerns. Alexa will likely expand, gaining the capacity to integrate remote diagnostics and escalation into Amazon’s wider telehealth network. Still, this mostly sounds like more of the same: using telehealth and the telemedicine capabilities, but mainly just extending what we do now, making it all a bit more convenient – possibly, a lot more convenient. But all these new tools, and especially diagnostics tools, make truly personal medicine possible – like Amazon, all this will be individual-specific: a market segment of you. read the entire unedited article at https://www.healthitanswers.net/into-the-future-amazon-and-the-coming-rise-of-personal-healthcare/
|
|
Scooped by
nrip
May 18, 2021 4:49 AM
|
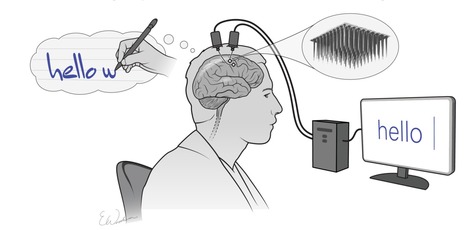
The combination of mental effort and state-of-the-art technology have allowed a man with spinal injury and immobilized limbs, to communicate by text at speeds rivaling those achieved by his able-bodied peers texting on a smartphone. Call it mindwriting. Scientists at Stanford University, Howard Hughes Medical Institute, and Brown University, developed an implanted brain-computer interface (BCI) technology that uses artificial intelligence to convert brain signals generated when someone visualizes the process of handwriting, into text on a computer, in real time. The team now reports on a trial in which a paralyzed clinical trial participant with a BCI implant was able to “type” words on a computer by merely thinking about the hand motions involved in creating written letters. The software effectively decoded the information from the BCI to quickly convert the man’s thoughts about handwriting into text on a computer screen. In the reported study, the 65-year-old male participant achieved a typing rate of 90 characters per minute, more than double the previous record for typing with a brain-computer interface. The goal is to restore the ability to communicate by text. As per Frank Willett, PhD, the first author of the paper, The system is so fast because each letter elicits a highly distinctive activity pattern, making it relatively easy for the algorithm to distinguish one from another, The new study is part of the BrainGate clinical trial, directed by Leigh Hochberg, MD, a neurologist and neuroscientist at Massachusetts General Hospital, Brown University, and the Providence VA Medical Center. The BrainGate collaboration has been working for several years on systems that enable people to generate text through direct brain control. While a major focus of BCI research has been on restoring gross motor skills, as the team further noted, “rapid sequences of highly dexterous behaviors, such as handwriting or touch typing, might enable faster rates of communication.” What wasn’t known, they pointed out, was whether “… the neural representation for a rapid and highly dexterous motor skill, such as handwriting, also remains intact.” Next, the team intends to work with a participant who cannot speak, such as someone with amyotrophic lateral sclerosis, a degenerative neurological disorder that results in the loss of movement and speech. In addition, they are looking to increase the number of characters available to the participants, such as capital letters and numbers. read the paper "High performance Brain-to-Text communication via handwriting" read the article in its entirety at https://www.genengnews.com/news/brain-computer-interface-converts-mental-handwriting-into-written-text/
|
|
Scooped by
nrip
May 16, 2021 7:53 PM
|
Since the early years of artificial intelligence, scientists have dreamed of creating computers that can “see” the world. As vision plays a key role in many things we do every day, cracking the code of computer vision seemed to be one of the major steps toward developing artificial general intelligence. But like many other goals in AI, computer vision has proven to be easier said than done. In the past decades, advances in machine learning and neuroscience have helped make great strides in computer vision. But we still have a long way to go before we can build AI systems that see the world as we do. Biological and Computer Vision, a book by Harvard Medical University Professor Gabriel Kreiman, provides an accessible account of how humans and animals process visual data and how far we’ve come toward replicating these functions in computers. Kreiman’s book helps understand the differences between biological and computer vision. The book details how billions of years of evolution have equipped us with a complicated visual processing system, and how studying it has helped inspire better computer vision algorithms. Kreiman also discusses what separates contemporary computer vision systems from their biological counterpart. Hardware differences Biological vision is the product of millions of years of evolution. There is no reason to reinvent the wheel when developing computational models. We can learn from how biology solves vision problems and use the solutions as inspiration to build better algorithms. Before being able to digitize vision, scientists had to overcome the huge hardware gap between biological and computer vision. Biological vision runs on an interconnected network of cortical cells and organic neurons. Computer vision, on the other hand, runs on electronic chips composed of transistors Architecture differences There’s a mismatch between the high-level architecture of artificial neural networks and what we know about the mammal visual cortex. Goal differences Several studies have shown that our visual system can dynamically tune its sensitivities to the common. Creating computer vision systems that have this kind of flexibility remains a major challenge, however. Current computer vision systems are designed to accomplish a single task. Integration differences In humans and animals, vision is closely related to smell, touch, and hearing senses. The visual, auditory, somatosensory, and olfactory cortices interact and pick up cues from each other to adjust their inferences of the world. In AI systems, on the other hand, each of these things exists separately. read more at https://venturebeat.com/2021/05/15/understanding-the-differences-between-biological-and-computer-vision/
|
|
Scooped by
nrip
May 15, 2021 4:55 PM
|
Mobile health apps are becoming increasingly popular, and they provide opportunities for effective health management. Existing chronic disease management (CDM) apps cannot meet users’ practical and urgent needs, and user adhesion is poor. Few studies, however, have investigated the factors that influence the continuance intention of CDM app users. Objective: Starting from the affordances of CDM apps, this study aimed to analyze how such apps can influence continuance intention through the role of health empowerment. Methods: Adopting a stimulus-organism-response framework, an antecedent model was established for continuance intention from the perspective of perceived affordances, uses and gratifications theory, and health empowerment. Perceived affordances were used as the “stimulus,” users’ gratifications and health empowerment were used as the “organism,” and continuance intention was used as the “response.” Data were collected online through a well-known questionnaire survey platform in China, and 323 valid questionnaires were obtained. The theoretical model was tested using structural equation modeling. Results: Perceived connection affordances were found to have significant positive effects on social interactivity gratification (t717=6.201, P<.001) and informativeness gratification (t717=5.068, P<.001). Perceived utilitarian affordances had significant positive effects - on informativeness gratification (t717=7.029, P<.001),
- technology gratification (t717=8.404, P<.001),
- and function gratification (t717=9.812, P<.001).
Perceived hedonic affordances had - significant positive effects on function gratification (t717=5.305, P<.001)
- and enjoyment gratification (t717=13.768, P<.001).
Five gratifications (t717=2.767, P=.005; t717=4.632, P<.001; t717=7.608, P<.001; t717=2.496, P=.012; t717=5.088, P<.001) had significant positive effects on health empowerment. Social interactivity gratification, informativeness gratification, and function gratification had significant positive effects on continuance intention. Technology gratification and enjoyment gratification did not have a significant effect on continuance intention. Health empowerment had a significant positive effect on continuance intention. Health empowerment and gratifications play mediating roles in the influence of affordances on continuance intention. Conclusions: Health empowerment and gratifications of users’ needs are effective ways to promote continuance intention. The gratifications of users’ needs can realize health empowerment and then inspire continuance intention. Affordances are key antecedents that affect gratifications of users’ needs, health empowerment, and continuance intention. The results indicated that users’ perceptions of an app’s affordances can promote the gratification of needs, and the gratification of key needs (ie, social interactivity, informativeness, technology, and function gratification) can stimulate users’ continuance intention. At the same time, the gratification of users’ needs can promote users’ cognitions of health empowerment, thus stimulating continuance intention. Health empowerment was found to play a mediating role in the influence of gratification on continuance intention. From a practical perspective, app service providers should design apps from the perspective of social interaction (eg, providing social networks), utilitarian functions (eg, health self-management), and hedonic functions (eg, enhancing the user’s interest). By meeting users’ various needs, app developers can improve the user’s ability to control his or her own health, thus achieving the purpose of extending the life of the app. more at https://mhealth.jmir.org/2021/5/e21831/
|
|
Scooped by
nrip
May 15, 2021 1:23 PM
|
Atypical eye gaze is an early-emerging symptom of autism spectrum disorder (ASD) and holds promise for autism screening. Current eye-tracking methods are expensive and require special equipment and calibration. There is a need for scalable, feasible methods for measuring eye gaze. This case-control study examines whether a mobile app that displays strategically designed brief movies can elicit and quantify differences in eye-gaze patterns of toddlers with autism spectrum disorder (ASD) vs those with typical development. In effect, using computational methods based on computer vision analysis, can a smartphone or tablet be used in real-world settings to reliably detect early symptoms of autism spectrum disorder? Findings In this study, a mobile device application deployed on a smartphone or tablet and used during a pediatric visit detected distinctive eye-gaze patterns in toddlers with autism spectrum disorder compared with typically developing toddlers, which were characterized by reduced attention to social stimuli and deficits in coordinating gaze with speech sounds. What this means These methods may have potential for developing scalable autism screening tools, exportable to natural settings, and enabling data sets amenable to machine learning. Conclusions and Relevance The app reliably measured both known and new gaze biomarkers that distinguished toddlers with ASD vs typical development. These novel results may have potential for developing scalable autism screening tools, exportable to natural settings, and enabling data sets amenable to machine learning. read the study at https://jamanetwork.com/journals/jamapediatrics/fullarticle/2779395
|
|
Scooped by
nrip
May 14, 2021 5:04 PM
|
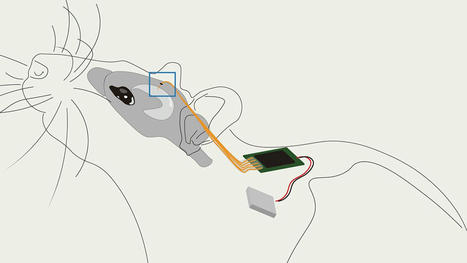
The world's smallest computer chip is the size of a dust mite! Check out the future of medical tech. Electronics are getting imperceptibly small, opening new avenues for medical technology to place advanced monitoring and treatment devices inside our bodies. And Columbia University engineers just demonstrated a new and revolutionary version of this, creating the world's smallest single-chip system ever developed, according to a recent study published in the journal Science Advances. And, critically, the tiny new chip can be implanted via a hypodermic needle to measure internal body temperature, and potentially much more. A tiny computer chip was implanted into seven mice at once The implant created by the engineers at Columbia is record-breakingly small, but it's also breaking new ground in simply existing as a wholly functional, electronic circuit whose total volume is less than 0.1 cubic millimeter. In other words, it's the size of a dust mite, not to mention far more compact than the world's smallest computer, which is a cube-shaped device precisely 0.01-inches (0.3 mm) on each side. The smaller, new chip is only visible with a microscope, and pushed the envelope in power-sourcing and communications ingenuity design. The injectable chip could serve as an 'early warning' system against future outbreaks Such tiny chips could also be implanted in the human body, and then communicate measured information and data wirelessly through ultrasound. As the device stands, it can only measure body temperature, but it could eventually also monitor respiratory function, glucose levels, and blood pressure. "We wanted to see how far we could push the limits on how small a functioning chip we could make," said Ken Shepard, leader of the Columbia study, in a report from New Atlas. "This is a new idea of 'chip as system' — this is a chip that alone, with nothing else, is a complete functioning electronic system." more at https://interestingengineering.com/smallest-ever-injectable-chip-hints-at-cybernetic-medicine
|
|
Scooped by
nrip
May 13, 2021 5:18 PM
|
We developed and validated an accurate in-hospital mortality prediction score in a live EHR for automatic and continuous calculation using a novel model that improved upon SOFA. The COVID-19 pandemic created an emergent need for a novel, accurate, and location and context-sensitive EHR-computable tool to predict mortality in hospitalized patients with and without COVID-19. Because developing a new score can take years, a predictive model must rely on well-validated scores. In contrast, COVID-19 is a novel disease for which existing scores may be of limited but unknown predictive value. As such, a predictive framework relying on multiple previously validated scores that can incorporate new information but only keeps the new inputs that explicitly improve performance is required. Stacked generalization provides a solution. A stacked model is built upon one or more baseline model(s) (e.g. SOFA) and incorporates additional models only when they improve prediction. Materials and Methods We developed, verified, and deployed a stacked generalization model to predict mortality using data available in the EHR by combining five previously validated scores and additional novel variables reported to be associated with COVID-19-specific mortality. We verified the model with prospectively collected data from 12 hospitals in Colorado between March 2020 and July 2020. We compared the area under the receiver operator curve (AUROC) for the new model to the SOFA score and the Charlson Comorbidity Index. Results The prospective cohort included 27,296 encounters, of which 1,358 (5.0%) were positive for SARS-CoV-2, 4,494 (16.5%) required intensive care unit care, 1,480 (5.4%) required mechanical ventilation, and 717 (2.6%) ended in death. The Charlson Comorbidity Index and SOFA scores predicted mortality with an AUROC of 0.72 and 0.90, respectively. Our novel score predicted mortality with AUROC 0.94. In the subset of patients with COVID-19, the stacked model predicted mortality with AUROC 0.90, whereas SOFA had AUROC of 0.85. Discussion Stacked regression allows a flexible, updatable, live-implementable, ethically defensible predictive analytics tool for decision support that begins with validated models and includes only novel information that improves prediction. read the paper abstract at https://academic.oup.com/jamia/advance-article/doi/10.1093/jamia/ocab100/6273353 read the entire paper at https://academic.oup.com/jamia/advance-article-pdf/doi/10.1093/jamia/ocab100/37905236/ocab100.pdf
|
|
Scooped by
nrip
May 13, 2021 7:27 AM
|
New artificial intelligence technology that uses a common CT angiography (CTA), as opposed to the more advanced imaging normally required to help identify patients who could benefit from endovascular stroke therapy (EST), is being developed at The University of Texas Health Science Center at Houston (UTHealth). Two UTHealth researchers worked together to create a machine-learning artificial intelligence tool that could be used for assessing a stroke at every hospital that takes care of stroke patients - not just at large academic hospitals in major cities. Research to further develop and test the technology tool is funded through a five-year, $2.5 million grant from the National Institutes of Health (NIH). "The vast majority of stroke patients don't show up at large hospitals, but in those smaller regional facilities. And most of the emphasis on screening techniques is only focused on the technologies used in those large academic centers. With this technology, we are looking to change that," said Sunil Sheth, MD, assistant professor of neurology at McGovern Medical School at UTHealth. Sheth set out with Luca Giancardo, PhD, assistant professor with the Center for Precision Health at UTHealth School of Biomedical Informatics, to develop a quicker way to assess patients. The result was a novel deep neural network architecture that leverages brain symmetry. Using CTAs, which are more widely available, the system can determine the presence or absence of a large vessel occlusion and whether the amount of "at-risk" tissue is above or below the thresholds seen in those patients who benefitted from EST in the clinical trials. "This is the first time a data set is being specifically collected aiming to address the lack of quality imaging available for stroke patients at smaller hospitals," Giancardo said. read the complete press release with further details on the work at https://www.uth.edu/news/story.htm?id=9fccdefb-ff91-4775-a759-a786689956ea
|
|
Scooped by
nrip
May 12, 2021 4:09 AM
|
Numerous studies demonstrate frequent mutations in the genome of SARS-CoV-2. Our goal was to statistically link mutations to severe disease outcome. We found that automated machine learning, such as the method of Tsamardinos and coworkers used here, is a versatile and effective tool to find salient features in large and noisy databases, such as the fast growing collection of SARS-CoV-2 genomes. In this work we used machine learning techniques to select mutation signatures associated with severe SARS-CoV-2 infections. We grouped patients into 2 major categories (“mild” and “severe”) by grouping the 179 outcome designations in the GISAID database. A protocol combined of logistic regression and feature selection algorithms revealed that mutation signatures of about twenty mutations can be used to separate the two groups. The mutation signature is in good agreement with the variants well known from previous genome sequencing studies, including Spike protein variants V1176F and S477N that co-occur with DG14G mutations and account for a large proportion of fast spreading SARS-CoV-2 variants. UTR mutations were also selected as part of the best mutation signatures. The mutations identified here are also part of previous, statistically derived mutation profiles. An online prediction platform was set up that can assign a probabilistic measure of infection severity to SARS-CoV-2 sequences, including a qualitative index of the strength of the diagnosis. The data confirm that machine learning methods can be conveniently used to select genomic mutations associated with disease severity, but one has to be cautious that such statistical associations – like common sequence signatures, or marker fingerprints in general – are by no means causal relations, unless confirmed by experiments. Our plans are to update the predictions server in regular time intervals. While this project was underway more than 100 thousand sequences were deposited in public databases, and importantly, new variants emerged in the UK and in South Africa that are not yet included in the current datasets. Also, in addition to mutations, we plan to include also insertions and deletions which will hopefully further improve the predictive power of the server. The study was funded by the Hungarian Ministry for Innovation and Technology (MIT) , within the framework of the Bionic thematic programme of the Semmelweis University. Read the entire study at https://www.biorxiv.org/content/10.1101/2021.04.01.438063v1.full Access the online portal mentioned above at https://covidoutcome.com/
|
|
Scooped by
nrip
May 12, 2021 12:12 AM
|
As researchers learn more about the brain, it has become clear that responsive neurostimulation is becoming increasingly effective at probing neural circuit function and treating neuropsychiatric disorders, such as epilepsy and Parkinson's disease. But current approaches to designing a fully implantable and biocompatible device able to make such interventions have major limitations: their resolution isn't high enough and most require large, bulky components that make implantation difficult with risk of complications. A Columbia Engineering team led by Dion Khodagholy has come up with a new approach that shows great promise to improve such devices. Building on their earlier work to develop smaller, more efficient conformable bioelectronic transistors and materials, the researchers orchestrated their devices to create high performance implantable circuits that allow reading and manipulation of brain circuits. Their multiplex-then-amplify (MTA) system requires only one amplifier per multiplexer, in contrast to current approaches that need an equal number of amplifiers as number of channels. The team built the MTA device and then confirmed its functionality by developing a fully implantable, responsive embedded system that can acquire—in real time—individual neural action potentials using conformable conducting polymer-based electrodes. It can accomplish this with low-latency arbitrary waveform stimulation and local data storage—all within a miniaturized (approximately the size of a quarter) physical footprint. Khodagholy collaborated on the study, published today by Proceedings of the National Academy of Sciences (PNAS), with Jennifer N. Gelinas, Department of Neurology and the Institute for Genomic Medicine at Columbia University Irving Medical Center. read more at https://medicalxpress.com/news/2021-05-neuroelectronic-brain-circuits.html
|
|
Scooped by
nrip
May 11, 2021 4:02 AM
|
Holograms are 3D video images of real people doing stuff such as presenting or performing "live" somewhere (albeit in digital holographic form). It’s now possible to "beam" to a remote conference stage to deliver a presentation or participate in a panel discussion as if you were there in person. Conversely, several people's holograms can simultaneously present at a conference or in a meeting and interact with each other as well as live presenters or performers. The COVID-19 pandemic has a lot of people thinking about the future of communication and collaboration. While videoconferencing has been the necessary go-to substitute for business travel and working at the office, users complain it's not the same as in-person interactions. Some organizations are adopting holograms as a new form of virtual presence, and it's making a memorable impact on audiences given its novelty. Companies in the pharmaceutical and healthcare industries are similarly using holograms to educate groups of doctors and medical practitioners. For example, instead of sending them to a posh vacation spot to learn about a new drug, pharmaceutical companies are instead inviting them to hotels for a meal and a presentation that includes the use of holograms. Pharmaceutical companies are able to cut costs and the doctors don't have to allot two or three days just to attend a relatively short presentation. Holograms aren't just science fiction anymore and their arrival seems to be well-timed, especially given the COVID-19 pandemic. There's also an early market "wow" factor that organizations can use to differentiate themselves. https://www.informationweek.com/strategic-cio/executive-insights-and-innovation/move-over-zoom-holograms-are-next/a/d-id/1340872
|
|
Scooped by
nrip
May 9, 2021 11:30 AM
|
Previous work has specifically described the potential for using telemedicine in disasters and public health emergencies. No telemedicine program can be created overnight, but U.S. health systems that have already implemented telemedical innovations can leverage them for the response to Covid-19. A central strategy for health care surge control is “forward triage” — the sorting of patients before they arrive in the emergency department (ED). Direct-to-consumer (or on-demand) telemedicine, a 21st-century approach to forward triage that allows patients to be efficiently screened, is both patient-centered and conducive to self-quarantine, and it protects patients, clinicians, and the community from exposure. It can allow physicians and patients to communicate 24/7, using smartphones or webcam-enabled computers. Respiratory symptoms — which may be early signs of Covid-19 — are among the conditions most commonly evaluated with this approach. Health care providers can easily obtain detailed travel and exposure histories. Automated screening algorithms can be built into the intake process, and local epidemiologic information can be used to standardize screening and practice patterns across providers. Much medical decision making is cognitive, and telemedicine can provide rapid access to subspecialists who aren’t immediately available in person. Recognizing that patients prioritize convenient and inexpensive care, Duffy and Lee recently asked whether in-person visits should become the second, third, or even last option for meeting patient needs read the original article at https://www.nejm.org/doi/10.1056/NEJMp2003539
|