Your new post is loading...

|
Scooped by
Gilbert C FAURE
October 6, 10:25 AM
|
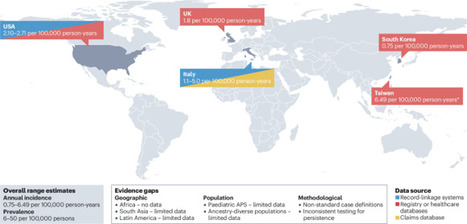
This Review provides a comprehensive overview of available evidence on the epidemiology of antiphospholipid syndrome (APS). The authors highlight the challenges associated with defining APS and its clinical heterogeneity and emphasize key areas that require further research to improve...
|
|
Scooped by
Gilbert C FAURE
April 22, 9:47 AM
|
Listen to this episode from Rheumatology Notebooks on Spotify. Podcast on "2023 ACR/EULAR antiphospholipid syndromeclassification criteria".Created with NotebookLM.Intro and outro music created with Suno.Link to the paper: http:// dx.doi. org/ 10. 1136/ ard- 2023-224609
|
|
Scooped by
Gilbert C FAURE
July 3, 2025 3:37 AM
|
|
|
Scooped by
Gilbert C FAURE
March 11, 2024 12:38 PM
|
Antiphospholipid syndrome (APS), also known as antiphospholipid antibody syndrome, is an autoimmune disorder in which autoantibodies are directed against phospholipid-protein complexes.
|
|
Scooped by
Gilbert C FAURE
December 17, 2022 1:57 AM
|
Create a free QxMD account to receive personalized paper recommendations, relevant to your practice. Get Started The role of the intestinal microbiome in antiphospholipid syndrome Dagmar J M van Mourik, Dorien M Salet, Saskia Middeldorp, Max Nieuwdorp, Thijs E van Mens Frontiers in Immunology 2022, 13: 954764 The antiphospholipid syndrome (APS) is a thrombotic autoimmune disease in which the origin of the disease-characterizing autoantibodies is unknown. Increased research effort into the role of the intestinal microbiome in autoimmunity has produced new insights in this field. This scoping review focusses on the gut microbiome in its relation to APS. EMBASE and MEDLINE were searched for original studies with relevance to the relation between the gut microbiome and APS. Thirty studies were included. Work on systemic lupus erythematosus, which strongly overlaps with APS, has shown that patients often display an altered gut microbiome composition, that the disease is transferable with the microbiome, and that microbiome manipulation affects disease activity in murine lupus models. The latter has also been shown for APS, although data on microbiome composition is less consistent. APS patients do display an altered intestinal IgA response. Evidence has accrued for molecular mimicry as an explanatory mechanism for these observations in APS and other autoimmune diseases. Specific gut microbes express proteins with homology to immunodominant APS autoantigens. The disease phenotype appears to be dependent on these mimicking proteins in an APS mouse model, and human APS B- and T-cells indeed cross-react with these mimics. Pre-clinical evidence furthermore suggests that diet may influence autoimmunity through the microbiome, as may microbial short chain fatty acid production, though this has not been studied in APS. Lastly, the microbiome has been shown to affect key drivers of thrombosis, and may thus affect APS severity through non-immunological mechanisms. Overall, these observations demonstrate the impact of the intestinal microbiome on autoimmunity and the importance of understanding its role in APS. Full Text Links We have located open access full text paper links. Full Text PDF Full Text Web Additional links Discussion You are not logged in. Sign Up or Log In to join the discussion. Related Papers Diet, microbiota and autoimmune diseases. S M Vieira, O E Pagovich, M A Kriegel Lupus 2014, 23 (6): 518-26 Pathogenic Autoreactive T and B Cells Cross-React with Mimotopes Expressed by a Common Human Gut Commensal to Trigger Autoimmunity. William E Ruff, Carina Dehner, Woo J Kim, Odelya Pagovich, Cassyanne L Aguiar, Andrew T Yu, Alexander S Roth, Silvio Manfredo Vieira, Christina Kriegel, Olamide Adeniyi, Melissa J Mulla, Vikki M Abrahams, William W Kwok, Ruth Nussinov, Doruk Erkan, Andrew L Goodman, Martin A Kriegel Cell Host & Microbe 2019 July 10, 26 (1): 100-113.e8 Abstracts of Presentations at the Association of Clinical Scientists 143 rd Meeting Louisville, KY May 11-14,2022. (no author information available yet) Annals of Clinical and Laboratory Science 2022, 52 (3): 511-525 The role of the gut microbiota in the pathogenesis of antiphospholipid syndrome. William E Ruff, Silvio M Vieira, Martin A Kriegel Current Rheumatology Reports 2015, 17 (1): 472 [The role of the microbiome in lupus and antiphospholipid syndrome]. Sylvio Redanz, Martin A Kriegel Zeitschrift Für Rheumatologie 2022, 81 (5): 423-426 Identification of novel, clinically correlated autoantigens in the monogenic autoimmune syndrome APS1 by proteome-wide PhIP-Seq. Sara E Vazquez, Elise Mn Ferré, David W Scheel, Sara Sunshine, Brenda Miao, Caleigh Mandel-Brehm, Zoe Quandt, Alice Y Chan, Mickie Cheng, Michael German, Michail Lionakis, Joseph L DeRisi, Mark S Anderson ELife 2020 May 15, 9 B cells in primary antiphospholipid syndrome: Review and remaining challenges. Yannick Dieudonné, Aurélien Guffroy, Vincent Poindron, Pauline Soulas Sprauel, Thierry Martin, Anne-Sophie Korganow, Vincent Gies Autoimmunity Reviews 2021, 20 (5): 102798 Gut Microbiota in Lupus: a Butterfly Effect? Rongli Li, Xia Meng, Beidi Chen, Lidan Zhao, Xuan Zhang Current Rheumatology Reports 2021 April 16, 23 (4): 27 Gut microbiota differently contributes to intestinal immune phenotype and systemic autoimmune progression in female and male lupus-prone mice. Benjamin M Johnson, Marie-Claude Gaudreau, Radhika Gudi, Robert Brown, Gary Gilkeson, Chenthamarakshan Vasu Journal of Autoimmunity 2020, 108: 102420 Gut Microbiota, Leaky Gut, and Autoimmune Diseases. Anna Christovich, Xin M Luo Frontiers in Immunology 2022, 13: 946248 Make the most of Read. Download the mobile app.
|
|
Scooped by
Gilbert C FAURE
February 17, 2022 2:25 PM
|
Researchers found circulating antiphospholipid antibodies, which can be more common among people with autoimmune disorders.
|
|
Scooped by
Gilbert C FAURE
October 1, 2021 5:41 AM
|
Abstract Patients with systemic lupus erythematosus (SLE) often develop glomerulonephritis (i.e., inflammation in the glomeruli of the kidney), commonly referred to as lupus nephritis. Patients with lupus nephritis typically have autoantibodies to the complement classical pathway protein C1q. Whether these anti-C1q antibodies play any role in the development of lupus nephritis has been unclear. In this issue of the JCI, a new study demonstrates that anti-C1q antibodies can amplify glomerular injury but only when they are bound within the glomerulus to C1q that has been already brought to that site by other types of glomerular-reactive autoantibodies . These studies are the first, to our knowledge, to provide a causal link between anti-C1q antibodies and target organ damage in SLE. The complement system is a central component of innate immunity that exhibits three pathways of activation: classical, alternative, and lectin-mediated. C1, a key component of the classical pathway, is actually a complex of three proteins: C1q, C1r, and C1s (1). C1q is a collagen-like component that is able to bind antibodies but only after the antibody has been bound to a foreign or self antigen. Once C1q is bound to the Fc antibody domain, C1r and C1s are sequentially cleaved and released, after which the rest of the classical pathway is activated. Immune complexes normally contain C1q bound via its “head” domains to Fc regions of IgG as part of the activation function of C1q within the classical pathway (1) (Figure 1). An alternate means of binding C1q, though, has also been described; it occurs when high-affinity autoantibodies directly recognize the collagenous “tail” portion of C1q through the antibody F(ab) antigen-combining sites rather than via the Fc domain. Since they were first described (2, 3), anti-C1q autoantibodies have been commonly identified in patients with autoimmune diseases such as systemic lupus erythematosus (SLE) and hypocomplementemic urticarial vasculitis. Although anti-C1q antibodies are associated with the presence of lupus nephritis — indeed probably serving as a biomarker for the presence of renal disease (4) — and anti-C1q antibodies are also preferentially localized in the glomeruli of patients with SLE (5), their pathophysiologic importance has remained undefined. Specifically, whether this class of acquired autoantibodies is merely an epiphenomenon or is truly pathogenic, and if so how and under what clinical circumstances, has remained an unanswered question. Figure 1 Roles of anti-C1q antibodies in the development of glomerular injury and antinuclear antibodies. (A) Anti-C1q antibodies (in yellow) such as JL-1 recognize the collagen-like “tails” of C1q in much the same manner as they would recognize any antigen through the F(ab) antigen-recognition domain. The administration of C1q and anti-C1q is not sufficient to cause glomerular injury as shown by Trouw et al. (6). However, when C1q-fixing anti-glomerular basement membrane (GBM) antibodies (in green) are first administered to mice, then C1q is able to bind to the Fc domain as it normally does. This brings anti-C1q antibodies into the glomerulus, resulting in sufficient complement activation to result in the generation of C3a, C5a, and MAC and the development of glomerulonephritis (B). As an alternate means by which anti-C1q antibodies could promote lupus-like autoimmunity, these antibodies could interfere with the normal ability of C1q to recognize apoptotic bodies containing DNA and other nuclear autoantigens (C). In this scenario, impaired clearance of apoptotic bodies, or clearance in a proinflammatory setting due to complement activation caused by the anti-C1q antibodies, could promote the development of autoantibodies that target DNA and other nuclear antigens, which is similar to what occurs when C1q is absent due to a genetic deficiency. Anti-C1q autoantibodies are pathogenic In this issue of the JCI, Trouw et al. (6) have now solved an important piece of this puzzle by first developing a murine mAb, JL-1, which was identified by ELISA based on its ability to recognize the tail domain of mouse C1q. When anti-C1q JL-1 was administered alone, it was bound in the glomerulus to C1q, which is normally present there at low levels; however, this interaction was insufficient to induce significant glomerular damage (Figure 1A). However, when JL-1 was administered to mice in which C1q levels in the glomerulus were greatly elevated as a consequence of its interaction with other antibodies with specificity for glomerular antigens, mice then exhibited significant glomerular injury as shown by decreased renal function and elevated “leakage” of protein into the urine (6) (Figure 1B). The combination of the first glomerular-binding antibody and JL-1 caused glomerular injury in a complement C4–, C3–, and Fc–dependent manner, reflecting a key role of the classical pathway itself in the generation of C3a, C5a, and the membrane attack complex (MAC). These downstream complement activation fragments are key mediators of complement-catalyzed autoimmune renal injury (7) (Figure 1B). In the setting described by Trouw et al., these complement mediators were probably generated by both types of antibodies, the initial glomerular-targeting antibodies as well as mAb JL-1. Together, the two types of antibodies generated enough mediators to be clinically important and cause glomerular injury in vivo. What do these results tell us about the role of C1q in SLE and also about this intriguing class of acquired autoantibodies? First, one has to ask whether the lone monoclonal antibody, JL-1, utilized in this study (6) to amplify glomerular injury is representative of the polyclonal population of C1q-reactive antibodies in human patients. It could be argued, as is well known in murine models, that placement of a “planted antigen” (herein possibly C1q) in the glomerulus followed by administration of a complement-fixing antibody that targets the antigen in situ readily leads to complement-dependent injury (8). The model system utilized by Trouw et al. (6) simply recapitulates this phenotype but in a clinically unrelated fashion. In addition, as pointed out by the authors, previous experiments in mice using glomerular-targeting antibodies also demonstrate dose-dependent “windows,” in which the injurious effects of complement activation are more prominent than at higher or lower doses of antibody (9). In this light, the use by the authors of a broad range of doses (of each reagent, the C1q-fixing anti-glomerular basement membrane antibody, and JL-1) would show how narrow the effect of the addition of monoclonal anti-C1q antibody on the development of glomerular injury is. However, in support of a close relationship between these findings in mice and SLE-associated lupus nephritis in humans, JL-1 is reported to recognize the same collagen-like domain of C1q as do human anti-C1q antibodies (2, 3, 6). In addition, previous studies in which C1q and polyclonal anti-C1q antibodies were both transferred into mice resulted in glomerular targeting of anti-C1q antibodies (10) as well as modest glomerular damage (11) similar to that caused by mAb JL-1 alone in the study by Trouw et al. (6). Nevertheless, a stronger link with human disease may be provided by a more careful comparison of the specific epitope reactivity of JL-1 and authentic autoantibodies from patients with glomerulonephritis. For example, is there evidence of cross-competition for C1q epitopes between human polyclonal anti-C1q autoantibodies and JL-1? Anti-C1q antibodies increase complement activation in a relatively uncontrolled fashion The complement system itself is regulated positively by amplification mechanisms (12) and negatively by regulatory proteins (13). At each activation step, a small amount of activated product can lead to the generation of from four to several thousand activated components derived from the immediate downstream target (1). The alternative pathway demonstrates an “amplification loop” effect, where C3b generated from the classical pathway can serve to bind factor B and initiate further C3 activation through formation of the C3 convertase C3bBb (12) (Figure 2). Although often thought of as a minor contributor to total complement activation — which is true if one considers only serum activation — amplification of injury in a target organ through engagement of the alternative pathway, amplifying injury in a target organ, is absolutely essential to the generation of local C5a- and MAC-dependent injury (14, 15). Figure 2 Simplified schematic demonstrating mechanisms of activation of classical and alternative pathways and generation of C3 convertases (light blue). The alternative pathway C3 convertase (green box) can be generated by the activity of the classical pathway C3 convertase C4b2a (yellow box) on C3, which results in C3b formation. This is called the alternative pathway amplification loop. In patients with C4 nephritic factors, autoantibodies react with the complex of C4b2a and keep it from being inactivated, thus generating more C3b than would normally occur. C3b* in the alternative pathway can originate from C3b generated by the classical pathway C3 convertase C4b2a. This concept is relevant to anti-C1q antibodies because the studies of Trouw et al. (6) strongly suggest that these autoantibodies likewise serve as an acquired mechanism of classical pathway amplification. Previously, the only means to amplify the classical pathway beyond what is possible through endogenous classical pathway components has been with C4-nephritic factor. This type of autoantibody, occasionally found in patients, stabilizes the classical pathway C3 convertase C4b2a and allows this convertase to generate far more activated C3 molecules than it normally would (16). Trouw et al. demonstrate that anti-C1q autoantibodies can result in a similarly amplified biologic effect of complement in vivo locally in the kidney, presumably by generating additional C3 through the classical pathway. In this light, it would be of some interest to determine the exact mechanism by which the classical pathway is amplified by JL-1 and whether this antibody interferes with other classical pathway regulatory mechanisms. Additional deleterious roles potentially played by anti-C1q autoantibodies In the larger context of lupus-like autoimmunity, C1q has taken on an increasingly important role and is necessary not only for classical pathway–dependent complement activation in target organs, as focused upon by Trouw et al. in this issue (6), but is also required to directly recognize and help to clear potentially dangerous nuclear autoantigens from apoptotic cells (17). Thus, in patients (18) and in certain autoimmune mouse strains (19), the absence of C1q leads to the development of anti-DNA antibodies and SLE. Of interest, C1q-deficient patients commonly exhibit severe renal disease (18), the cause of which has been ascribed to non–complement-dependent mechanisms, as C3 is not required in mice to develop glomerular injury in the absence of C1q (20). In this context of multiple roles for C1q, one could hypothesize that anti-C1q autoantibodies not only affect patients with SLE by injuring the kidney, as suggested by Trouw et al. (6), but also by enhancing the development of anti-DNA and other glomerular-targeting nuclear autoantibodies, because there is too little C1q available for effective clearance of these dangerous antigens (Figure 1C). Thus, these autoantibodies would not only amplify local injury but also potentially accelerate the development of antinuclear autoantibodies by interfering with C1q clearance functions (21). Alternatively, if these autoantibodies also lead to enhanced complement activation at sites where C1q is recognizing nuclear antigens, this could in principle switch noninflammatory recognition of apoptotic bodies by C1q and its receptors to inflammatory recognition when C5a and other complement activation fragments are also generated, and their receptors are engaged on cells clearing these antigens. In sum, acquired anti-C1q autoantibodies could utilize several possible mechanisms by which they could increase the severity of an autoimmune response and glomerulonephritis. The studies by Trouw et al. (6) provide an important conceptual advance in this area and open up the possibility of determining how inhibiting C1q or modulating its effects leads to severe SLE. In particular, the use of JL-1 and similar monoclonal antibodies in mouse models should allow these and other investigators to better understand the molecular mechanisms that lead both to increased development of anti-DNA antibodies and to tissue injury. Footnotes See the related article beginning on page 679. Nonstandard abbreviations used: MAC, membrane attack complex; SLE, systemic lupus erythematosus. Conflict of interest: The author has declared that no conflict of interest exists. References Lachmann, PJ, Hughes-Jones, NC. Initiation of complement activation. Springer Semin. Immunopathol. 1984. 7:143-162. View this article via: PubMed CrossRef Google Scholar Uwatoko, S, Mannik, M. Low-molecular weight C1q-binding immunoglobulin G in patients with systemic lupus erythematosus consists of autoantibodies to the collagen-like region of C1q. J. Clin. Invest. 1988. 82:816-824. View this article via: JCI PubMed CrossRef Google Scholar Wisnieski, JJ, Naff, GB. Serum IgG antibodies to C1q in hypocomplementemic urticarial vasculitis syndrome. Arthritis Rheum. 1989. 32:1119-1127. View this article via: PubMed CrossRef Google Scholar Coremans, IEM, et al. Changes in antibodies to C1q predict renal relapses in systemic lupus erythematosus. Am. J. Kidney Dis. 1995. 26:595-601. View this article via: PubMed CrossRef Google Scholar Mannik, M, Wener, MH. Deposition of antibodies to the collagen-like region of C1q in renal glomeruli of patients with proliferative lupus glomerulonephritis. Arthritis Rheum. 1997. 40:1504-1511. View this article via: PubMed CrossRef Google Scholar Trouw, LA, et al. Anti-C1q autoantibodies deposit in glomeruli but are only pathogenic in combination with glomerular C1q-containing immune complexes. J. Clin. Invest. 2004. 114:679-688.doi:10.1172/JCI200421075. View this article via: JCI PubMed Google Scholar Quigg, RJ. Complement and autoimmune glomerular diseases. Curr. Dir. Autoimmun. 2004. 7:165-180. View this article via: PubMed Google Scholar Feintzeig, ID, Dittmer, JE, Cybulski, AV, Salant, DJ. Antibody, antigen, and glomerular capillary wall charge interactions: influence of antigen location on in situ immune complex formation. Kidney Int. 1986. 29:649-657. View this article via: PubMed CrossRef Google Scholar Quigg, RJ, et al. Blockade of antibody-induced glomerulonephritis with Crry-Ig, a soluble murine complement inhibitor. J. Immunol. 1998. 160:4553-4560. View this article via: PubMed Google Scholar Uwatoko, S, Gauthier, VJ, Mannik, M. Autoantibodies to the collagen-like region of C1Q deposit in glomeruli via C1Q in immune deposits. Clin. Immunol. Immunopathol. 1991. 61:268-273. View this article via: PubMed CrossRef Google Scholar Trouw, LA, et al. Glomerular deposition of C1q and anti-C1q antibodies in mice following injection of antimouse C1q antibodies. Clin. Exp. Immunol. 2003. 132:32-39. View this article via: PubMed CrossRef Google Scholar Muller-Eberhard, HJ. Molecular organization and function of the complement system. Ann. Rev. Biochem. 1988. 57:321-347. View this article via: PubMed CrossRef Google Scholar Liszewski, MK, Farries, TC, Lublin, DM, Rooney, IA, Atkinson, JP. Control of the complement system. Adv. Immunol. 1996. 61:201-283. View this article via: PubMed CrossRef Google Scholar Girardi, G, et al. Complement C5a receptors and neutrophils mediate fetal injury in the antiphospholipid syndrome. J. Clin. Invest. 2003. 112:1644-1654. doi:10.1172/JCI200318817. View this article via: JCI PubMed Google Scholar Holers, VM, Thurman, JM. The alternative pathway of complement in disease: opportunities for therapeutic targeting. Mol. Immunol. 2004. 41:147-152. View this article via: PubMed CrossRef Google Scholar Gigli, I, Sorvillo, J, Mecarelli-Halbwachs, L, Leibowitch, J. Mechanism of action of the C4 nephritic factor. Deregulation of the classical pathway of C3 convertase. J. Exp. Med. 1981. 154:1-12. View this article via: PubMed CrossRef Google Scholar Botto, M, et al. Homozygous C1q deficiency causes glomerulonephritis associated with multiple apoptotic bodies. Nat. Genet. 1998. 19:56-59. View this article via: PubMed CrossRef Google Scholar Bowness, P, et al. Hereditary C1q deficiency and systemic lupus erythematosus. Q. J. Med. 1994. 87:455-464. Mitchell, DA, et al. C1q deficiency and autoimmunity: the effects of genetic background on disease expression. J. Immunol. 2002. 168:2538-2543. View this article via: PubMed Google Scholar Mitchell, DA, et al. C1q protects against the development of glomerulonephritis independently of C3 activation. J. Immunol. 1999. 162:5676-5679. View this article via: PubMed Google Scholar Botto, M, Walport, MJ. C1q, autoimmunity and apoptosis. Immunobiology. 2002. 205:395-406. View this article via: PubMed CrossRef Google Scholar
|
|
Scooped by
Gilbert C FAURE
March 3, 2021 7:58 AM
|
Neutrophil extracellular traps (NETs) are a network of extracellular fibers, compounds of chromatin, neutrophil DNA and histones, which are covered with antimicrobial enzymes with granular components.
|
|
Scooped by
Gilbert C FAURE
December 27, 2020 2:47 PM
|
Objective Coagulopathy is one of the characteristics observed in critically ill patients with coronavirus disease 2019 (COVID‐19). Antiphospholipid antibodies (aPLs) contribute to coagulopathy, tho...
|
|
Scooped by
Gilbert C FAURE
November 18, 2020 1:19 PM
|
Antiphospholipid syndrome (APS), is an acquired autoimmune disorder characterised by thrombosis, pregnancy morbidity, and the presence of antiphospholipid antibodies (aPL). Although venous thromboembolism is the most common manifestation, thrombotic events in APS may also occur in virtually any...
|
|
Scooped by
Gilbert C FAURE
October 7, 2020 2:52 PM
|
To the Editor, Recently in the Journal of Thrombosis and Haemostasis, Harzallah and colleagues report the results of antiphospholipid antibody testing in a series of 56 patients with confirmed or suspected SARS‐CoV‐2 infection. 1 Twenty‐five patients were found to be positive for lupus anticoagulants, while five patients had either anticardiolipin or anti–β2‐glycoprotein 1 antibodies. The isotypes for the anticardiolipin and anti–β2‐glycoprotein 1 antibodies were reportedly IgG and IgM, although specific antibody titers and details of which were found in combination with a lupus anticoagulant in three overlap patients were not reported. The authors also reference published work by Zhang and colleagues, who reported three patients with SARS‐CoV‐2 infection, coagulopathy, thrombocytopenia, and the presence of anticardiolipin IgA and anti–β2‐glycoprotein 1 IgA and IgG antibodies who developed cerebral infarcts. 2 Harzallah and colleagues suggest the presence of these antibodies should be used as evidence for early anticoagulation of patients with COVID‐19. Antiphospholipid antibodies are common in the general population, especially during infection. 3 , 4 Whether the IgA isotype alone, noted by Zhang and colleagues, invokes thrombosis remains controversial, with only high titer IgG and IgM isotypes included as diagnostic criteria for the antiphospholipid syndrome. 5 Lack of IgG and/or IgM titers in these case series precludes any evaluation of their role in the thrombotic sequelae described. Thrombosis is common during critical illness and all patients in the Zhang series had preexisting cardiovascular disease, further increasing risk for arterial thrombosis. A key question remains whether COVID‐19 patients experience arterial thrombotic events at a higher rate compared to critically ill patients without SARS‐CoV‐2. The findings presented by Zhang and colleagues cannot confirm anticardiolipin antibodies as the causal agent for the arterial thrombosis observed in their series. False positive lupus anticoagulant testing might be expected in patients with COVID‐19 given the marked elevation in measured C‐reactive protein (CRP) levels seen in patients with significant pulmonary or systemic inflammation. Many assays to detect lupus anticoagulants are sensitive to the presence of CRP, resulting in false positive results, further limiting interpretation of this test in the acute inflammatory state. 6 COVID‐19 appears to induce a hypercoagulable state, with elevated fibrinogen, and minimal prolongation of prothrombin time and activated partial thromboplastin time, as seen in these patients. The exact mechanisms underlying the coagulopathy are unclear. 7 We urge clinicians who are evaluating coagulation parameters in patients with COVID‐19 to be cognizant of the pre‐analytic and analytic variables that affect the validity and interpretation of coagulation testing and to adhere to established anticoagulation protocols and guidelines until clinical studies demonstrating efficacy and safety of various anticoagulation strategies are published.
|
|
Scooped by
Gilbert C FAURE
August 27, 2020 7:41 AM
|
Antiphospholipid syndrome (APS) is a prothrombotic condition characterized by recurrent vascular thrombosis and/or pregnancy morbidity in the presence of circulating antiphospholipid antibodies. Central nervous system (CNS) involvement is a prominent ...
|
|
Scooped by
Gilbert C FAURE
May 5, 2020 12:04 PM
|
Antiphospholipid syndrome (APS) is a multisystem autoimmune condition characterized by vascular thromboses and/or pregnancy loss associated with persistently positive antiphospholipid antibodies (aPL).
|
|
|
Scooped by
Gilbert C FAURE
May 13, 3:29 AM
|
Antiphospholipid antibodies (aPL) are directed against phospholipids and phospholipid-binding proteins. Laboratory assays used to detect aPL include serological tests for aPL against β2-glycoprotein 1, cardiolipin and other molecules, as well as functional assays for lupus anticoagulant. The presence of aPL can lead to endothelial dysfunction or a hypercoagulable state through prothrombotic and antifibrinolytic mechanisms. These processes, often in conjunction with a ‘second hit’, such as trauma, surgery, or other causes of hypercoagulability or stasis, can lead to venous or arterial thrombosis. The thrombotic risk associated with aPL is best recognized in thrombotic antiphospholipid syndrome, characterized by a persistently positive test for lupus anticoagulant or seropositivity for aPL associated with venous, arterial or microvascular thrombosis. However, aPL seropositivity and its clinical effect on thrombotic events have been increasingly recognized in a broader group of individuals who do not meet traditional research criteria for thrombotic antiphospholipid syndrome. In this Review, we provide an overview of the evidence related to aPL seropositivity in individuals with or without previous thrombosis and the clinical relevance of aPL seropositivity in predicting the risk of thrombotic cardiovascular events. We discuss potential management strategies and identify key knowledge gaps that warrant further research. Antiphospholipid antibodies (aPL) are associated with an elevated risk of thromboembolic events in patients with antiphospholipid syndrome and, increasingly, in those without previous thrombosis. In this Review, Bikdeli and colleagues discuss the clinical relevance of aPL seropositivity in predicting the risk of thrombotic cardiovascular events, summarize potential management strategies and identify key knowledge gaps that warrant further research.
|
|
Scooped by
Gilbert C FAURE
November 29, 2025 10:05 AM
|
Interested in the Methodology of the 2023 ACR/EULAR Antiphospholipid Syndrome Classification Criteria?
The Publication Series is Below:
Phase I/II Report: Generation and Reduction of Candidate Criteria (2021) - https://lnkd.in/eM_cbsME
Phase III-A/B Report: Defining and Structuring the Clinical and Laboratory Domains (2025) - https://lnkd.in/euGN5uFd
Phase III-C Report: Assessment of Patient Scenarios (Derivation Cohort) and Refinement of Definitions (2025) - https://lnkd.in/ezt258mf
Phase III-D Report: Multicriteria Decision Analysis (2024) - https://lnkd.in/eabvQvmN
The 2023 ACR/EULAR Antiphospholipid Syndrome Classification Criteria (main paper, which includes the final criteria and phase IV validation report [2023]) - https://lnkd.in/eXnYY72D
Efforts to Better Characterize "Antiphospholipid Antibody Nephropathy" for the 2023 ACR/EULAR Antiphospholipid Syndrome Classification Criteria: Renal Pathology Subcommittee Report (2024) - https://lnkd.in/epbMZXvS
Medha Barbhaiya Stéphane ZUILY
Thank you to all the contributors.
|
|
Scooped by
Gilbert C FAURE
May 4, 2024 1:45 PM
|
Antiphospholipid syndrome (APS) consists of thrombotic, non-thrombotic and obstetric clinical manifestations developing in individuals with persistent antiphospholipid antibodies (aPL). Although researchers have made progress in characterizing different clinical phenotypes of aPL-positive people, the current approach to clinical management is still mostly based on a ‘one size fits all’ strategy, which is derived from the results of a limited number of prospective, controlled studies. With the 2023 publication of the ACR–EULAR APS classification criteria, it is now possible to rethink APS, to lay the groundwork for subphenotyping through novel pathophysiology-informed approaches, and to set a future APS research agenda guided by unmet needs in clinical management. In this Review, Knight and Erkan consider how the 2023 ACR–EULAR classification criteria for antiphospholipid syndrome (APS) can guide future research to subphenotype APS by understanding its pathophysiology, paving the way for the personalized and proactive management of individuals with APS.
|
|
Scooped by
Gilbert C FAURE
April 24, 2023 5:17 AM
|
Antiphospholipid syndrome is an autoimmune disorder characterized by vascular thrombosis and/or pregnancy morbidity associated with persistent antiphospholipid antibody positivity. Cases fulfilling the Sydney criteria for obstetric morbidity with no previous thrombosis are known as obstetric antiphospholipid syndrome (OAPS). OAPS is the most identified cause of recurrent pregnancy loss and late-pregnancy morbidity related to placental injury. Cases with incomplete clinical or laboratory data are classified as obstetric morbidity APS (OMAPS) and non-criteria OAPS (NC-OAPS), respectively. Inflammatory and thrombotic mechanisms are involved in the pathophysiology of OAPS. Trophoblasts, endothelium, platelets and innate immune cells are key cellular players. Complement activation plays a crucial pathogenic role. Secondary placental thrombosis appears by clot formation in response to tissue factor activation. New risk assessment tools could improve the prediction of obstetric complication recurrences or thromboses. The standard-of-care treatment consists of low-dose aspirin and prophylactic low molecular weight heparin. In refractory cases, the addition of hydroxychloroquine, low-dose prednisone or IVIG improve pregnancy outcomes. Statins and eculizumab are currently being tested for treating selected OAPS women. Finally, we revisited recent insights and concerns about the pathophysiology, diagnosis and management of OAPS.
|
|
Scooped by
Gilbert C FAURE
February 17, 2022 2:27 PM
|
Objective To describe the baseline characteristics of patients with positivity for antiphospholipid antibodies (aPLs) who were enrolled in an international registry, the Antiphospholipid Syndrome (...
|
|
Scooped by
Gilbert C FAURE
December 17, 2021 5:03 AM
|
Coronavirus disease 2019 (COVID-19) is associated with a high rate of thrombosis. Prolonged activated partial thromboplastin times (aPTT) and antiphospholipid antibodies (aPL) are reported i
|
|
Scooped by
Gilbert C FAURE
March 16, 2021 8:57 AM
|
Antiphospholipid syndrome (APS) is a hypercoagulation condition associated with the incidence of heterogenic antiphospholipid antibodies (aPLs), which non-specifically affect hemostasis processes. APS is clinically manifested by recurrent arterial and venous thromboses and reproduction losses.
|
|
Scooped by
Gilbert C FAURE
January 20, 2021 4:34 AM
|
Skin disorders associated with antiphospholipid syndrome...
|
|
Scooped by
Gilbert C FAURE
November 29, 2020 4:10 AM
|
Antiphospholipid syndrome (APS), an acquired autoimmune thrombophilia, is characterised by thrombosis and/or pregnancy morbidity in association with persistent antiphospholipid antibodies. The 16th International Congress on Antiphospholipid Antibodies ...
|
|
Scooped by
Gilbert C FAURE
November 14, 2020 1:38 PM
|
Antiphospholipid Syndrome Antiphospholipid syndrome (APS) is defined by the coexistence of obstetric morbidity (mainly pregnancy losses) and/or vascular thrombosis (venous or arterial) with the presence of aPL, namely lupus anticoagulant, anticardiolipin, or anti-β2-glycoprotein I antibodies. From: Handbook of Systemic Autoimmune Diseases, 2018 Related terms: View all Topics Antiphospholipid Syndrome Lucia R. Wolgast MD, in Transfusion Medicine and Hemostasis (Third Edition), 2019 Introduction The antiphospholipid (aPL) syndrome (APS) is an autoimmune thrombophilic condition that is defined by a combination of clinical and laboratory criteria. In general terms, APS patients have developed circulating antibodies against plasma proteins that bind to phospholipids (i.e., aPL antibodies) with subsequent clinical morbidity of thrombosis and/or pregnancy complications. The investigational criteria for APS (often referred to as the Sydney Investigational Criteria) are detailed in Table 108.1 and require that patients have documented evidence for vascular thrombosis and/or obstetric complications, such as unexplained recurrent miscarriages, intrauterine growth restriction, intrauterine fetal demise, preeclampsia/toxemia, placental abruption, and preterm labor. The laboratory criteria require identifying the persistent aPL antibodies (i.e., at least two abnormal measurements at least 12 weeks apart), including elevated medium to high tiers of anticardiolipin (aCL) IgG or IgM antibodies, anti-β2-glycoprotein I (anti-β2GPI) IgG or IgM antibodies, and/or positive lupus anticoagulant (LA). The laboratory diagnosis of APS is discussed in Chapter 158. Table 108.1. Sydney Investigational Criteria for the Diagnosis of the Antiphospholipid Syndromea Clinical • Vascular thrombosis (one or more episodes of arterial, venous, or small vessel thrombosis). For histopathologic diagnosis, there should be no evidence of inflammation in the vessel wall. • Pregnancy morbidities attributable to placental insufficiency, including (a) three or more otherwise unexplained recurrent spontaneous miscarriages, before 10 weeks of gestation, (b) one or more fetal losses after the 10th week of gestation, (c) stillbirth, and (d) episode of preeclampsia, preterm labor, placental abruption, intrauterine growth restriction, or oligohydramnios that are otherwise unexplained. Laboratory • Medium- or high-titer aCL or anti-β2GPI IgG and/or IgM antibody present on two or more occasions, at least 12 weeks apart, measured by standard ELISAs. • Lupus anticoagulant in plasma, on two or more occasions, at least 12 weeks apart, detected according to the guidelines of the ISTH SSC Subcommittee on Lupus Anticoagulants and Phospholipid-Dependent Antibodies. β2GPI, β2-glycoprotein I; aCL, anticardiolipin; aPL, antiphospholipid; ELISA, enzyme-linked immunosorbent assay; Ig, immunoglobulin. a “Definite APS” is considered to be present if at least one of the clinical criteria and one of the laboratory criteria are met. Modified from Miyakis, S., Lockshin, M. D., Atsumi, T., et al. (2006). International consensus statement on an update of the classification criteria for definite antiphospholipid syndrome (APS). J Thromb Haemost, 4, 295–306. It is important for the reader to understand that these criteria were not designed to be requirements for the clinical diagnosis of APS. Rather, they were intended to provide a uniformly rigorous definition of APS for the purpose of standardizing research on the disorder. In “real-world” clinical practice, some patients may be appropriately diagnosed for presumptive APS without meeting the strict investigational criteria. Some APS patients may be positive for other “noncriteria” clinical laboratory tests—see Chapter 158—that have not been included by consensus panels as diagnostic criteria for the disorder, but these positive noncriteria laboratory tests may indicate a clinical risk and warrant treatment. Furthermore, APS patients may have positive APS criteria assays but not the typical criteria manifestations. These “noncriteria manifestations” include thrombocytopenia, livedo reticularis, skin ulcers, nephropathy, migraine, cognitive defects, diffuse alveolar hemorrhage, and valvular heart disease (Libman–Sacks endocarditis), and these clinical manifestations may need to be managed differently. Occasional patients may even test entirely negative for the APS criteria assays but have typical clinical manifestations of the disorder—a situation referred to as seronegative APS (termed SNAPS). At present, APS may be divided into the following subcategories: (1) Primary APS is the “stand alone” disorder, in the absence of systemic lupus erythematosus (SLE), (2) secondary APS occurs in the presence of APS, (3) catastrophic APS (CAPS) manifests as disseminated thrombosis in large and small vessels with resulting multiorgan failure (Table 108.2), and (4) SNAPS includes patients whose diagnostic tests are entirely negative but who, on clinical grounds, are still suspected to have the disorder. Table 108.2. Proposed Criteria for the Classification of Catastrophic Antiphospholipid Syndrome (APS) 1. Evidence of involvement of three or more organs, systems, and/or tissuesa 2. Development of manifestations simultaneously or in less than a week 3. Confirmation by histopathology of small vessel occlusion in at least one organ or tissueb 4. Laboratory confirmation of the presence of antiphospholipid antibodies (lupus anticoagulant and/or anticardiolipin antibodies)c Definite Catastrophic APS • All four criteria Probable Catastrophic APS • All four criteria, except for only two organs, systems and/or tissues involvement • All four criteria, except for the absence of laboratory confirmation at least 6 weeks apart due to the early death of a patient never previously tested for aPL before the catastrophic APS event • Criteria 1, 2, and 4 • Criteria 1, 3, and 4 and the development of a third event in more than a week but less than a month, despite anticoagulation a Usually, clinical evidence of vessel occlusions, confirmed by imaging techniques when appropriate. Renal involvement is defined by a 50% rise in serum creatinine, severe systemic hypertension (N180/100 mm Hg), and/or proteinuria (N500 mg/24 hours). b For histopathological confirmation, significant evidence of thrombosis must be present, although, in contrast to Sydney criteria, vasculitis may coexist occasionally. c If the patient had not been previously diagnosed as having an APS, the laboratory confirmation requires that the presence of antiphospholipid antibodies must be detected on two or more occasions at least 6 weeks apart (not necessarily at the time of the event), according to the proposed preliminary criteria for the classification of definite APS. Modified from Asherson, R. A., Cevera, R., de Groot, P. G., et al. (2003). Catastrophic antiphospholipid syndrome: international consensus statement on classification criteria and treatment guidelines. Lupus, 12, 530–534. Antiphospholipid Syndrome Nancy Agmon-Levin, ... Yehuda Shoenfeld, in The Autoimmune Diseases (Fifth Edition), 2014 The antiphospholipid syndrome (APS) is an autoimmune disorder characterized by thrombosis, pregnancy losses, and the presence of at least one of three antiphospholipid antibodies. However, it has been acknowledged that the clinical spectrum of APS is much wider, including systemic and organ-specific manifestations. Moreover, the presence of more than 20 antiphospholipid antibodies has been recognized, some of which may participate in the pathogenesis of APS although not included as criteria. Our knowledge and understanding of the etio-pathogenesis of APS has increased tremendously, as the effects of antiphospholipid antibodies, mainly the anti-B2GPI–B2GPI immune complexes, were elucidated. The latter bind to different cells (i.e., monocytes, endothelial cells, and trophoblasts), recruit cell surface receptors, and subsequently induce intracellular signaling. Additionally an arsenal of environmental factors as infectious agents and vitamin D has been associated with the presence of antiphospholipid antibodies and overt APS. It seems therefore that in APS both thrombotic and immune-mediated mechanisms play a part and may be considered as candidates for targeted therapeutic interventions. Antiphospholipid Syndrome ROBERT A.S. ROUBEY, in The Autoimmune Diseases (Fourth Edition), 2006 Publisher Summary The antiphospholipid syndrome (APS) is the association of autoantibodies having an apparent specificity for anionic phospholipids with one or more clinical manifestations that include venous and arterial thrombosis and pregnancy loss and morbidity. APS is an under-recognized autoimmune disease that accounts for a significant proportion of thromboembolic disease and recurrent pregnancy loss. Animal models of APS are important tools for investigating the cellular basis of the autoimmune response, the contribution of genetic factors, and mechanisms by which antiphospholipid antibodies (aPL) contribute to thrombosis and pregnancy loss Anticoagulation rather than immunosuppression is the current mainstay of therapy. Although effective in most cases, full anticoagulation carries a significant risk of adverse side effects. Future research characterizing the underlying autoimmune response, the spectrum of APS autoantibodies, and the relevant mechanisms of hypercoagulability will lead to the identification of novel therapeutic targets and approaches. These new approaches raise hope for safer and more effective treatment of APS. Antiphospholipid syndrome Munther A. Khamashta, Mary-Carmen Amigo, in Rheumatology (Sixth Edition), 2015 Antiphospholipid syndrome: definition and history Antiphospholipid syndrome (APS) is an autoimmune multisystemic disorder characterized by recurrent arterial and venous thrombosis and/or pregnancy morbidity associated with the presence of persistent antiphospholipid antibodies (aPLs). aPLs are a heterogeneous group of antibodies directed against anionic phospholipids or protein-phospholipid complexes. Laboratory tests to identify aPL includes solid-phase immunoassays (enzyme-linked immunosorbent assay [ELISA]) to detect anticardiolipin (aCL) and anti–β2-glycoprotein I (anti-β2-GPI) antibodies and functional assays to detect the so-called lupus anticoagulants (LACs) that demonstrate the ability of aPL to prolong phospholipid-dependent clotting reactions.1 The term lupus anticoagulant is a misnomer. The LAC phenomenon results in prolonged plasma clotting times; however, patients with LAC are subject to thrombosis, not to hemorrhage, except in uncommon cases such as in hypoprothrombinemia-LAC syndrome. Although initially described in patients with systemic lupus erythematosus (SLE), APS was soon recognized also to occur in patients without underlying autoimmune disease. APS was then classified as “secondary” in the presence of SLE and “primary” in the absence of SLE or other autoimmune disorders. Primary APS is the most common cause of acquired thrombophilia and accounts for 15% to 20% of all episodes of deep vein thrombosis with or without pulmonary embolism, one third of new strokes occurring in patients younger than age 50, and 10% to 15% of women with recurrent fetal loss.2 APS also accounts for a significant proportion of thromboembolic disease and recurrent fetal loss in patients with SLE. aPLs are present in 30% to 40% of SLE patients, and 10% to 15% of all SLE patients have clinical manifestations of APS.3 It is now generally accepted that aPLs are the most frequent acquired risk factor for a treatable cause of recurrent pregnancy loss and for pregnancy complications. In 1999, an international consensus meeting formulated the first classification criteria (known as the Sapporo criteria) for patients with APS.4 In 2006, these criteria were updated1 (Box 139.1). Antiphospholipid Syndrome Tadej Avčin, Kathleen M. O'Neil, in Textbook of Pediatric Rheumatology (Seventh Edition), 2016 Other Manifestations Cardiac manifestations are frequent in adult patients with APS but have not been extensively investigated in childhood. The most prominent cardiac manifestations include valvular disease, occlusive coronary artery disease, cardiomyopathy, and intracardiac thrombosis.22,248 Nonbacterial (Libman–Sacks) vegetations were disclosed by echocardiographic studies in 11% of adult patients with APS,22 but were only rarely observed in patients with pediatric APS.29,249 Several cases of pediatric patients with aPL-related myocardial infarction have been reported, often in association with underlying SLE or congenital heart disease.32,250-253 Multiple small vascular occlusions are responsible for APS cardiomyopathy, especially in CAPS, in which it is one of the most common causes of death.254,255 Pulmonary embolism and infarction constitute the most frequent pulmonary manifestation of APS.45,182,256-258 aPLs were reported in 30% to 40% of children with pulmonary embolism who were referred for hematology evaluation.256,258 Rarely, recurrent pulmonary embolism may lead to pulmonary hypertension.196,259,260 The kidney is a major target organ of pediatric APS with manifestations that include renal vascular occlusion, thrombotic glomerular microangiopathy, and hypertension.46,261-265 The term antiphospholipid syndrome-associated nephropathy (APSN) was proposed to describe thrombotic microangiopathy involving both arterioles and glomerular capillaries that cause hypertension, acute renal failure, proteinuria, and poor renal function with a tendency to develop end-stage renal disease.2,266-268 This entity was reported in 16% of Thai patients with childhood-onset SLE who underwent renal biopsy and was significantly more frequent in adult SLE patients (41%).268 aPLs are also associated with hepatic, digestive, and adrenal manifestations resulting from occlusive vascular disease of intraabdominal vessels.269-272 Osteoarticular manifestations such as avascular necrosis of bone, nontraumatic fractures, and bone marrow necrosis are rarely seen in APS patients.273,274 Adult patients with primary APS and no prior glucocorticoid treatment appear to have an increased risk of avascular necrosis.275 aPLs were reported as one of the most common prothrombotic alterations in patients with multifocal osteonecrosis, which is present in 20% of cases.276 Perthes disease has been linked with aPLs in two pediatric studies,274,277 but the association does not appear to be strong. Antiphospholipid Syndrome Tatsuya Atsumi, ... Takao Koike, in Systemic Lupus Erythematosus (Fifth Edition), 2011 Antiphospholipid antibodies (aPLs) include a heterogeneous group of circulating immunoglobulins present in a wide range of infectious and autoimmune diseases. In particular, anticardiolipin antibodies (aCL) and lupus anticoagulants (LA) are associated with the antiphospholipid syndrome (APS). APS is recognized as a condition that is a frequent cause of acquired thrombophilia. They react with a complex of phospholipid and plasma proteins, including β2GPI, prothrombin, annexin V, high- and low-molecular-weight kininogen, protein S, and protein C, previously known as “cofactors.” Because of their strong relationship with clinical symptoms, aPLs have been considered pathogenic antibodies. It is recognized that the inhibition of the natural anticoagulant systems, the impairment of fibrinolytic activity, and the direct effect of aPLs on cell functions are some of the mechanisms of aPL-mediated thrombosis. Studies on the pathogenicity of aPLs have been carried out mainly on the corresponding antigens, especially on the function of β2GPI and their modifications by the antibodies. Evidence suggests that complement activation is also required for aPL-mediated tissue injury, and findings have revealed that aPLs play a role in the T-cell responses. Pathogenesis of Antiphospholipid Antibody Syndrome Ian Giles, ... Yiannis Ioannou, in Dubois' Lupus Erythematosus and Related Syndromes (Ninth Edition), 2019 Clinical Importance of the Antiphospholipid Syndrome in Patients With SLE APS has a wide range of clinical manifestations.5 Initially, APS was identified in patients with SLE, in whom a positive test for either aPLs occurred in the presence of thrombosis or pregnancy morbidity. The existence, however, of primary APS (PAPS) in patients lacking another autoimmune rheumatic disease (ARD) was identified in ~50% of APS patients. The original description of the remaining cases as secondary APS, occurring in the presence of another ARD, most commonly SLE, has now been dropped because the clinical and serologic features of APS are similar in both groups. In this regard, the 2006 APS classification criteria recommended that any associated disorder should be reported, such as SLE-associated APS.4 A catastrophic variant occurs in less than 1% of patients with APS who develop multiple (often small vessel) thromboses resulting in multiorgan failure, and 40% of these patients have SLE.6 Antiphospholipid Syndrome Wendy Lim MD, MSc, in Transfusion Medicine and Hemostasis (Second Edition), 2013 Future Directions APS is a complex disorder with evolving diagnostic criteria. Insight into the pathophysiology of APS may lead to novel treatments for APS, which to date have focused on antithrombotic therapy. Complement activation may play an important role in fetal loss, and although there is currently no specific complement-targeted therapy approved for patients with APS, complement inhibition may prove to be a novel upstream treatment for APS. Other investigational treatments include the use of rituximab, other immunosuppressive agents and autologous stem cell transplantation, all of which require further study. Management of patients with aPL and APS can be challenging, as many patients with APS have risk factors for bleeding and have a high risk of recurrent thromboembolism. The clinical trials and observational studies performed to date have yielded valuable information on the management of patients with APS, but further research is required to address the ongoing controversies that exist in the management of these patients. The Clinical Evaluation of Kidney Disease in Systemic Lupus Erythematosus Brad H. Rovin, Isabelle Ayoub, in Systemic Lupus Erythematosus, 2016 Antiphospholipid Syndrome and the Kidney APS (Chapters 56–58Chapter 56Chapter 57Chapter 58) can result in kidney injury by causing noninflammatory occlusions of renal blood vessels, including the intrarenal microvasculature. APS is seen in about 30% of patients with SLE, often (but not always) accompanied by LN and antiphospholipid antibodies such as anticardiolipin and anti-β2-glycoprotein I antibodies, or lupus anticoagulants.41 It is important to consider the diagnosis of renal APS and verify with a kidney biopsy, because the usual immunosuppression used for LN does not treat renal APS, which requires anticoagulation. Failure to treat APS can lead to CKD or ESRD. Antiphospholipid Syndrome in Systemic Autoimmune Diseases Roger A. Levy, ... Ricard Cervera, in Handbook of Systemic Autoimmune Diseases, 2017 1.1 Introduction Antiphospholipid syndrome (APS) is defined by the occurrence of venous and arterial thromboses (often multiple) and pregnancy morbidity (abortions, foetal deaths, premature births), in the presence of antiphospholipid antibodies (aPL); namely, lupus anticoagulant (LA), anticardiolipin antibodies (aCL), or anti-β2 glycoprotein-I (anti-β2GPI) antibodies. APS can occur in patients having neither clinical nor laboratory evidence of another definable condition (primary or isolated APS), or it may be associated with other diseases, mainly systemic lupus erythematosus (SLE), and occasionally with other autoimmune conditions, infections, drugs, and malignancies. Rapid chronological occlusive events, occurring over days to weeks, have been termed as catastrophic APS (CAPS). Other postulated APS subsets include microangiopathic APS (MAPS) and seronegative APS.
|
|
Scooped by
Gilbert C FAURE
September 18, 2020 2:49 PM
|
Clarity and guidance is required with regard to the use of direct oral anticoagulants in antiphospholipid syndrome (APS) patients, within the confines of the recent European Medicines Agenc
|
|
Scooped by
Gilbert C FAURE
May 15, 2020 2:59 PM
|
Abstract Background The laboratory detection of lupus anticoagulants (LA) in anticoagulated patients represents a challenge and there is no consensus on the types of assays/procedures to be adopted...
|