Your new post is loading...

|
Scooped by
Gilbert C FAURE
Today, 12:46 PM
|
Allergy care has changed.
And in many ways, that is a good thing.
The old approach often looked like this:
↳ Avoid more and more things
↳ Blame every symptom on a positive test
↳ Wait until symptoms get bad
↳ Treat everyone the same
↳ Reach for short-term relief again and again
↳ Make a plan only after a reaction happens
That is not the direction we want to keep going.
Better allergy care is more precise.
It starts with the right question:
What is actually going on here?
Because sneezing, wheezing, eczema, hives, and food reactions are not all the same problem.
And they should not all be treated the same way.
The newer approach is more thoughtful:
1️⃣ Targeted avoidance
Avoid only confirmed triggers, not everything “just in case.”
2️⃣ History plus testing
A test alone does not diagnose allergy. Test results need context.
3️⃣ Earlier control of inflammation
For asthma, rhinitis, and eczema, the goal is not just to chase flares. It is to control disease earlier.
4️⃣ Personalized care
Rhinitis, asthma, eczema, food allergy, and hives each need their own strategy.
5️⃣ Long-term tools when needed
Sprays, inhalers, skin care, allergy shots, biologics, and food allergy planning all have a role in the right patient.
6️⃣ Prevention and action plans
Education matters. Follow-up matters. Knowing what to do in a reaction matters.
7️⃣ Early food introduction for babies
One of the biggest shifts has been infant feeding.
The old idea was to delay common allergenic foods like peanut and egg.
Now we know that, when babies are developmentally ready, early introduction of common allergenic foods can help lower food allergy risk, especially in the right setting and with the right guidance.
So the “new way” is not doing more for the sake of doing more.
It is doing the right thing, for the right condition, at the right time.
That means less fear.
Less guesswork.
And better care.
What change in allergy care do you think patients or even clinicians still misunderstand the most?
|
|
Scooped by
Gilbert C FAURE
June 19, 12:28 PM
|
New episode on JAK inhibitors for eczema 🎧
What is the difference between a JAK inhibitor cream and a pill?
Topical JAK inhibitors work mainly where they are applied, with much less systemic exposure.
Oral JAK inhibitors work throughout the body, which is why patient selection, monitoring, and lab checks matter.
In this episode, host Payel Gupta, MD, FACAAI speaks with Nicole Chase, MD about how JAK inhibitors work, who may benefit, and how to use them safely.
I created this infographic to help make the current options easier to understand.
Thank you to The ITCH Podcast for the shoutout and for including my infographic in the episode notes, and to Allergy & Asthma Network for helping bring this patient education forward.
Listen here: https://lnkd.in/g8yzBtEb
|
|
Scooped by
Gilbert C FAURE
May 17, 4:16 AM
|
Allergy clinic looks simple.
It rarely is.
What people see
↳ Skin testing
↳ Patch testing
↳ Food challenges
↳ Allergy shots
↳ Biologics
What they do not see
↳ Sorting out whether a reaction was IgE-mediated, delayed, irritant, infectious, mast cell-related, bradykinin-mediated, or not allergy at all
↳ Explaining why a positive test does not always mean clinical allergy
↳ Rebuilding trust after broad food panels turn tolerated foods into sources of anxiety
↳ Reviewing ingredient lists, cofactors, timing, and symptom patterns in detail
↳ Figuring out whether “sinus allergy” is allergic rhinitis, vasomotor rhinitis, reflux, chronic sinus disease, or something else
↳ Deciding when hives are spontaneous urticaria and when swelling may be hereditary angioedema, ACE inhibitor angioedema, or another non-histamine process
↳ Recognizing when the story fits alpha-gal, especially when reactions are delayed and the timing feels “off”
↳ Working through drug allergy labels that have followed patients for years
↳ Sorting eczema from allergic contact dermatitis, then using patch testing when the story fits
↳ Explaining why flushing is not always allergy, swelling is not always angioedema, and eczema is not always food driven
↳ Figuring out whether “uncontrolled asthma” is persistent airway inflammation, poor inhaler technique, adherence issues, rhinitis, reflux, vocal cord dysfunction, or the wrong diagnosis altogether
↳ Working up recurrent sinus, lung, or skin infections and asking whether the problem is allergy, immune deficiency, or both
↳ Evaluating for antibody deficiency or other immune problems when the infection history does not add up
↳ Prior authorizations, school forms, biologic renewals, and portal messages in between visits
↳ Helping patients unlearn years of misinformation from social media, panel testing, and vague “sensitivity” reports
That is the part people miss.
A good allergy visit is not just about finding a trigger.
It is about asking better questions.
It is about narrowing a differential.
It is about knowing when the answer is allergy, and when it is not.
A big part of this specialty is not diagnosing more allergy.
It is ruling it out correctly.
And honestly, that is where a lot of the value lives.
Because the right diagnosis does two things:
↳ It finds what truly needs treatment
↳ It frees patients from avoiding things they were never actually allergic to
That can mean fewer false labels.
Less fear.
Less unnecessary restriction.
And better care.
Allergy-immunology sits at a strange intersection of detective work, pattern recognition, patient education, skin disease, airway disease, swelling disorders, immune evaluation, and long-term management.
It looks lighter from the outside than it really is.
Clinical allergists know otherwise.
What do you think is the most misunderstood part of allergy practice? | 14 comments on LinkedIn
|
|
Scooped by
Gilbert C FAURE
February 2, 3:28 AM
|
What Your IgG Test Results Mean (and Don’t Mean)
TL;DR: IgG sensitivity tests can’t tell you what foods you're sensitive to.
IgG sensitivity tests claim to work by measuring levels of IgG antibodies in your blood against specific foods. Some test up to 100 foods, and the idea is that if your body makes a lot of IgG to a certain food, it means your immune system sees that food as a “problem.” Companies that make these tests say this immune response may be linked to symptoms like bloating, fatigue, headaches, or skin issues. Based on the results, they recommend avoiding foods that show high IgG levels.
However, these tests measuring IgG antibodies, aren't scientifically proven. Experts, including the American Academy of Allergy, Asthma, and Immunology (AAAAI), say IgG antibodies actually show normal exposure and tolerance to a food. Meaning that your body tolerates those foods, not that you're sensitive to them!
These tests are expensive and can lead to unnecessary food restrictions and can cause anxiety, nutrient deficiencies, and a bad relationship with food.
✅ An elimination diet, done with a healthcare professional, is still the best way to pinpoint food sensitivities. It takes time, but it’s the most trusted method!
https://lnkd.in/dBhYfZf2
https://lnkd.in/dYJ47Wjh
#Debunked #FoodSensitivity #GutHealth #EliminationDiet
|
|
Scooped by
Gilbert C FAURE
November 12, 2025 5:08 AM
|
Very proud to present our November issue. Drug #hypersensitivity reactions (DHRs) constitute a major concern in clinical practice, as they compromise patient safety and restrict the use of essential medications. These immune-mediated adverse drug reactions occur after exposure to therapeutic doses and can manifest with a broad clinical spectrum, ranging from mild cutaneous reactions to severe, potentially fatal conditions.
This issue opens with an editorial by Li et al., highlighting the inaugural EAACI Hong Kong Allergy School where global experts in drug allergy gathered under the theme “East Meets West” to call for harmonized international definitions of drug hypersensitivity and standardized criteria for identifying low-risk penicillin allergy, underscoring the urgent need to reduce mislabelling and advance safe, evidence-based delabelling practices worldwide. Leonardi et al. provide a comprehensive overview of the clinical presentations, diagnostic approaches, and treatment strategies for drug-induced ocular adverse events. Cortellini et al. present data and recommendations on the characteristics of hypersensitivity reactions to antiplatelet drugs and the associated diagnostic procedures, to maximize their safety and effectiveness. Gelincik et al. review current knowledge on the pathomechanisms of hypersensitivity reactions to quinolones, including diagnostic tests and cross-reactivities, and propose a practical diagnostic approach for clinicians. Hutten et al. highlight significant discrepancies between studies on cross-allergy to beta-lactam antibiotics, particularly concerning recommendations for safe alternatives. Labella et al. investigate the utility of direct single-dose drug provocation testing without prior skin testing in adult European patients at low risk of penicillin allergy. Bilgic-Eltan et al. analyze the discrepancies between suspected and confirmed drug hypersensitivity in a well-defined cohort of patients with inborn errors of immunity. Helevä et al. evaluate the benefits of aspirin treatment after desensitization in patients with chronic rhinosinusitis with nasal polyps, asthma, and N-ERD. Goh et al. explore haptenated ligands presented by HLA-A*02:01, characterize the T cell repertoire involved in penicillin-induced reactions in a hypersensitive patient, and investigate whether a dominant penicillin-specific T cell receptor clonotype recognizes haptenated HLA peptides. Bertolotti et al. present the thoroughly documented case of a patient with delayed cross-reactivity to all seven available iodinated contrast media. Cho, Jo, and Park et al. leverage the WHO global pharmacovigilance database to identify the ten drugs most frequently associated with severe cutaneous adverse reactions, providing large-scale epidemiological insights into delayed drug hypersensitivities and contributing to global drug safety. Céspedes and Pérez-Moreno et al. demonstrate that IgG removal enhances…………..
journalallergy.com
|
|
Scooped by
Gilbert C FAURE
July 30, 2025 4:30 AM
|
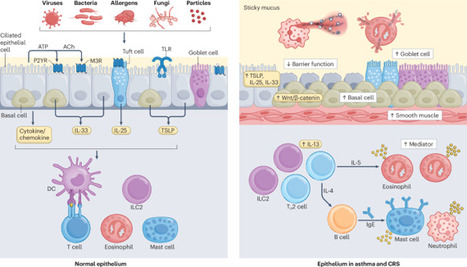
Asthma and chronic rhinosinusitis (CRS) are common chronic inflammatory diseases of the respiratory tract that have increased in prevalence over the past five decades. The clinical relationship between asthma and CRS has been well recognized, suggesting a common pathogenesis between these diseases. Both diseases are driven by complex airway epithelial cell and immune cell interactions that occur in response to environmental triggers such as allergens, microorganisms and irritants. Advances, including a growing understanding of the biology of the cells involved in the disease, the application of multiomics technologies and the performance of large-scale clinical studies, have led to a better understanding of the pathophysiology and heterogeneity of asthma and CRS. This research has promoted the concept that these diseases consist of several endotypes, in which airway epithelial cells, innate lymphoid cells, T cells, B cells, granulocytes and their mediators are distinctly involved in the immunopathology. Identification of the disease heterogeneity and immunological markers has also greatly improved the protocols for biologic therapies and the clinical outcomes in certain subsets of patients. However, many clinical and research questions remain. In this Review, we discuss recent advances in characterizing the immunological mechanisms of asthma and CRS, with a focus on the main cell types and molecules involved in these diseases. In this Review, Kato and Kita discuss the complex interactions between airway epithelial cells and immune cells that contribute to the development of asthma and chronic rhinosinusitis. They highlight recent advances in understanding the clinical heterogeneity of these diseases and explain the progress that has been made in developing new therapies.

|
Suggested by
LIGHTING
February 17, 2025 6:19 AM
|
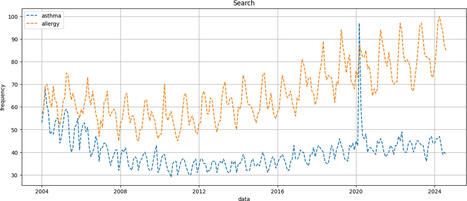
Background Google Trends (GT) is a free tool that provides insights into the public’s interest and information-seeking behavior on specific topics. In this study, we utilized GT data on patients’ search history to better understand their questions and information needs regarding asthma.
|
|
Scooped by
Gilbert C FAURE
December 3, 2024 4:27 AM
|
An injection given during some asthma and COPD attacks is more effective than the current treatment of steroid tablets, reducing the need for further treatment
|
|
Scooped by
Gilbert C FAURE
October 6, 2024 4:42 AM
|
"A blog about allergy, asthma & immunology"
|
|
Scooped by
Gilbert C FAURE
April 5, 2024 7:29 AM
|
|
|
Scooped by
Gilbert C FAURE
January 20, 2024 4:59 AM
|
|
|
Scooped by
Gilbert C FAURE
January 10, 2024 3:00 AM
|
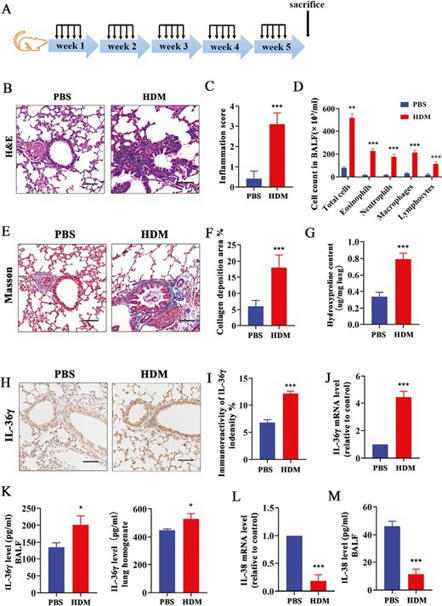
IL-36γ was upregulated in the lungs of chronic asthma mice, and it contributed to the airway remodeling. IL-38 can alleviate the airway remodeling in asthma by
|
|
Scooped by
Gilbert C FAURE
December 29, 2023 3:53 AM
|
|
|
|
Rescooped by
Gilbert C FAURE
from Mucosal Immunity
September 12, 11:11 AM
|
Airway epithelial cells as drivers of severe #asthma pathogenesis in this review from Bart Lambrecht, Gianni Marone and colleagues: https://lnkd.in/g9tZSgSV
|
|
Scooped by
Gilbert C FAURE
May 17, 4:54 AM
|
Allergy-Immunology is moving past diagnosis-first treatment.
The question now is which pathway fits.
What started with anti-IgE has expanded into a much broader therapeutic era:
anti-IL-5, anti-IL-4Rα, anti-TSLP, anti-IL-13, anti-IL-31RA, BTK inhibition, kallikrein pathway targeting, FXIIa inhibition, and RNA-targeted therapy.
This timeline shows how quickly the field has evolved.
A few things stand out:
🔹 Asthma helped lead the way
From Xolair to anti-IL-5 therapies to Tezspire, asthma has been one of the major drivers of targeted treatment development in our field.
🔹 Type 2 disease is not just one disease
The same inflammatory pathways show up across asthma, atopic dermatitis, CRSwNP, eosinophilic disease, and more, but not in identical ways.
🔹 Hereditary angioedema is a great example of precision medicine
HAE management has expanded well beyond older paradigms, with both prophylactic and on-demand targeted therapies now available.
🔹 We are moving beyond monoclonal antibodies alone
This is no longer just a biologics story.
It is also a story of oral targeted therapy, pathway-specific inhibition, and RNA-directed treatment.
🔹 Mechanism matters more than ever
As options grow, choosing therapy becomes less about “what is available” and more about:
↳ phenotype
↳ endotype
↳ comorbid disease
↳ age/indication
↳ convenience
↳ access and coverage
For trainees, this timeline is a reminder of how fast the field is moving.
For clinicians, it is a reminder of how much treatment selection has changed in just two decades.
And honestly, we are probably still early.
Which approval do you think most changed practice in Allergy-Immunology?
|
|
Scooped by
Gilbert C FAURE
April 13, 9:52 AM
|
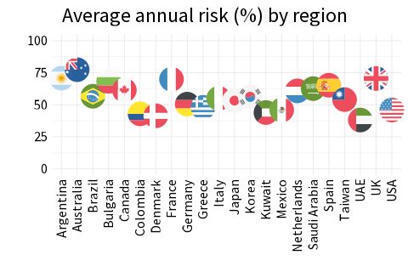
📢 Happy to share our latest paper on RESA, a risk prediction tool for asthma attacks (exacerbations) in severe asthma, developed using data from 27 regions across the planet.
Led by Dr. Wenjia Chen, RESA is a modular model with a core and optional set of predictors, predicting the risk of any or frequent attacks. This is a highly relevant outcome, as we strive for more efficient management of this important subgroup of asthma.
★ The more we tried, the clearer it became that a universally applicable model without local adjustment may not be realistic. The team concluded that the most responsible approach is to treat background exacerbation risk as an input parameter.
This reflects the nature of asthma attacks, a biological event, but also shaped by subjective symptom perception, standards of care, and environmental factors.
This real-world heterogeneity remains hidden until we try to quantify the risk, and is difficult to identify in the harmonized world of trials.
This work would not have been possible without the sustained efforts behind large-scale initiatives like ISAR and NOVELTY.
👉 Open access paper in American Academy of Allergy, Asthma & Immunology - AAAAI journal: https://lnkd.in/gMd7FepJ
👉 Web app (RESAScore.com): https://www.resascore.com/
International collaboration: The University of British Columbia | Collaboration for Outcomes Research and Evaluation (CORE) | National University of Singapore | Observational & Pragmatic Research Institute | AstraZeneca | Respiratory Evaluation Sciences Program
|
|
Scooped by
Gilbert C FAURE
December 28, 2025 5:34 AM
|
Bronchiectasis and asthma can co-exist in the same patient, and the characteristics may be different from bronchiectasis alone. Here the authors characterise the function of ILC3 cells and how IL-17C potentiates IL-17A expression promoting a neutrophil dominated asthma endotype in mouse...
|
|
Scooped by
Gilbert C FAURE
August 7, 2025 3:35 AM
|
"A blog about allergy, asthma & immunology"
|
|
Scooped by
Gilbert C FAURE
May 24, 2025 2:13 AM
|
📢 One of the most appreciated/liked articles in the social media of Allergy published in 2024:
Open Access: Navigating the evolving landscape of atopic dermatitis: Challenges and future opportunities: The 4th Davos declaration. Claudia Traidl-Hoffmann
Read the article here: doi.org/10.1111/all.16247
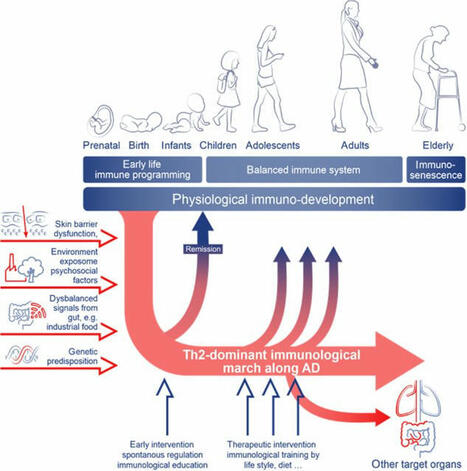
With over 170 references and 6 figures, this article summarizes the key points discussed during the Global Allergy Forum in Davos. During this event, scientific experts and stakeholders met to address the increasing prevalence of #atopicdermatitis (AD). Topics covered include: #epithelialbarrier maintenance and disturbances in atopic diseases; #environmental changes as a driving force of atopic diseases; immunological march along the course of AD; neuroimmunology, systemic inflammation and comorbidities; therapeutic, educational, and global economic aspects; future directions
Read more articles published in #Allergy on #asthma here: https://lnkd.in/dvHaYziZ
#Allergy_journal
|
|
Scooped by
Gilbert C FAURE
January 19, 2025 10:43 AM
|
|
|
Scooped by
Gilbert C FAURE
November 30, 2024 1:45 PM
|
|
|
Scooped by
Gilbert C FAURE
April 18, 2024 6:08 AM
|
The inflammation process plays a crucial role in allergic respiratory diseases, such as asthma and allergic rhinitis. Although the pulmonary epithelium, the carpet of cells that forms the inner surface of the lungs, is recognized as a major player in the respiratory inflammation that causes these diseases, the underlying mechanisms are still poorly understood.
|
|
Scooped by
Gilbert C FAURE
February 11, 2024 6:41 AM
|
An overactive population of natural killer cells in children with eczema may worsen skin damage and provoke allergic sensitivity or development of asthma.
|
|
Scooped by
Gilbert C FAURE
January 16, 2024 1:13 PM
|
|
|
Scooped by
Gilbert C FAURE
January 5, 2024 1:16 PM
|
"A blog about allergy, asthma & immunology"
|