Your new post is loading...

|
Scooped by
Gilbert C FAURE
October 12, 4:07 AM
|
Your child tested positive for a food allergy.
But does that mean they are actually allergic?
Not necessarily.
This is one of the most common misunderstandings I see in my allergy clinic.
A positive skin prick test or blood IgE test does not automatically mean someone has a food allergy.
It means their immune system has made IgE antibodies that recognize the food.
But whether eating that food will cause a reaction is a different question.
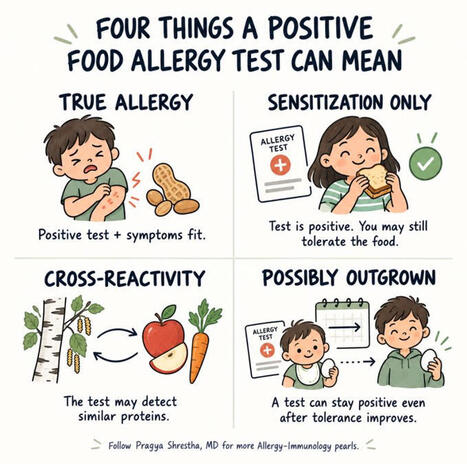
Here are 4 things a positive food allergy test can mean:
1️⃣ TRUE FOOD ALLERGY
The test is positive AND the clinical history supports an allergic reaction.
For example:
A child develops hives, vomiting, or wheezing shortly after eating peanuts, and peanut testing is positive.
The history and test results fit together.
2️⃣ SENSITIZATION WITHOUT ALLERGY
This is where confusion often begins.
A child may test positive to milk, egg, or peanut but eat that food regularly without any symptoms.
That is called sensitization.
And sensitization does not always mean allergy.
👉 If someone regularly eats a food without problems, a positive test alone is generally not a reason to remove it from their diet.
3️⃣ CROSS-REACTIVITY
Sometimes, the immune system recognizes proteins that look similar.
For example:
Someone with birch pollen allergy may test positive to apple or carrot because these foods contain proteins similar to birch pollen.
Some people develop itching in the mouth when eating these foods, called pollen-food allergy syndrome.
Others may have positive tests without symptoms.
A positive result does not always mean a dangerous food allergy.
4️⃣ AN ALLERGY THAT MAY HAVE BEEN OUTGROWN
This is particularly important in children.
Some children outgrow milk, egg, wheat, or other food allergies over time.
But their allergy tests may remain positive even after they develop tolerance.
That is why we look at:
↳ Previous reactions
↳ Changes in skin test or specific IgE results over time
↳ Whether a supervised oral food challenge is appropriate
An oral food challenge, performed under medical supervision, is the gold standard for confirming whether someone can tolerate a food when the diagnosis remains uncertain.
Here is what I wish more parents knew:
A positive test does not tell us the whole story.
And a larger skin test or higher IgE level does not reliably predict how severe a future reaction will be.
Testing should be guided by the clinical history, not used as a broad screening tool without a clear reason.
Unnecessary food avoidance can affect nutrition, quality of life, and create significant anxiety for families.
Before eliminating a food based only on a test result, discuss it with an allergist.
If there is a history of a possible allergic reaction, do not try reintroducing the food at home without appropriate guidance.
We treat patients, not just positive test results.
Have you or your child ever been told to avoid a food based only on a positive allergy test?
|
|
Scooped by
Gilbert C FAURE
September 15, 4:03 AM
|
|
|
Scooped by
Gilbert C FAURE
August 13, 4:38 AM
|
Positive alpha-gal test. No reaction to red meat.
Should you stop eating it?
I am seeing more patients with positive alpha-gal testing who have never had symptoms.
Many are worried that continuing to eat red meat could trigger a future reaction.
But a positive test alone does not mean someone has alpha-gal syndrome.
A recent CDC study found that nearly 1 in 4 adults tested in five tick-heavy states had detectable alpha-gal IgE.
In Tennessee, the rate was 21.5%.
These were mostly healthy blood donors, not patients with known allergic reactions.
This highlights an important difference:
↳ Sensitization: Alpha-gal IgE is detectable in the blood.
↳ Alpha-gal syndrome: Exposure to alpha-gal causes compatible symptoms.
If someone regularly eats beef, pork, lamb, or dairy without symptoms, they generally do not need to avoid those foods solely because a blood test is positive.
Unnecessary food avoidance can lead to:
↳ Anxiety around eating
↳ Nutritional restrictions
↳ Confusion about medications and vaccines
↳ An allergy diagnosis the patient may not actually have
Before diagnosing alpha-gal syndrome, we look for delayed symptoms after mammalian products:
↳ Hives or swelling
↳ Abdominal pain, vomiting, or diarrhea
↳ Wheezing or trouble breathing
↳ Dizziness or anaphylaxis
Symptoms often begin 2 to 6 hours after exposure.
That delay can make the connection easy to miss.
For someone with a positive test but no symptoms, the most useful preventive step is usually not automatically avoiding red meat.
It is preventing more tick bites.
Additional tick bites may increase alpha-gal IgE and may increase the risk of developing clinical reactions.
Use tick repellent.
Wear protective clothing outdoors.
Check your skin, clothing, children, and pets after spending time outside.
A positive allergy test shows immune recognition.
It does not always prove clinical allergy.
Have you ever been told to avoid a food because of a positive test, even though you had been eating it safely?
|
|
Scooped by
Gilbert C FAURE
June 1, 10:31 AM
|
Mast Cell–Neuronal Crosstalk in Allergic Defense The schematic illustrates how the immune and nervous systems cooperate through mast cell–neuronal pathways, supporting the “toxin hypothesis.” This concept suggests that allergic responses evolved as protective mechanisms to detect and avoid harmful substances. The process begins when environmental antigens breach epithelial barriers and are captured by dendritic cells, initiating a type 2 immune response. During the sensitization phase, dendritic cells activate T helper 2 (Th2) cells, which in turn stimulate B cells to produce antigen-specific IgE antibodies. These IgE molecules bind to mast cells, priming them for future encounters. Upon secondary exposure to the same antigen, mast cells become rapidly activated, releasing mediators such as leukotriene C4 (LTC4), which play a central role in signaling danger. Activated mast cells communicate with the nervous system through specific receptor-ligand interactions. Molecules like LTC4 bind to receptors such as CysLT2R, while other mediators including histamine and serotonin engage their respective receptors on sensory neurons. This interaction triggers neural pathways that transmit signals to the brain, integrating immune detection with behavioral responses. One key outcome of this crosstalk is antigen-driven avoidance behavior. Signals involving molecules such as GDF15 influence the central nervous system, prompting organisms to avoid harmful substances. This behavioral adaptation reduces further exposure to the antigen and helps protect against inflammation, particularly in the gastrointestinal tract. Different tissues exhibit specialized neuro-immune responses. Sensory neurons innervating the skin, gut, lungs, and mucosal surfaces mediate distinct allergic symptoms such as itching, sneezing, coughing, or gastrointestinal distress. These localized reflexes act as rapid defense mechanisms to expel or avoid harmful agents. At the molecular level, mast cells release a variety of mediators that interact with neuronal receptors, including histamine (H1R/H4R), serotonin (5-HT2/3R), and proteases (PAR1). Some signaling pathways remain incompletely understood, as indicated by unknown receptor-ligand pairs, highlighting areas for future research. Overall, mast cell–neuronal communication represents a sophisticated system linking immune detection to behavioral and physiological responses. This integration not only explains allergic symptoms but also underscores their potential evolutionary role in protecting the host from environmental toxins.
|
|
Scooped by
Gilbert C FAURE
May 17, 4:16 AM
|
Allergy clinic looks simple.
It rarely is.
What people see
↳ Skin testing
↳ Patch testing
↳ Food challenges
↳ Allergy shots
↳ Biologics
What they do not see
↳ Sorting out whether a reaction was IgE-mediated, delayed, irritant, infectious, mast cell-related, bradykinin-mediated, or not allergy at all
↳ Explaining why a positive test does not always mean clinical allergy
↳ Rebuilding trust after broad food panels turn tolerated foods into sources of anxiety
↳ Reviewing ingredient lists, cofactors, timing, and symptom patterns in detail
↳ Figuring out whether “sinus allergy” is allergic rhinitis, vasomotor rhinitis, reflux, chronic sinus disease, or something else
↳ Deciding when hives are spontaneous urticaria and when swelling may be hereditary angioedema, ACE inhibitor angioedema, or another non-histamine process
↳ Recognizing when the story fits alpha-gal, especially when reactions are delayed and the timing feels “off”
↳ Working through drug allergy labels that have followed patients for years
↳ Sorting eczema from allergic contact dermatitis, then using patch testing when the story fits
↳ Explaining why flushing is not always allergy, swelling is not always angioedema, and eczema is not always food driven
↳ Figuring out whether “uncontrolled asthma” is persistent airway inflammation, poor inhaler technique, adherence issues, rhinitis, reflux, vocal cord dysfunction, or the wrong diagnosis altogether
↳ Working up recurrent sinus, lung, or skin infections and asking whether the problem is allergy, immune deficiency, or both
↳ Evaluating for antibody deficiency or other immune problems when the infection history does not add up
↳ Prior authorizations, school forms, biologic renewals, and portal messages in between visits
↳ Helping patients unlearn years of misinformation from social media, panel testing, and vague “sensitivity” reports
That is the part people miss.
A good allergy visit is not just about finding a trigger.
It is about asking better questions.
It is about narrowing a differential.
It is about knowing when the answer is allergy, and when it is not.
A big part of this specialty is not diagnosing more allergy.
It is ruling it out correctly.
And honestly, that is where a lot of the value lives.
Because the right diagnosis does two things:
↳ It finds what truly needs treatment
↳ It frees patients from avoiding things they were never actually allergic to
That can mean fewer false labels.
Less fear.
Less unnecessary restriction.
And better care.
Allergy-immunology sits at a strange intersection of detective work, pattern recognition, patient education, skin disease, airway disease, swelling disorders, immune evaluation, and long-term management.
It looks lighter from the outside than it really is.
Clinical allergists know otherwise.
What do you think is the most misunderstood part of allergy practice? | 14 comments on LinkedIn
|
|
Scooped by
Gilbert C FAURE
March 21, 5:42 AM
|
📣 Allergies : une spécialité médicale, pas un terrain pour les pratiques non scientifiques
Sur les réseaux sociaux, on voit fleurir de nombreuses « techniques » présentées comme des solutions miracles pour comprendre ou soigner les allergies.
Elles se parent souvent d’un discours séduisant, rassurant, pseudo‑scientifique… et elles ciblent particulièrement les personnes perdues face à leurs symptômes.
Le problème, c’est que ces approches ne reposent sur aucune base médicale.
Leur discours, souvent construit sur des concepts flous ou invérifiables, peut représenter un véritable danger pour les personnes allergiques.
Les allergies ne sont ni une intuition, ni une énergie, ni une impression.
Ce sont des maladies du système immunitaire, qu’elles soient immédiates (médiation IgE) ou retardées (médiation cellulaire).
Elles déclenchent une cascade de réactions immunitaires complexes, qui n’ont absolument rien à voir avec des manipulations symboliques, des gestes approximatifs ou des méthodes sans fondement scientifique.
🩺 L’allergologie est une spécialité médicale reconnue comme telle depuis 2017, fondée sur :
• des tests validés
• des protocoles rigoureux
• une compréhension croissante des mécanismes immunitaires mis en jeu
• des traitements efficaces et sécurisés
S’éloigner de cette expertise, c’est prendre le risque :
– d’un mauvais diagnostic
– d’un retard de prise en charge
– d’une exposition à des risques non maîtrisés
– d’une aggravation des symptômes
🎯 Pour les allergies, la sécurité passe par la science.
Consulter un professionnel formé, c’est se protéger.
Faire confiance à des méthodes non validées, c’est le danger dont certains n’ont pas conscience. Surfer sur la détresse des personnes allergiques a coup de séances coûtant parfois une blinde est- ce bien raisonnable ?
Bien sûr, d’autres spécialités connaissent aussi ces mêmes problèmes !!
|
|
Scooped by
Gilbert C FAURE
February 11, 4:07 AM
|
Is IgE really just the antibody of allergy — or a core pillar of human immunity?
A seminal review in Frontiers in Immunology challenges the idea that IgE is merely pathologic. Instead, it argues that IgE evolved as a protective immune mechanism against multicellular parasites, particularly helminths — with major implications for immune-compromised patients.
Key insights:
• IgE-driven Th2 responses are physiologic in helminth infection, not aberrant
• Most environmental allergens belong to the same protein families targeted during parasitic infection
• Parasite-specific IgE correlates with resistance to reinfection in schistosomiasis, hookworm, and ascariasis
• Helminths actively regulate host immunity, shaping tolerance via IL-10, TGF-β, and IgG4
Why this matters in immune-compromised states
In conditions such as advanced HIV, malignancy, chemotherapy, or immunosuppressive therapy:
• IgE responses may dominate as other immune pathways fail
• Cross-reactive IgE can mimic allergy, malignancy, or autoimmune disease
• Loss of regulatory balance may convert protective IgE into clinically significant inflammation
• Atypical eosinophilia, tissue infiltration, or mass-like immune phenomena may result
This framework helps explain why immune-compromised patients often present with non-classic, confusing inflammatory patterns — and why parasite-derived antigens can be protective in healthy hosts yet harmful in immune-dysregulated ones.
Takeaway:
IgE may represent an ancient survival system that becomes maladaptive only when immune regulation breaks down. Understanding this axis is critical for allergy, parasitology, vaccine development — and modern clinical immunology.
📄 Helminth allergens, parasite-specific IgE, and its protective role in human immunity (Frontiers in Immunology)
Authors:
Colin Matthew Fitzsimmons • Franco Harald Falcone • David William Dunne
(University of Cambridge | University of Nottingham)
#Immunology #IgE #Immunocompromised #ClinicalImmunology #Allergy #Parasitology #TranslationalMedicine #GlobalHealth
|
|
Scooped by
Gilbert C FAURE
January 4, 12:57 PM
|
Allergies alimentaires : de grandes disparités à l’échelle mondiale
L’article proposé par la WAO Sur un projet international mené auprès de 150 centres dans 50 pays met en évidence de grandes différences dans la prise en charge des allergies alimentaires selon les pays,que ce soit dans les possibilités diagnostiques ou le prix des traitements d’urgence .
-Le test cutané est utilisé mais certaines régions d’Afrique et d’Asie y ont un accès inégal .
- les IgE spécifiques, souvent utilisées en alternative.
-L’immunothérapie orale est surtout pratiquée en Europe occidentale, puis en Amérique du Nord, en Europe du Sud et en Europe du Nord. L’omalizumab est également utilisé notamment en Europe occidentale, en Amérique du Nord, en Asie de l’Est et en Océanie.
-La sévérité des réactions varie fortement selon les zones géographiques.
L’utilisation d’adrénaline va de 3 % en Asie du Sud à 50 % en Afrique australe, avec des taux importants en Asie de l’Est, en Asie occidentale, en Europe du Sud et en Amérique du Nord. La disponibilité de l’adrénaline elle-même est très variable selon les pays, et certains n’y ont pas accès aux auto‑injecteurs,
Allergènes :Avant 5 ans, le lait et l’œuf sont les allergènes les plus fréquents. Entre 5 et 11 ans, l’œuf >du lait, >l’arachide et des fruits à coque. Chez les adolescents, l’arachide le plus courant au niveau mondial, suivie des noix et des crustacés. Chez les adultes, les crustacés, les noix, l’arachide et le poisson sont les allergènes les plus souvent rapportés,
Ces résultats montrent que les allergies alimentaires représentent un enjeu mondial majeur, influencé par l’accès aux diagnostics, aux traitements, aux auto‑injecteurs d’adrénaline et aux soins d’urgence. Selon l’outil DEFASE, environ 3 % des patients pourraient être classés comme souffrant d’allergies alimentaires sévères, un taux comparable à celui observé dans l’asthme sévère réfractaire.
https://lnkd.in/ebF3d252
Cet article est très intéressant et engage à comparer les prix dans différents pays :
les tarifs hors assurance sont d’environ 1 000 à 3 000 dollars pour une admission aux urgences aux États‑Unis et 3 000 à 10 000 dollars pour une journée en soins intensifs, alors qu’en Thaïlande une journée de soins intensifs coûte hors assurance 900 à 2 700 euros, tandis qu’en France les coûts hospitaliers sont beaucoup plus faibles grâce à la prise en charge publique, mais peuvent devenir élevés pour les personnes sans aucune assurance
Aux USA les prix vont de 199 dollars pour le nouveau spray nasal d’adrenaline à près de 300 dollars pour le système parlant injectable. Et 600 euros pour le plus connu ( tarifs hors assurance ) En France il faut compter entre environ 62 et 91 euros pour deux dispositifs . , l’Assurance maladie rembourse 65 % du prix des auto‑injecteurs d’adrénaline et, dans la plupart des cas, les complémentaires santé prennent en charge le reste du coût.
|
|
Scooped by
Gilbert C FAURE
August 7, 2025 3:35 AM
|
"A blog about allergy, asthma & immunology"
|
|
Scooped by
Gilbert C FAURE
July 8, 2025 8:34 AM
|
8th July is World Allergy Day.
This article in Times Of India mentioned about our old study: Allergic diseases have significant impact on the quality-of-life, social life, and economy. Inadequate knowledge about allergic testing further add on to the burden of the disease. Reposting this for awareness about harmonisation of allergens testing.
The clinical suspicion of allergic sensitization can be confirmed by demonstrating the presence of allergen specific immunoglobulin-E (IgE) antibodies in vivo (skin prick test) or in vitro methods (Blood tests: FEIA, ELISA, CRD etc). There is a lack of well-defined protocols and guidelines for the diagnosis of respiratory allergy testing in India. Therefore, the evidence-based guidelines is the need of the hour.
|
|
Scooped by
Gilbert C FAURE
June 12, 2025 11:14 AM
|
On behalf of the Allergy Diagnosis Working Group Of the French Society of Allergology (GTBA – SFA), I’m proud to have contributed to the dissemination of the EAACI guidelines on the diagnosis of IgE-mediated Food Allergy within the French-speaking medical community:
- French translation of the food allergy guidelines on diagnosis for a special issue of the French Allergy Journal (RFA) dedicated to Food Allergy: https://lnkd.in/dBAxRQXC
- Plenary presentation at the French National Congress of Allergology (CFA 2025) in Paris with a focus on methodology based on the accuracy of diagnostic tests to understand the recommended diagnostic approach: https://lnkd.in/dGAEc7PK
- Presentation at a workshop/controversy at the 30th National Congress of AMAFORCAL in Rabat, Morocco
Julien Goret, Joana Vitte, Alexandra Santos, MD PhD, Société Française d'Allergologie - SFA, European Academy of Allergy and Clinical Immunology - EAACI, @GTBA, Youness EL GUEDDARI, Elleni-Sofia Vaia
|
|
Scooped by
Gilbert C FAURE
September 8, 2024 11:47 AM
|
|
|
Scooped by
Gilbert C FAURE
March 9, 2023 7:53 AM
|
Un consortium international (*), comprenant le laboratoire de génétique humaine des maladies infectieuses, à l’Institut Imagine (Inserm, APHP, Université Paris Cité), vient de publier une nouvelle étude dans la revue Journal of Experimental Medicine. Les médecins et chercheurs ont identifié un nouveau gène en cause dans le syndrome « hyper IgE », responsable d’allergies et d’eczéma sévères.
|
|
|
Scooped by
Gilbert C FAURE
October 7, 4:51 AM
|
More peanuts in pregnancy ≠ less peanut allergy in babies.
A major new NEJM trial just tested this.
For years, families have asked whether eating more peanut during pregnancy could lower their baby’s risk of developing peanut allergy.
Now we have much better data.
A new randomized trial included more than 2,100 pregnancies in families at higher risk for allergic disease.
One group was asked to eat at least:
🥜 60 peanuts per week
🥚 6 eggs per week
They continued this during pregnancy and through the first 4 months after delivery while breastfeeding.
The comparison group ate substantially less peanut and egg.
At 1 year of age, the babies were evaluated for IgE-mediated peanut or egg allergy.
The result?
7.8% of babies in the high peanut-and-egg group developed peanut or egg allergy.
8.4% in the comparison group did.
That difference was not statistically significant.
So eating substantially more peanut and egg during pregnancy and breastfeeding did not prevent food allergy in the baby.
But here is the important part:
This does not mean peanut exposure does not matter.
The stronger evidence for prevention comes after the baby is born.
Early introduction of peanut into an infant’s diet, followed by regular ingestion, can reduce the risk of developing peanut allergy.
So the practical message for parents is:
👉 You generally do not need to avoid peanut or egg during pregnancy just to prevent allergy.
👉 Eating extra peanut during pregnancy has not been shown to prevent peanut allergy.
👉 Introducing allergenic foods at the right time during infancy still matters.
Food allergy prevention may be less about what mom eats during pregnancy and more about when the baby starts eating the food.
Were you ever told to eat more, or avoid, certain foods during pregnancy because of allergy risk?
|
|
Scooped by
Gilbert C FAURE
August 18, 8:42 AM
|
If your food sensitivity panel flagged 20 foods,
the problem may be the test - not your diet.
I see patients who arrive with pages of results showing “high” IgG to milk, wheat, egg, corn, soy, and dozens of other foods.
Naturally, they ask:
“Do I need to stop eating all of these?”
Usually, no.
Here is what is important to understand.
IgG is not the antibody we use to diagnose a typical food allergy.
Food allergy is usually evaluated with the history plus targeted testing for IgE, using skin testing or blood testing when appropriate.
Sometimes an oral food challenge is needed to confirm the diagnosis.
Food-specific IgG tells us something very different.
↳ It often means your immune system has been exposed to that food.
↳ Finding IgG against a food does not prove that the food is causing your symptoms.
↳ IgG4 responses may even be associated with immune tolerance rather than allergy.
That is why major allergy organizations recommend against using food IgG or IgG4 panels to diagnose food allergy or food intolerance.
And there is a real downside to these tests.
A report may label 20, 30, or even 50 foods as problematic.
Then someone starts removing:
Milk.
Wheat.
Egg.
Soy.
Nuts.
Fruit.
Vegetables.
Suddenly the diet becomes extremely limited, even though many of those foods were being eaten without any problem.
For children, unnecessary restriction can be especially concerning because they need enough calories, protein, vitamins, and minerals for normal growth.
So if a test tells you that you are “sensitive” to a long list of foods, ask an important question:
What exactly is this test measuring?
A positive antibody result is not automatically a diagnosis.
Your symptoms, the timing of the reaction, the food involved, and the right type of testing all matter.
Sometimes the best answer after an IgG panel is not to remove more foods.
It is to put foods back.
Have you ever been told to avoid a long list of foods based on an IgG test?
|
|
Scooped by
Gilbert C FAURE
June 13, 2:04 PM
|
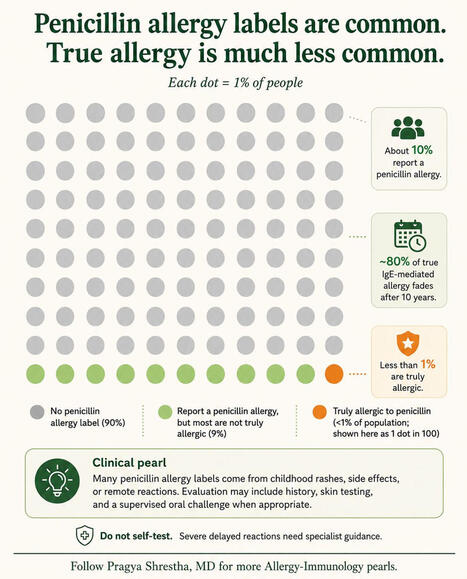
About 1 in 10 people carry a penicillin allergy label.
But less than 1% are truly allergic.
That gap matters.
Because a penicillin allergy label can mean:
↳ broader antibiotics
↳ more side effects
↳ higher costs
↳ fewer first-line treatment options
Many labels come from childhood rashes, GI side effects, or reactions that happened decades ago.
And about 80% of true IgE-mediated penicillin allergy fades after 10 years.
This does not mean self-test at home.
It means the label may be worth revisiting with an allergist.
Sometimes better care starts by removing the wrong diagnosis.
|
|
Scooped by
Gilbert C FAURE
May 17, 4:54 AM
|
Allergy-Immunology is moving past diagnosis-first treatment.
The question now is which pathway fits.
What started with anti-IgE has expanded into a much broader therapeutic era:
anti-IL-5, anti-IL-4Rα, anti-TSLP, anti-IL-13, anti-IL-31RA, BTK inhibition, kallikrein pathway targeting, FXIIa inhibition, and RNA-targeted therapy.
This timeline shows how quickly the field has evolved.
A few things stand out:
🔹 Asthma helped lead the way
From Xolair to anti-IL-5 therapies to Tezspire, asthma has been one of the major drivers of targeted treatment development in our field.
🔹 Type 2 disease is not just one disease
The same inflammatory pathways show up across asthma, atopic dermatitis, CRSwNP, eosinophilic disease, and more, but not in identical ways.
🔹 Hereditary angioedema is a great example of precision medicine
HAE management has expanded well beyond older paradigms, with both prophylactic and on-demand targeted therapies now available.
🔹 We are moving beyond monoclonal antibodies alone
This is no longer just a biologics story.
It is also a story of oral targeted therapy, pathway-specific inhibition, and RNA-directed treatment.
🔹 Mechanism matters more than ever
As options grow, choosing therapy becomes less about “what is available” and more about:
↳ phenotype
↳ endotype
↳ comorbid disease
↳ age/indication
↳ convenience
↳ access and coverage
For trainees, this timeline is a reminder of how fast the field is moving.
For clinicians, it is a reminder of how much treatment selection has changed in just two decades.
And honestly, we are probably still early.
Which approval do you think most changed practice in Allergy-Immunology?
|
|
Scooped by
Gilbert C FAURE
May 13, 3:38 AM
|
👩⚕️ One of the biggest mistakes I see in allergy care:
broad food panel testing.
If you come to my clinic expecting a 50-food scratch test on your child’s back, you are probably going to be disappointed.
Here’s why:
1️⃣ Skin prick testing without a history is a guessing game
A positive wheal (that little bump on the skin) means sensitization.
It does not automatically mean your child will react if they eat that food.
Without a credible reaction history to guide us, broad skin testing creates false alarms - not answers.
2️⃣ IgE blood panels have the same problem
A positive specific IgE does not equal food allergy.
It can simply mean sensitization.
When these panels are ordered without the right clinical context, the positive predictive value is low. We end up managing numbers on a lab report instead of treating the patient in front of us.
3️⃣ IgG “sensitivity” panels are a different category - and even less supported
IgG to foods usually reflects exposure and normal immune tolerance.
No major allergy society recommends IgG food panels to diagnose food allergy or food sensitivity.
A positive IgG to egg usually just means… your child eats egg.
It tells me more about what they had for dinner than what is actually making them sick.
4️⃣ These tests create fear around safe foods
Test 50 foods without a good history, and you are almost guaranteed to get positives.
Then families are left avoiding nutritious foods for months or years with no real reaction history to justify it.
I’ve seen children unnecessarily avoiding: Egg, Tree nuts, Wheat, Dairy
…all because of a “number” on a page.
5️⃣ They delay the right diagnosis
This is the part that bothers me most.
When we chase panel results, we can miss what is actually going on.
Chronic GI symptoms may be: FPIES, EoE, Celiac, reflux, constipation, or something non-immunologic entirely
Eczema has many drivers beyond food.
Broad panels do not clarify the picture - they often cloud it.
✅ What I do instead
I start with a detailed history. Always.
Then, if needed, I order:
🔹 Targeted skin testing
🔹 Targeted specific IgE testing
🔹 Oral food challenge when we need a real answer
The story a parent tells me in clinic is often worth far more than 50 wheals on a back. | 14 comments on LinkedIn
|
|
Scooped by
Gilbert C FAURE
February 11, 4:11 AM
|
ALLERGIC REACTION
Immunology & Medical Laboratory Science
1. Introduction
An allergic reaction is a common immunological phenomenon encountered in clinical practice. It represents an inappropriate and exaggerated immune response to substances that are ordinarily harmless. While many allergic reactions are mild, some can be severe and life-threatening, emphasizing the importance of understanding their mechanism, diagnosis, and laboratory relevance.
2. Definition
An allergic reaction is an immunologically mediated hypersensitivity response that occurs when a previously sensitized individual is re-exposed to a specific allergen, leading to activation of immune cells and release of inflammatory mediators.
Most allergic reactions are classified as Type I (IgE-mediated) hypersensitivity reactions.
3. Allergens and Routes of Exposure
3.1 Common Allergens
Allergens are substances capable of inducing allergic reactions in susceptible individuals.
•Inhaled allergens: pollen, dust mites, mold spores, animal dander
•Ingested allergens: peanuts, shellfish, eggs, milk, drugs
•Injected allergens: insect stings, injectable drugs, blood products
•Contact allergens: latex, cosmetics, metals (nickel), detergents
3.2 Routes of Entry
•Respiratory tract
•Gastrointestinal tract
•Skin
•Bloodstream
The route of entry influences the clinical presentation.
4. Immunological Mechanism of Allergic Reaction
Allergic reactions occur in two main phases:
4.1 Sensitization Phase (Primary Exposure)
This phase occurs during the first exposure to the allergen and does not produce clinical symptoms.
Steps involved:
1. The allergen enters the body.
2. Antigen-presenting cells (APCs) process the allergen.
3. APCs present the antigen to CD4⁺ T helper (Th2) cells.
4. Th2 cells release cytokines such as IL-4 and IL-13.
5. These cytokines stimulate B cells to produce IgE antibodies.
6. IgE binds to high-affinity FcεRI receptors on mast cells and basophils.
The individual is now sensitized.
4.2 Effector Phase (Re-exposure)
Upon subsequent exposure to the same allergen:
1. The allergen binds to IgE on mast cells.
2. Cross-linking of IgE occurs.
3. Mast cells undergo degranulation.
4. Inflammatory mediators are released, producing clinical symptoms.
5. Chemical Mediators Released
5.1 Pre-formed Mediators
•Histamine: causes vasodilation, itching, edema, and bronchoconstriction
5.2 Newly Synthesized Mediators
•Leukotrienes: bronchoconstriction and mucus secretion
•Prostaglandins: inflammation and pain
•Cytokines: recruit eosinophils and other inflammatory cells
These mediators are responsible for the acute and late-phase reactions.
#MedicalLaboratoryScience
#Immunology
#AllergicReactions
#PatientSafety
#LaboratoryMedicine
#HealthcareEducation
#MLS
|
|
Scooped by
Gilbert C FAURE
January 8, 4:58 AM
|
💡 𝐖𝐡𝐚𝐭 𝐢𝐟 𝐰𝐞 𝐜𝐨𝐮𝐥𝐝 𝐭𝐞𝐚𝐜𝐡 𝐁 𝐜𝐞𝐥𝐥𝐬 𝐭𝐨 "𝐟𝐨𝐫𝐠𝐞𝐭" 𝐈𝐠𝐄??
📖 In a recent Science Immunology study, long-term allergic memory was mapped 𝐧𝐨𝐭 𝐭𝐨 𝐈𝐠𝐄 cells, but mainly to 𝐈𝐠𝐆𝟏⁺ 𝐦𝐞𝐦𝐨𝐫𝐲 𝐁 𝐜𝐞𝐥𝐥𝐬 with a type-2 imprint, primed to change from IgG1 to IgE when the allergen returns (recall).
🧬 𝐃𝐢𝐬𝐜𝐨𝐯𝐞𝐫𝐢𝐧𝐠 𝐓-𝐩𝐨𝐰𝐞𝐫
🔁 𝐓-𝐜𝐞𝐥𝐥 𝐜𝐲𝐭𝐨𝐤𝐢𝐧𝐞𝐬 as gatekeepers: 𝐈𝐋-𝟒/𝐈𝐋-𝟏𝟑 drive this switch at recall; dampen those cues and IgE recall drops. Notably, exposing these memory B cells to allergen without IL-4 can make them “𝐟𝐨𝐫𝐠𝐞𝐭” 𝐭𝐡𝐞 𝐈𝐠𝐄 𝐩𝐫𝐨𝐠𝐫𝐚𝐦 and default to 𝐈𝐠𝐆, even when IL-4 reappears later.
🧪 𝐋𝐞𝐭’𝐬 𝐥𝐞𝐚𝐫𝐧 (𝐧𝐞𝐮𝐫𝐨)𝐈𝐦𝐦𝐮𝐧𝐨𝐥𝐨𝐠𝐲 — 𝐀𝐥𝐥𝐞𝐫𝐠𝐲 𝐛𝐚𝐬𝐢𝐜𝐬
• 𝐀𝐥𝐥𝐞𝐫𝐠𝐲 = an excessive immune response to a 𝐡𝐚𝐫𝐦𝐥𝐞𝐬𝐬 𝐚𝐧𝐭𝐢𝐠𝐞𝐧 (𝐚𝐥𝐥𝐞𝐫𝐠𝐞𝐧) recognized by 𝐈𝐠𝐄 𝐚𝐧𝐭𝐢𝐛𝐨𝐝𝐢𝐞𝐬.
• 𝐈𝐠𝐄 binds to its high-affinity receptor (𝐅𝐜ε𝐑𝐈) on 𝐦𝐚𝐬𝐭 𝐜𝐞𝐥𝐥𝐬 and 𝐛𝐚𝐬𝐨𝐩𝐡𝐢𝐥𝐬; upon re-exposure, the allergen cross-links IgE → 𝐝𝐞𝐠𝐫𝐚𝐧𝐮𝐥𝐚𝐭𝐢𝐨𝐧 (histamine release…) → hives, wheezing, anaphylaxis.
• 𝐈𝐠𝐆𝟏⁺ 𝐦𝐞𝐦𝐨𝐫𝐲 𝐁 𝐜𝐞𝐥𝐥𝐬 store the “recipe”; with 𝐈𝐋-𝟒/𝐈𝐋-𝟏𝟑 they can 𝐜𝐥𝐚𝐬𝐬-𝐬𝐰𝐢𝐭𝐜𝐡 𝐛𝐚𝐜𝐤 𝐭𝐨 𝐈𝐠𝐄, helping explain relapses.
🧬 𝐂𝐡𝐚𝐥𝐥𝐞𝐧𝐠𝐢𝐧𝐠 𝐭𝐡𝐞 𝐩𝐚𝐫𝐚𝐝𝐢𝐠𝐦: the immune system is not a defense system… it is much more than that.
🔗 𝐑𝐞𝐚𝐝 𝐭𝐡𝐞 𝐩𝐚𝐩𝐞𝐫 𝐢𝐧 𝐒𝐜𝐢𝐞𝐧𝐜𝐞 𝐈𝐦𝐦𝐮𝐧𝐨𝐥𝐨𝐠𝐲: https://lnkd.in/d5zeXDDX
🔖 Save for later. 🔁 Share with your science-curious friends.
#immunology #allergy #IgE #Bcells #IL4 #IL13 #mastcells #ScienceImmunology #ChallengingTheParadigm
|
|
Scooped by
Gilbert C FAURE
October 2, 2025 2:42 AM
|
✨✨✨ Nous sommes très heureux d’annoncer la publication des résultats de #AllergenChipChallenge dans la prestigieuse revue Journal of Allergy and Clinical Immunology https://lnkd.in/e_Mn4c73
Ce projet est le fruit d’un travail collectif remarquable, qui a rassemblé cliniciens, biologistes, data scientists et chercheurs autour d’un objectif commun : mieux comprendre et interpréter les données issues des puces à allergènes et de générer par #MachineLearning un #algorithme de prédiction des #allergies à partir d'un profil d'IgE et de données cliniques.
La base de données et l'algorithme sont en libre accès au bénéfice de la recherche et des patients allergiques.
Un grand merci 🙏 à Joana Vitte et Pascal Demoly pour avoir initié ce passionnant projet, la Société Française d'Allergologie - SFA, AllergoBioNet, Health Data Hub et Bpifrance pour leur soutien déterminant, ainsi qu’à toutes celles et ceux qui ont contribué à rendre cette aventure possible Guillaume Martinroche Amir Guemari Pol André APOIL Isabella Annesi-Maesano Eric Fromentin @Laurent Guilleminault Davide Caimmi Caroline Klingebiel @Céline Beauvillain Alain Didier Jeremy Corriger Lauriane Armand Agathe Delaune Trustii.io Naama BAK CHU de Bordeaux.
➡️ Ces avancées montrent la puissance de la collaboration et de l’ouverture des données pour faire progresser la recherche en allergologie et au-delà. Le projet continue.
#OpenData #Database #Allergie #Allergologie #Allergy #Immunologie #Recherche #IA #MachineLearning #SFA #GTESIA
|
|
Scooped by
Gilbert C FAURE
July 19, 2025 8:06 AM
|
|
|
Scooped by
Gilbert C FAURE
July 7, 2025 5:48 AM
|
🔬 Et si on arrêtait de réduire les mastocytes à l’IgE ?
Pendant des décennies, la triade « mastocyte - IgE - allergie » a structuré notre compréhension des réactions d’hypersensibilité immédiate.
Mais aujourd’hui, nous savons que cette vision est incomplète.
📌 L’article-clé paru en janvier 2025 (Int J Mol Sci. 26(3):927) montre que les mastocytes (MC) disposent d’un répertoire de récepteurs bien plus vaste que FcεRI, et que leur activation peut suivre des voies non-IgE, dites "pseudoallergiques", via des récepteurs comme MRGPRX2.
💥 Résultat ?
➡️ Des réactions cliniques rapides, sans sensibilisation préalable ni IgE spécifique détectable.
➡️ Une dégranulation induite par des médicaments (fluoroquinolones, vancomycine, morphine...), des neuropeptides (substance P), ou des stimuli physiques.
➡️ Une inflammation neurogène amplifiée par l’interaction étroite entre MC et terminaisons nerveuses périphériques.
🧠 Les implications dépassent largement le champ allergologique classique :
- Urticaire chronique, dermatite atopique, prurit rebelle
- Syndrome d’activation mastocytaire (MCAS)
- Rosacée, asthme non contrôlé, inflammation cérébrale...
💡Comprendre MRGPRX2, c’est élargir notre cadre diagnostique et thérapeutique.
👉 De nouveaux traitements ciblent déjà cette voie : antagonistes de MRGPRX2, cannabinoïdes non-psychoactifs (PEA, CBD), anticorps anti-Siglec-8...
🧬 Les mastocytes sont bien plus que des effecteurs allergiques.
Ils sont au carrefour de l’immunité, du système nerveux et des interfaces barrière.
Et si l’on actualisait nos réflexes cliniques ?
Source : https://lnkd.in/etTeyKBh
Dr Lucie WETCHOKO
|
|
Scooped by
Gilbert C FAURE
October 16, 2024 10:11 AM
|
Comparable production of IL-4 by both TFR and TFH cells. A helper role for TFR cells in food allergy was previously demonstrated with the use of TFR cell–deficient Foxp3CreBcl6fl/fl (Bcl6FC) mice (18).
|
|
Scooped by
Gilbert C FAURE
April 18, 2023 12:06 PM
|
Basophils bind IgE via FceRI-alpha beta gamma 2, which they uniquely share only with mast cells. In doing so, they can rapidly release mediators that are hallmark of allergic disease. This fundamental similarity, along with some morphological features shared by the two cell types, has long brought into question the biological significance that basophils mediate beyond that of mast cells. Unlike mast cells, which mature and reside in tissues, basophils are released into circulation from the bone marrow (constituting 1% of leukocytes), only to infiltrate tissues under specific inflammatory conditions. Evidence is emerging that basophils mediate non-redundant roles in allergic disease and, unsuspectingly, are implicated in a variety of other pathologies [e.g., myocardial infarction, autoimmunity, chronic obstructive pulmonary disease, fibrosis, cancer, etc.]. Recent findings strengthen the notion that these cells mediate protection from parasitic infections, whereas related studies implicate basophils promoting wound healing. Central to these functions is the substantial evidence that human and mouse basophils are increasingly implicated as important sources of IL-4 and IL-13. Nonetheless, much remains unclear regarding the role of basophils in pathology vs. homeostasis. In this review, we discuss the dichotomous (protective and/or harmful) roles of basophils in a wide spectrum of non-allergic disorders.
|